Joint Pain
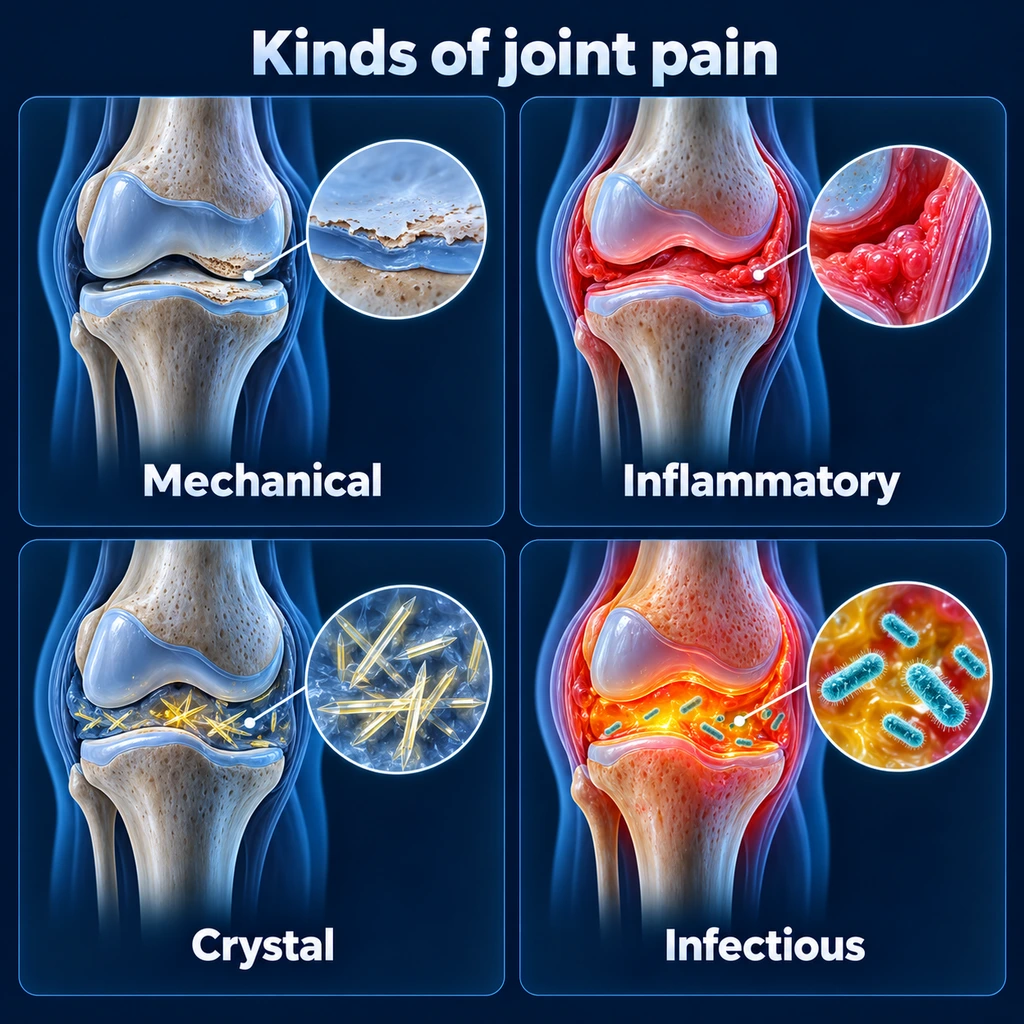

Table of Contents
Overview
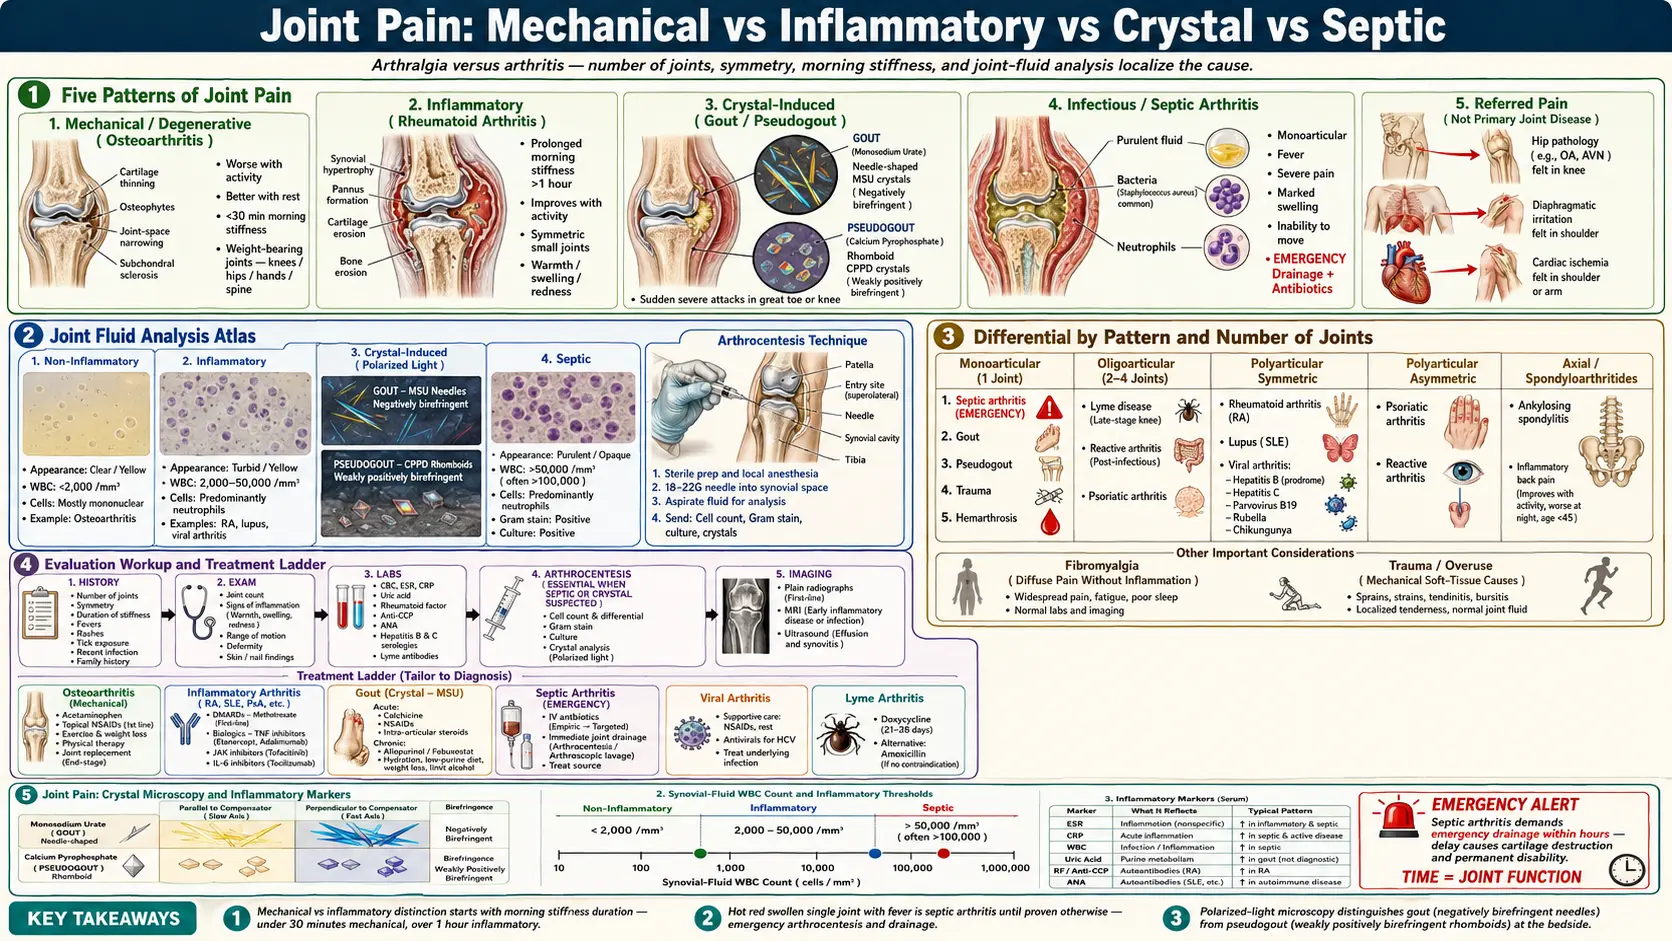
Joint pain, or arthralgia, is pain felt in one or more joints. When inflammation is also present — with swelling, warmth, redness, and stiffness — it is called arthritis. Joint pain can result from mechanical wear, autoimmune disease, infection, crystal deposition, or systemic illness. Viral infections, including hepatitis B and C, are well-recognized causes of acute polyarthralgia, and joint pain is often a feature of the prodromal phase of viral hepatitis.
Types of Joint Pain
- Mechanical (degenerative) — worse with activity, better with rest, minimal morning stiffness (under 30 minutes). Typical of osteoarthritis.
- Inflammatory — prolonged morning stiffness (over an hour), improves with activity, often with swelling, warmth, and redness. Typical of rheumatoid arthritis, lupus, psoriatic arthritis, and other autoimmune diseases.
- Crystal-induced — sudden, severe attacks. Gout (monosodium urate) and pseudogout (calcium pyrophosphate) are the prototypes.
- Infectious (septic) — usually monoarticular, with fever, severe pain, marked swelling, and inability to move the joint. A medical emergency.
- Referred pain — hip pathology felt in the knee; shoulder pain from diaphragmatic or cardiac sources.
Common Causes
- Osteoarthritis — the most common joint disease; affects knees, hips, hands, spine.
- Rheumatoid arthritis — symmetric small-joint polyarthritis with morning stiffness.
- Gout and pseudogout — acute monoarthritis, often in the great toe (gout) or knee (pseudogout).
- Septic arthritis — bacterial infection of a joint; requires emergency drainage and antibiotics.
- Viral arthritis — hepatitis B (often during the prodrome), hepatitis C, parvovirus B19, rubella, chikungunya.
- Lyme disease — late stages cause oligoarticular arthritis, often of the knee.
- Systemic lupus erythematosus — non-erosive symmetric arthritis.
- Psoriatic arthritis, ankylosing spondylitis, reactive arthritis — spondyloarthritides.
- Fibromyalgia — diffuse pain without joint inflammation.
- Trauma and overuse — sprains, strains, tendinitis, bursitis.
Evaluation
- History — number of joints involved, symmetry, duration of stiffness, fevers, rashes, recent infections, tick exposure, family history.
- Physical exam — joint count, signs of inflammation, range of motion, deformity, skin findings.
- Labs — complete blood count (CBC), erythrocyte sedimentation rate (ESR), C-reactive protein (CRP), uric acid, rheumatoid factor, anti-CCP, antinuclear antibody (ANA), hepatitis B and C serologies, Lyme antibodies as indicated.
- Joint aspiration — essential when septic arthritis or crystal disease is suspected. Send for cell count, Gram stain, culture, and crystal analysis.
- Imaging — plain radiographs first; magnetic resonance imaging (MRI) for early inflammatory disease, internal derangement, or infection; ultrasound for effusion and synovitis.
Management
- Treat the underlying cause.
- Acetaminophen and topical nonsteroidal anti-inflammatory drugs (NSAIDs) — first-line for mild osteoarthritis.
- Oral nonsteroidal anti-inflammatory drugs — effective for inflammatory and crystal arthritis but with gastrointestinal (GI), renal, and cardiovascular risk.
- DMARDs and biologics — methotrexate, tumor necrosis factor (TNF) inhibitors, JAK inhibitors, and others for rheumatoid arthritis and related diseases.
- Colchicine, allopurinol, febuxostat — for gout management.
- Antibiotics and joint drainage — for septic arthritis.
- Physical therapy and exercise — central to nearly all chronic joint conditions.
- Joint replacement — for end-stage osteoarthritis of hip and knee.
When to Seek Medical Care
- Single hot, red, swollen joint with fever — possible septic arthritis.
- Joint pain after significant trauma or injury.
- Joint pain with rash, oral ulcers, or systemic symptoms.
- Inability to bear weight or move the joint.
- Persistent pain or stiffness lasting more than two weeks.
Connections
- All Symptoms
- Arthritis
- Hepatitis B
- Fibromyalgia
- Hepatitis
- Lupus
- Lyme Disease
- Turmeric
- Osteoporosis
- Gout
- Hepatitis C
- Tendinitis
- Ankylosing Spondylitis
- Inflammatory Markers
- Uric Acid
- Cold Hands & Feet
- Peripheral Neuropathy
- Proline
- Bone Broth
- Shoulder Pain
- Muscle Cramps
- Neck Pain
- Herbs covered on this site that discuss this condition: Tart Cherry (Prunus cerasus) · Willow Bark (Salix alba) · Boneset
Key Research Papers
Historical Background
Joint disease has been described for thousands of years; gout was recognized by Hippocrates as "the unwalkable disease." The development of synovial fluid analysis in the mid-20th century, beginning with Daniel McCarty's identification of monosodium urate and calcium pyrophosphate crystals under polarized light microscopy in the 1960s, transformed the diagnosis of crystal arthropathies. The biologic revolution starting in the late 1990s with tumor necrosis factor inhibitors radically improved outcomes for rheumatoid arthritis and the spondyloarthritides.
Key Research Papers
- McInnes IB, Schett G. The pathogenesis of rheumatoid arthritis. New England Journal of Medicine. 2011;365(23):2205-2219. — doi:10.1056/NEJMra1004965
- Dalbeth N, Merriman TR, Stamp LK. Gout. The Lancet. 2016;388(10055):2039-2052. — doi:10.1016/s0140-6736(16)00346-9
- Margaretten ME, Kohlwes J, Moore D, Bent S. Does this adult patient have septic arthritis? JAMA. 2007;297(13):1478-1488. — doi:10.1001/jama.297.13.1478
- Hochberg MC, Altman RD, April KT, et al. American College of Rheumatology 2012 recommendations for the use of nonpharmacologic and pharmacologic therapies in osteoarthritis of the hand, hip, and knee. Arthritis Care & Research. 2012;64(4):465-474. — doi:10.1056/NEJMra1505557
- Aletaha D, Neogi T, Silman AJ, et al. 2010 Rheumatoid arthritis classification criteria: an ACR/EULAR collaborative initiative. Arthritis & Rheumatism. 2010;62(9):2569-2581. — doi:10.1136/ard.2010.138461
- Vassilopoulos D, Calabrese LH. Virally associated arthritis 2008: clinical, epidemiologic, and pathophysiologic considerations. Arthritis Research & Therapy. 2008;10(5):215. — doi:10.1186/ar2480
- Steere AC, Strle F, Wormser GP, et al. Lyme borreliosis. Nature Reviews Disease Primers. 2016;2:16090. — doi:10.1038/nrdp.2016.90
- McCarty DJ, Hollander JL. Identification of urate crystals in gouty synovial fluid. Annals of Internal Medicine. 1961;54:452-460. — doi:10.7326/0003-4819-54-3-452
Featured Videos