⚠ Evidence warning: Clinical trials or other evidence do not support the claims that low-dose naltrexone helps postural orthostatic tachycardia syndrome and the listed best-responder groups. This page keeps it as a report of what people, websites or other media say.
Low-Dose Naltrexone for Postural Orthostatic Tachycardia Syndrome (POTS)
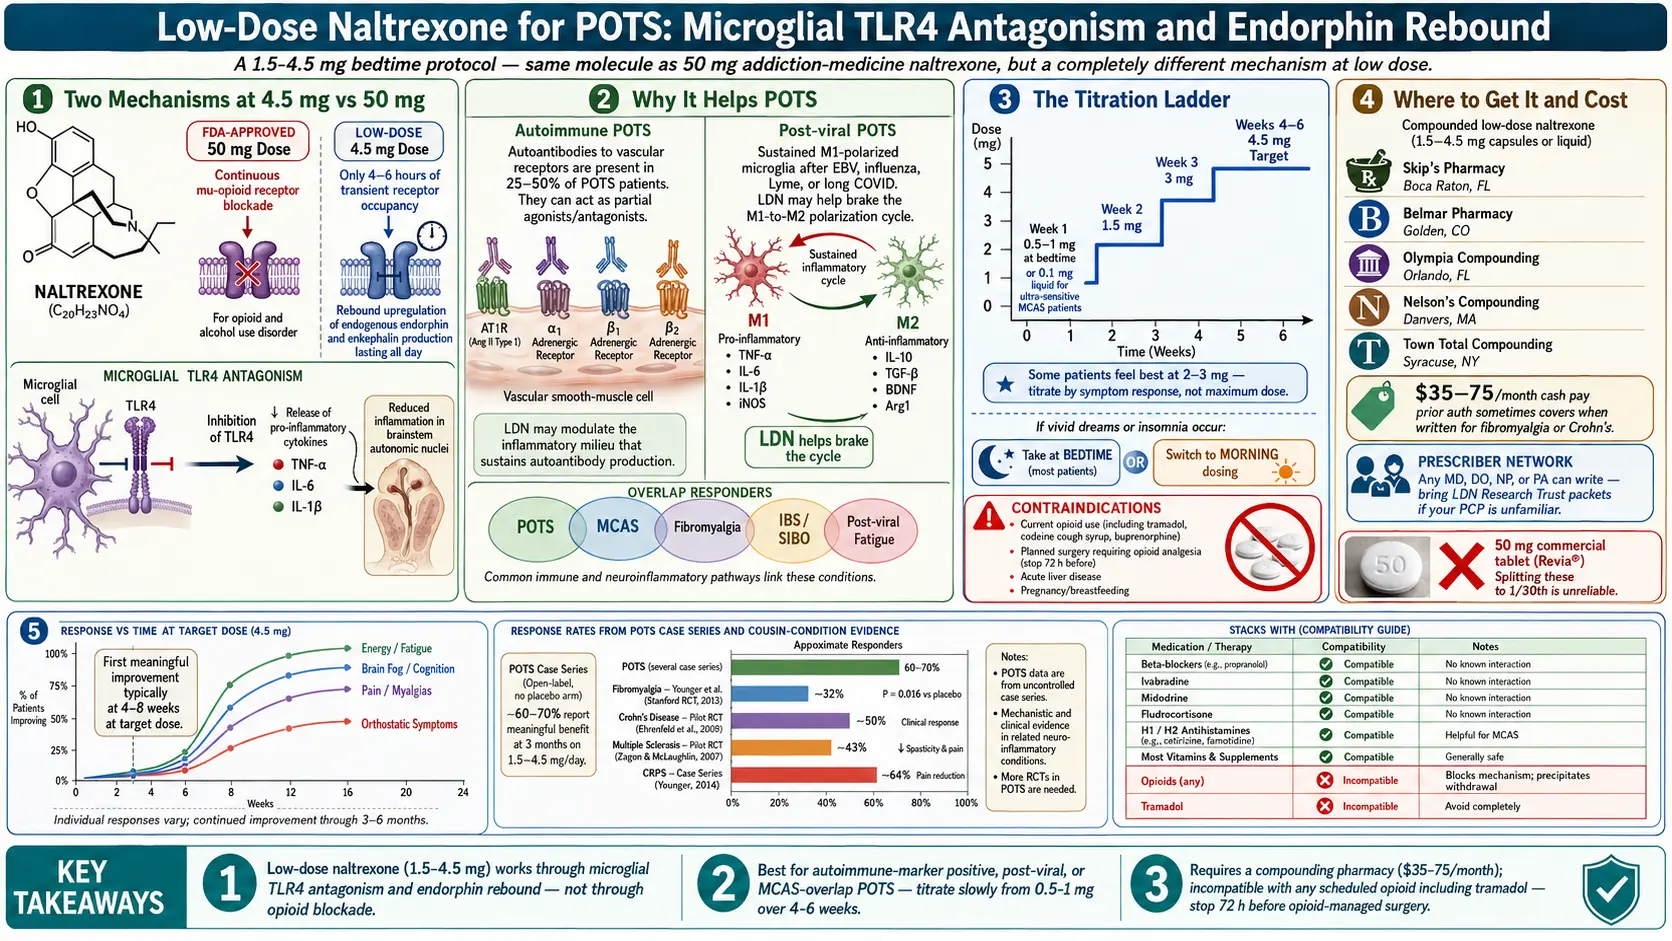
Table of Contents
- What Low Dose Naltrexone Actually Is
- Why It Helps Postural Orthostatic Tachycardia Syndrome
- What the Evidence Shows
- Who Low Dose Naltrexone Is Best For
- Who the Research Raises Concerns For
- Starting Protocol — Titration
- Side Effects and How to Manage Them
- Where Low Dose Naltrexone Comes From — Compounding Pharmacies
- How Patients Obtain a Prescription When the Doctor Is Not Familiar With It
- Combining Low Dose Naltrexone with Other Postural Orthostatic Tachycardia Syndrome Treatments
- Timeline of Expected Effects
- What “Worked” Looks Like
- Key Research Papers
- Connections
- Featured Videos
1. What Low Dose Naltrexone Actually Is
Naltrexone is a pure opioid receptor antagonist. At its U.S. Food and Drug Administration-approved dose of 50 mg daily, it’s used to treat opioid dependence and alcohol use disorder — it blocks the mu-opioid receptor continuously so that opioids and alcohol-driven endorphin reward produce no high.
At low doses (1.5–4.5 mg), the drug behaves almost nothing like its 50 mg self. Two completely different mechanisms take over:
- Transient opioid receptor blockade. At 4.5 mg, naltrexone occupies opioid receptors for only about 4–6 hours. That brief blockade fools the hypothalamus into thinking endorphins are in short supply, triggering a rebound upregulation of endogenous endorphin and enkephalin production that lasts all day.
- TLR4 antagonism on microglia. Researchers propose, largely from laboratory and animal work, that low-dose naltrexone inhibits toll-like receptor 4 on microglia in the central and peripheral nervous system, damping the release of pro-inflammatory cytokines (tumor necrosis factor-alpha, interleukin-6, interleukin-1-beta) that drive chronic neuroinflammation. A 2014 review by Younger and colleagues describes this as a possible anti-inflammatory action on microglial cells and calls the use of low-dose naltrexone for chronic disorders “still highly experimental”.
The opioid-receptor blockade itself does nothing therapeutic — it’s the rebound and the microglial effects that matter. That is why low dose naltrexone (LDN) doesn’t feel like anything when you take it; it isn’t working through an acute pharmacologic effect the way a beta-blocker does.
2. Why It Helps Postural Orthostatic Tachycardia Syndrome
Two strands of postural orthostatic tachycardia syndrome (POTS) research point directly at what low dose naltrexone does.
Autoimmunity. Roughly 25–50% of postural orthostatic tachycardia syndrome patients in screened cohorts carry functional autoantibodies against adrenergic and muscarinic receptors — most notably the AT1R (angiotensin II type 1 receptor), alpha-1 adrenergic receptor, and beta-1 and beta-2 adrenergic receptors. These antibodies act as partial agonists or antagonists and appear to drive at least a subset of the orthostatic dysregulation.
Neuroinflammation. Post-viral postural orthostatic tachycardia syndrome (post-EBV, post-influenza, post-Lyme, long COVID) shows features consistent with chronic low-grade neuroinflammation — persistent fatigue, brain fog, post-exertional malaise, sensitivity to light and sound. Microglia in a sustained M1-polarized state amplify autonomic dysregulation in the brainstem nuclei that govern heart rate and vascular tone.
Low dose naltrexone’s microglial TLR4 effect is a plausible brake on that inflammatory loop, and its endorphin-rebound effect modulates pain processing and autonomic balance. Case series and patient-reported outcomes describe improvements in fatigue, brain fog, orthostatic symptoms, pain, and mast cell overlap symptoms.
3. What the Evidence Shows
Honest summary: there are no large randomized controlled trials of low dose naltrexone for postural orthostatic tachycardia syndrome specifically. The evidence base is pieced together from three sources.
- Postural orthostatic tachycardia syndrome-specific case series are small chart reviews from one autonomic clinic. A 2023 review of 6 tilt-table-confirmed patients found that 3 reported improvement, 2 stopped for lack of perceived benefit, no side effects were reported, and questionnaire scores for fatigue, mood and autonomic symptoms changed inconsistently; the authors concluded that low dose naltrexone “has little evidence for efficacy” in postural orthostatic tachycardia syndrome. A 2025 chart review of 29 people with dysautonomia (including postural orthostatic tachycardia syndrome) found improvement in pain documented in 7 (24%), no significant change in autonomic symptom scores (COMPASS-31) at a follow-up visit 3 to 9 months later, and mild side effects in 5; most started at 1 mg daily. Open-label, no placebo arm — interpret accordingly.
- Small trials with mixed results in adjacent conditions. In fibromyalgia, a small crossover trial in 31 women (Younger and colleagues, Stanford, 2013) found a larger drop in pain on 4.5 mg than on placebo (28.8% vs 18.0%). Longer trials did not confirm it: the 12-month INNOVA trial in 98 women found no clinically meaningful pain benefit over placebo, with mostly mild side effects about as common on the drug as on placebo (68.8% vs 72%), and a 2026 re-analysis by researchers who ran an earlier fibromyalgia trial reports “lower efficacy than previously reported”. A 2014 review lists reports of reduced symptom severity in Crohn’s disease and multiple sclerosis as well, while noting that published trials have small samples and few replications. For complex regional pain syndrome the evidence is case reports (two patients in a 2013 report). All share mechanistic overlap with postural orthostatic tachycardia syndrome: neuroinflammation, autonomic involvement, chronic pain.
- Long COVID — a close cousin of post-viral postural orthostatic tachycardia syndrome. A 2026 systematic review found no randomized trials; four small before-and-after studies (155 people, 1 to 6 mg a day) showed moderate improvements in fatigue, brain fog and sleep and large improvements in pain and daily functioning, with low certainty of evidence and no serious adverse events in the two studies that assessed safety.
Low dose naltrexone is not a miracle drug for postural orthostatic tachycardia syndrome. Practitioners who prescribe it describe modest-to-moderate improvement, most useful when stacked with other postural orthostatic tachycardia syndrome treatments rather than used as a standalone therapy.
4. Who Low Dose Naltrexone Is Best For
Response is not uniform. Practitioners describe these subgroups as the most likely to benefit:
- Postural orthostatic tachycardia syndrome with autoimmune markers — positive AT1R or beta-1 adrenergic receptor antibodies, elevated antinuclear antibody (ANA), Hashimoto’s or other thyroid autoimmunity
- Post-viral postural orthostatic tachycardia syndrome — post-EBV, post-Lyme, post-influenza, long COVID
- Postural orthostatic tachycardia syndrome with prominent fatigue, brain fog, or post-exertional malaise
- Postural orthostatic tachycardia syndrome with mast cell activation syndrome (MCAS) overlap (mast cell activation)
- Postural orthostatic tachycardia syndrome with fibromyalgia overlap
- Postural orthostatic tachycardia syndrome with irritable bowel syndrome (IBS) or small intestinal bacterial overgrowth (SIBO) overlap (low dose naltrexone doubles as a gentle gut prokinetic at these doses)
5. Who the Research Raises Concerns For
- Current opioid use — naltrexone blocks opioid painkillers and can trigger acute withdrawal. This includes tramadol, codeine-containing cough syrups, and buprenorphine.
- Planned surgery requiring opioid pain management — practitioners describe stopping low dose naltrexone at least 72 hours before and restarting once opioids are no longer needed.
- Acute liver disease — the naltrexone label reports cases of hepatitis and clinically significant liver dysfunction, as well as transient liver enzyme rises, in people taking naltrexone at its standard dose; liver function tests (LFTs) measure these enzymes.
- Pregnancy or breastfeeding — insufficient data; most prescribers pause.
6. Starting Protocol — Titration
The classic target dose is 4.5 mg at bedtime, which practitioners describe reaching by slow titration. Starting at the target dose is the most common reason patients bounce off low dose naltrexone with vivid dreams or a symptom flare.
- Week 1: 0.5–1 mg at bedtime. Some practitioners start ultra-sensitive patients (common in mast cell activation syndrome and postural orthostatic tachycardia syndrome) at 0.1 mg — compounding pharmacies can provide a liquid for precise micro-dosing.
- Week 2: 1.5 mg at bedtime if tolerated.
- Week 3: 3 mg at bedtime.
- Weeks 4–6: 4.5 mg at bedtime — the target.
A meaningful minority of patients feel best on 2–3 mg and worse at 4.5 mg. Practitioners describe adjusting the dose by symptom response rather than by reaching the maximum dose, and moving to morning dosing when vivid dreams or insomnia persist — many patients report tolerating it equally well and some prefer it.
7. Side Effects and How to Manage Them
- Vivid dreams — the most common side effect; typically occurs in the first 1–2 weeks and fades. When it persists or is distressing, practitioners describe switching to morning dosing.
- Insomnia or sleep disruption — practitioners describe lowering the dose by 50% for a week or moving the dose to morning.
- Gastrointestinal (GI) upset — practitioners describe taking it with food; it usually resolves within days.
- Headache — practitioners describe reducing the dose by 50% for one week, then raising it again slowly.
- Transient symptom flare in the first week — fatigue, orthostatic worsening, or pain uptick; common and often called a “herx” (a loose analogy, not a literal Herxheimer reaction). Practitioners describe continuing if it is tolerable and dropping back a step if it is severe.
- Rare: liver enzyme elevation — practitioners describe checking LFTs at 6 weeks in people with any liver history or unexplained fatigue.
8. Where Low Dose Naltrexone Comes From — Compounding Pharmacies
Low dose naltrexone is not a stock pharmacy item at these doses. Commercial naltrexone comes as 50 mg tablets; trying to split a tablet into 1/30th is unreliable and potentially unsafe. It is made by compounding pharmacies, which prepare low dose naltrexone capsules or liquid in the exact dose prescribed (0.5, 1, 1.5, 2, 3, 4.5 mg are standard).
Many compounding pharmacies across the US prepare low dose naltrexone.
Cost: typically $35–75 per month cash pay. Some insurers will cover with prior authorization, especially when the prescribing indication is fibromyalgia, Crohn’s, or another off-label use. Any MD, DO, NP, or PA can write the prescription — no specialty licensure required.
9. How Patients Obtain a Prescription When the Doctor Is Not Familiar With It
Most primary care physicians have never prescribed low dose naltrexone, and patients describe arriving prepared.
- A patient advocacy group publishes patient and physician information packets on low dose naltrexone, which patients bring to their primary care physician (PCP).
- A dysautonomia patient advocacy group publishes a clinician summary on low dose naltrexone.
- Some autonomic specialty clinics, including telemedicine clinics, prescribe low dose naltrexone routinely when a PCP declines.
- A patient advocacy group keeps a physician directory listing prescribers by state and country.
An initial visit plus a compounding script is usually all it takes. Refills are straightforward once the pharmacy relationship is set up.
10. Combining Low Dose Naltrexone with Other Postural Orthostatic Tachycardia Syndrome Treatments
Low dose naltrexone plays well with essentially every standard postural orthostatic tachycardia syndrome medication:
- Beta-blockers (propranolol, metoprolol)
- Ivabradine
- Midodrine
- Fludrocortisone
- H1 and H2 antihistamines (for mast cell activation syndrome overlap)
- Most vitamins, minerals, and non-opioid analgesics
The one real-world constraint is opioids — any scheduled opioid analgesic, including tramadol, is incompatible while low dose naltrexone is onboard. For stacking strategy with other postural orthostatic tachycardia syndrome drugs, see the Medications Guide.
11. Timeline of Expected Effects
Low dose naltrexone is slow. Practitioners report that most patients notice the first meaningful shift at 4–8 weeks at target dose. A minority of responders feel it within 1–2 weeks, usually as improved energy or reduced brain fog first.
Practitioners describe a fair trial as at least 3 months at target dose before a person is judged a non-responder, and describe people who feel well at 3 mg staying at that dose — target dose is not the same as optimal dose.
12. What “Worked” Looks Like
Responders typically describe:
- Reduced orthostatic symptoms — less pre-syncope, less heart-pounding on standing
- Less post-exertional malaise after modest activity
- Better cognitive function — quicker word-finding, longer reading stamina
- Fewer mast cell activation syndrome flares or reduced flare intensity
- Improved exercise tolerance (usually in conjunction with a graded program)
The effect is often subtle at first. Practitioners describe a weekly symptom diary — standing heart rate, fatigue score, brain fog score, flare count — as the most reliable way to see whether low dose naltrexone is helping.
Key Research Papers
- Younger J, Parkitny L, McLain D. The use of low-dose naltrexone (LDN) as a novel anti-inflammatory treatment for chronic pain. Clinical Rheumatology. 2014;33(4):451–459. — doi:10.1007/s10067-014-2517-2
- Toljan K, Vrooman B. Low-Dose Naltrexone (LDN) — Review of Therapeutic Utilization. Medical Sciences (Basel). 2018;6(4):82. — doi:10.3390/medsci6040082
- Younger J, Noor N, McCue R, Mackey S. Low-dose naltrexone for the treatment of fibromyalgia: findings of a small, randomized, double-blind, placebo-controlled, counterbalanced, crossover trial assessing daily pain levels. Arthritis & Rheumatism. 2013;65(2):529–538. — PubMed PMID: 23359310
- Weinstock LB, Brook JB, Myers TL, Goodman B. Successful treatment of postural orthostatic tachycardia and mast cell activation syndromes using naltrexone, immunoglobulin and antibiotic treatment. BMJ Case Rep. 2018;2018:bcr-2017-221405. — doi:10.1136/bcr-2017-221405
- Stallkamp Tidd SJ, Cantrell C, Greene BD, Wilson R. Low-Dose Naltrexone Use in Postural Orthostatic Tachycardia Syndrome: A Case Series. Cureus. 2023;15(8):e43426. — PubMed PMID: 37706146
- Zapata N, Georgiadi E, Cantrell C, Rilinger RG, Levine MA, Wilson R. Low-Dose Naltrexone for Managing Pain and Autonomic Symptoms in Patients With Dysautonomia. Cureus. 2025;17(6):e86538. — PubMed PMID: 40698237
- Rodríguez-Freire C, Navarrete J, Rozadilla-Sacanell A, Sanabria-Mazo JP, Del Pino-Gaya B, Borràs X, Feliu-Soler A, Luciano JV. Efficacy of Low-Dose Naltrexone in Women With Fibromyalgia Syndrome: A 12-Month Randomised, Double-Blind, Placebo-Controlled Single-Centre Clinical Trial (INNOVA Study). European Journal of Pain. 2026;30(6):e70321. — PubMed PMID: 42385209
- Bruun KD, Nielsen MJ, Vaegter HB, Blichfeldt-Eckhardt MR, Amris K, Pedersen JR. Low-dose naltrexone for fibromyalgia: a re-analysis suggests lower efficacy than previously reported. Korean Journal of Pain. 2026;39(1):140–143. — PubMed PMID: 41469218
- Chopra P, Cooper MS. Treatment of Complex Regional Pain Syndrome (CRPS) using low dose naltrexone (LDN). Journal of Neuroimmune Pharmacology. 2013;8(3):470–476. — PubMed PMID: 23546884
- Byambasuren O, Atkins T, Baptista S, Glasziou P, Chakraborty S. Effect of low-dose naltrexone for long COVID: a systematic review and meta-analysis. BMJ Open. 2026;16(7):e111253. — PubMed PMID: 42463201
PubMed Topic Searches
Curated PubMed topic searches — each link opens a live query so you always see the most recent literature.
Connections
- Neurology
- Low-Dose Naltrexone: History and Origins — how a 50 mg addiction drug became a 4.5 mg immune therapy — Bernard Bihari’s 1985 acquired immunodeficiency syndrome (AIDS) observation, the Penn State opioid-growth-factor work, and how low dose naltrexone spread through compounding pharmacies.
- Postural Orthostatic Tachycardia Syndrome Overview
- Medications Guide
- Postural Orthostatic Tachycardia Syndrome Subtypes
- Compression and Exercise Program
- Salt and Hydration Protocol
- Vagus Nerve and Autonomic Retraining
- Tilt Table Test
- Postural Orthostatic Tachycardia Syndrome/Mast Cell Activation Syndrome/EDS Triad
- Mast Cell Activation Syndrome
- Fibromyalgia
- Myalgic Encephalomyelitis/Chronic Fatigue Syndrome
- Small Intestinal Bacterial Overgrowth
- Low-Dose Naltrexone (Remedy)
- Post-Viral Triggers: Epstein-Barr Virus and Others
- Brain Fog
- Fatigue
- Low-Dose Naltrexone for Fibromyalgia — the same drug in its best-studied indication, where the Younger/Stanford trials were run — the fullest account of titration schedules, morning-versus-bedtime timing, and compounding costs.
- Low Dose Naltrexone Abilify and Experimental Therapies