Low-Dose Naltrexone: The Off-Label Immunomodulator Redefining Chronic Illness Care
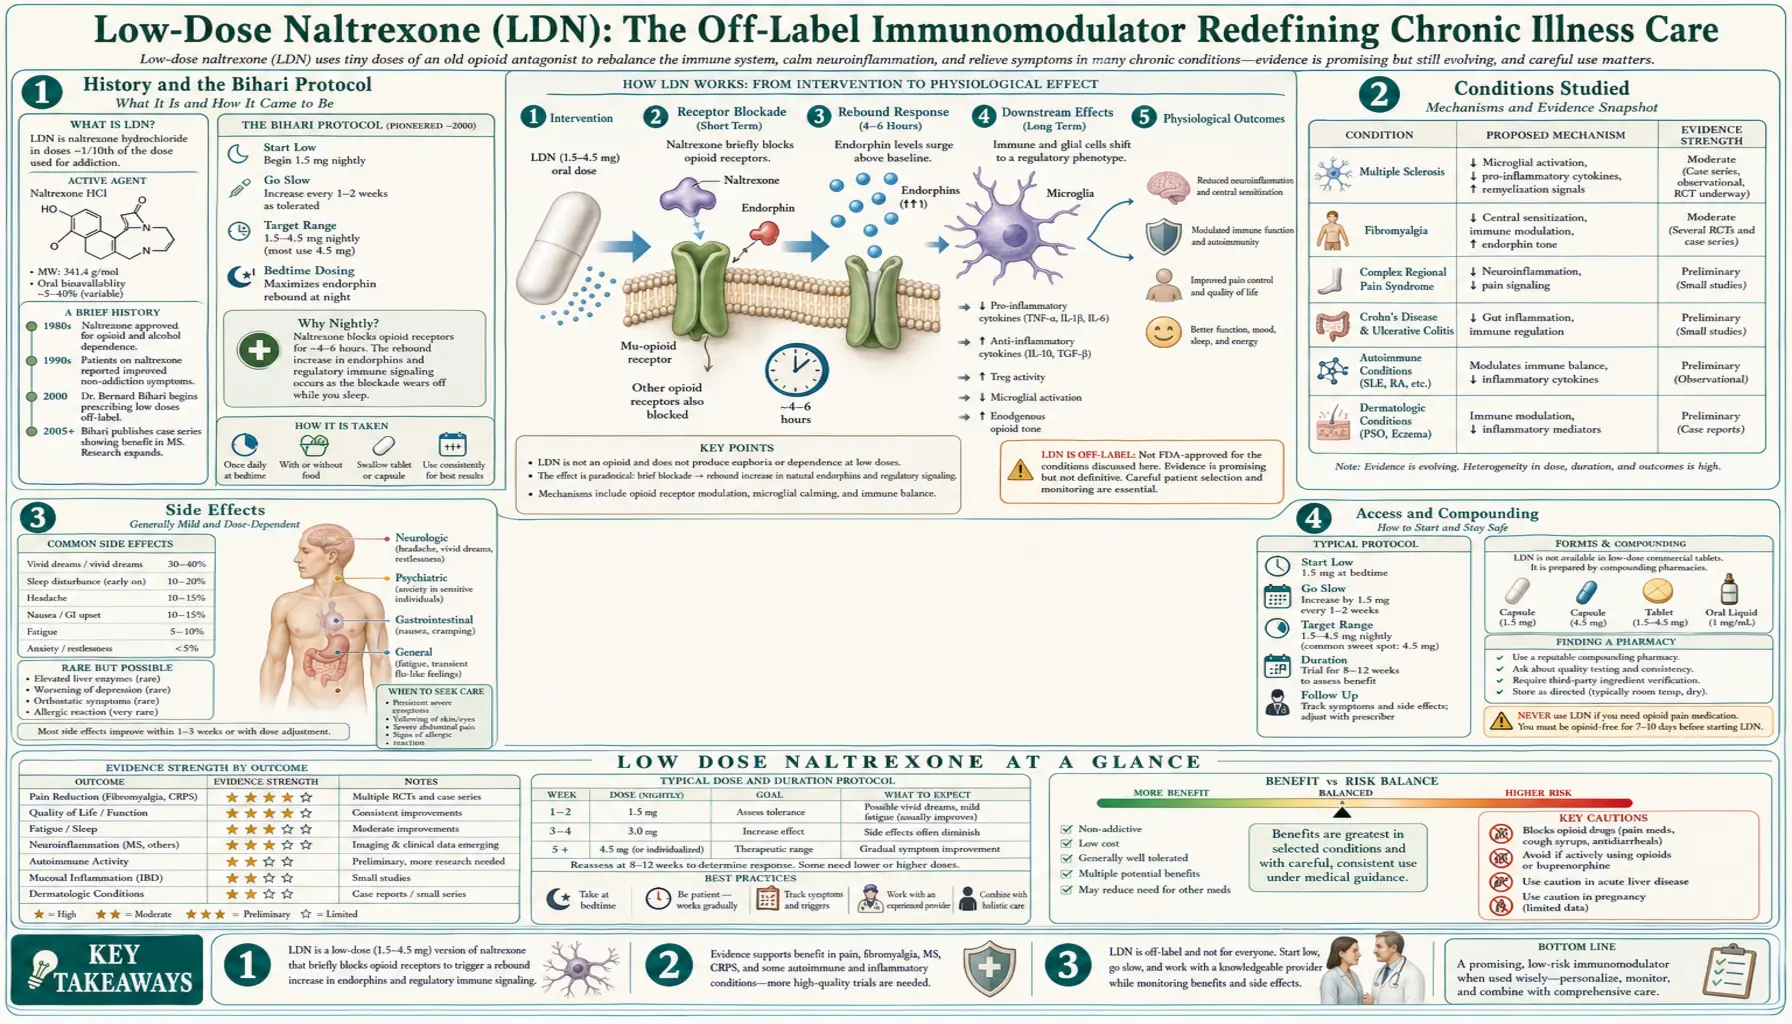
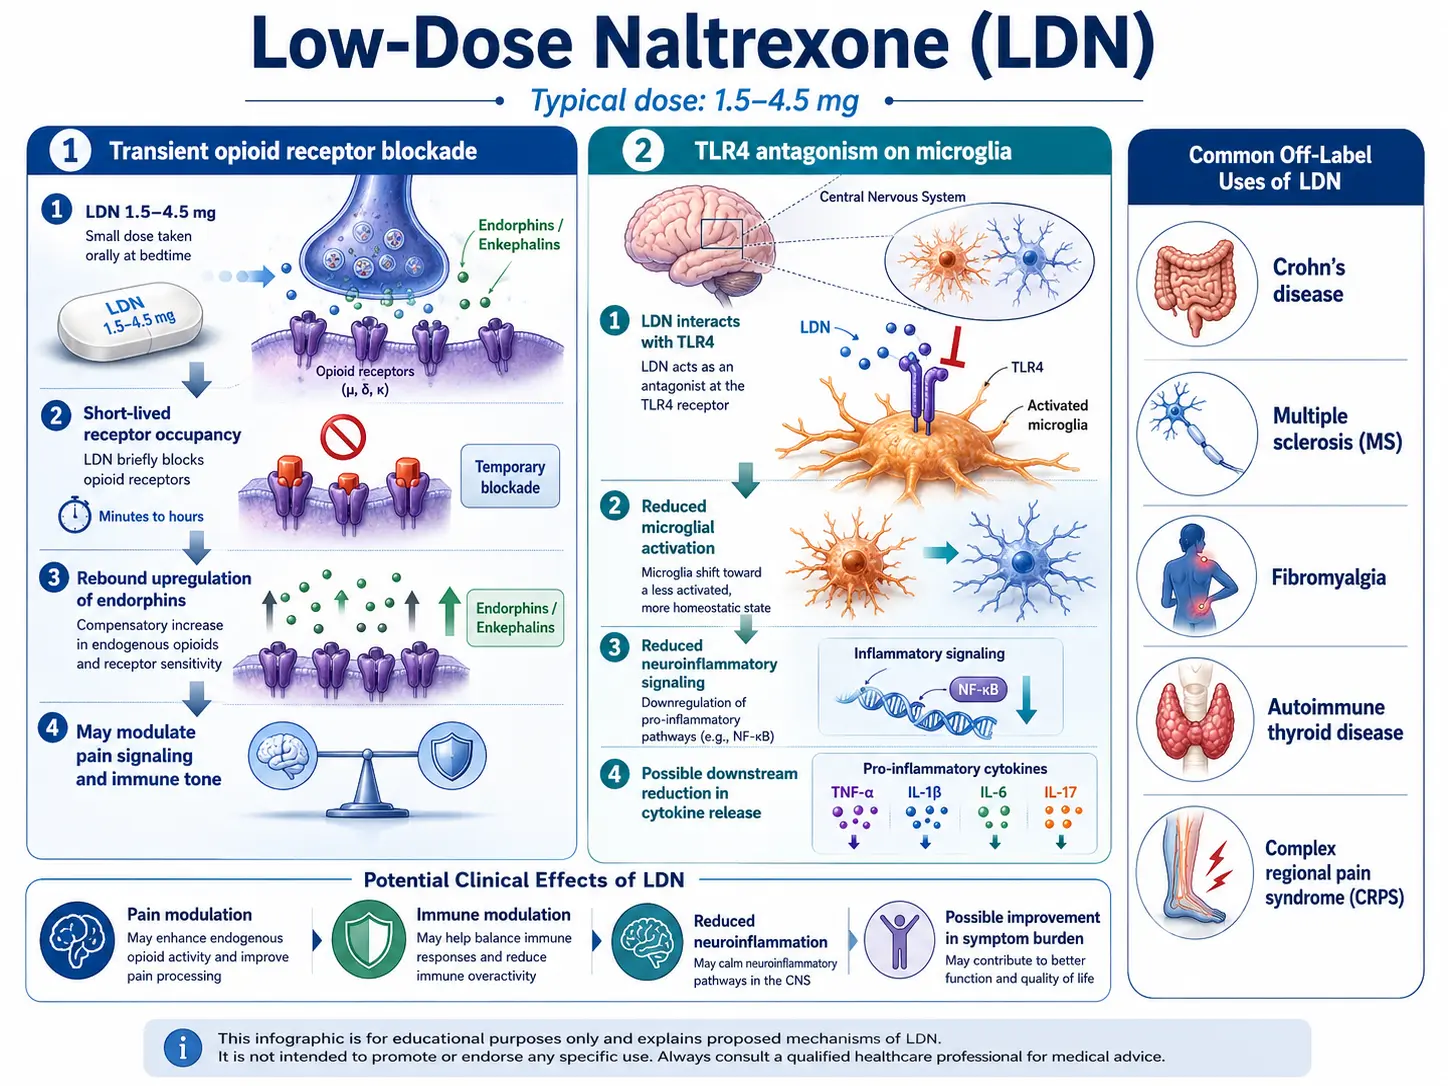
Naltrexone is a pure opioid-receptor antagonist first approved in 1984 at a daily oral dose of 50 mg for alcohol use disorder and opioid use disorder. In 1985, physician Bernard Bihari observed that at roughly one-tenth that dose — now called low-dose naltrexone — the drug produced entirely different effects: modulation of the immune system, reduction of inflammatory cytokines, and in some patients, substantial improvement in autoimmune disease and chronic pain. The mechanism differs from standard-dose naltrexone and centers on brief nightly opioid-receptor blockade, rebound endorphin release, and direct effects on glial cells in the central nervous system.
Today low dose naltrexone (LDN) is used off-label for a long list of chronic-inflammatory and autoimmune conditions. This article explains the mechanism, the evidence base, common dosing, side effects, and where low dose naltrexone fits in an evidence-informed chronic-illness protocol.
Table of Contents
History and the Bihari Protocol
Low-dose naltrexone traces to Dr. Bernard Bihari (1931–2010), a Harvard-trained New York addiction physician who first observed its apparent immune effects in human immunodeficiency virus (HIV)/acquired immunodeficiency syndrome (AIDS) patients in 1985–1986 and later extended it to autoimmune disease and cancer. Because naltrexone’s patent had long expired, no sponsor has carried low dose naltrexone through large-scale U.S. Food and Drug Administration (FDA) trials, so the evidence remains a patchwork of small studies and clinical experience — the fuller story is told in the dedicated History article.
Mechanism — Three Pathways
- Transient opioid-receptor blockade with endorphin rebound. Taking a low dose at bedtime produces a brief (4–6 hour) blockade of mu-opioid receptors. The body responds by increasing production of endogenous opioids and enkephalins, which then act on immune cells bearing opioid receptors, modulating cytokine balance toward a less inflammatory profile.
- Toll-like receptor 4 (TLR4) antagonism on microglia. Low dose naltrexone directly inhibits TLR4 on central-nervous-system glial cells, reducing the pro-inflammatory cascade implicated in chronic pain, fibromyalgia, and neuroinflammation.
- Direct effects on regulatory T cells and natural killer cells. Low dose naltrexone has been shown to normalize regulatory T-cell activity and enhance natural killer-cell function, relevant in both autoimmunity and cancer biology.
Conditions Studied
Low dose naltrexone has been studied or is commonly used off-label for:
- Multiple sclerosis. Randomized trials and observational data suggest reduced fatigue, spasticity, and quality-of-life benefit.
- Crohn’s disease. A small placebo-controlled trial in 34 adults found clinical remission in 30% of patients on low-dose naltrexone versus 18% on placebo, a difference that was not statistically significant, although more patients on the drug had a clinical response (83% versus 38%) and an endoscopic response (72% versus 25%). The often-quoted 67% remission figure comes from an earlier 17-patient open-label pilot with no placebo group.
- Fibromyalgia. Small crossover trials have shown meaningful pain reduction; a larger 2024 placebo-controlled trial in 99 women (6 mg daily for 12 weeks) found no significant difference from placebo in pain.
- Hashimoto’s thyroiditis. Case series and clinical reports describe reduced TPO antibodies and improved symptoms.
- Chronic pain and complex regional pain syndrome. TLR4-mediated benefit.
- Psoriasis, lupus, and systemic sclerosis. Case series and small studies.
- Long-COVID fatigue and post-viral syndromes. Open-label reports.
Dosing and Titration
The standard low dose naltrexone range is 1.5 mg to 4.5 mg taken at bedtime. Titration typically starts at 0.5 mg or 1.5 mg and advances every 1–2 weeks as tolerated. Some patients respond best to lower doses (<3 mg). A subset of patients with central-sensitization syndromes or sleep disruption on the standard regimen tolerate morning dosing or ultra-low doses better. Because standard naltrexone tablets are 50 mg, low dose naltrexone requires compounded capsules, sublingual drops, or quartering tablets.
Side Effects
- Vivid dreams or sleep disruption in the first 1–2 weeks. Usually settles.
- Mild headaches, nausea, or gastrointestinal (GI) upset.
- Transient increase in symptoms in some autoimmune patients during the first month.
Important Considerations and Contraindications
- Opioid medications. Low dose naltrexone blocks opioid-receptor effects. Anyone using prescription opioids for pain should not use low dose naltrexone concurrently, and low dose naltrexone should not be started within 7 days of opioid discontinuation.
- Pregnancy. Safety data are limited; use is typically avoided.
- Acute hepatitis. Standard-dose naltrexone has a black-box warning for hepatotoxicity at very high doses; low dose naltrexone doses are orders of magnitude lower, but liver enzymes should be monitored.
- Immunosuppressive therapies. Low dose naltrexone’s immunomodulation may interact with biologics; coordinate with prescribing clinician.
Access and Compounding
Because low dose naltrexone doses do not exist in manufactured form, a compounding pharmacy must prepare the capsules. Many compounding pharmacies worldwide now specialize in low dose naltrexone and can fill prescriptions through telemedicine. Quality varies — patients typically do better with immediate-release capsules than with slow-release formulations, because the transient blockade is part of the mechanism.
Key Research Papers
- Younger J, Parkitny L, McLain D (2014). The use of low-dose naltrexone (LDN) as a novel anti-inflammatory treatment for chronic pain. Clinical Rheumatology — PubMed PMID: 24526250
- Hutchinson MR, Zhang Y, Brown K, et al. (2008). Non-stereoselective reversal of neuropathic pain by naloxone and naltrexone: involvement of toll-like receptor 4 (TLR4). The European Journal of Neuroscience — PubMed PMID: 18662331
- Smith JP, Stock H, Bingaman S, et al. (2007). Low-dose naltrexone therapy improves active Crohn's disease. The American Journal of Gastroenterology — PubMed PMID: 17222320
- Smith JP, Bingaman SI, Ruggiero F, et al. (2011). Therapy with the opioid antagonist naltrexone promotes mucosal healing in active Crohn's disease: a randomized placebo-controlled trial. Digestive Diseases and Sciences — PubMed PMID: 21380937
- Parker CE, Nguyen TM, Segal D, et al. (2018). Low dose naltrexone for induction of remission in Crohn's disease. The Cochrane Database of Systematic Reviews — PubMed PMID: 29607497
- Younger J, Noor N, McCue R, et al. (2013). Low-dose naltrexone for the treatment of fibromyalgia: findings of a small, randomized, double-blind, placebo-controlled, counterbalanced, crossover trial assessing daily pain levels. Arthritis and Rheumatism — PubMed PMID: 23359310
- Due Bruun K, Christensen R, Amris K, et al. (2024). Naltrexone 6 mg once daily versus placebo in women with fibromyalgia: a randomised, double-blind, placebo-controlled trial. The Lancet. Rheumatology — PubMed PMID: 38258677
- Cree BA, Kornyeyeva E, Goodin DS (2010). Pilot trial of low-dose naltrexone and quality of life in multiple sclerosis. Annals of Neurology — PubMed PMID: 20695007
PubMed Topic Searches
Selected PubMed topic searches relevant to low-dose naltrexone mechanisms, autoimmune disease, chronic pain, and immunomodulation.
- PubMed: Low-dose naltrexone and autoimmune disease
- PubMed: Low-dose naltrexone and fibromyalgia
- PubMed: Low-dose naltrexone and multiple sclerosis
- PubMed: Low-dose naltrexone and Crohn's disease
- PubMed: Naltrexone and opioid growth factor (OGF)
- PubMed: LDN and complex regional pain syndrome
- PubMed: Naltrexone, TLR4, and microglia
- PubMed: LDN and Hashimoto's thyroiditis
- PubMed: Low-dose naltrexone and cancer
- PubMed: Low-dose naltrexone and post-viral syndromes
- PubMed: Naltrexone pharmacokinetics at low dose
- PubMed: Naltrexone and endogenous endorphin rebound
Connections
- All Remedies
- Chronic Pain
- Fibromyalgia
- Lupus
- Crohn's Disease
- Multiple Sclerosis
- Hashimoto's Thyroiditis
- Postural Orthostatic Tachycardia Syndrome
- Fatigue
- Gut Healing
- Stress Management
- Thyroid Panel
- Inflammatory Markers
- Anti Inflammatory Diet
- Complex Regional Pain Syndrome
- Psoriasis
- Chronic Fatigue Syndrome
- Central Sensitization Explained
- Sjogrens Syndrome
- Conditions on this site that reference this page: Irritable Bowel Syndrome Medications Guide · Low Dose Naltrexone, Abilify & Experimental Therapies for Myalgic Encephalomyelitis/Chronic Fatigue Syndrome · Post-Exertional Malaise (PEM) Explained · Low-Dose Naltrexone for Postural Orthostatic Tachycardia Syndrome · Postural Orthostatic Tachycardia Syndrome Medications Guide · ACR 2016 Diagnostic Criteria for Fibromyalgia · Cannabis, Cannabidiol & Medical Marijuana for Fibromyalgia · Exercise Pacing and Graded Movement for Fibromyalgia