Tilt Table Test and NASA Lean Test for Postural Orthostatic Tachycardia Syndrome (POTS)
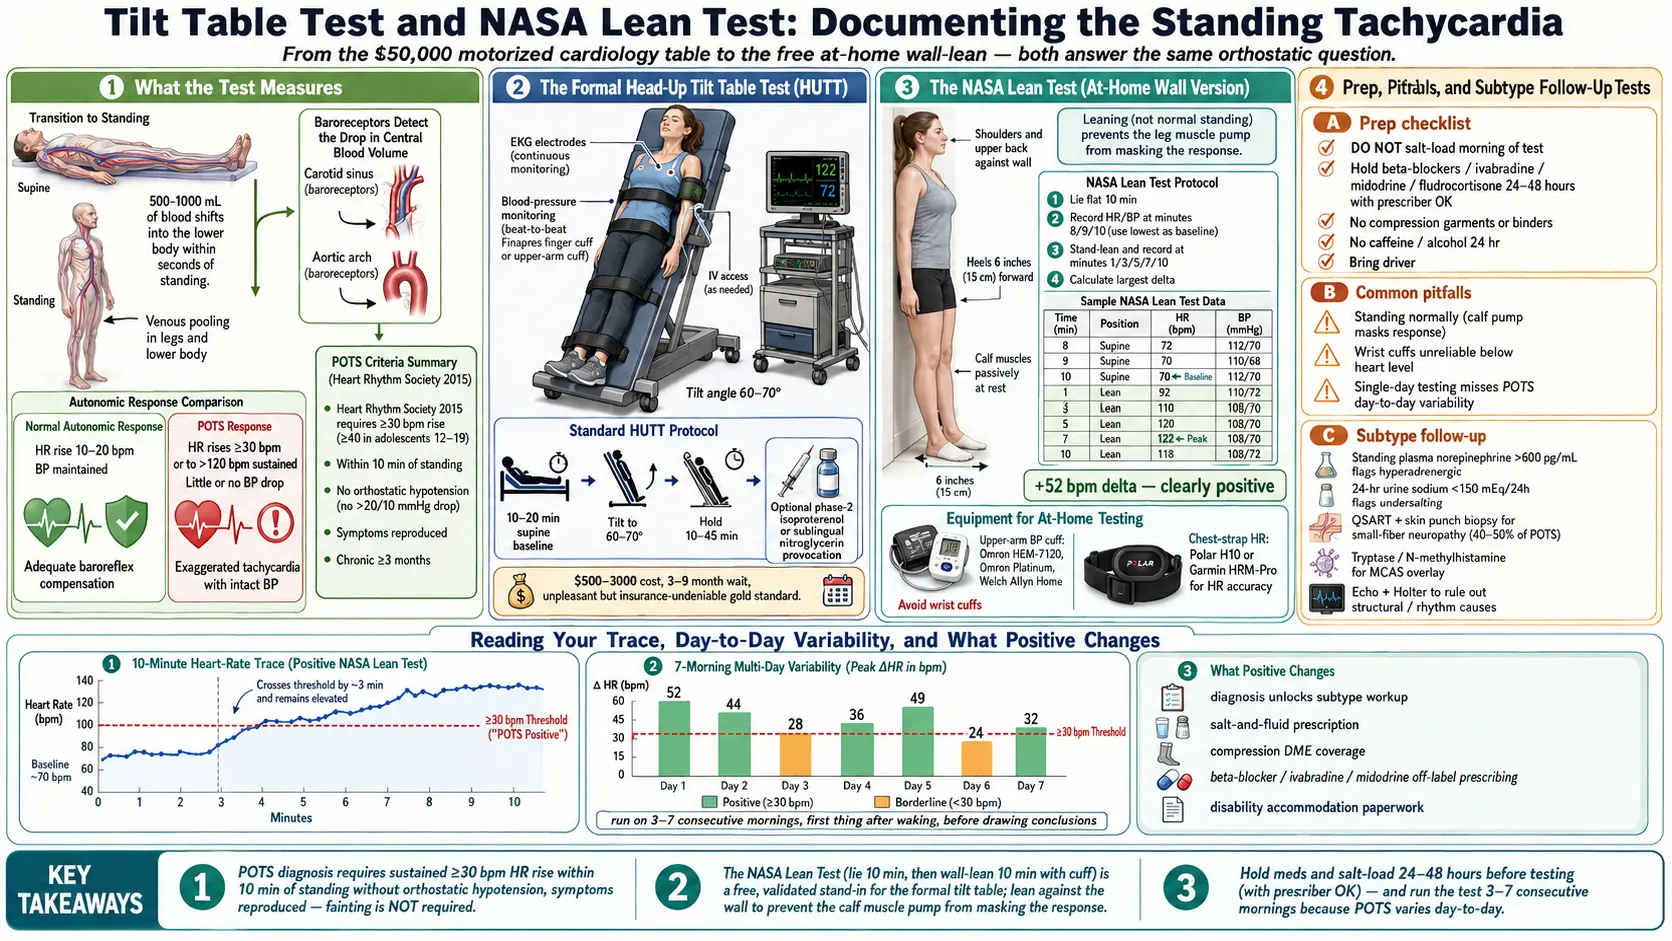
Table of Contents
- What Doctors Are Actually Measuring
- Postural Orthostatic Tachycardia Syndrome Diagnostic Criteria
- The Formal Tilt Table Test
- Preparing for a Tilt Test
- The NASA Lean Test (At-Home Version)
- Why the Test Uses a Wall Lean
- Equipment Used for Home Testing
- Reading the Results
- Other Tests in a Postural Orthostatic Tachycardia Syndrome Workup
- When a Test Is Negative But You Still Feel Postural Orthostatic Tachycardia Syndrome
- What a Positive Result Changes
- Key Research Papers
- Connections
- Featured Videos
1. What Doctors Are Actually Measuring
If you’re nervous about a tilt test, start here. The whole point of every postural orthostatic tachycardia syndrome (POTS) test — whether you’re strapped to a $50,000 motorized table in a cardiology lab or standing against your bedroom wall with a drugstore blood pressure cuff — is to answer one simple question: when gravity pulls your blood down into your legs, does your autonomic nervous system compensate correctly, or does it overshoot?
When a healthy person stands, about 500–1000 mL of blood shifts into the lower body within seconds. The baroreceptors in your neck and chest detect the drop in central blood volume, and your autonomic nervous system responds by constricting blood vessels and nudging your heart rate up by roughly 10–20 bpm. Blood pressure stays stable. You feel nothing.
In postural orthostatic tachycardia syndrome, the blood vessels don’t tighten enough, or too much blood pools, or the brain misreads the signal. Your heart rate has to sprint — often 30, 40, 60 bpm above baseline — just to keep blood moving up to your head. That’s the tachycardia in Postural Orthostatic Tachycardia Syndrome. The tests just capture it in numbers.
2. Postural Orthostatic Tachycardia Syndrome Diagnostic Criteria
The 2015 Heart Rhythm Society expert consensus statement defines postural orthostatic tachycardia syndrome by three features:
- Frequent symptoms that occur with standing — such as lightheadedness, palpitations, tremulousness, generalized weakness, blurred vision, exercise intolerance, and fatigue
- Heart rate increase of at least 30 bpm when moving from lying down to a standing position held for more than 30 seconds — at least 40 bpm in adolescents aged 12–19
- No orthostatic hypotension — a drop of more than 20 mmHg in systolic blood pressure (if blood pressure does fall that far, that’s a different diagnosis)
Raj’s 2013 review in Circulation states the criteria slightly differently: the heart-rate rise occurs within 10 minutes of assuming an upright posture, symptoms have lasted at least 6 months, and orthostatic hypotension is a fall of more than 20/10 mmHg.
Fainting is not part of the definition. Raj’s review notes that only a minority of postural orthostatic tachycardia syndrome patients (about 30%) actually faint, while lightheadedness and near-fainting are common. The diagnosis is about the sustained tachycardia plus the symptom cluster, not syncope.
3. The Formal Tilt Table Test
Here’s what actually happens when you walk into a cardiology or neurology autonomic lab for a head-up tilt test (HUTT):
- You lie flat on a padded motorized table for 10–20 minutes while baseline measurements are taken
- An intravenous (IV) line is placed (in case syncope requires rescue, or for phase-2 drug provocation)
- A continuous electrocardiogram (EKG) is running the entire time
- A blood pressure cuff reads automatically every 1–2 minutes, or a beat-to-beat finger cuff (Finapres/Portapres) streams continuously
- Straps secure your torso, hips, and feet so you won’t fall if you lose consciousness
- The table tilts you upright to 60–70 degrees (not quite vertical) and holds you there for 10 to 45 minutes
If the initial passive phase is negative, some labs run a phase 2 using isoproterenol (a beta-agonist infusion) or sublingual nitroglycerin to provoke a response. This is controversial — it can generate false positives — and labs differ in whether they use it.
Pros: gold-standard measurement, removes the confounder of leg-muscle pumping, captures late-phase reactions (neurocardiogenic syncope can take 20–30 minutes to unfold), and produces a report insurance companies cannot dismiss.
Cons: expensive ($500–$3,000 depending on coverage), wait lists of 3–9 months at many centers, and genuinely unpleasant — lightheadedness, palpitations, nausea, and occasionally vomiting or brief syncope are common during the test.
4. Preparing for a Tilt Test
Preparation affects the result. The aim of the usual pre-test instructions is to let the test capture the person’s typical response, rather than one masked by extra salt, fluid, medication or compression.
- Salt-loading or fluid-loading the morning of the test can mask the tachycardia and produce a falsely negative report; drinking normally, without extra electrolyte drinks, keeps the result representative.
- Beta-blockers, ivabradine, midodrine, and fludrocortisone are sometimes held for 24–48 hours before the test — only with the prescribing doctor’s written OK, because stopping a beta-blocker abruptly can cause a rebound.
- Prokinetics and stimulants are commonly held for 24 hours when that is safe
- A light, low-salt breakfast at least 2 hours before is the usual instruction
- Loose clothing: compression garments, abdominal binders and tight waistbands all counteract blood pooling, which is what the test measures
- Caffeine and alcohol are usually stopped for 24 hours before
- A driver home: patients are often not safe behind a wheel for several hours afterward
A written symptom log is useful to bring. Many labs ask patients to narrate what they feel in real time during the tilt, and anxious patients can forget to mention the lightheadedness because it’s so normal for them.
5. The NASA Lean Test (At-Home Version)
The NASA Lean Test is based on NASA physiology experiments from the 1970s in small samples of healthy young men or astronauts, which studied normal responses to standing rather than diagnosing orthostatic disorders. It has since spread rapidly as a free, roughly 15-minute, at-home check that needs only a blood pressure cuff and a wall. A 2025 review in Clinical Autonomic Research found, however, that validation studies comparing it with tilt-table or active-standing tests are lacking, noted that NASA itself now uses a standard 10-minute active standing test instead, and concluded that the lean test “may currently not be used as a diagnostic tool.”
Protocol:
- Lying flat on the back for 10 minutes, without phone or talking. Blood pressure (BP) and HR are recorded at minutes 8, 9, and 10, and the lowest of the three readings is the supine baseline.
- Standing and leaning against a wall, heels about 6 inches from the baseboard, shoulders and upper back touching the wall. This passively pools blood in the legs and keeps the calf muscles from pumping it back up.
- Blood pressure and HR are recorded at minutes 1, 3, 5, 7, and 10 of standing.
- The result is the largest HR increase from the supine baseline to any standing reading.
Positive for postural orthostatic tachycardia syndrome: heart rate rises by at least 30 bpm (adult) or 40 bpm (adolescent), symptoms are present, and systolic blood pressure does not drop more than 20 mmHg.
This test is cheap, repeatable, and patient-controlled. The tradeoff: it uses intermittent cuff readings instead of beat-to-beat monitoring, so very short HR spikes can be missed, and results vary from day to day, which is why it is often repeated on several mornings in a row.
6. Why the Test Uses a Wall Lean
This is the detail most people get wrong. If you stand normally during a home orthostatic test, your calf muscles act as a second heart. Every tiny postural micro-adjustment — shifting weight, wiggling toes, bracing the knees — squeezes the deep veins in your legs and pumps blood back up toward your chest. That muscle pump can completely mask a postural orthostatic tachycardia syndrome response.
Leaning against a wall with heels forward puts you in a near-passive posture. Your legs aren’t working. Blood pools in the lower extremities the same way it does when a tilt table holds you at 70 degrees. That’s the mechanical reason the lean is meant to resemble a tilt. In practice the two are not interchangeable: in a 2025 study of 80 young adults with post-COVID-19 syndrome who had both tests, the heart-rate rise was smaller on the tilt table than in the NASA lean test (21.5 vs 27.0 bpm) while systolic blood pressure changes were comparable, and the 2025 Clinical Autonomic Research review noted that there are no structured data on the validity of a leaning test.
Crossing the legs, shifting weight or rising onto the toes reactivates the muscle pump, which is why the protocol calls for standing still.
7. Equipment Used for Home Testing
The equipment is simple, but a few choices affect accuracy:
- Upper-arm automatic blood pressure cuff — validated consumer models work, typically costing around $40–$100.
- Wrist cuffs become inaccurate when the arm is below heart level, as it is in the standing phase, and also misread during tachycardia.
- For more accurate heart rate, a chest-strap heart-rate monitor or a smartwatch can be paired with the cuff. The cuff’s built-in pulse reading averages over the inflation cycle and can under-report brief spikes.
- A paper log or a simple spreadsheet is enough to record readings; symptom-tracking apps can graph trends but are not needed.
8. Reading the Results
Here’s what a clearly positive NASA Lean Test looks like:
| Time Point | Position | HR (bpm) | Blood pressure (mmHg) | Notes |
|---|---|---|---|---|
| Min 8 supine | Flat | 72 | 112/70 | Calm baseline |
| Min 9 supine | Flat | 70 | 110/68 | Baseline = 70 |
| Min 10 supine | Flat | 71 | 111/69 | |
| Min 1 standing | Wall lean | 98 | 108/72 | +28 bpm |
| Min 3 standing | Wall lean | 115 | 106/74 | +45 bpm, lightheaded |
| Min 5 standing | Wall lean | 118 | 104/76 | Palpitations |
| Min 7 standing | Wall lean | 122 | 102/78 | Tremor, nausea |
| Min 10 standing | Wall lean | 120 | 103/76 | Symptoms sustained |
Reading the table: baseline was 70 bpm supine. Peak standing HR was 122 bpm at minute 7. That’s a +52 bpm delta, well above the 30 bpm threshold. Systolic blood pressure dropped only 9 mmHg — not orthostatic hypotension. Symptoms were reproduced. This is a clearly positive NASA Lean Test.
Borderline patterns show a 25–29 bpm rise, or symptoms without hitting the threshold, or a rise that occurs only on some days. Negative is a rise under 20 bpm with no symptoms.
Postural orthostatic tachycardia syndrome varies day to day, sometimes dramatically, so repeating the test on 3 to 7 consecutive mornings gives a fuller picture than a single reading. First thing after waking is often the most sensitive window, because overnight fluid shifts leave the body volume-depleted. The 2025 Clinical Autonomic Research review added that results of provocative cardiovascular tests are best recorded and interpreted by specialists rather than by patients themselves.
9. Other Tests in a Postural Orthostatic Tachycardia Syndrome Workup
Once a tilt or stand test shows the postural orthostatic tachycardia syndrome pattern, the next question is which kind. These follow-up tests help pin down the subtype and rule out overlapping conditions:
- Standing plasma norepinephrine — drawn supine and again after 10 minutes standing. A standing level above 600 pg/mL suggests the hyperadrenergic subtype. See the Subtypes page.
- 24-hour urine sodium — the 2015 Heart Rhythm Society statement lists a 24-hour urine sample to assess sodium intake as part of an expanded evaluation, and adds that these expanded tests “should not be performed routinely as there is no evidence that they improve the care or the process of care in the majority of patients.”
- Tilt with Valsalva maneuver — checks baroreflex integrity
- Autonomic reflex screen (ARS) — a battery of deep-breathing, Valsalva, and tilt tests, often done at Mayo, Cleveland Clinic, Vanderbilt, Johns Hopkins autonomic labs
- QSART (Quantitative Sudomotor Axon Reflex Test) — measures small-fiber sweat nerve function; abnormal in neuropathic postural orthostatic tachycardia syndrome
- Skin punch biopsy — looks at epidermal nerve fiber density to diagnose small-fiber neuropathy, present in roughly 40–50% of postural orthostatic tachycardia syndrome patients
- Tryptase, plasma histamine, N-methylhistamine — if mast cell activation syndrome (MCAS) is suspected
- Echocardiogram and 24-hour Holter monitor — rule out structural and rhythm causes of tachycardia
10. When a Test Is Negative But You Still Feel Postural Orthostatic Tachycardia Syndrome
This happens often, and it does not mean you’re imagining things.
Postural orthostatic tachycardia syndrome is remarkably variable. The same patient can hit +50 bpm on a Monday morning and +18 bpm on Thursday afternoon. Known modifiers include:
- Time of day — most patients are worse in the morning before they’ve rehydrated
- Menstrual cycle phase — in a questionnaire study, women with postural orthostatic tachycardia syndrome reported the most lightheadedness during menses and less in the follicular phase; in a small laboratory study, presyncope during prolonged standing was more common in the early follicular phase than in the mid-luteal phase, while a later tilt study found no difference in presyncope between the two phases
- Hydration status — even 500 mL of extra fluid the night before can blunt a test
- Recent illness or post-viral inflammation
- Deconditioning or recent rest — prolonged bedrest paradoxically masks some autonomic features
- Medication half-lives — a beta-blocker taken 20 hours ago can still be on board
- Sleep debt — sympathetic overdrive from poor sleep can either worsen or mask the response
When a tilt or NASA Lean is negative but the symptoms are classic, repeat testing — across a full menstrual cycle, or as a repeat formal tilt during a worse week — is how the variability is usually handled. One negative report is not the final word. Many patients are diagnosed on the second or third attempt.
11. What a Positive Result Changes
A documented positive test is the single most useful piece of paper in a postural orthostatic tachycardia syndrome patient’s chart. Concretely, it delivers:
- An ICD-10 code (G90.A) for Postural Orthostatic Tachycardia Syndrome, which insurance needs to approve testing, medications, and disability accommodations
- Access to medicines prescribed for documented postural orthostatic tachycardia syndrome — ivabradine, midodrine, fludrocortisone, and pyridostigmine. The FDA has not approved any medication for postural orthostatic tachycardia syndrome, so all of these are used “off label” (Raj 2013). See the Medications Guide.
- School and workplace accommodations under ADA (seated work, water at desk, breaks to lie down, modified PE)
- Referral to an autonomic specialist — many won’t see you without documentation
- Validation. This matters more than it should. Many patients have been told for years that their tachycardia is anxiety. A positive tilt ends that conversation.
Key Research Papers
- Raj SR. Postural Tachycardia Syndrome (POTS). Circulation. 2013;127(23):2336–2342. — doi:10.1161/CIRCULATIONAHA.112.144501
- Sheldon RS, Grubb BP, Olshansky B, et al. 2015 Heart Rhythm Society Expert Consensus Statement on the Diagnosis and Treatment of Postural Tachycardia Syndrome, Inappropriate Sinus Tachycardia, and Vasovagal Syncope. Heart Rhythm. 2015;12(6):e41–e63. — doi:10.1016/j.hrthm.2015.03.029
- Bashir M, Ahluwalia H, Khan T, Sayeed SI. Role of NASA 10-minute Lean Test in diagnosing postural orthostatic tachycardia syndrome: a preliminary study in young population. Ital J Med. 2021;15(2):1340. — doi:10.4081/itjm.2021.1340
- Freeman R, Wieling W, Axelrod FB, et al. Consensus statement on the definition of orthostatic hypotension, neurally mediated syncope and the postural tachycardia syndrome. Auton Neurosci. 2011;161(1–2):46–48. — doi:10.1016/j.autneu.2011.02.004
- Teuschl Y, Fanciulli A, Pavy-Le Traon A, et al. Is the NASA Lean Test a suitable tool to diagnose cardiovascular autonomic disorders? Clin Auton Res. 2025;35(3):529–531. — PubMed PMID: 39786620
- Sathaporn N, Timinkul A, Panwong W, et al. Comparison of the head-up tilt test and the 10-minute NASA lean test for assessing blood pressure and heart rate responses in young individuals with postacute COVID-19 syndrome. Blood Press Monit. 2025;30(4):153–160. — PubMed PMID: 40105186
- Peggs KJ, Nguyen H, Enayat D, et al. Gynecologic disorders and menstrual cycle lightheadedness in postural tachycardia syndrome. Int J Gynaecol Obstet. 2012;118(3):242–246. — PubMed PMID: 22721633
- Fu Q, VanGundy TB, Shibata S, et al. Menstrual cycle affects renal-adrenal and hemodynamic responses during prolonged standing in the postural orthostatic tachycardia syndrome. Hypertension. 2010;56(1):82–90. — PubMed PMID: 20479333
- Stickford AS, VanGundy TB, Levine BD, Fu Q. Menstrual cycle phase does not affect sympathetic neural activity in women with postural orthostatic tachycardia syndrome. J Physiol. 2015;593(9):2131–2143. — PubMed PMID: 25656420
PubMed Topic Searches
Additional PubMed searches for the diagnostic literature on postural orthostatic tachycardia syndrome and orthostatic testing:
- PubMed: POTS tilt table test
- PubMed: NASA lean test POTS
- PubMed: Orthostatic intolerance diagnosis
- PubMed: POTS diagnostic criteria
- PubMed: Autonomic reflex screen
- PubMed: QSART small fiber neuropathy
- PubMed: Head-up tilt test with isoproterenol
- PubMed: Orthostatic tachycardia and heart rate variability
Connections
- Neurology
- Postural Orthostatic Tachycardia Syndrome Overview
- Postural Orthostatic Tachycardia Syndrome Subtypes
- Medications Guide
- Compression & Exercise Program
- Salt & Hydration Protocol
- Vagus Nerve & Autonomic Retraining
- Low-Dose Naltrexone
- Postural Orthostatic Tachycardia Syndrome-MCAS-EDS Triad
- Mast Cell Activation Syndrome (MCAS)
- Chronic Fatigue Syndrome (Myalgic Encephalomyelitis/CFS)
- Arrhythmia
- Lightheadedness on Standing
- Small Intestinal Bacterial Overgrowth
- Fibromyalgia
- Postural Orthostatic Tachycardia Syndrome Diet
- 2 Day CPET and Objective Testing
- Orthostatic Intolerance in Myalgic Encephalomyelitis/Chronic Fatigue Syndrome (ME/CFS)