Postural Orthostatic Tachycardia Syndrome (POTS): The Autonomic Syndrome Everyone Is Finally Talking About
Postural orthostatic tachycardia syndrome (POTS) is a form of dysautonomia characterized by an abnormal increase in heart rate upon standing, accompanied by symptoms such as lightheadedness, palpitations, fatigue, cognitive impairment, and exercise intolerance. Estimates suggest 1 to 3 million Americans have postural orthostatic tachycardia syndrome, with a sharp female predominance (5:1 to 10:1) and typical onset in the second to fourth decade. Diagnoses surged following COVID-19, which is now recognized as one of the strongest known triggers.
Deep-Dive Articles
Postural orthostatic tachycardia syndrome is complicated, and generic advice rarely gets anyone better. The eight guides below each tackle one piece of the puzzle — the subtype you actually have, the tests that confirm it, the daily protocols that move the needle, the medications that help and the ones that don’t, and the overlap conditions (mast cell activation syndrome (MCAS), Ehlers-Danlos) you may also need to investigate. Start with whichever piece matches where you are right now.
Postural Orthostatic Tachycardia Syndrome Subtypes
Hyperadrenergic, neuropathic, and hypovolemic postural orthostatic tachycardia syndrome explained in plain language. Each one has different root causes and different best treatments — knowing your subtype is the single most useful thing you can learn about your own postural orthostatic tachycardia syndrome.
Read the deep dive →Tilt Table & NASA Lean Test
What to expect during a tilt table test, how to do the at-home NASA Lean Test if you can’t get a specialist appointment, how to read the heart-rate/blood-pressure curve, and why the timing matters.
Read the deep dive →Salt & Hydration Protocol
The 10g sodium / 2–3 L fluid target — why it works, how to actually hit it without feeling sick, homemade ORS recipes, commercial options (Liquid IV, LMNT, Normalyte), and when salt tablets beat food-based salt.
Read the deep dive →Compression & Exercise Program
Compression garments (abdominal binders vs. thigh-high stockings), and the CHOP/Dallas recumbent exercise protocol that reverses deconditioning without triggering post-exertional crashes. Week-by-week progression.
Read the deep dive →Medications Guide
Beta-blockers vs. ivabradine vs. midodrine vs. fludrocortisone vs. pyridostigmine — what each one does, who it helps, the tradeoffs, typical dosing, and how they stack. The honest medication map most doctors don’t have time to explain.
Read the deep dive →Postural Orthostatic Tachycardia Syndrome/Mast Cell Activation Syndrome/Ehlers-Danlos Syndrome Triad
If you’re flexible, bloated, and dizzy, you may have all three. How to recognize the triad, the Beighton hypermobility score, when to screen for mast cell activation, and why treating only one condition often fails.
Read the deep dive →Low-Dose Naltrexone for Postural Orthostatic Tachycardia Syndrome
The 1.5–4.5 mg bedtime protocol that’s quietly become one of the most-used off-label postural orthostatic tachycardia syndrome treatments. How it works (microglial modulation, not opioids), titration, cost, and what the case-series evidence actually shows.
Read the deep dive →Vagus Nerve & Autonomic Retraining
Cold-water face dunks, humming, slow diaphragmatic breathing, DNRS and Primal Trust brain-retraining programs. The non-pharmaceutical lane — cheap, safe, and for many people genuinely effective.
Read the deep dive →Diet: Small Frequent Meals & Postprandial Crashes
Splanchnic pooling, low-GI carbs, electrolytes, and meal timing for postural orthostatic tachycardia syndrome.
Read the deep dive →What Postural Orthostatic Tachycardia Syndrome Is
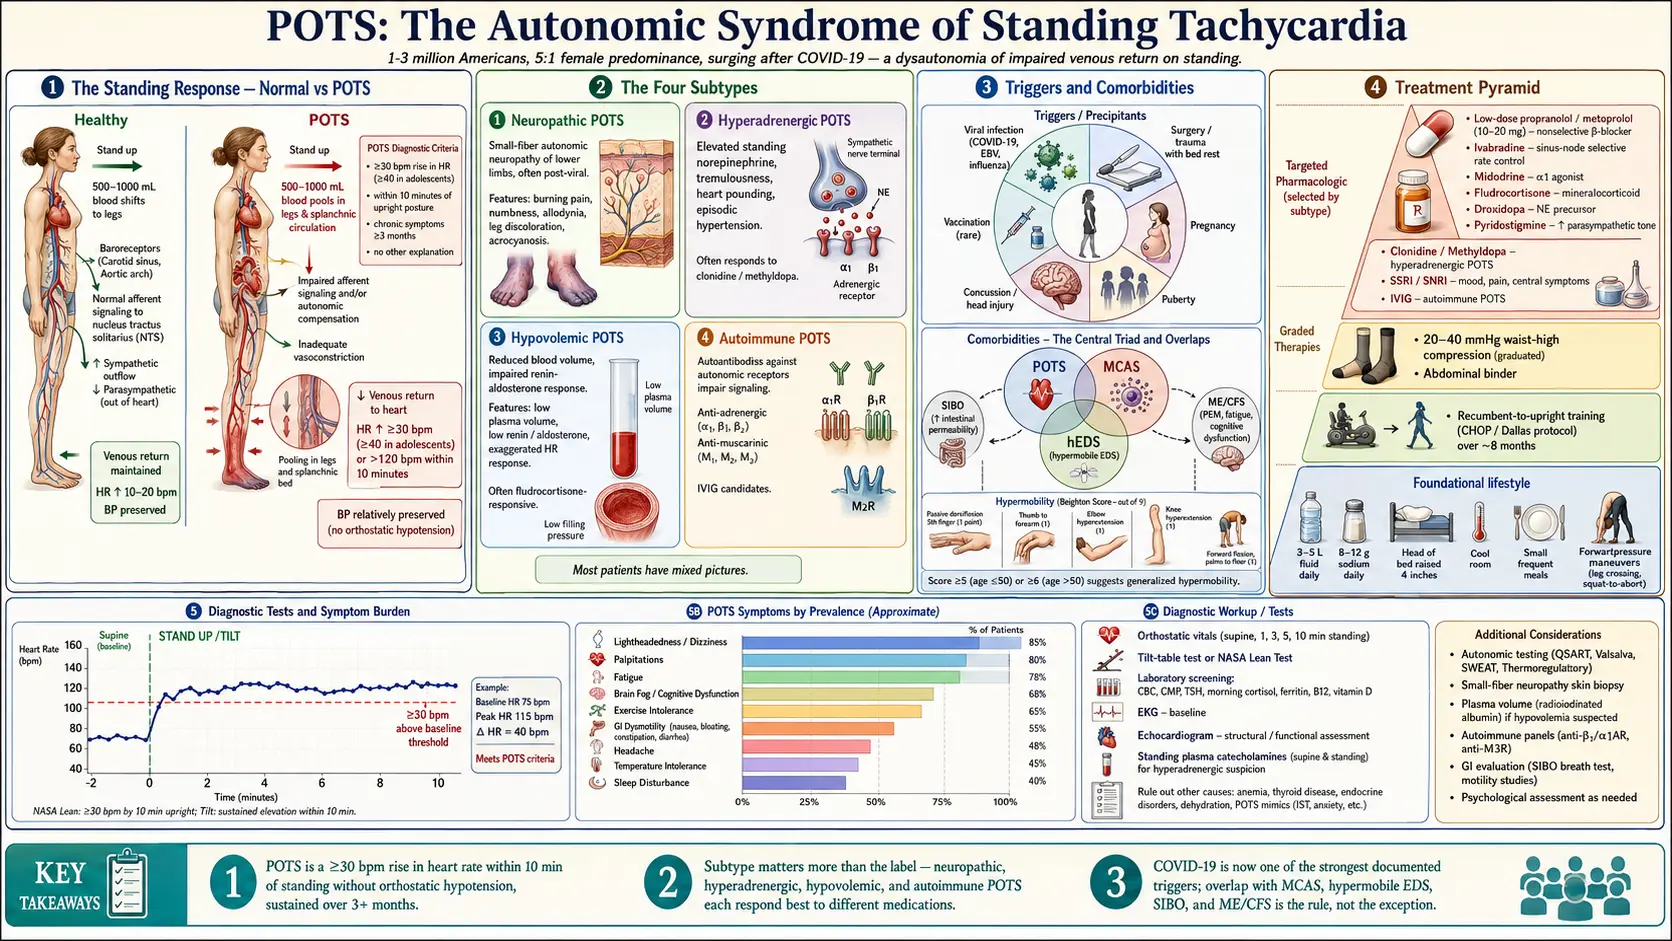
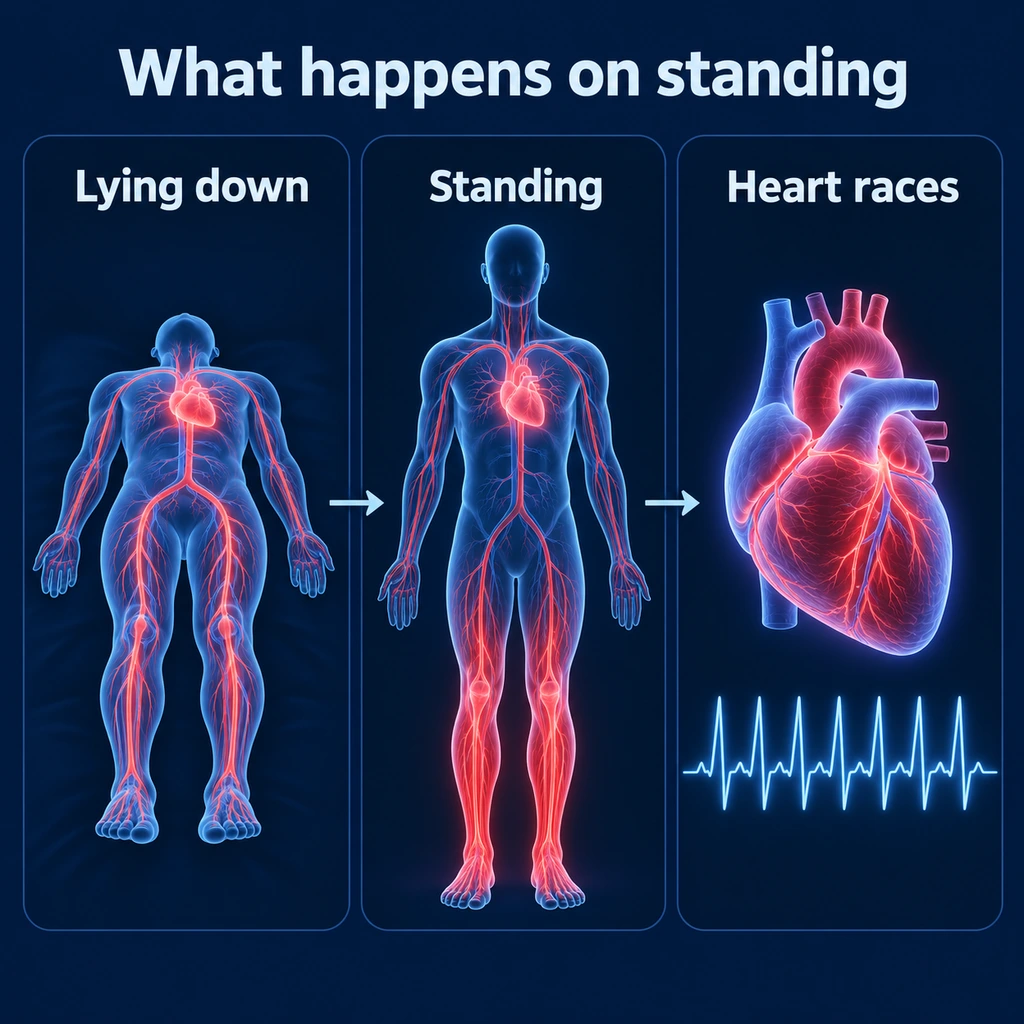
When a healthy person stands up, roughly 500–1000 mL of blood shifts toward the legs. Baroreceptors detect the transient drop in blood return, and the autonomic nervous system compensates through vasoconstriction and a modest rise in heart rate (10–20 bpm). In postural orthostatic tachycardia syndrome this response is exaggerated: heart rate rises by 30 bpm or more (40 or more in 12- to 19-year-olds) within 10 minutes of standing, without a substantial drop in blood pressure. The body is functionally struggling to keep blood returning to the heart and brain when upright.
Diagnostic Criteria
- Heart rate increase of ≥30 bpm (≥40 in adolescents aged 12–19) within 10 minutes of standing or head-up tilt. A standing heart rate of 120 bpm or more is common in POTS but is not itself a criterion (Sheldon 2015).
- Without orthostatic hypotension (no drop of >20/10 mmHg).
- Chronic symptoms of orthostatic intolerance for at least 3 months.
- Absence of another explanation such as dehydration, medications, or primary autonomic failure.
Symptoms
- Lightheadedness, pre-syncope, occasional syncope
- Palpitations
- Exercise intolerance
- Fatigue (often profound)
- Brain fog and concentration difficulty
- Headache
- Nausea and gastrointestinal (GI) dysmotility
- Temperature intolerance, flushing
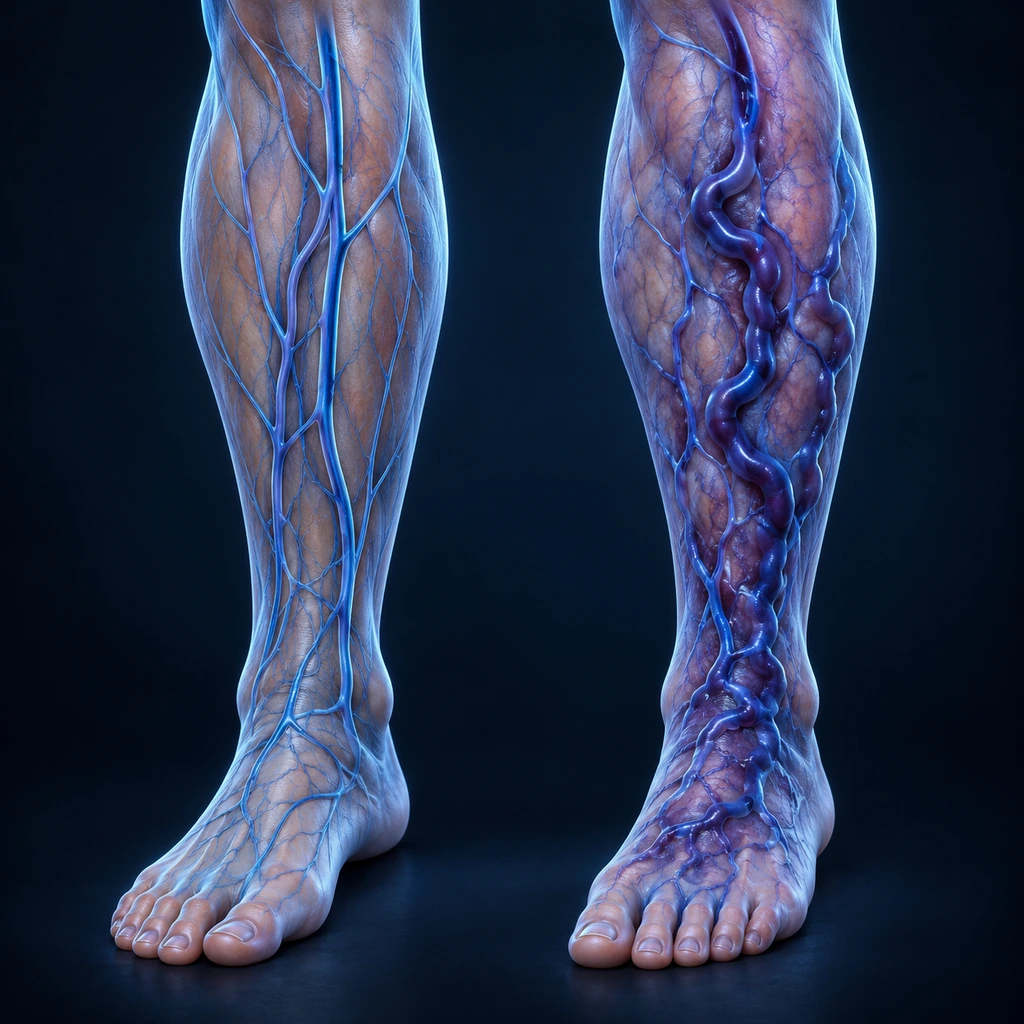
- Pooling of blood in legs with standing — blue/purple discoloration
- Tremulousness, anxiety-like symptoms
- Sleep disturbance
- Menstrual worsening of symptoms
Subtypes
- Neuropathic postural orthostatic tachycardia syndrome. Small-fiber autonomic neuropathy with impaired lower-extremity vasoconstriction. Often post-viral.
- Hyperadrenergic postural orthostatic tachycardia syndrome. Elevated standing norepinephrine, tremulousness, episodic hypertension.
- Hypovolemic postural orthostatic tachycardia syndrome. Reduced blood volume with impaired renin-aldosterone response.
- Autoimmune postural orthostatic tachycardia syndrome. Antibodies against adrenergic or muscarinic receptors; overlap with autoimmune conditions.
- Most patients have mixed pictures.
Triggers
- Viral infection — COVID-19, Epstein-Barr virus, influenza, and others.
- Surgery or trauma, particularly with prolonged bed rest.
- Pregnancy.
- Puberty — many cases emerge in teens.
- Concussion or head injury.
- Ehlers-Danlos/hypermobility spectrum disorders — common overlap.
- Vaccination — rare but documented.
Clinical Evaluation
- Detailed orthostatic vitals or 10-minute active stand test.
- Tilt-table test (gold standard) for definitive diagnosis or atypical cases.
- CBC, CMP, TSH, cortisol (to exclude adrenal insufficiency), ferritin, B12, vitamin D.
- Electrocardiogram (EKG) and echocardiogram to exclude structural heart disease.
- Standing catecholamines in hyperadrenergic subtype.
- Assessment for mast-cell activation, autoimmunity, and hypermobility where clinical suspicion warrants.
Treatment
- Volume expansion. 2–3 L of water and 10–12 g of salt (sodium chloride) a day in the 2015 Heart Rhythm Society consensus (Sheldon 2015); at least 2–3 L of water and 3–10 g of sodium a day in the 2019 NIH expert consensus (Vernino 2021).
- Compression garments. Waist-high 20–40 mmHg compression reduces venous pooling substantially.
- Beta-blockers. Low-dose propranolol or metoprolol for tachycardia.
- Ivabradine. Selective sinoatrial-node blocker, particularly effective in inappropriate sinus tachycardia overlap.
- Midodrine. Alpha-1 agonist increasing vascular tone.
- Fludrocortisone. Mineralocorticoid for volume expansion.
- Droxidopa. Synthetic norepinephrine precursor.
- Pyridostigmine. Enhances parasympathetic tone.
- Clonidine or methyldopa in hyperadrenergic subtype.
- Selective serotonin reuptake inhibitors (SSRIs)/serotonin-norepinephrine reuptake inhibitors (SNRIs) in some cases.
- IVIG or immune modulation in autoimmune postural orthostatic tachycardia syndrome.
Lifestyle and Daily Strategies
- Reclined aerobic exercise — recumbent bike, rowing, or swimming — to rebuild cardiovascular conditioning without triggering upright symptoms. The Dallas/CHOP protocols specifically use 3–6 months of graded reclined exercise.
- Raise head of bed by 4 inches to reduce morning symptoms.
- Counterpressure maneuvers — leg crossing, squatting — to abort presyncope.
- Cool room temperature, avoid hot showers and saunas.
- Small, frequent meals to avoid postprandial pooling.
- Pacing analogous to myalgic encephalomyelitis/chronic fatigue syndrome (ME/CFS) if post-exertional worsening is present.
Table of Contents
Key Research Papers
- Freeman R, Wieling W, Axelrod FB, et al. (2011). Consensus statement on the definition of orthostatic hypotension, neurally mediated syncope and the postural tachycardia syndrome. Clinical Autonomic Research — PubMed PMID: 21431947
- Sheldon RS, Grubb BP 2nd, Olshansky B, et al. (2015). 2015 heart rhythm society expert consensus statement on the diagnosis and treatment of postural tachycardia syndrome, inappropriate sinus tachycardia, and vasovagal syncope. Heart Rhythm — PubMed PMID: 25980576
- Vernino S, Bourne KM, Stiles LE, et al. (2021). Postural orthostatic tachycardia syndrome (POTS): State of the science and clinical care from a 2019 National Institutes of Health Expert Consensus Meeting - Part 1. Autonomic Neuroscience — PubMed PMID: 34144933
- Raj SR, Arnold AC, Barboi A, et al. (2021). Long-COVID postural tachycardia syndrome: an American Autonomic Society statement. Clinical Autonomic Research — PubMed PMID: 33740207
- Raj SR, Black BK, Biaggioni I, et al. (2009). Propranolol decreases tachycardia and improves symptoms in the postural tachycardia syndrome: less is more. Circulation — PubMed PMID: 19687359
- Taub PR, Zadourian A, Lo HC, et al. (2021). Randomized Trial of Ivabradine in Patients With Hyperadrenergic Postural Orthostatic Tachycardia Syndrome. Journal of the American College of Cardiology — PubMed PMID: 33602468
- Bourne KM, Sheldon RS, Hall J, et al. (2021). Compression Garment Reduces Orthostatic Tachycardia and Symptoms in Patients With Postural Orthostatic Tachycardia Syndrome. Journal of the American College of Cardiology — PubMed PMID: 33478652
- Fu Q, Vangundy TB, Shibata S, et al. (2011). Exercise training versus propranolol in the treatment of the postural orthostatic tachycardia syndrome. Hypertension (Dallas, Tex. — PubMed PMID: 21690484
PubMed Topic Searches
Curated PubMed topic searches on Postural Orthostatic Tachycardia Syndrome (POTS). Each link opens a live PubMed query so the result set stays current as new studies are indexed.
- PubMed: Topic search: Postural orthostatic tachycardia syndrome review
- PubMed: Topic search: POTS diagnostic criteria consensus
- PubMed: Topic search: POTS hyperadrenergic
- PubMed: Topic search: POTS neuropathic hypovolemic
- PubMed: Topic search: Tilt table test POTS
- PubMed: Topic search: Midodrine POTS
- PubMed: Topic search: Ivabradine POTS
- PubMed: Topic search: Fludrocortisone POTS
- PubMed: Topic search: Ehlers-Danlos POTS
- PubMed: Topic search: Compression garments orthostatic
- PubMed: Topic search: POTS salt fluid loading
- PubMed: Topic search: POTS dysautonomia review
Connections
- Neurology
- Postural Orthostatic Tachycardia Syndrome Subtypes
- Postural Orthostatic Tachycardia Syndrome/Mast Cell Activation Syndrome/Ehlers-Danlos Syndrome Triad
- Medications Guide
- Compression & Exercise
- Salt & Hydration
- Vagus Nerve & Retraining
- Low Dose Naltrexone for Postural Orthostatic Tachycardia Syndrome
- Tilt Table Test
- Postural Orthostatic Tachycardia Syndrome Diet
- Mast Cell Activation Syndrome
- Myalgic Encephalomyelitis/Chronic Fatigue Syndrome
- Ehlers-Danlos Syndrome
- Fibromyalgia
- Hashimoto's Thyroiditis
- Small Intestinal Bacterial Overgrowth
- Lightheadedness on Standing
- Brain Fog
- Magnesium
Featured Videos