⚠ Evidence warning: Clinical trials or other evidence do not support the claim that regular saline infusions through a PICC or port are genuinely life-restoring for a subset of patients with refractory postural orthostatic tachycardia syndrome. This page keeps it as a report of what people, websites or other media say.
Postural Orthostatic Tachycardia Syndrome (POTS) Subtypes: Hyperadrenergic, Neuropathic, and Hypovolemic
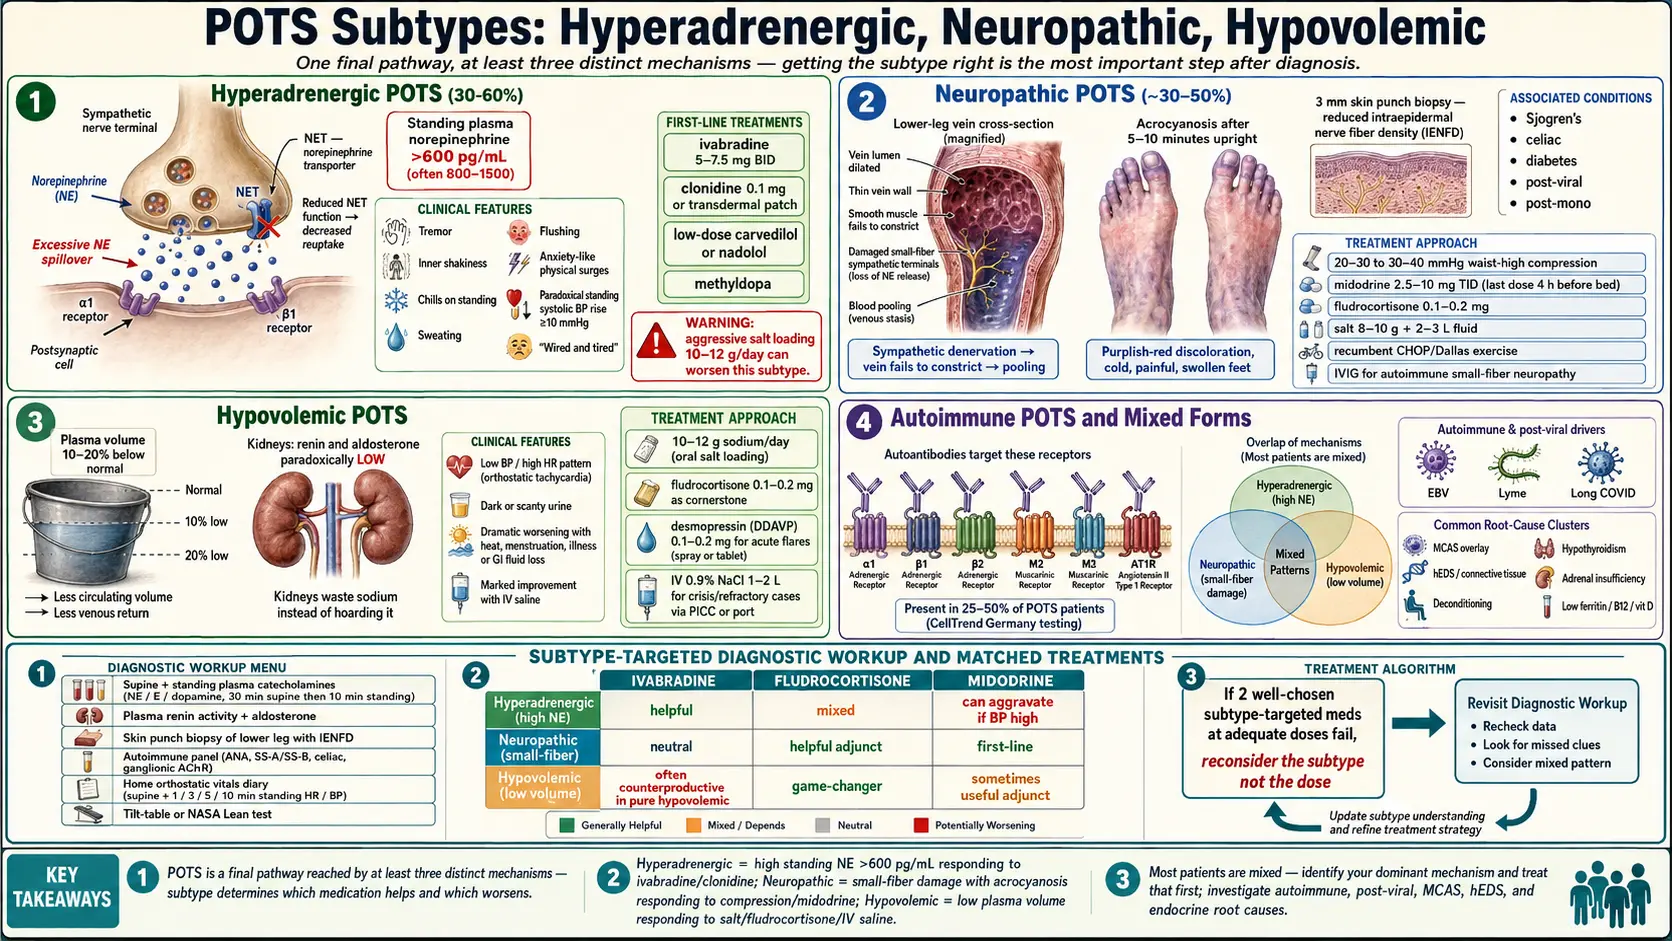
Table of Contents
- Why Subtypes Matter
- Hyperadrenergic Postural Orthostatic Tachycardia Syndrome
- Neuropathic Postural Orthostatic Tachycardia Syndrome
- Hypovolemic Postural Orthostatic Tachycardia Syndrome
- Overlap and Mixed Forms
- How the Subtypes Are Told Apart
- Why the Treatment Difference Matters
- Underlying Drivers Linked to Each Subtype
- Key Research Papers
- Connections
- Featured Videos
1. Why Subtypes Matter
If you’ve been diagnosed with postural orthostatic tachycardia syndrome (POTS) and handed the same generic advice as everyone else in the clinic — drink more water, add salt, wear compression socks, take a beta blocker — and it’s not working, you are not failing. You may simply have been matched to the wrong protocol for your subtype.
Postural orthostatic tachycardia syndrome is not one disease. It’s a final common pathway — an abnormally large heart-rate response to standing — produced by at least three distinct mechanisms. Hyperadrenergic postural orthostatic tachycardia syndrome is driven by excess sympathetic nerve output. Neuropathic postural orthostatic tachycardia syndrome is driven by small-fiber nerve damage in the legs, causing blood to pool downward. Hypovolemic postural orthostatic tachycardia syndrome is driven by low circulating plasma volume and broken volume regulation.
Each mechanism responds best to a different medication and a different lifestyle emphasis. A drug that calms one subtype can actively worsen another. That is why the cookie-cutter approach fails so many patients — and why figuring out your dominant subtype is arguably the most important step after diagnosis.
2. Hyperadrenergic Postural Orthostatic Tachycardia Syndrome
The 2015 Heart Rhythm Society expert consensus statement says the hyperadrenergic form occurs in up to 50% of patients; a 2007 Mayo Clinic review of 152 patients documented a hyperadrenergic status in 29.0%. The defining lab feature: standing plasma norepinephrine above 600 pg/mL (often 800–1500+), compared with a normal supine baseline. The nervous system behaves as if it’s in chronic fight-or-flight.
Typical clinical picture:
- Tremor, inner shakiness, and chills on standing
- Sweating and flushing, sometimes with migraines
- Anxiety-like surges that are physical, not psychological, in origin
- Paradoxical hypertension on standing — systolic blood pressure (BP) rises ≥10 mmHg upright (most postural orthostatic tachycardia syndrome patients drop)
- Heart-pounding awareness, palpitations, feeling “wired and tired”
Underlying mechanisms include norepinephrine transporter (NET) deficiency, autoimmune activation of adrenergic receptors, and central sympathetic dysregulation. Many patients trace symptom onset to a viral illness, head injury, or significant stressor.
Best-Responding Medications
- Ivabradine (5–7.5 mg twice daily) — slows sinus node firing without touching blood pressure. First choice for many hyperadrenergic patients.
- Clonidine (0.1 mg once or twice daily, or 0.1 mg transdermal patch weekly) — central alpha-2 agonist, dials down sympathetic outflow directly. Also helpful for sleep.
- Low-dose beta blockers — carvedilol (3.125–6.25 mg twice daily), which also has vasodilating action, or nadolol (10–20 mg daily). The 2015 Heart Rhythm Society statement notes that low-dose propranolol (10–20 mg by mouth) acutely lowers standing heart rate and improves symptoms in postural orthostatic tachycardia syndrome, that higher doses of propranolol are less well tolerated, and that other beta blockers have not been studied.
- Methyldopa in a subset whose daytime blood pressure runs high.
What Often Backfires
Aggressive salt loading (10–12 g/day) and fludrocortisone — the standard playbook for the other two subtypes — can push standing blood pressure higher and intensify symptoms in hyperadrenergic patients. In this subtype, standing blood pressure readings show whether added salt is pushing blood pressure higher.
3. Neuropathic Postural Orthostatic Tachycardia Syndrome
In neuropathic postural orthostatic tachycardia syndrome, the peripheral sympathetic nerves that normally squeeze the leg veins on standing are partially damaged. Blood pools in the lower body. Venous return drops. The heart compensates by racing.
Typical picture:
- Purplish-red discoloration of the feet and lower legs after a few minutes standing (acrocyanosis)
- Legs feel heavy and swollen; cold feet are common
- Symptoms much better when recumbent; worse in heat and after meals
- Heart rate rises sharply but blood pressure often stays near normal
- Often preceded by a viral infection, mononucleosis, or diagnosed alongside Sjögren’s, celiac disease, or diabetes
The gold-standard confirmation is a skin punch biopsy from the lower leg, examined for intraepidermal nerve fiber density. Reduced density confirms small-fiber neuropathy (SFN), which is present in an estimated 30–50% of postural orthostatic tachycardia syndrome patients and is the signature of this subtype.
Best-Responding Medications and Interventions
- High-grade compression — 20–30 or 30–40 mmHg, waist-high or at minimum thigh-high. Knee-high alone is inadequate for true neuropathic pooling.
- Recumbent exercise (rowing, recumbent bike, swimming) — the Levine/Dallas protocol rebuilds cardiac and lower-body muscle pump capacity without triggering symptoms; the protocol moves on to upright exercise after 2–3 months.
- Midodrine (2.5–10 mg up to three times daily, last dose no later than 4 hours before bedtime) — peripheral alpha-1 agonist, directly constricts the leaky leg vasculature.
- Fludrocortisone (0.1–0.2 mg daily) — expands plasma volume, increases vascular sensitivity to norepinephrine.
- Salt and fluid loading — the 2015 Heart Rhythm Society statement says the consumption of up to 2–3 L of water and 10–12 g of salt (sodium chloride) daily “may be considered” for postural orthostatic tachycardia syndrome (a Class IIb recommendation).
If autoimmunity is driving the small-fiber damage (biopsy plus positive antibodies), some centers use IVIG in refractory cases.
4. Hypovolemic Postural Orthostatic Tachycardia Syndrome
Here the problem is plumbing volume, not nerves or adrenaline. Formal testing (radiolabeled albumin or red-cell mass) often shows plasma volume deficits of 10–20%. The renin-aldosterone axis, which should correct the shortfall, paradoxically runs low instead of high — so the kidneys waste salt when they should be hoarding it.
Typical picture:
- Classic low blood pressure, high heart rate orthostatic pattern
- Dark or scanty urine despite reasonable fluid intake
- Marked worsening with heat, menstruation, illness, or any gastrointestinal (GI) fluid loss
- Dramatic, immediate improvement from intravenous (IV) saline — a key clinical clue
- Salt cravings that feel physiological, not habit
Best-Responding Medications and Interventions
- High-dose salt: about 10–12 g of salt (sodium chloride) a day — the 2015 Heart Rhythm Society statement describes this, “if tolerated, using salt tablets, if necessary,” together with at least 2–3 L of water a day, for patients known or strongly suspected to have low blood volume. Food, salt tablets and commercial electrolyte mixes are the usual sources.
- Fludrocortisone (0.1–0.2 mg daily) — used to boost sodium retention and expand plasma volume, although the 2015 Heart Rhythm Society statement notes that its effectiveness has not been tested in randomized clinical trials. Potassium is monitored during use.
- Desmopressin (DDAVP 0.1–0.2 mg orally) for acute flares; it reduces free-water loss, and in a 2012 crossover trial (30 patients, a single 0.2 mg dose), it lowered standing heart rate and improved symptoms over the 4 hours measured, and the authors wrote that its safety would need to be examined before it could be recommended for routine treatment. Low blood sodium is a recognised risk of desmopressin, particularly with repeated use.
- Intravenous saline (1–2 L of 0.9% normal saline) for crisis or severe flares. The 2015 Heart Rhythm Society statement rates an acute infusion of up to 2 L as reasonable for short-term decompensation (Class IIa) but rates regular infusions as not recommended (Class III): “Regular intravenous infusions of saline in patients with POTS are not recommended in the absence of evidence, and chronic or repeated intravenous cannulation is potentially harmful,” since long-term infusions usually require a chronic central venous catheter. Some patients with refractory disease nonetheless receive weekly or twice-weekly infusions through a PICC or port — a last-resort measure but genuinely life-restoring for a subset.
Midodrine and beta blockers can be layered on but are rarely sufficient alone in this subtype, where expanding blood volume is the central aim.
5. Overlap and Mixed Forms
Here is the honest reality nobody puts on the intake sheet: most postural orthostatic tachycardia syndrome patients have features of more than one subtype. A patient can have mild small-fiber neuropathy in the legs and a norepinephrine spike on standing. Another can be hypovolemic and have secondary hyperadrenergic compensation.
For this reason the dominant mechanism — the one contributing most to the worst symptoms — can matter more than a rigid subtype label. Lab tests and orthostatic vitals indicate a starting point, and the response to a first medication trial adds to the picture.
When two subtype-targeted medications at adequate doses have not helped, one possible explanation is that the treatment is aimed at the wrong mechanism rather than given at the wrong dose.
6. How the Subtypes Are Told Apart
No single test identifies the subtype; the overall pattern does. The evaluations used include:
- Supine and standing plasma catecholamines (norepinephrine, epinephrine, dopamine) — 30 minutes supine, then 10 minutes standing, drawn at each timepoint. A standing norepinephrine >600 pg/mL strongly supports hyperadrenergic postural orthostatic tachycardia syndrome.
- Plasma renin activity and aldosterone — inappropriately low values despite orthostasis support hypovolemic postural orthostatic tachycardia syndrome.
- Skin punch biopsy (lower leg, 3 mm) with intraepidermal nerve fiber density analysis — confirms or rules out small-fiber neuropathy and points toward neuropathic postural orthostatic tachycardia syndrome.
- Comprehensive autoimmune panel — antinuclear antibody (ANA), Sjögren’s SS-A/SS-B, celiac antibodies, ganglionic AChR antibody, and (where available) adrenergic and muscarinic receptor antibodies.
- Home orthostatic vitals diary — supine and 1-, 3-, 5-, and 10-minute standing HR and blood pressure, morning and afternoon, for two weeks. Patterns emerge that single in-office readings miss.
- Formal tilt-table or NASA Lean Test — documents the orthostatic response in a standardized way. See Tilt-Table and NASA Lean Test.
Not every clinic orders all of these; specialist autonomic centers are the most likely to complete the full workup.
7. Why the Treatment Difference Matters
Concrete examples of why mismatched treatment fails:
- Ivabradine is described by clinicians as most helpful in hyperadrenergic postural orthostatic tachycardia syndrome because it directly slows the overactive sinus node. In pure neuropathic postural orthostatic tachycardia syndrome it helps less — the tachycardia is a compensation for pooled blood, not a primary driver, and slowing the heart without addressing the pooling can worsen presyncope.
- Fludrocortisone is described as most helpful in hypovolemic postural orthostatic tachycardia syndrome and useful in neuropathic. In hyperadrenergic postural orthostatic tachycardia syndrome it can push an already-elevated standing blood pressure into headache, chest tightness, and worse symptoms.
- Midodrine shines for neuropathic pooling and is reasonable in hypovolemic postural orthostatic tachycardia syndrome as add-on. In hyperadrenergic postural orthostatic tachycardia syndrome with supine hypertension it can trigger dangerous overnight blood pressure spikes.
- Propranolol at low doses is often well-tolerated in hyperadrenergic postural orthostatic tachycardia syndrome. In neuropathic postural orthostatic tachycardia syndrome with already-marginal cardiac output on standing, even a small beta blockade can worsen fatigue.
- High-dose salt rescues hypovolemic patients and helps neuropathic patients; it aggravates a subset of hyperadrenergic patients.
For a deeper dive into individual drugs, doses, and titration, see the Medications Guide.
8. Underlying Drivers Linked to Each Subtype
Subtype identification isn’t the end of the workup. Each subtype has its own short list of root causes that, if found and treated, can shrink or resolve the postural orthostatic tachycardia syndrome itself.
- Autoimmune drivers — adrenergic alpha-1, beta-1, beta-2 receptor antibodies; muscarinic M2, M3 antibodies; angiotensin II type 1 receptor (AT1R) antibodies. Strongest association with hyperadrenergic and some neuropathic cases. Testing is offered only by specialty laboratories. Positive results have been used as grounds for trials of IVIG or plasmapheresis.
- Post-infectious triggers — Epstein-Barr virus reactivation, Lyme and co-infections, post-viral syndromes (including long-haul post-viral illness after SARS-CoV-2 infection). Common prelude to neuropathic and mixed subtypes.
- Mast Cell Activation Syndrome (MCAS) — flushing, food/medication reactivity, and unexplained anaphylactoid episodes suggest mast cell activation syndrome overlay, especially in hyperadrenergic presentations. See the postural orthostatic tachycardia syndrome-MCAS-EDS Triad.
- Ehlers-Danlos syndrome / hypermobility spectrum disorder — connective-tissue laxity means veins don’t hold their tone. Strongly associated with neuropathic and mixed postural orthostatic tachycardia syndrome.
- Deconditioning — prolonged bedrest from any illness reduces plasma volume and cardiac chamber size. Contributes to all subtypes and is almost always partially reversible with graded recumbent exercise.
- Endocrine contributors — hypothyroidism, adrenal insufficiency, low ferritin, B12 deficiency, vitamin D deficiency. Cheap to screen, sometimes dramatically impactful to correct.
Key Research Papers
- Raj SR, et al. Postural Tachycardia Syndrome (POTS). Circulation. 2013. — doi:10.1161/CIRCULATIONAHA.112.144501
- Sheldon RS, et al. 2015 Heart Rhythm Society expert consensus statement on the diagnosis and treatment of postural tachycardia syndrome, inappropriate sinus tachycardia, and vasovagal syncope. Heart Rhythm. 2015;12(6):e41-e63. — doi:10.1016/j.hrthm.2015.03.029
- Miller AJ, Raj SR. Pharmacotherapy for postural tachycardia syndrome. Auton Neurosci. 2018;215:28-36. — PubMed PMID: 29753556
- Fedorowski A. Postural orthostatic tachycardia syndrome: clinical presentation, aetiology and management. J Intern Med. 2019;285(4):352-366. — PubMed PMID: 30372565
PubMed Topic Searches
Curated PubMed topic searches — each link opens a live query so you always see the most recent literature.
- PubMed: Hyperadrenergic POTS and norepinephrine
- PubMed: Neuropathic POTS and small-fiber neuropathy
- PubMed: Hypovolemic POTS and plasma volume
- PubMed: POTS autoimmune antibodies
- PubMed: POTS, clonidine, and ivabradine
- PubMed: POTS subtype classification
- PubMed: POTS, fludrocortisone, and midodrine
- PubMed: POTS plasma volume and renin-aldosterone
Connections
- Neurology
- Postural Orthostatic Tachycardia Syndrome Overview
- Medications Guide
- Postural Orthostatic Tachycardia Syndrome/Mast Cell Activation Syndrome/Ehlers-Danlos Syndrome Triad
- Tilt Table Test
- Compression and Exercise Program
- Salt and Hydration Protocol
- Vagus Nerve and Autonomic Retraining
- Low Dose Naltrexone for Postural Orthostatic Tachycardia Syndrome
- Mast Cell Activation Syndrome
- Small Intestinal Bacterial Overgrowth
- Myalgic Encephalomyelitis/Chronic Fatigue Syndrome
- Fibromyalgia
- Ehlers-Danlos Syndrome
- Potassium
- Magnesium
- Fatigue
- Brain Fog
- Vestibular Migraine