Low Dose Naltrexone, Abilify & Experimental Therapies for Myalgic Encephalomyelitis/Chronic Fatigue Syndrome (ME/CFS)
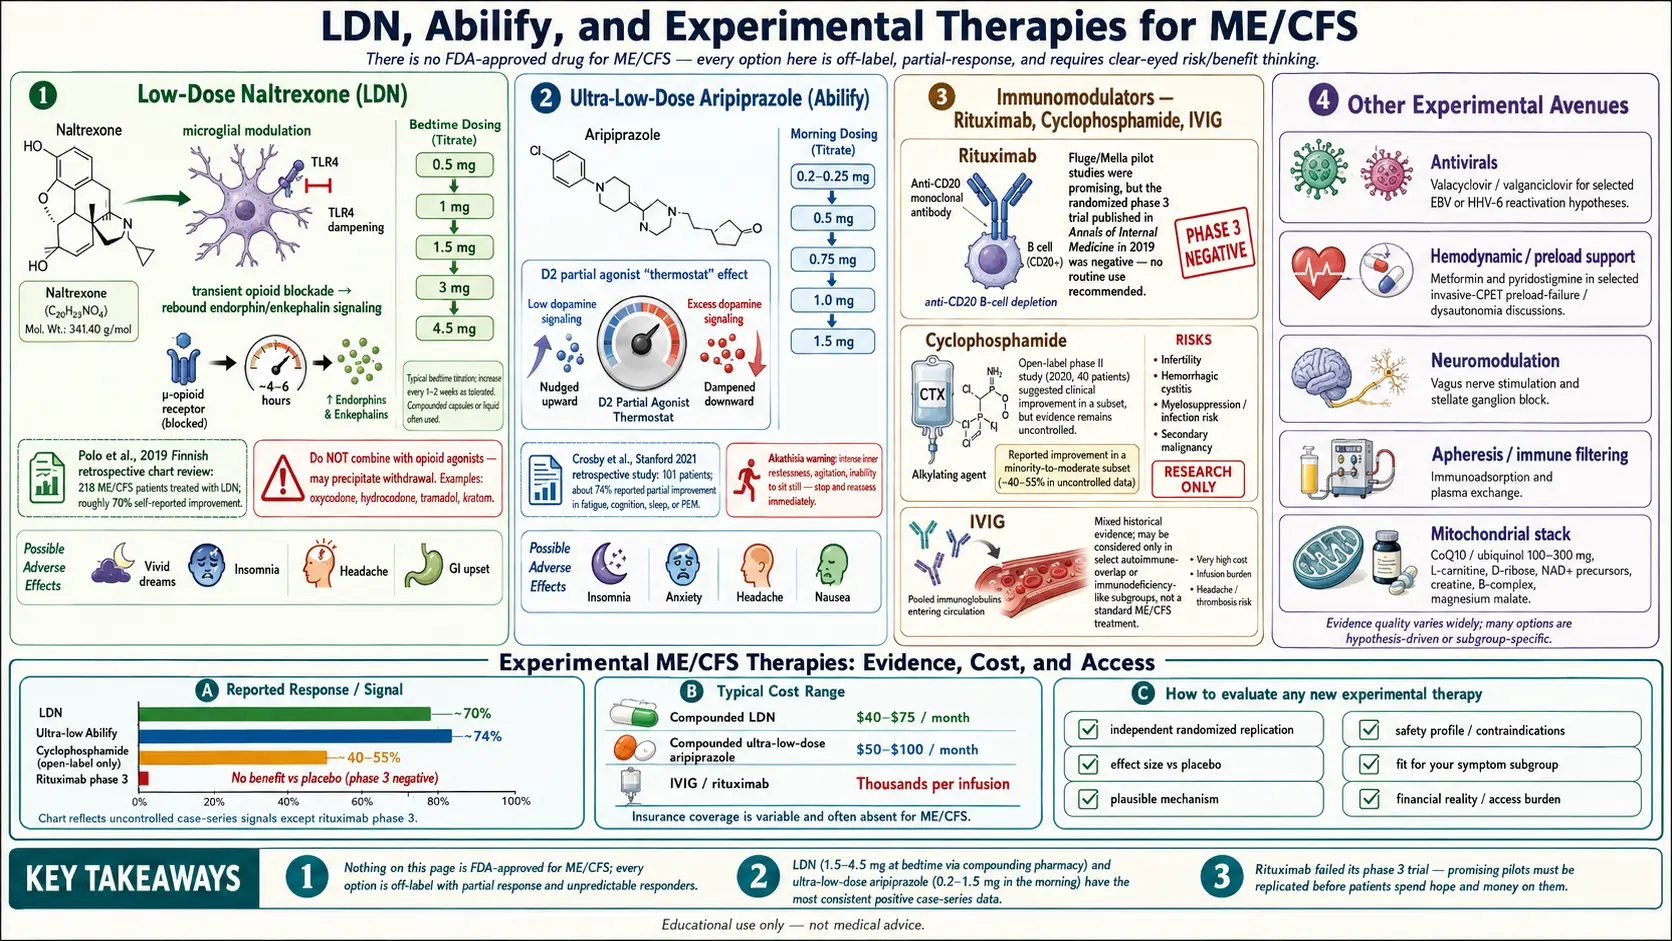
Table of Contents
- The Honest Framing — Nothing Here Is U.S. Food and Drug Administration-Approved
- Low-Dose Naltrexone
- Ultra-Low-Dose Aripiprazole
- Rituximab — The Norwegian Story
- Cyclophosphamide
- IVIG (Intravenous Immunoglobulin)
- Metformin and Pyridostigmine
- Antivirals — Valacyclovir and Valganciclovir
- Immunoadsorption
- Mitochondrial Support — Coenzyme Q10, D-Ribose, Reduced Nicotinamide Adenine Dinucleotide
- Vagus Nerve Stimulation and Stellate Ganglion Block
- Plasma Exchange
- How to Evaluate a New Experimental Therapy
- Key Research Papers
- Connections
- Featured Videos
The Honest Framing — Nothing Here Is U.S. Food and Drug Administration-Approved
Before the drug-by-drug rundown, a piece of framing that most articles skip: there is no U.S. Food and Drug Administration-approved medication for myalgic encephalomyelitis/chronic fatigue syndrome (ME/CFS). Every therapy on this page is off-label, compassionate-use, or strictly experimental. Some have small, encouraging trials behind them. Others have one promising Phase 2 result and one crushing Phase 3 failure. A few rest on case reports and physician experience alone.
That does not mean these options are useless. It means a few facts are worth knowing up front: response rates are partial, responders cannot be predicted in advance, side effects matter, and cost and access are real obstacles. A 30–40% response rate looks tiny in a cancer trial but can be life-changing in a disease where the alternative is nothing. What follows is a patient-facing map of the terrain — what each option actually is, what the evidence says, and what it typically costs a real person to try.
None of this replaces a long-term myalgic encephalomyelitis-literate physician; it is background for better-informed conversations with one.
Low-Dose Naltrexone
What it is. Naltrexone is an opioid-receptor blocker originally approved at 50 mg daily to treat opioid and alcohol dependence. At one-tenth that dose or less — typically 1.5 to 4.5 mg at bedtime — it does something very different. Low-dose naltrexone appears to dampen neuroinflammation rather than block opioids in any meaningful clinical way.
How it works (best current theory). At these tiny doses, naltrexone binds Toll-like receptor 4 (TLR4) on microglia, the immune cells of the brain. In myalgic encephalomyelitis/chronic fatigue syndrome, post-viral syndromes, fibromyalgia, and long-illness states generally, microglia appear to be stuck in a chronically activated, pro-inflammatory mode. Blocking TLR4 helps quiet them. There is also a brief transient opioid blockade during the few hours the drug is in your system, which is thought to trigger a rebound rise in endorphins and enkephalins — a compensatory endorphin surge. Both mechanisms are plausible; neither is fully proven.
The evidence in myalgic encephalomyelitis/chronic fatigue syndrome. The most-cited study is Polo and colleagues (2019), a Finnish retrospective chart review of 218 myalgic encephalomyelitis/chronic fatigue syndrome patients treated with low dose naltrexone (LDN). Roughly 70% reported meaningful improvement in fatigue, cognition, pain, and sleep. Retrospective chart reviews are the weakest form of clinical evidence — there is no placebo arm and recall bias is real — but the signal is consistent with a small randomized, double-blind, placebo-controlled crossover trial in 31 women with fibromyalgia from Jarred Younger's group (University of Alabama at Birmingham) and decades of anecdotal reports from myalgic encephalomyelitis/chronic fatigue syndrome specialists.
Larger fibromyalgia trials. Two later placebo-controlled trials of low dose naltrexone in women with fibromyalgia, a condition that often overlaps with myalgic encephalomyelitis/chronic fatigue syndrome, did not show a clear benefit for pain. A trial in Denmark (2024) gave 6 mg daily for 12 weeks to 99 women: pain fell by 1.3 points on a 0–10 scale with low dose naltrexone and 0.9 points with placebo, a difference of 0.34 points (p=0.27); the authors noted it might improve memory problems and called for trials of that. A 2026 trial gave 4.5 mg daily to 98 women over 12 months and found no clinically meaningful benefit over placebo for pain-related outcomes. Both trials found the drug well tolerated, with side-effect rates similar to placebo.
How it is actually used.
- Starting dose: 0.5 mg or 1 mg at bedtime. Most myalgic encephalomyelitis/chronic fatigue syndrome patients are sensitive to medication and crash on full starting doses.
- Titration: increase by 0.5–1 mg every 1–2 weeks, as tolerated, toward a target of 3–4.5 mg. Some patients do best at 1.5 or 2 mg and never go higher.
- Timing: bedtime is traditional, but vivid dreams and insomnia are the single most common reason people quit. People who have this problem often move the dose to the morning — the mechanism does not appear to depend on timing.
- Trial length: the usual trial is at least 3 months at target dose before judging the effect. Some responders take 4–6 months to bloom.
Compounding and cost. The 50 mg naltrexone tablet cannot be split accurately to 1.5 mg. Capsules or a sublingual liquid are made by a compounding pharmacy. In the U.S., compounded low dose naltrexone typically runs $40–$75 per month cash. Insurance rarely covers it because the use is off-label, but a number of national and regional compounding pharmacies ship nationwide with a prescription. UK and EU patients often pay less.
Side effects. Most common: vivid dreams, insomnia for the first 1–2 weeks, mild headaches. Less common: gastrointestinal (GI) upset, anxiety spike on the first few doses. Serious side effects are rare at these doses.
The opioid conflict. This is critical. Naltrexone blocks opioid receptors, so it will precipitate immediate withdrawal in anyone taking prescription opioids (oxycodone, hydrocodone, tramadol, kratom, etc.) and will blunt their pain relief. For anyone taking opioids for any reason, low dose naltrexone is not used until they have been opioid-free for at least a week. Tramadol is a particular problem because many patients forget it counts. Non-opioid pain medications (nonsteroidal anti-inflammatory drugs (NSAIDs), gabapentin, duloxetine, low-dose amitriptyline) do not carry this conflict with low dose naltrexone.
For a deeper dive on dosing, sourcing, and protocols, see the main Low-Dose Naltrexone article. Many myalgic encephalomyelitis/chronic fatigue syndrome patients with comorbid fibromyalgia or postural orthostatic tachycardia syndrome (POTS) also find the disease-specific pages useful: low dose naltrexone for Fibromyalgia and low dose naltrexone for postural orthostatic tachycardia syndrome.
Ultra-Low-Dose Aripiprazole
What it is. Aripiprazole is a second-generation antipsychotic approved at 10–30 mg daily for schizophrenia and bipolar disorder. The myalgic encephalomyelitis/chronic fatigue syndrome application uses ultra-low doses of 0.2 to 2 mg — roughly one-tenth to one-twentieth the psychiatric dose.
How it works (theory). Aripiprazole is a partial agonist at the dopamine D2 receptor. Depending on ambient dopamine tone, it either nudges the receptor up or dampens it down — it behaves like a thermostat rather than a switch. At ultra-low doses, the hypothesis is that it modestly increases dopamine signaling in a brain that has become hypo-dopaminergic from chronic neuroinflammation. There may also be microglial effects shared with other antipsychotics. Nobody fully understands why it would help myalgic encephalomyelitis/chronic fatigue syndrome, which is part of why most rheumatologists and neurologists have never heard of this use.
The evidence. The key publication is a Stanford case series by Crosby and colleagues (2021), reporting on 101 myalgic encephalomyelitis/chronic fatigue syndrome patients treated with ultra-low-dose aripiprazole by a single clinician. Roughly 74% reported at least partial improvement, with benefits most pronounced for cognitive fog and fatigue. This is one uncontrolled case series from one clinic. Placebo and selection bias are unaccounted for, and no randomized trial has yet replicated the finding.
How it is used.
- Starting dose: 0.2–0.25 mg in the morning. This requires compounding (commercial aripiprazole tablets come in 2, 5, 10 mg).
- Titration: adjust by 0.25 mg every 1–2 weeks. Most responders settle in the 0.5–1.5 mg range. Going higher often worsens symptoms — this is unusual for a drug and part of why ultra-low dosing matters.
- Timing: morning. Aripiprazole has a long half-life (~75 hours), which also means side effects build over weeks.
Compounded cost. $50–$100 per month cash, similar to low dose naltrexone.
Side effects and risks. The main risk is akathisia — an intensely unpleasant inner restlessness, a need to keep moving, often misidentified as anxiety. It can appear at any dose and is the most common reason people stop. Other antipsychotic-class warnings (weight gain, metabolic syndrome, tardive dyskinesia) are vanishingly rare at these doses and short durations, but not zero. Long-term safety data at ultra-low doses does not exist. Knowing what akathisia feels like matters for anyone starting aripiprazole, because it is the side effect that most often ends treatment.
Rituximab — The Norwegian Story
What it is. Rituximab is a monoclonal antibody that depletes CD20-positive B cells. It is U.S. Food and Drug Administration-approved for non-Hodgkin lymphoma, rheumatoid arthritis, and several autoimmune conditions. The myalgic encephalomyelitis/chronic fatigue syndrome story started by accident.
The origin. Norwegian oncologists Øystein Fluge and Olav Mella saw major relief of myalgic encephalomyelitis/chronic fatigue syndrome symptoms during cancer chemotherapy in one patient who had both myalgic encephalomyelitis/chronic fatigue syndrome and lymphoma. That led to a pilot study of rituximab, which showed a clear clinical response in three patients, and then to small controlled trials.
The evidence arc.
- Fluge & Mella, PLoS ONE 2011. Randomized, placebo-controlled pilot in 30 patients. Roughly two-thirds of the rituximab arm reported meaningful improvement, often delayed by months: major or moderate response was seen in 10 of 15 patients (67%) on rituximab versus 2 of 15 (13%) on placebo, with responses starting 2 to 7 months after treatment. The primary end point, the fatigue score 3 months after treatment, was negative. The myalgic encephalomyelitis (ME) community was electrified.
- Open-label phase 2 (2015). Extended dosing confirmed the signal in 29 patients with response rates around 64%.
- Phase 3 (Fluge, Annals of Internal Medicine, 2019). Large multicenter randomized controlled trial (RCT), 151 patients, proper blinding. Negative. Rituximab did not outperform placebo: overall response rates were 26.0% on rituximab and 35.1% on placebo, and serious adverse events occurred in 26.0% of the rituximab group versus 18.9% of the placebo group. The field deflated.
What to make of this. The Phase 3 was well-run and reasonably sized. The honest reading is that rituximab is not a broadly effective myalgic encephalomyelitis/chronic fatigue syndrome drug. A minority of clinicians still argue there may be a B-cell-driven subgroup that responded in the earlier trials and got diluted out of the bigger one — but that remains hypothesis, not evidence. The Phase 3 result leaves no trial support for rituximab in routine myalgic encephalomyelitis/chronic fatigue syndrome use. It is worth knowing about because the story illustrates how a single positive trial can fail to hold up when it is repeated on a larger scale.
Cyclophosphamide
What it is. A broadly immunosuppressive chemotherapy drug, used for aggressive autoimmune disease (lupus nephritis, vasculitis) and some cancers.
The evidence. The same Norwegian group, with Fluge and Mella among the authors, reported an open-label Phase 2 study in 40 myalgic encephalomyelitis/chronic fatigue syndrome patients (Rekeland et al., 2020), given six intravenous infusions four weeks apart. The overall response rate by fatigue score was 55.0% (22 of 40 patients), and at extended follow-up to 4 years 68% of responders (15 of 22) were still in remission. No placebo arm. No large randomized controlled trial has followed.
Why it is rarely used. Cyclophosphamide is genuinely toxic: infertility risk, bone marrow suppression, hemorrhagic cystitis, long-term secondary cancer risk. The risk-benefit math is hard to justify outside a trial, especially when we cannot yet predict responders. It remains of biological interest because it suggests an immune-driven subgroup exists, but it is not used as a routine off-label option.
Six-year follow-up. In a 2024 report from the same group (Rekeland et al., 2024), 44.1% of the cyclophosphamide patients scored at least 70 on the Short Form 36 physical function scale (SF-36 PF) after six years, compared with 27.6% of the rituximab group and 20.4% of the placebo group from the separate rituximab trial. The researchers state that cyclophosphamide “carries toxicity concerns and should not be used for ME/CFS patients outside clinical trials.”
IVIG (Intravenous Immunoglobulin)
What it is. Pooled human antibodies from thousands of donors, infused over several hours. Used in primary immunodeficiency, autoimmune neurologic disease (chronic inflammatory demyelinating polyneuropathy (CIDP), myasthenia gravis), and some vasculitides.
The evidence in myalgic encephalomyelitis/chronic fatigue syndrome. Mixed and mostly old. Rowe (1997) ran a double-blind randomized controlled trial in 71 adolescents with myalgic encephalomyelitis/chronic fatigue syndrome (three infusions of 1 g/kg, one month apart). It reported a significant mean functional improvement at the six-month follow-up, and also a significant improvement in both the immunoglobulin and the placebo groups from the start of the trial. Later controlled adult trials were negative or inconsistent. Today IVIG is most commonly used in myalgic encephalomyelitis/chronic fatigue syndrome patients who have documented immune abnormalities — low immunoglobulin G (IgG) subclasses, specific antibody deficiency, or overlapping small-fiber neuropathy or autoimmune dysautonomia. In those subgroups it sometimes helps substantially.
Access reality. IVIG is expensive ($5,000–$10,000 per infusion) and insurance approval requires one of the recognized U.S. Food and Drug Administration-approved indications. Getting it for "myalgic encephalomyelitis/chronic fatigue syndrome" alone is nearly impossible; getting it for common variable immune deficiency or biopsy-proven small-fiber neuropathy is sometimes feasible. Where IVIG is being considered, the usual first step is a full immunology workup: quantitative immunoglobulins, immunoglobulin G subclasses, pneumococcal and tetanus titers before and after vaccination.
Metformin and Pyridostigmine
Metformin. The old diabetes drug has attracted interest because it targets AMP-activated protein kinase (AMPK) and mitochondrial function — both implicated in myalgic encephalomyelitis/chronic fatigue syndrome. Small pilots are underway; the case for trying 500–1500 mg daily in myalgic encephalomyelitis/chronic fatigue syndrome patients who also have insulin resistance or metabolic syndrome is stronger than in lean patients. Cheap, well-tolerated, and widely available, so the risk of a trial is low. Main side effect: gastrointestinal upset and B12 depletion with long-term use (B12 is often supplemented by people who stay on it more than a year).
Pyridostigmine. An acetylcholinesterase inhibitor originally approved for myasthenia gravis. At 30–60 mg three times daily, it boosts acetylcholine signaling and appears to improve orthostatic intolerance, cognitive fog, and exercise tolerance in a subset of myalgic encephalomyelitis/chronic fatigue syndrome patients, particularly those with overlapping postural orthostatic tachycardia syndrome. In a randomized, placebo-controlled trial in 45 patients using an invasive cardiopulmonary exercise test (iCPET), Joseph and colleagues (2022) found that a single 60-mg dose of pyridostigmine improved peak oxygen uptake by increasing cardiac output and right ventricular filling pressures. It is used widely by myalgic encephalomyelitis and postural orthostatic tachycardia syndrome specialists. Side effects are predictable cholinergic ones: cramping, diarrhea, increased saliva, muscle twitching — all dose-dependent and reversible.
Neither drug is myalgic encephalomyelitis/chronic fatigue syndrome-specific, but both are cheap, generic, well-understood, and used by knowledgeable physicians as additions to a wider plan.
Antivirals — Valacyclovir and Valganciclovir
The rationale. A meaningful fraction of myalgic encephalomyelitis/chronic fatigue syndrome is triggered by herpes-family viruses — Epstein-Barr virus (EBV) and human herpesvirus 6 (HHV-6) most often. See the sibling article on post-viral triggers. The theory is that in some patients these viruses do not fully clear; they smolder in a low-grade, partially-reactivated state that keeps the immune system and brain chronically inflamed. Long-term antivirals, in theory, suppress the smolder.
The evidence. A. Martin Lerner (Michigan) and Jose Montoya (Stanford) each published open-label case series in myalgic encephalomyelitis/chronic fatigue syndrome subgroups with elevated Epstein-Barr virus or HHV-6 antibody titers. Valacyclovir (primarily for Epstein-Barr virus) and valganciclovir (broader, including HHV-6 and cytomegalovirus, CMV) produced partial response rates of roughly 30–50% after 6–12 months of treatment. Subsequent placebo-controlled trials have been smaller and more mixed. Montoya's 2013 valganciclovir randomized controlled trial assigned 30 patients with raised HHV-6 and Epstein-Barr virus antibody levels 2:1 to valganciclovir or placebo for 6 months. The main fatigue score (Multidimensional Fatigue Inventory, MFI-20) improved more on valganciclovir, but the difference was not statistically significant; the mental-fatigue subscore, the Fatigue Severity Scale and cognitive function did improve significantly versus placebo.
How it is used. Valacyclovir 1 g two to four times daily, or valganciclovir 450–900 mg daily, typically for 6–12 months. Valganciclovir is the more potent option but carries real bone-marrow toxicity and requires frequent lab monitoring (complete blood count (CBC) every 2–4 weeks). Valacyclovir is much safer but may be too narrow for HHV-6 dominant cases. Finding a physician who will prescribe these off-label for myalgic encephalomyelitis/chronic fatigue syndrome is the hard part — usually an infectious disease specialist who works with myalgic encephalomyelitis/chronic fatigue syndrome patients or one of the handful of myalgic encephalomyelitis specialty clinics.
Immunoadsorption
What it is. A procedure like dialysis in which your blood is circulated through a column that selectively removes autoantibodies — particularly those against adrenergic and muscarinic receptors, which have been repeatedly implicated in myalgic encephalomyelitis/chronic fatigue syndrome and postural orthostatic tachycardia syndrome by German researchers (Scheibenbogen group, Charité Berlin).
The evidence. Small open-label trials from Berlin show meaningful improvement in a subgroup of myalgic encephalomyelitis/chronic fatigue syndrome patients with elevated β2-adrenergic and M3/M4 muscarinic receptor autoantibodies. Benefits last months to a year or more in some responders. No large randomized controlled trial has been completed.
- 2018 pilot (Scheibenbogen and colleagues). 10 patients with post-infectious illness and elevated β2-adrenergic receptor antibodies were treated over 5 days. 7 reported rapid improvement during treatment; 3 of these had moderate to marked improvement lasting 6–12+ months, 2 improved only briefly, and 2 improved for several months after first getting worse.
- 2020 repeat treatment (Tölle and colleagues). 5 of the earlier responders were treated again about two years later. 4 improved rapidly, for six to 12 months; one did not improve.
- 2024–25 post-COVID study (Stein and colleagues). 20 people with myalgic encephalomyelitis/chronic fatigue syndrome after COVID-19 and raised β2-adrenergic receptor antibodies had five immunoadsorption sessions, which cut total immunoglobulin G by 79%. 14 of 20 (70%) improved by 10 or more points on the Short Form 36 physical function scale, with gains lasting to six months. There was no placebo group.
Access. Available mainly in Germany and a few European centers, generally on self-pay basis (cost often $15,000–$25,000 for a course of sessions). Not available in the U.S. for this indication.
Mitochondrial Support — Coenzyme Q10, D-Ribose, Reduced Nicotinamide Adenine Dinucleotide
Multiple studies show disturbed energy metabolism in myalgic encephalomyelitis/chronic fatigue syndrome — impaired oxidative phosphorylation, reduced adenosine triphosphate (ATP) production, increased oxidative stress. Three supplements have accumulated small-trial evidence:
- Coenzyme Q10 (CoQ10 / ubiquinol) at 200–400 mg daily, often combined with reduced nicotinamide adenine dinucleotide (NADH). The Castro-Marrero group (Spain) published randomized controlled trials. In 2015 (73 patients, 8 weeks, 200 mg coenzyme Q10 + 20 mg NADH daily) fatigue fell more than on placebo. In 2016 (80 patients, 8 weeks) fatigue again fell more than on placebo and the treated group’s maximum heart rate during a cycle exercise test fell from baseline, but pain and sleep did not improve. The largest trial (2021, 207 patients, 200 mg coenzyme Q10 + 20 mg NADH once daily, 12 weeks) reported less cognitive fatigue, better health-related quality of life, and better sleep duration at 4 weeks and sleep efficiency at 8 weeks, all measured within the treated group against its own starting point. Effect sizes were modest but real.
- D-ribose at 5 g three times daily. Open-label Teitelbaum studies reported broad improvements; placebo-controlled data are weaker. Cheap and well-tolerated, but expect at most a modest effect.
- Reduced nicotinamide adenine dinucleotide at 10–20 mg daily. Used in combination with coenzyme Q10 in the Castro-Marrero protocol.
None of these are curative. They sit in the category of cheap, safe, evidence-supported additions that a minority of patients notice clearly, that a larger fraction notice subtly, and that some do not notice at all. The trials of these supplements ran 8 to 12 weeks.
Vagus Nerve Stimulation and Stellate Ganglion Block
Vagus nerve stimulation (VNS). Non-invasive devices (transcutaneous auricular VNS, a handheld neck vagus-nerve stimulator) target the vagus nerve through the ear or the neck. The mechanism is anti-inflammatory: vagal stimulation dampens systemic cytokine production via the cholinergic anti-inflammatory pathway. Small pilot studies in myalgic encephalomyelitis/chronic fatigue syndrome, long-illness populations, and fibromyalgia show signal; randomized controlled trial evidence is preliminary. Devices range from cheap clip-on ear stimulators (~$100) to prescription handhelds (several hundred dollars). Risk is minimal; the effects reported so far are modest.
Stellate ganglion block (SGB). An anesthetic injection into the sympathetic ganglion in the neck, originally used for complex regional pain syndrome and post-traumatic stress disorder (PTSD). Case reports and small series suggest benefit in dysautonomia and some post-viral fatigue states. It is genuinely experimental for myalgic encephalomyelitis/chronic fatigue syndrome — no randomized controlled trial exists, mechanism is speculative (sympathetic reset), and the procedure costs $1,000–$2,500 per side, usually repeated. It is performed by anesthesiologists experienced with the procedure.
Plasma Exchange
Therapeutic plasma exchange (TPE) physically removes plasma and replaces it with donor plasma or albumin, clearing circulating antibodies and inflammatory proteins. It is established therapy for several neuroimmune diseases (myasthenia crisis, Guillain-Barré, thrombotic thrombocytopenic purpura (TTP)). In myalgic encephalomyelitis/chronic fatigue syndrome and overlapping long-illness cohorts, plasma exchange is strictly research-stage: a handful of small European series, mostly overlapping with the immunoadsorption work. No U.S. clinical pathway exists. Listed here for completeness, not as a realistic option.
How to Evaluate a New Experimental Therapy
New myalgic encephalomyelitis/chronic fatigue syndrome therapies will appear in the press regularly. A practical checklist before you spend money, hope, or your fragile energy budget:
- Peer-reviewed or preprint? Preprints (medRxiv, bioRxiv, Research Square) have not been vetted. Anything preprint-only is provisional.
- How big was the trial? A case series of 5 patients is a hypothesis; 30 is a pilot; 150 with a placebo arm is a real signal.
- Placebo or open-label? In a disease with strong day-to-day variability and a large subjective component, placebo effects of 20–40% are routine. An open-label 50% response rate may collapse to 10% versus placebo.
- Who funded and who ran it? A trial run by the clinic that sells the treatment is not dispositive.
- Your baseline. If you are severely ill and bedbound, a therapy that causes a post-exertional malaise (PEM) crash can cost you months of recovery. The calculus is very different from mild-moderate illness.
- Reversibility. Supplements and low dose naltrexone are easily stopped. Chemotherapy agents, surgical procedures, and injectable antibodies are not.
- Stacking. Starting three things at once means you will never know which one worked or which one crashed you. Changing one variable at a time keeps each effect readable.
The most common mistake myalgic encephalomyelitis/chronic fatigue syndrome patients make is not trying experimental therapies — it is trying too many, too fast, without baselines, and then losing track of what helped. A simple weekly symptom diary (fatigue, PEM frequency, cognition, sleep, orthostatic symptoms, each 0–10) before and during any trial pays off enormously.
For the structural framework you are working within, see pacing and the energy envelope. No drug replaces pacing; drugs, at best, widen the envelope.
Key Research Papers
- Polo O, Pesonen P, Tuominen E. Low-dose naltrexone in the treatment of myalgic encephalomyelitis/chronic fatigue syndrome (ME/CFS). Fatigue: Biomedicine, Health & Behavior. 2019;7(4):207–217. — doi:10.1080/21641846.2019.1692770
- Crosby LD, Kalanidhi S, Bonilla A, Subramanian A, Ballon JS, Bonilla H. Off label use of Aripiprazole shows promise as a treatment for Myalgic Encephalomyelitis/Chronic Fatigue Syndrome (ME/CFS): a retrospective study of 101 patients treated with a low dose of Aripiprazole. J Transl Med. 2021;19(1):50. — doi:10.1186/s12967-021-02721-9
- Fluge Ø, et al. B-lymphocyte depletion in patients with myalgic encephalomyelitis/chronic fatigue syndrome: a randomized, double-blind, placebo-controlled trial. Ann Intern Med. 2019. — doi:10.7326/M18-1451
- Fluge Ø, et al. Benefit from B-lymphocyte depletion using the anti-CD20 antibody rituximab in chronic fatigue syndrome: a double-blind and placebo-controlled study. PLoS ONE. 2011. — doi:10.1371/journal.pone.0026358
- Castro-Marrero J, et al. Does oral coenzyme Q10 plus NADH supplementation improve fatigue and biochemical parameters in chronic fatigue syndrome? Antioxid Redox Signal. 2015. — doi:10.1089/ars.2014.6181
- Castro-Marrero J, et al. Effect of coenzyme Q10 plus nicotinamide adenine dinucleotide supplementation on maximum heart rate after exercise testing in chronic fatigue syndrome - A randomized, controlled, double-blind trial. Clin Nutr. 2016;35(4):826-34. — doi:10.1016/j.clnu.2015.07.010
- Castro-Marrero J, Segundo MJ, Lacasa M, Martinez-Martinez A, Sentañes RS, Alegre-Martin J. Effect of Dietary Coenzyme Q10 Plus NADH Supplementation on Fatigue Perception and Health-Related Quality of Life in Individuals with Myalgic Encephalomyelitis/Chronic Fatigue Syndrome: A Prospective, Randomized, Double-Blind, Placebo-Controlled Trial. Nutrients. 2021;13(8):2658. — doi:10.3390/nu13082658
- Younger J, Noor N, McCue R, Mackey S. Low-dose naltrexone for the treatment of fibromyalgia: findings of a small, randomized, double-blind, placebo-controlled, counterbalanced, crossover trial assessing daily pain levels. Arthritis Rheum. 2013;65(2):529-38. — doi:10.1002/art.37734
- Due Bruun K, et al. Naltrexone 6 mg once daily versus placebo in women with fibromyalgia: a randomised, double-blind, placebo-controlled trial. Lancet Rheumatol. 2024;6(1):e31-e39. — doi:10.1016/S2665-9913(23)00278-3
- Rodríguez-Freire C, et al. Efficacy of Low-Dose Naltrexone in Women With Fibromyalgia Syndrome: A 12-Month Randomised, Double-Blind, Placebo-Controlled Single-Centre Clinical Trial (INNOVA Study). Eur J Pain. 2026;30(6):e70321. — doi:10.1002/ejp.70321
- Rekeland IG, et al. Intravenous Cyclophosphamide in Myalgic Encephalomyelitis/Chronic Fatigue Syndrome. An Open-Label Phase II Study. Front Med (Lausanne). 2020;7:162. — doi:10.3389/fmed.2020.00162
- Rekeland IG, et al. Six-year follow-up of participants in two clinical trials of rituximab or cyclophosphamide in Myalgic Encephalomyelitis/Chronic Fatigue Syndrome. PLoS One. 2024;19(7):e0307484. — doi:10.1371/journal.pone.0307484
- Rowe KS. Double-blind randomized controlled trial to assess the efficacy of intravenous gammaglobulin for the management of chronic fatigue syndrome in adolescents. J Psychiatr Res. 1997;31(1):133-47. — doi:10.1016/s0022-3956(96)00047-7
- Joseph P, et al. Neurovascular Dysregulation and Acute Exercise Intolerance in Myalgic Encephalomyelitis/Chronic Fatigue Syndrome: A Randomized, Placebo-Controlled Trial of Pyridostigmine. Chest. 2022;162(5):1116-1126. — doi:10.1016/j.chest.2022.04.146
- Montoya JG, et al. Randomized clinical trial to evaluate the efficacy and safety of valganciclovir in a subset of patients with chronic fatigue syndrome. J Med Virol. 2013;85(12):2101-9. — doi:10.1002/jmv.23713
- Scheibenbogen C, et al. Immunoadsorption to remove ß2 adrenergic receptor antibodies in Chronic Fatigue Syndrome CFS/ME. PLoS One. 2018;13(3):e0193672. — doi:10.1371/journal.pone.0193672
- Tölle M, et al. Myalgic Encephalomyelitis/Chronic Fatigue Syndrome: Efficacy of Repeat Immunoadsorption. J Clin Med. 2020;9(8):2443. — doi:10.3390/jcm9082443
- Stein E, et al. Efficacy of repeated immunoadsorption in patients with post-COVID myalgic encephalomyelitis/chronic fatigue syndrome and elevated β2-adrenergic receptor autoantibodies: a prospective cohort study. Lancet Reg Health Eur. 2025;49:101161. — doi:10.1016/j.lanepe.2024.101161
PubMed Topic Searches
For further reading, the following PubMed topic searches return current peer-reviewed work on pharmacologic and experimental approaches to myalgic encephalomyelitis/chronic fatigue syndrome:
- PubMed: Low-dose naltrexone and ME/CFS
- PubMed: Aripiprazole in ME/CFS
- PubMed: Rituximab and ME/CFS — the Fluge/Mella trials
- PubMed: Cyclophosphamide in ME/CFS
- PubMed: Valganciclovir and herpesvirus-triggered ME/CFS
- PubMed: Pyridostigmine in ME/CFS and orthostatic intolerance
- PubMed: Immunoadsorption and autoantibody removal in ME/CFS
- PubMed: CoQ10 and NADH in ME/CFS
- PubMed: Vagus nerve stimulation for fatigue
- PubMed: IVIG in ME/CFS
Connections
- Neurology
- Myalgic Encephalomyelitis/Chronic Fatigue Syndrome Overview
- Post-Viral Triggers: Epstein-Barr Virus and Others
- Post-Exertional Malaise
- Pacing and the Energy Envelope
- 2-Day CPET and Objective Testing
- Myalgic Encephalomyelitis/Chronic Fatigue Syndrome Diagnostic Criteria
- Orthostatic Intolerance in Myalgic Encephalomyelitis/Chronic Fatigue Syndrome
- Severe and Very Severe Myalgic Encephalomyelitis
- Mitochondrial Dysfunction and Energy Metabolism
- Low-Dose Naltrexone
- Low Dose Naltrexone for Fibromyalgia
- Low Dose Naltrexone for Postural Orthostatic Tachycardia Syndrome
- Postural Orthostatic Tachycardia Syndrome
- Mast Cell Activation Syndrome
- Fibromyalgia
- Chronic Pain
- Fatigue