Post-Viral Triggers: Epstein-Barr Virus and Others in Myalgic Encephalomyelitis/Chronic Fatigue Syndrome (ME/CFS)
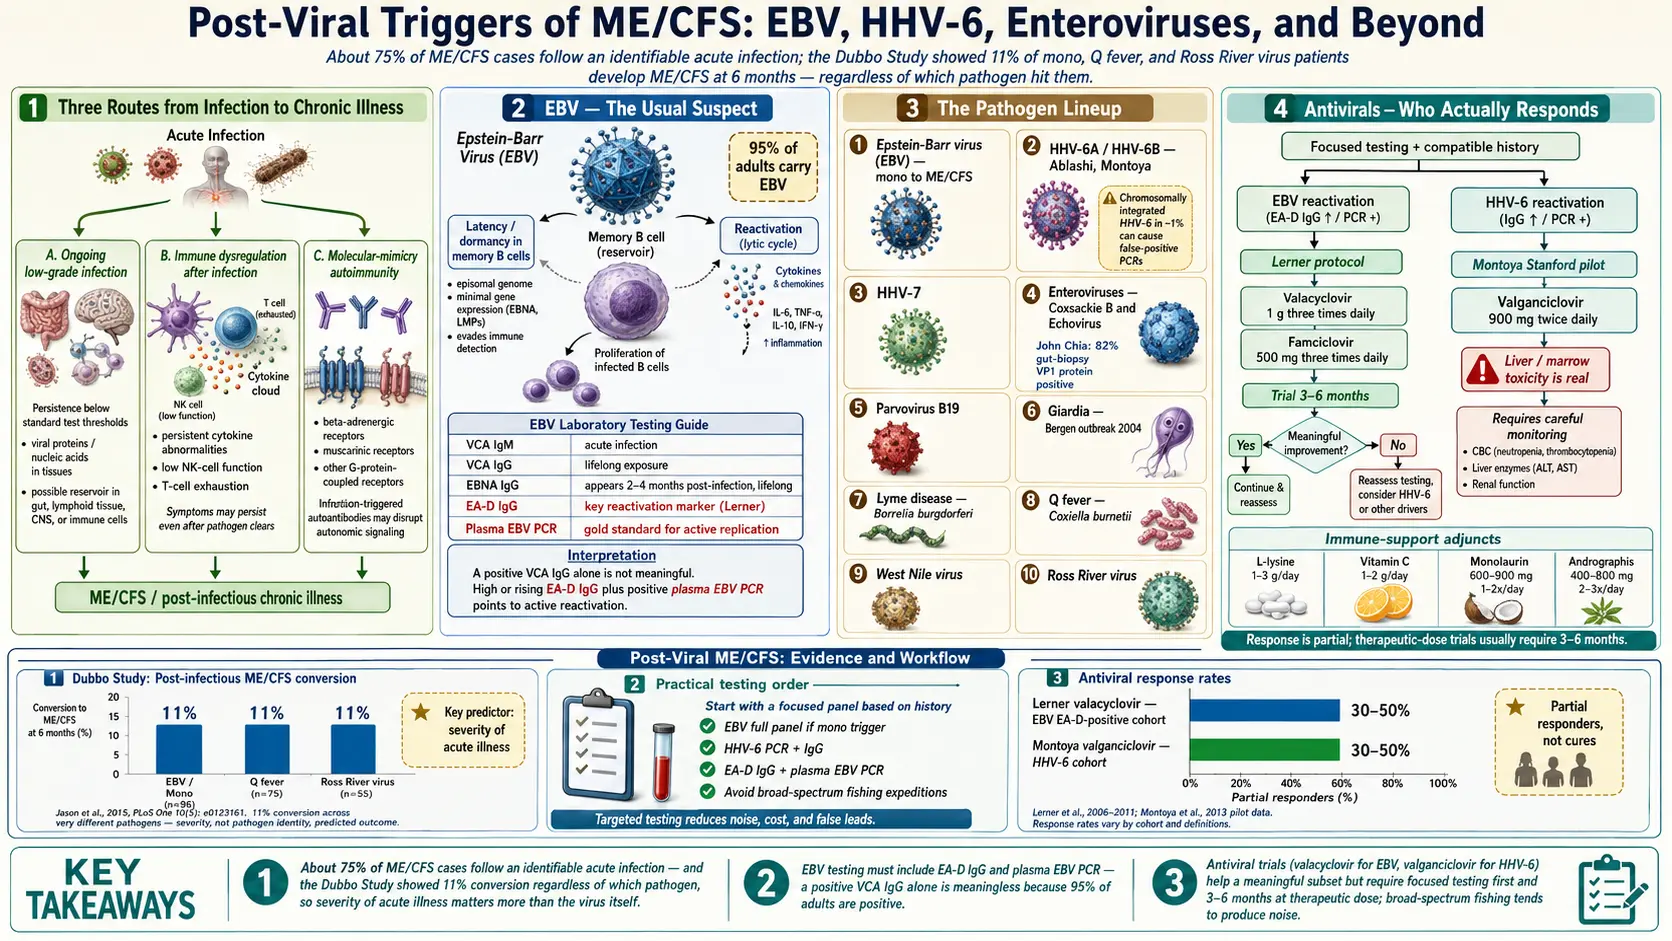
Table of Contents
- What "Post-Viral" Actually Means
- The Dubbo Study — Mono as the Starting Gun
- Epstein-Barr Virus: The Usual Suspect
- Reading Your Epstein-Barr Virus Panel Without Panic
- HHV-6 and HHV-7 Reactivation
- Enteroviruses: Coxsackie B and Echovirus
- Parvovirus B19
- Giardia and the Bergen Outbreak
- Lyme Disease as a Myalgic Encephalomyelitis/Chronic Fatigue Syndrome Trigger
- Q Fever (Coxiella burnetii)
- West Nile and Ross River Virus
- COVID-19 as a Trigger
- Antivirals: Who Actually Responds
- Natural Antivirals and Immune Support
- A Practical Testing and Treatment Order
- Key Research Papers
- Connections
- Featured Videos
What "Post-Viral" Actually Means
A large fraction of myalgic encephalomyelitis/chronic fatigue syndrome (ME/CFS) patients can point to a specific illness that started everything. One week they were fine; a few weeks later they had a sore throat, a fever, and swollen glands; six months later they still could not climb the stairs without their heart rate spiking and needing a two-day recovery. That pattern — an acute infection followed by a chronic multi-system collapse — is what clinicians mean by a post-infectious or post-viral onset of myalgic encephalomyelitis/chronic fatigue syndrome.
"Post-viral" does not necessarily mean the virus is still replicating inside you. It can mean any of three things, and all three probably happen in different patients:
- Ongoing low-grade infection — the pathogen is still there, hiding in tissue reservoirs, at levels too low for standard testing.
- Immune dysregulation triggered by the infection — the pathogen is gone, but the immune system never returned to its pre-illness baseline. Cytokines, natural killer cell function, and T-cell exhaustion markers stay abnormal for years.
- Autoimmunity against self-tissue — the infection primed antibodies against molecular mimics of your own receptors (beta-adrenergic, muscarinic, G-protein-coupled), and those antibodies persist.
A 2024 deep-phenotyping study at the U.S. National Institutes of Health examined people whose myalgic encephalomyelitis/chronic fatigue syndrome began after an infection, alongside matched controls. It found immune signs that the authors read as chronic antigen stimulation (more naive and fewer switched-memory B cells, the white blood cells that make antibodies), an altered "effort preference" rather than physical or central fatigue, linked to dysfunction of integrative brain regions with consequences for autonomic functioning (the automatic control of heart rate and blood pressure) and physical conditioning, and gene-expression and metabolic differences that varied by sex. The paper states that how the illness works (its pathophysiology) is unknown and that no disease-modifying treatments are available.
This article walks through the specific pathogens repeatedly linked to myalgic encephalomyelitis/chronic fatigue syndrome onset, how they are tested for, and what treatments are used if a trigger is confirmed. The approach described is not a fishing expedition — random broad-spectrum viral panels tend to produce confusing results — but a focused workup guided by the patient's history.
The Dubbo Study — Mono as the Starting Gun
The single most-cited post-viral myalgic encephalomyelitis/chronic fatigue syndrome study came out of the Australian town of Dubbo, published in the BMJ in 2006 by Ian Hickie and colleagues. The researchers followed 253 people diagnosed with one of three acute infections — Epstein-Barr virus (mononucleosis), Q fever, or Ross River virus — and checked in at six months.
The headline result: 11% of these patients met criteria for myalgic encephalomyelitis/chronic fatigue syndrome six months later, regardless of which of the three pathogens had hit them. The rate was the same across all three infections, which is the crucial finding — it meant the trigger was not Epstein-Barr virus-specific. Something about the host's response to a significant infection, not the virus itself, determined who tipped into chronic illness.
The predictors of who became chronic were not the viral load or the strain. The paper reports that the syndrome was predicted largely by the severity of the initial acute illness (how high the fever, how swollen the glands, how long the bed rest) rather than by demographic, psychological or microbiological factors. A mild case of mono rarely kicked off myalgic encephalomyelitis/chronic fatigue syndrome. A flattening, two-weeks-in-bed case did so in about one in ten.
Dubbo reframed myalgic encephalomyelitis/chronic fatigue syndrome as something that happens to a minority of people after severe infections, not a mysterious condition that appears from nowhere. It also legitimized the experience of patients who knew exactly when their illness started.
Epstein-Barr Virus: The Usual Suspect
Epstein-Barr virus (EBV) is a herpesvirus that roughly 95% of adults carry for life. Most people catch it as children, where it causes nothing memorable. Catch it as a teenager or young adult and you get infectious mononucleosis — the classic sore throat, enormous lymph nodes, exhausted-for-a-month illness. After the acute phase, the virus goes dormant inside memory B cells, where it stays forever, occasionally reactivating and being re-suppressed without you noticing.
In myalgic encephalomyelitis/chronic fatigue syndrome, two things can go wrong with that dormancy:
- Primary infection that never fully clears. The acute mono just drags on and on, evolving into myalgic encephalomyelitis/chronic fatigue syndrome without a clear transition point. This is the classic Dubbo scenario.
- Reactivation in someone with old Epstein-Barr virus. You had mono at 17, forgot about it, and then in your 30s a stressful period, surgery, or another infection lets Epstein-Barr virus come out of dormancy. Immune surveillance fails to put it back, and a chronic reactivation pattern establishes.
Epstein-Barr virus in myalgic encephalomyelitis/chronic fatigue syndrome is not just a passenger. Lab work has shown abnormal antibody profiles, deficient Epstein-Barr virus-specific T-cell responses, and in some cohorts detectable viral DNA in blood or saliva when controls have none. The 2018 Rasa review in the Journal of Translational Medicine summarizes the evidence: chronic Epstein-Barr virus reactivation is present in a meaningful subset of myalgic encephalomyelitis/chronic fatigue syndrome patients, though not in all of them.
Reading Your Epstein-Barr Virus Panel Without Panic
The biggest source of confusion in Epstein-Barr virus testing is that a positive immunoglobulin G (IgG) result alone proves almost nothing. Ninety-five percent of adults are immunoglobulin G positive. Your doctor saying "your Epstein-Barr virus came back positive" is meaningless without the specific antibody subsets.
Here is what each marker means, in plain terms:
- VCA IgM (viral capsid antigen, immunoglobulin M (IgM) class) — rises in the first few weeks of acute infection, then fades. A positive VCA IgM in an adult who has been sick for 2–6 weeks suggests recent primary mono.
- VCA IgG — rises during acute infection and stays positive for life. By itself it tells you only that you have been exposed to Epstein-Barr virus at some point, which again is true of almost everyone.
- EBNA IgG (Epstein-Barr nuclear antigen, immunoglobulin G) — appears 2–4 months after the acute infection and stays positive for life. A positive EBNA IgG means the infection is old. A negative EBNA with positive VCA IgG is suspicious for either a recent infection or, in a chronic-illness context, a faulty immune response that has failed to mount a normal memory profile.
- Early Antigen-D (EA-D) immunoglobulin G — the key reactivation marker. In healthy people with old EBV, EA-D is usually negative or low. A high or rising EA-D titer in someone with chronic fatigue suggests ongoing reactivation. Dr. Martin Lerner built his treatment protocols around this marker.
- Epstein-Barr virus polymerase chain reaction (PCR) — measures actual viral DNA in blood (whole blood or plasma) or saliva. A positive plasma polymerase chain reaction is the strongest evidence of active viral replication, because dormant Epstein-Barr virus sits inside B cells and does not spill into plasma. Whole-blood polymerase chain reaction is more sensitive but less specific (it picks up latent genomes inside memory B cells too).
What a full panel covers: a panel used to look for Epstein-Barr virus reactivation includes VCA IgM, VCA IgG, EBNA IgG, EA-D immunoglobulin G, and plasma Epstein-Barr virus polymerase chain reaction. A standard "mono spot" or a single immunoglobulin G cannot answer the question. The point of the full panel is to distinguish old exposure (everyone) from active reactivation (a minority).
HHV-6 and HHV-7 Reactivation
Human herpesvirus-6 and -7 are cousins of Epstein-Barr virus. Almost everyone catches HHV-6 as a toddler — it causes roseola, the classic "fever-then-rash" baby illness — and like Epstein-Barr virus, it stays dormant for life. HHV-6 comes in two variants: HHV-6A (less common, more often linked to neurological disease) and HHV-6B (the childhood roseola strain).
In myalgic encephalomyelitis/chronic fatigue syndrome cohorts, HHV-6 reactivation has been reported for decades, particularly by Dharam Ablashi (one of HHV-6's original co-discoverers) and by the Stanford group around Jose Montoya. Testing options:
- HHV-6 immunoglobulin G and immunoglobulin M — high immunoglobulin G titers or positive immunoglobulin M can suggest reactivation, though interpretation is less clean than Epstein-Barr virus.
- HHV-6 polymerase chain reaction in plasma — the most specific test; a positive result points to active replication.
- Chromosomally-integrated HHV-6 (ciHHV-6) — in about 1% of people, HHV-6 has integrated into germline DNA. These patients will have positive polymerase chain reaction in every sample they ever give, which does not mean active infection. A specialty lab can distinguish ciHHV-6 from true reactivation.
HHV-7 is less studied in myalgic encephalomyelitis/chronic fatigue syndrome but has been flagged as a potential co-reactivator. Most clinicians test for HHV-6 first and add HHV-7 only if the workup is negative and suspicion remains high.
Enteroviruses: Coxsackie B and Echovirus
Enteroviruses are a large family of RNA viruses that cause summer colds, hand-foot-and-mouth, and occasionally more serious illness. Two subgroups keep surfacing in myalgic encephalomyelitis/chronic fatigue syndrome literature: Coxsackie B (especially types 3 and 4, CVB3 and CVB4) and echoviruses.
The leading voice on enteroviral myalgic encephalomyelitis/chronic fatigue syndrome is Dr. John Chia in California. His 2008 paper in the Journal of Clinical Pathology studied stomach biopsies from myalgic encephalomyelitis/chronic fatigue syndrome patients and found enteroviral VP1 protein in 82% of patients versus 20% of controls (135 of 165 patient biopsies versus 7 of 34 control biopsies), and enterovirus genetic material (RNA) in 9 of 24 patient samples tested versus 1 of 21 controls. The patients were 165 consecutive people with chronic fatigue syndrome and ongoing abdominal complaints seen in one practice. The study shows the virus is found more often in these patients; its design cannot show whether the virus causes the illness. Chia's argument is that enteroviruses can persist in gut tissue for years, replicating at low levels below the threshold of standard blood tests, and that the gut is the reservoir driving chronic symptoms.
Testing enterovirus is harder than testing Epstein-Barr virus:
- Standard antibody panels (neutralizing antibodies against Coxsackie B types 1–6 (CVB1-6) and the common echovirus types) show only prior exposure.
- A high, persistent titer (1:320 or above) against a single Coxsackie strain in a chronically ill patient is suggestive but not diagnostic.
- The most specific test is stomach biopsy with VP1 immunostaining, but only a handful of labs worldwide run it.
- Stool enterovirus polymerase chain reaction can pick up active shedding but is often negative in chronic cases.
Practitioners who follow Chia's work place enterovirus on the short list when the illness started with a gastrointestinal episode — sudden vomiting, diarrhea, body aches in summer.
Parvovirus B19
Parvovirus B19 causes "fifth disease" in children (the slapped-cheek rash) and can cause a flu-like illness with joint pain in adults. A subset of adults infected with parvovirus B19 develop chronic fatigue and arthralgia that persists for years after the acute phase.
Testing: parvovirus B19 immunoglobulin M (recent), immunoglobulin G (old exposure), and polymerase chain reaction for DNA. Chronic-phase patients can be immunoglobulin G positive and polymerase chain reaction positive simultaneously, suggesting failed clearance. Treatment is mostly supportive; intravenous immunoglobulin (IVIG) has been tried in severely immune-compromised patients but is not standard for myalgic encephalomyelitis/chronic fatigue syndrome.
Giardia and the Bergen Outbreak
In 2004, the drinking-water supply of Bergen, Norway was contaminated with Giardia lamblia. Between 1,300 and 2,500 people developed acute giardiasis — watery diarrhea, cramping, bloating. The water was treated and the parasites cleared. Then the Norwegian health system followed the cohort.
Halvor Naess and colleagues described the patients referred with long-lasting fatigue in BMC Gastroenterology in 2012: of 96 such patients, 58 met chronic fatigue syndrome criteria, at a mean of 2.7 years after the infection. With 1,262 laboratory-confirmed giardiasis cases in all, the authors concluded that at least 5% developed a post-infectious fatigue syndrome. That report had no comparison group.
The controlled comparison came later. Sverre Litleskare and colleagues followed 1,252 laboratory-confirmed cases against 2,504 unexposed Bergen residents matched for age and sex. Ten years after the outbreak, chronic fatigue was present in 26% of exposed people versus 11% of controls (adjusted odds ratio 3.01), down from 31% at 6 years, and irritable bowel syndrome in 43% versus 14%. Follow-up at 6 and 10 years thus showed that many of these patients did not recover.
Bergen is important because it is the cleanest real-world experiment ever run on post-infectious myalgic encephalomyelitis/chronic fatigue syndrome outside of viral pathogens. It proved that a protozoan gut infection can trigger the same chronic-fatigue syndrome that Epstein-Barr virus does, reinforcing the idea that the trigger matters less than the host response.
When myalgic encephalomyelitis/chronic fatigue syndrome follows traveler's diarrhea or a known Giardia exposure, the tests used to find an active infection are a stool Giardia antigen test or polymerase chain reaction. Metronidazole or tinidazole clears an active infection, though clearing the parasite often does not clear the fatigue.
Lyme Disease as a Myalgic Encephalomyelitis/Chronic Fatigue Syndrome Trigger
The relationship between Lyme disease and myalgic encephalomyelitis/chronic fatigue syndrome is tangled and contested. The clean version: a minority of patients treated for acute Lyme with a standard course of doxycycline remain ill six months later with fatigue, cognitive dysfunction, sleep disturbance, and musculoskeletal pain. The U.S. Centers for Disease Control and Prevention (CDC) calls this Post-Treatment Lyme Disease Syndrome (PTLDS). The clinical picture overlaps heavily with myalgic encephalomyelitis/chronic fatigue syndrome — in some series, more than half of PTLDS patients meet myalgic encephalomyelitis/chronic fatigue syndrome criteria.
Whether PTLDS represents persistent infection, immune dysregulation, or autoimmunity is an active research question. The points that come up for patients:
- When myalgic encephalomyelitis/chronic fatigue syndrome began after a tick bite, a bulls-eye rash, or a summer flu-like illness in a Lyme-endemic area, the standard blood test is two-tier Lyme serology: a first antibody test (an enzyme immunoassay, EIA, also called ELISA, enzyme-linked immunosorbent assay) and, if that is positive or unclear, a second test. The second test was traditionally a Western blot. Since 2019 the U.S. Centers for Disease Control and Prevention accepts a second enzyme immunoassay in place of the Western blot as an "acceptable alternative", when the test kit is cleared by the U.S. Food and Drug Administration for that use.
- Seronegative Lyme is controversial but real in a small percentage of cases; clinical judgment matters.
- Co-infections (babesia, bartonella, anaplasma) are part of the same discussion, because they can produce their own chronic syndromes.
For a fuller discussion, see Lyme Disease and PTLDS and Chronic Lyme.
Q Fever (Coxiella burnetii)
Coxiella burnetii is a bacterium carried by sheep, goats, and cattle. Humans catch it by inhaling contaminated dust, usually near farms or slaughterhouses. Acute Q fever is a flu-like illness with high fever, headache, and sometimes pneumonia or hepatitis.
A defined minority of Q fever patients develop Q Fever Fatigue Syndrome (QFS), a chronic post-infectious state indistinguishable from myalgic encephalomyelitis/chronic fatigue syndrome in most respects. Q fever was one of the three triggers in the Dubbo study, and the Netherlands had a large Q fever outbreak from 2007–2010 that produced a QFS cohort followed for over a decade.
Testing: Coxiella phase I and phase II IgG. These are the tests used when someone grew up near livestock or had an unexplained pneumonia before myalgic encephalomyelitis/chronic fatigue syndrome onset.
West Nile and Ross River Virus
Both are mosquito-borne RNA viruses. Ross River virus is endemic to Australia and the South Pacific; it causes an acute illness of fever, rash, and prolonged polyarthralgia, and was the third pathogen in the Dubbo study. West Nile virus is endemic across North America; most infections are asymptomatic, but those who develop symptomatic West Nile (flu-like illness, occasionally encephalitis) have a recognized post-viral fatigue syndrome that can persist for years.
Testing is by immunoglobulin G/immunoglobulin M serology. Treatment is supportive. These are mostly diagnostic "ah-ha" findings — they explain an onset rather than offering a treatment target — but explaining the start of the illness matters for patients who have been told their symptoms are psychosomatic.
COVID-19 as a Trigger
The U.S. National Institutes of Health's RECOVER-Adult study follows adults across the country after SARS-CoV-2 infection (the virus that causes COVID-19). In its 2025 report, adults followed from the time of infection developed myalgic encephalomyelitis/chronic fatigue syndrome at a rate of 2.66 per 100 person-years, compared with 0.93 per 100 person-years in matched uninfected participants — a hazard ratio of 4.93.
Of all infected participants, 4.5% (531 of 11,785) met the 2015 Institute of Medicine criteria for myalgic encephalomyelitis/chronic fatigue syndrome after infection, compared with 0.6% (9 of 1,439) of uninfected participants. Post-exertional malaise was the most common symptom (24.0% of infected participants), and most people with post-COVID-19 myalgic encephalomyelitis/chronic fatigue syndrome (88.7%, 471 of 531) also met the study's criteria for long COVID. The authors note that the diagnostic criteria rely on self-reported symptoms, which can wax and wane.
Antivirals: Who Actually Responds
Antiviral medication is not a routine myalgic encephalomyelitis/chronic fatigue syndrome treatment, but in carefully selected subsets it can produce striking improvement. The evidence base is small, uncontrolled in most cases, and drawn mostly from two clinicians — the late Martin Lerner in Michigan and Jose Montoya's group at Stanford.
Valacyclovir targets Epstein-Barr virus, herpes simplex virus types 1 and 2 (HSV-1, HSV-2), and varicella-zoster virus (VZV, the chickenpox and shingles virus). Lerner's 2007 paper in In Vivo reported a blinded, randomized, placebo-controlled trial of valacyclovir in an "Epstein-Barr virus subset" of chronic fatigue syndrome patients, followed by 36 months of follow-up. After six months, the valacyclovir group's Energy Index score (a measure of physical capacity) rose by 1.12 points versus 0.42 on placebo. Over the follow-up the paper reports fewer fast heart rhythms (sinus tachycardias), improved heart-wall motion, falling Epstein-Barr virus VCA IgM antibody levels, and patients resuming normal activities. The markers followed were Epstein-Barr virus VCA IgM and early antigen (EA) antibodies, 24-hour heart (Holter) monitoring and a heart scan (MUGA ventriculography). The dose used was 14.3 mg/kg every 6 hours.
Valganciclovir is a stronger drug, active against HHV-6 and cytomegalovirus (CMV) in addition to Epstein-Barr virus. It has meaningful side effects — bone-marrow suppression, neutropenia, potential carcinogenicity — and requires close lab monitoring. Montoya's 2013 double-blind, placebo-controlled trial randomized 30 chronic fatigue syndrome patients with high HHV-6 and Epstein-Barr virus antibody titers (2:1) to valganciclovir or placebo for 6 months. It found no statistically significant difference on its main fatigue score (the Multidimensional Fatigue Inventory, MFI-20), but better mental-fatigue (P = 0.039), fatigue-severity (P = 0.006) and cognitive-function (P = 0.025) scores, and patients on valganciclovir were 7.4 times more likely to be classed as responders. The authors call for larger and longer trials. Use is reserved for patients with strong serological evidence of HHV-6 or cytomegalovirus reactivation and willingness to accept monitoring.
Famciclovir is another option in the valacyclovir family, sometimes chosen for its convenience or tolerability.
Who responds: generally patients with a clear post-viral onset, persistent serological evidence of reactivation (EA-D, plasma polymerase chain reaction, high HHV-6 titers), and a relatively short duration of illness. The published trials enrolled only patients with abnormal Epstein-Barr virus or HHV-6 antibody results, so they give no evidence of benefit for people with long-standing illness and normal serology, while the drugs' side-effect risks still apply.
These medications are prescription-only, and their use for myalgic encephalomyelitis/chronic fatigue syndrome rests on the Lerner/Montoya framework rather than on an approved indication. Patients report that most general practitioners and infectious disease specialists do not prescribe them for this illness; the framework is discussed mainly at specialist myalgic encephalomyelitis/chronic fatigue syndrome clinics and by a U.S. clinician coalition that publishes guidance on the illness.
Natural Antivirals and Immune Support
Several supplements have antiviral activity in vitro or in small trials. None are substitutes for prescription antivirals in confirmed reactivation, but they are cheap, generally low-risk, and some patients report benefit:
- L-Lysine — an amino acid that competes with arginine, which herpesviruses need for replication. Classically used for HSV cold sores at 1–3 g per day. Some myalgic encephalomyelitis/chronic fatigue syndrome patients use it for Epstein-Barr virus reactivation. See L-Lysine.
- Monolaurin — a coconut-derived fatty-acid derivative with in vitro activity against enveloped viruses including Epstein-Barr virus. Typical dose 600–1,800 mg daily.
- Olive leaf extract — contains oleuropein, which has shown antiviral effects in laboratory studies. Quality varies wildly between brands.
- N-acetylcysteine (NAC) — replenishes glutathione, which is typically depleted in chronic viral illness. 600–1,800 mg daily.
On the immune-modulation side, two prescription interventions have moved from fringe to mainstream discussion:
- Low-Dose Naltrexone — 1.5–4.5 mg at bedtime. Modulates microglia and reduces neuroinflammation. A meaningful fraction of myalgic encephalomyelitis/chronic fatigue syndrome patients report reduced pain and brain-fog on low dose naltrexone (LDN). See the sibling article on low dose naltrexone, aripiprazole, and experimental therapies for the full protocol.
- Low-Dose Interleukin-2 (IL-2) — experimental, administered by subcutaneous injection, expands regulatory T cells and has been trialed in autoimmunity and a handful of myalgic encephalomyelitis/chronic fatigue syndrome cases. Not yet standard, but on the horizon.
A Practical Testing and Treatment Order
For people who trace their myalgic encephalomyelitis/chronic fatigue syndrome to a post-viral trigger, the workup this article describes is a focused one, rather than every test listed above at once:
- History first. The month and, if possible, the week the illness started, and the symptoms of that first illness: fever, sore throat, swollen glands, rash, diarrhea, tick bite, travel.
- Targeted serology. Based on the history, one or two likely pathogens are tested. Classic mono history: Epstein-Barr virus full panel (VCA IgM, VCA IgG, EBNA IgG, EA-D immunoglobulin G, plasma polymerase chain reaction). Summer gastrointestinal onset: enterovirus panel plus stool Giardia. Tick exposure: two-tier Lyme plus co-infections. Farm or livestock exposure: Q fever phase I and II. Mosquito-heavy summer onset: West Nile immunoglobulin G/immunoglobulin M.
- HHV-6 testing is added when the Epstein-Barr virus results are suggestive and more detail is wanted, particularly when cognitive symptoms dominate.
- Interpretation. The results have to separate "old exposure" from "active reactivation" from "chromosomally integrated" HHV-6, which takes familiarity with these specialised tests.
- If a clear trigger is identified, the targeted treatments are metronidazole for Giardia, doxycycline for new-onset Lyme, and valacyclovir or valganciclovir for confirmed reactivation (the antiviral use rests on the small studies above). Pacing, sleep, and orthostatic-intolerance management are used alongside, because the non-viral dysfunction in myalgic encephalomyelitis/chronic fatigue syndrome persists even when a pathogen is addressed.
A final word on expectations: identifying a post-viral trigger is meaningful but is not a cure. Patients and practitioners describe improvements of 20–40% with a specific antiviral, but the full myalgic encephalomyelitis/chronic fatigue syndrome — post-exertional malaise, orthostatic intolerance, cognitive dysfunction — usually involves the full toolkit: pacing, autonomic management, sleep repair, and in some cases experimental therapies. The trigger is the door that opened the illness. Closing it helps. It rarely ends it.
Key Research Papers
- Hickie I, et al. Post-infective and chronic fatigue syndromes precipitated by viral and non-viral pathogens: prospective cohort study (Dubbo). BMJ. 2006. — doi:10.1136/bmj.38933.585764.AE
- Chia JK, Chia AY. Chronic fatigue syndrome is associated with chronic enterovirus infection of the stomach. J Clin Pathol. 2008. — doi:10.1136/jcp.2007.050054
- Naess H, Nyland M, Hausken T, et al. Chronic fatigue syndrome after Giardia enteritis: clinical characteristics, disability and long-term sickness absence. BMC Gastroenterol. 2012;12:13. — doi:10.1186/1471-230X-12-13
- Lerner AM, Beqaj SH, Deeter RG, Fitzgerald JT. Valacyclovir treatment in Epstein-Barr virus subset chronic fatigue syndrome: thirty-six months follow-up. In Vivo. 2007;21(5):707–13. — PubMed PMID: 18019402
- Montoya JG, Kogelnik AM, Bhangoo M, et al. Randomized clinical trial to evaluate the efficacy and safety of valganciclovir in a subset of patients with chronic fatigue syndrome. J Med Virol. 2013;85(12):2101–9. — PubMed PMID: 23959519
- Litleskare S, Rortveit G, Eide GE, et al. Prevalence of Irritable Bowel Syndrome and Chronic Fatigue 10 Years After Giardia Infection. Clin Gastroenterol Hepatol. 2018;16(7):1064–1072.e4. — PubMed PMID: 29378314
- Mead P, Petersen J, Hinckley A. Updated CDC Recommendation for Serologic Diagnosis of Lyme Disease. MMWR Morb Mortal Wkly Rep. 2019;68(32):703. — PubMed PMID: 31415492
- Vernon SD, Zheng T, Do H, et al. Incidence and Prevalence of Post-COVID-19 Myalgic Encephalomyelitis: A Report from the Observational RECOVER-Adult Study. J Gen Intern Med. 2025;40(5):1085–1094. — PubMed PMID: 39804551
- Walitt B, Singh K, LaMunion SR, et al. Deep phenotyping of post-infectious myalgic encephalomyelitis/chronic fatigue syndrome. Nat Commun. 2024;15(1):907. — PubMed PMID: 38383456
- Rasa S, et al. Chronic viral infections in myalgic encephalomyelitis/chronic fatigue syndrome (ME/CFS). J Transl Med. 2018. — doi:10.1186/s12967-018-1644-y
PubMed Topic Searches
The following PubMed topic searches return current peer-reviewed work on post-viral triggers of myalgic encephalomyelitis/chronic fatigue syndrome and related syndromes:
- PubMed: EBV and ME/CFS
- PubMed: HHV-6 and chronic fatigue syndrome
- PubMed: Enterovirus, Coxsackie B, and ME/CFS
- PubMed: Dubbo post-infective fatigue cohort
- PubMed: Giardia and post-infectious fatigue (Bergen cohort)
- PubMed: Q Fever Fatigue Syndrome
- PubMed: Post-Treatment Lyme Disease Syndrome
- PubMed: Valganciclovir trials in ME/CFS
- PubMed: Ross River virus and chronic fatigue
- PubMed: Parvovirus B19 and chronic fatigue
Connections
- Neurology
- Myalgic Encephalomyelitis/Chronic Fatigue Syndrome Overview
- Lyme Disease
- PTLDS and Chronic Lyme
- Post-Exertional Malaise
- Myalgic Encephalomyelitis/Chronic Fatigue Syndrome Diagnostic Criteria
- 2-Day CPET and Objective Testing
- Orthostatic Intolerance in Myalgic Encephalomyelitis/Chronic Fatigue Syndrome
- Pacing and the Energy Envelope
- Severe and Very Severe Myalgic Encephalomyelitis
- Low Dose Naltrexone, Abilify and Experimental Therapies
- Mitochondrial Dysfunction and Energy Metabolism
- Hashimoto's Thyroiditis
- Lysine
- Epstein-Barr Virus
- Postural Orthostatic Tachycardia Syndrome
- Mast Cell Activation Syndrome
- Fibromyalgia
- Fatigue
- Infectious Disease