Myalgic Encephalomyelitis / Chronic Fatigue Syndrome (ME/CFS): An Under-Recognized Multi-System Disease
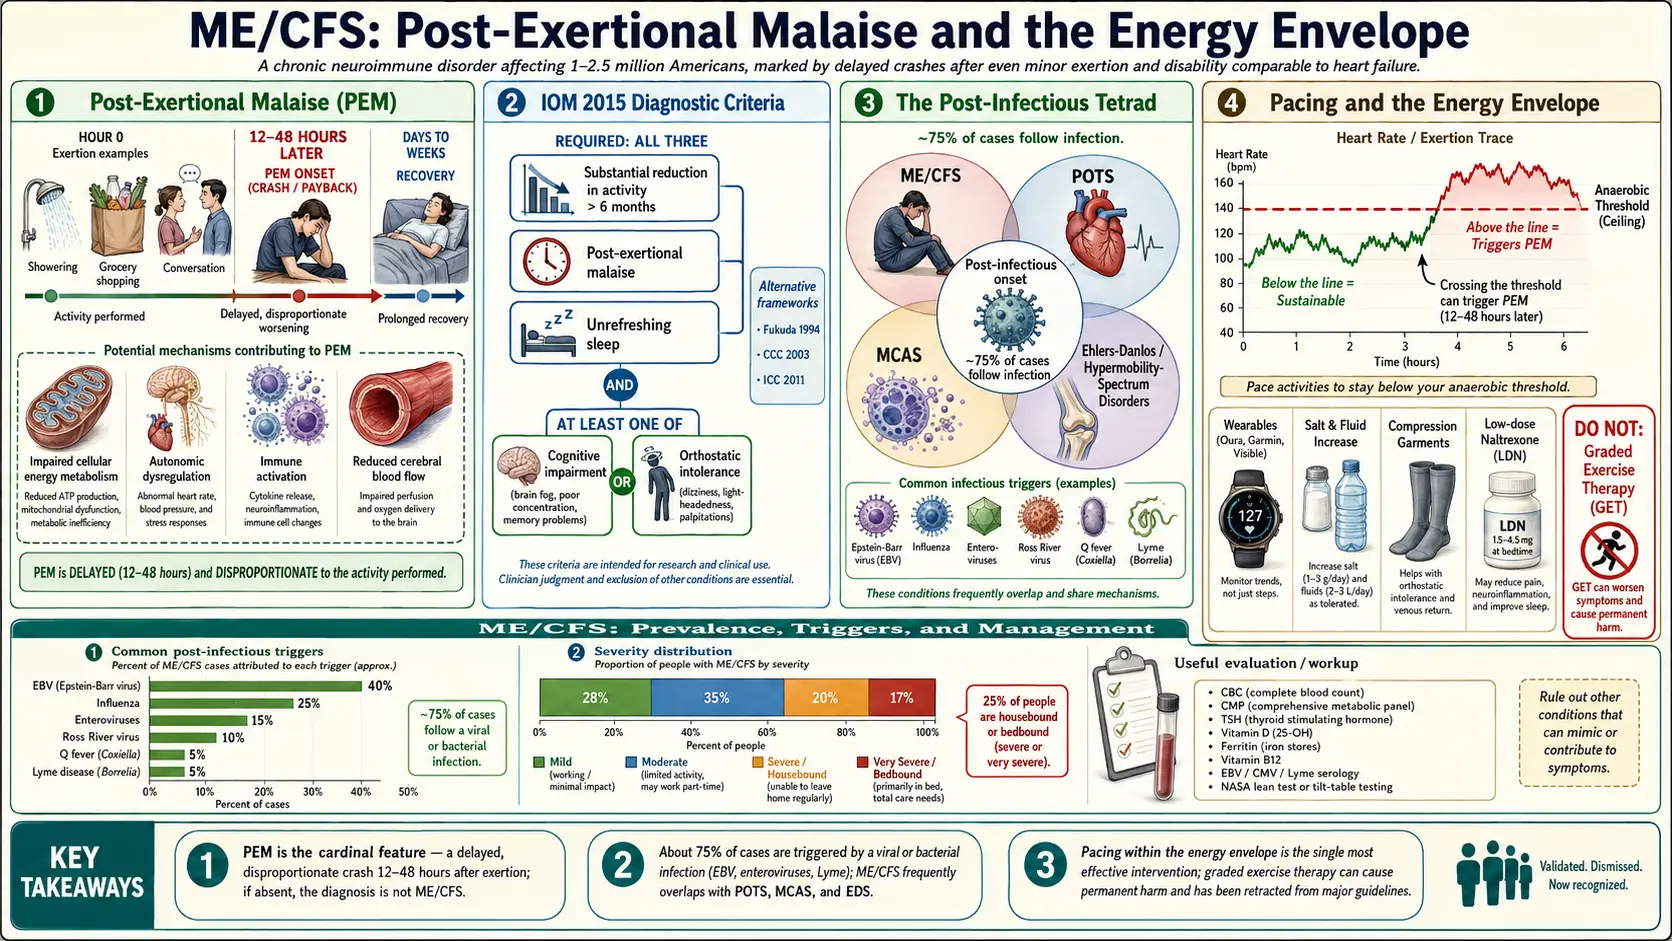
Myalgic encephalomyelitis / chronic fatigue syndrome (ME/CFS) is a serious, chronic, complex multi-system illness affecting an estimated 1 to 2.5 million Americans — likely many more given persistent diagnostic gaps. Its hallmark is post-exertional malaise (PEM), a dramatic worsening of symptoms after even minor physical, cognitive, or emotional exertion, lasting days to weeks and often completely disproportionate to the triggering activity. Unlike ordinary fatigue, myalgic encephalomyelitis/chronic fatigue syndrome is not relieved by rest, is often precipitated by a viral illness, and carries levels of functional disability comparable to heart failure or late-stage cancer.
This article covers diagnostic criteria, the critical distinction of PEM, common triggers, overlapping conditions, and the current management framework that prioritizes pacing above all.
What Myalgic Encephalomyelitis/Chronic Fatigue Syndrome Is
Myalgic encephalomyelitis/chronic fatigue syndrome is a neuroimmune disorder characterized by profound fatigue, post-exertional worsening, unrefreshing sleep, cognitive impairment (“brain fog”), and orthostatic intolerance, persisting for at least six months. It is distinguished from depression and from generic fatigue by the characteristic PEM response, which can be triggered by activities as modest as showering, grocery shopping, or holding a conversation.
Post-Exertional Malaise — The Cardinal Feature
PEM is a delayed, prolonged, disproportionate worsening of symptoms typically appearing 12–48 hours after exertion and lasting days to weeks. Patients describe it as “crashing” or “payback.” The pathophysiology appears to involve impaired cellular energy metabolism, autonomic dysregulation, immune activation, and altered cerebral blood flow — distinct mechanisms from deconditioning. Identifying PEM is the single most important diagnostic step; if it is absent, the diagnosis is something else.
Diagnostic Criteria
The 2015 IOM/NAM criteria require all three core symptoms:
- Substantial reduction or impairment in pre-illness activity levels, lasting >6 months, accompanied by fatigue that is often profound, not the result of ongoing exertion, and not substantially alleviated by rest.
- Post-exertional malaise.
- Unrefreshing sleep.
Plus at least one of:
- Cognitive impairment.
- Orthostatic intolerance.
Symptoms and Overlap
- Flu-like symptoms, tender lymph nodes, sore throat
- Headaches (often new or worse than previous pattern)
- Muscle and joint pain without swelling
- Temperature dysregulation
- Food and chemical sensitivities
- Gastrointestinal symptoms
- Dysautonomia (orthostatic tachycardia, palpitations, presyncope)
Myalgic encephalomyelitis/chronic fatigue syndrome frequently overlaps with postural orthostatic tachycardia syndrome (POTS), mast cell activation syndrome (MCAS), Ehlers-Danlos/hypermobility spectrum disorders, and fibromyalgia — together sometimes called the “tetrad” of post-infectious/dysautonomic syndromes.
Triggers and Mechanisms
About 75 percent of cases follow an acute viral illness — mononucleosis (Epstein-Barr virus), influenza, enteroviruses, Ross River virus, Q fever, Lyme disease, and other infections. Long-term post-viral fatigue syndromes resemble myalgic encephalomyelitis/chronic fatigue syndrome closely. Proposed mechanisms include persistent immune activation, reduced natural-killer-cell function, autonomic dysregulation, mitochondrial dysfunction, reduced cerebral blood flow, and autoantibodies against autonomic receptors.
Workup
- CBC, CMP, CRP, erythrocyte sedimentation rate (ESR), thyroid-stimulating hormone (TSH), free T4, cortisol, hemoglobin A1c (HbA1c), vitamin D, ferritin, B12.
- Celiac screen, iron studies.
- Epstein-Barr virus (EBV), cytomegalovirus (CMV), Lyme, babesia if indicated.
- Orthostatic vitals or a 10-minute stand test; tilt-table testing if postural orthostatic tachycardia syndrome is suspected.
- Sleep study to exclude obstructive sleep apnea.
- Age-appropriate cancer screening.
Management — Pacing Above All
- Pacing. Staying strictly within one’s “energy envelope” to avoid triggering PEM. This is the single most effective intervention. Heart-rate monitoring during daily activities, typically staying under an anaerobic threshold calculated from baseline, helps patients pace objectively.
- Sleep hygiene and pharmacological sleep support where needed.
- Orthostatic intolerance. Increased salt and fluid, compression garments, midodrine, fludrocortisone, ivabradine where appropriate.
- Symptomatic pain management — low-dose naltrexone, duloxetine, amitriptyline, gabapentin where appropriate.
- Low-dose naltrexone (1.5–4.5 mg at bedtime) is used for ME/CFS, but no published randomized trial in ME/CFS was found in a PubMed search (trials so far are in long COVID and chronic pain); a 2015 Norwegian health-technology review found only very low-quality evidence for low-dose naltrexone in any condition (Ringerike 2015).
- Cognitive load pacing — brain fog improves with reduced cognitive exertion, not pushing through.
- Nutrient repletion as indicated.
- Mental-health support for the adjustment and isolation of chronic illness (not as treatment of the underlying disease).
What to Avoid: Graded Exercise and Cognitive Behavioral Therapy-as-Cure Framings
Historical recommendations of graded exercise therapy (GET) and cognitive behavioral therapy (CBT) framed as curative have been retracted from U.K. NICE guidelines and by most expert bodies. GET can cause severe, sometimes permanent, harm in myalgic encephalomyelitis/chronic fatigue syndrome patients by repeatedly triggering PEM. CBT may help with coping but does not treat the underlying disease. These distinctions matter because many clinicians still recommend them.
Deep-Dive Articles
Post-Exertional Malaise (PEM) Explained
PEM is the cardinal feature that separates myalgic encephalomyelitis/chronic fatigue syndrome from ordinary fatigue. Delayed onset (24-72 h), disproportionate severity, prolonged recovery, and how to recognize it in yourself.
Read the deep dive →2-Day CPET & Objective Testing
The two-day cardiopulmonary exercise test is the gold standard for documenting PEM objectively. Where to get one (Workwell, Bateman Horne, Ithaca), cost, preparation, and disability use.
Read the deep dive →Pacing & Energy Envelope
Heart-rate pacing, anaerobic threshold, the envelope theory, wearables (Oura, Garmin, Visible), rest protocols, and why GET is harmful in myalgic encephalomyelitis/chronic fatigue syndrome.
Read the deep dive →IOM/SEID vs CCC vs ICC Criteria
Four competing diagnostic frameworks — Fukuda 1994, Canadian Consensus Criteria (CCC) 2003, International Consensus Criteria (ICC) 2011, IOM/SEID 2015. Which to use and why it matters.
Read the deep dive →Orthostatic Intolerance
Postural orthostatic tachycardia syndrome, neurally mediated hypotension, and orthostatic intolerance overlap with myalgic encephalomyelitis/chronic fatigue syndrome. Tilt testing, NASA lean test, salt/fluids/compression, and when medications help.
Read the deep dive →Post-Viral Triggers: Epstein-Barr Virus & Others
Epstein-Barr, HHV-6, enterovirus, giardia, and Lyme as common myalgic encephalomyelitis/chronic fatigue syndrome triggers. Testing (antibody panels, polymerase chain reaction, PCR), reactivation vs active infection, and antiviral considerations.
Read the deep dive →Severe & Very Severe Myalgic Encephalomyelitis
25% of myalgic encephalomyelitis/chronic fatigue syndrome patients are housebound or bedbound. Light/sound/touch sensitivity, tube feeding, home-care logistics, caregiver guidance, and the invisibility crisis.
Read the deep dive →Low Dose Naltrexone, Abilify & Experimental Therapies
Low-dose naltrexone, ultra-low-dose aripiprazole (Abilify), rituximab/cyclophosphamide trials, IVIG, and what early-phase research looks promising.
Read the deep dive →Mitochondrial Dysfunction & Energy Metabolism
The CPET data, adenosine triphosphate (ATP) production failure, and evidence for coenzyme Q10 (CoQ10)/carnitine/ribose.
Read the deep dive →Table of Contents
- Deep-Dive Articles
- What Myalgic Encephalomyelitis/Chronic Fatigue Syndrome Is
- Post-Exertional Malaise — The Cardinal Feature
- Diagnostic Criteria
- Symptoms and Overlap
- Triggers and Mechanisms
- Workup
- Management — Pacing Above All
- What to Avoid: Graded Exercise and Cognitive Behavioral Therapy-as-Cure Framings
- Key Research Papers
- Connections
- Featured Videos
Key Research Papers
- Clayton EW (2015). Beyond myalgic encephalomyelitis/chronic fatigue syndrome: an IOM report on redefining an illness. JAMA — PubMed PMID: 25668027
- Bateman L, Bested AC, Bonilla HF, et al. (2021). Myalgic Encephalomyelitis/Chronic Fatigue Syndrome: Essentials of Diagnosis and Management. Mayo Clinic Proceedings — PubMed PMID: 34454716
- Walitt B, Singh K, LaMunion SR, et al. (2024). Deep phenotyping of post-infectious myalgic encephalomyelitis/chronic fatigue syndrome. Nature Communications — PubMed PMID: 38383456
- Keller B, Receno CN, Franconi CJ, et al. (2024). Cardiopulmonary and metabolic responses during a 2-day CPET in myalgic encephalomyelitis/chronic fatigue syndrome: translating reduced oxygen consumption to impairment status to treatment considerations. Journal of Translational Medicine — PubMed PMID: 38965566
- Loebel M, Grabowski P, Heidecke H, et al. (2016). Antibodies to β adrenergic and muscarinic cholinergic receptors in patients with Chronic Fatigue Syndrome. Brain, Behavior, and Immunity — PubMed PMID: 26399744
- van Campen CLMC, Rowe PC, Visser FC (2021). Cerebral blood flow remains reduced after tilt testing in myalgic encephalomyelitis/chronic fatigue syndrome patients. Clinical Neurophysiology Practice — PubMed PMID: 34667909
- Kingdon C, Lowe A, Shepherd C, et al. (2022). What Primary Care Practitioners Need to Know about the New NICE Guideline for Myalgic Encephalomyelitis/Chronic Fatigue Syndrome in Adults. Healthcare (Basel, Switzerland) — PubMed PMID: 36553962
- Cabanas H, Muraki K, Eaton-Fitch N, et al. (2021). Potential Therapeutic Benefit of Low Dose Naltrexone in Myalgic Encephalomyelitis/Chronic Fatigue Syndrome: Role of Transient Receptor Potential Melastatin 3 Ion Channels in Pathophysiology and Treatment. Frontiers in Immunology — PubMed PMID: 34326841
PubMed Topic Searches
Curated PubMed topic searches on myalgic encephalomyelitis/chronic fatigue syndrome. Each link opens a live PubMed query so the result set stays current as new studies are indexed.
- PubMed: Topic search: Myalgic encephalomyelitis chronic fatigue syndrome
- PubMed: Topic search: ME/CFS IOM diagnostic criteria
- PubMed: Topic search: Post-exertional malaise
- PubMed: Topic search: CFS mitochondrial dysfunction
- PubMed: Topic search: ME/CFS cytokine inflammation
- PubMed: Topic search: CFS autonomic dysfunction
- PubMed: Topic search: Pacing ME/CFS
- PubMed: Topic search: Low-dose naltrexone ME/CFS
- PubMed: Topic search: Epstein-Barr virus chronic fatigue
- PubMed: Topic search: CFS two-day CPET
- PubMed: Topic search: ME/CFS prevalence epidemiology
- PubMed: Topic search: ME/CFS treatment review
Connections
- Neurology
- Mitochondria & Adenosine Triphosphate — interactive animation
- Post-Viral Triggers: Epstein-Barr Virus and Others
- Post-Exertional Malaise
- Myalgic Encephalomyelitis/Chronic Fatigue Syndrome Diagnostic Criteria
- Severe and Very Severe Myalgic Encephalomyelitis
- 2-Day CPET and Objective Testing
- Orthostatic Intolerance in Myalgic Encephalomyelitis/Chronic Fatigue Syndrome
- Pacing and the Energy Envelope
- Low Dose Naltrexone, Abilify and Experimental Therapies
- Mitochondrial Dysfunction and Energy Metabolism
- Postural Orthostatic Tachycardia Syndrome
- Mast Cell Activation Syndrome
- Fibromyalgia
- Fatigue
- Brain Fog
- Low-Dose Naltrexone
- Lysine
- Magnesium
- Inflammatory Markers
- Mononucleosis
- Herbs covered on this site that discuss this condition: Muira Puama · Damiana · Noni (Morinda citrifolia)
Featured Videos