The Postural Orthostatic Tachycardia Syndrome (POTS)/Mast Cell Activation Syndrome (MCAS)/Ehlers-Danlos Syndrome (EDS) Triad
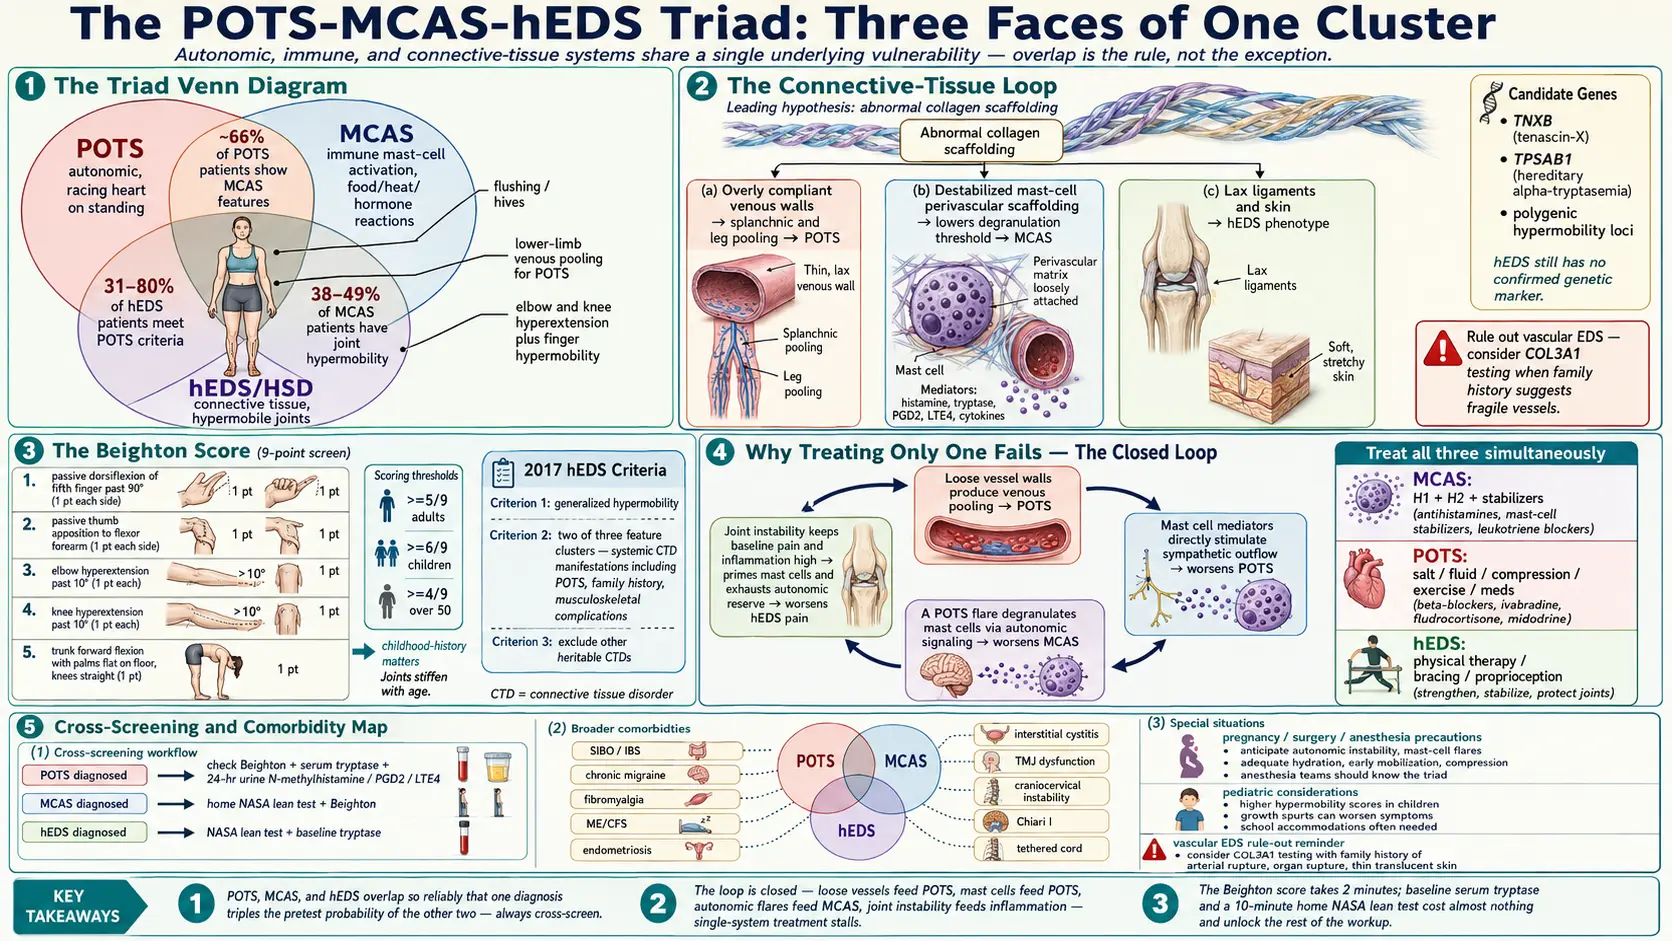
Table of Contents
- The Triad at a Glance
- Why They Cluster
- Hypermobility Spectrum Disorder (HSD) vs hEDS
- The Beighton Score (9-point scale)
- The hEDS 2017 Diagnostic Criteria
- Mast Cell Activation Syndrome Within the Triad
- Screening for the Other Two
- Shared Comorbidities Beyond the Core 3
- Why Treating Only One Often Stalls
- Integrated Treatment Strategy
- Finding Providers Who Understand the Triad
- Pregnancy, Surgery, and Anesthesia in the Triad
- Children and Adolescents
- Key Research Papers
- Connections
- Featured Videos
1. The Triad at a Glance
If you’ve been told that your racing heart, your food reactions, and your bendy joints “can’t possibly all be connected,” you have been told something that contradicts twenty years of clinical research. They are connected. They are connected so reliably that specialists now talk about them as a single clustered phenomenon with three faces.
The three faces are:
- Postural orthostatic tachycardia syndrome (POTS) — a disorder of the autonomic nervous system in which the heart rate spikes 30+ beats per minute on standing, often with lightheadedness, brain fog, and exercise intolerance.
- Mast cell activation syndrome (MCAS) — a disorder of the immune system’s mast cells, which release histamine, tryptase, and other mediators inappropriately in response to food, heat, stress, hormones, or nothing identifiable at all.
- hEDS / HSD — Hypermobile Ehlers-Danlos Syndrome and Hypermobility Spectrum Disorder. Heritable disorders of connective tissue in which collagen-rich structures (joints, ligaments, skin, blood vessel walls, gut wall) are structurally fragile and overly compliant.
The overlap is not rare. A 2017 review of autonomic problems in hypermobile Ehlers-Danlos syndrome (hEDS) by Hakim and colleagues describes postural orthostatic tachycardia syndrome, neurally mediated low blood pressure and other forms of orthostatic intolerance as part of the hEDS picture. It also states that their incidence, prevalence and natural history remain unquantified, although observations from specialist clinics suggest they are frequently seen in hEDS. A companion 2017 review (Seneviratne and colleagues) describes research implicating mast cell dysregulation in a cluster of Ehlers-Danlos syndromes and in dysautonomia.
Draw a Venn diagram of the three and the shared middle is enormous. With one confirmed, the chance of having another is described as far above baseline, which is why specialists screen for the other two.
2. Why They Cluster
No one has proven a single unifying cause, but the leading theory is mechanistically satisfying. A connective tissue defect affects blood vessel walls — the veins of the lower body become abnormally compliant, blood pools on standing, cardiac return drops, and the sympathetic nervous system compensates with a tachycardia (postural orthostatic tachycardia syndrome). The same connective tissue abnormality is thought to disturb the scaffolding around mast cells at every tissue interface, lowering the threshold for degranulation (mast cell activation syndrome). And the hypermobile joints are the most visible expression of the underlying collagen problem.
Genetic hypotheses under active study include TNXB variants (tenascin-X deficiency produces an Ehlers-Danlos syndrome-like phenotype), TPSAB1 duplications (hereditary alpha-tryptasemia, associated with elevated baseline tryptase and a striking overlap with connective tissue symptoms), and a set of polygenic hypermobility loci. No single confirmed gene explains the whole triad, and hEDS itself remains a clinical diagnosis without a confirmed genetic marker.
The takeaway for patients: the mechanism is real, it is being actively researched, and the absence of a single smoking-gun gene does not make your cluster imaginary.
3. Hypermobility Spectrum Disorder (HSD) vs hEDS
Two labels, one spectrum.
HSD describes people who have symptomatic joint hypermobility — pain, subluxations, fatigue — but who do not meet every box of the 2017 hEDS criteria. hEDS is the label for those who do meet all three criterion sets. Functionally, the two groups look and behave very similarly, and many clinicians treat them identically. The label matters for insurance, for research enrollment, and for family counseling, but it does not meaningfully change management.
A crucial caveat: other Ehlers-Danlos syndrome (EDS) subtypes exist and are not part of this triad in the same way. Classical Ehlers-Danlos syndrome (COL5A1/COL5A2), vascular Ehlers-Danlos syndrome (COL3A1), dermatosparaxis, kyphoscoliotic, and rarer subtypes each have a confirmed genetic test and a different management picture. Vascular Ehlers-Danlos syndrome in particular is life-threatening, and the criteria require it to be ruled out when family history or physical findings suggest it. When anything about a presentation is atypical — translucent skin, fragile vessels, a parent who died young of arterial rupture — a full genetic panel is how these other types are excluded before an hEDS label is given.
4. The Beighton Score (9-point scale)
The Beighton score is a fast bedside screen for generalized joint hypermobility. It takes about two minutes and can be done at home, alone or with a partner. One point is scored for each of the following:
- Passive dorsiflexion of the 5th finger past 90° (1 point each side — max 2)
- Passive apposition of the thumb to the flexor forearm (1 point each side — max 2)
- Hyperextension of the elbow past 10° (1 point each side — max 2)
- Hyperextension of the knee past 10° (1 point each side — max 2)
- Forward flexion of the trunk, palms flat on the floor with knees straight (1 point — max 1)
Scoring: ≥5/9 in adults, ≥6/9 in children, and ≥4/9 in adults over 50 suggests generalized joint hypermobility. Scores tend to decrease with age as tissues stiffen, so childhood history matters. Patients whose joints were dramatically loose at age 10 but have stiffened in adulthood still carry the connective tissue pattern.
A Beighton score alone does not diagnose hEDS — it is one of the three criterion sets (see below). But a positive Beighton in a patient with postural orthostatic tachycardia syndrome or mast cell activation syndrome is one of the strongest reasons specialists give for the full workup.
5. The hEDS 2017 Diagnostic Criteria (simplified)
Formal hEDS diagnosis requires all three of the following criteria:
Criterion 1 — Generalized joint hypermobility
A Beighton score at or above the age cutoff: ≥6 in children before puberty and adolescents, ≥5 from puberty to age 50, ≥4 over age 50. When the score is one point below the cutoff, two or more “yes” answers on a five-question history complete the criterion: hands flat on the floor with straight knees (now or ever), thumb bent to touch the forearm (now or ever), contortions or the splits as a child, a shoulder or kneecap that dislocated more than once as a child or teenager, and considering oneself “double jointed”.
Criterion 2 — Two of three feature clusters
- Feature A: Systemic manifestations of a generalized connective tissue disorder — at least five of these twelve: unusually soft or velvety skin; mild skin hyperextensibility; unexplained stretch marks (striae); bilateral piezogenic papules of the heel; recurrent or multiple abdominal hernias; atrophic scarring at two or more sites; pelvic floor, rectal or uterine prolapse without known risk factors; dental crowding with a high or narrow palate; arachnodactyly (positive wrist or thumb sign on both sides); arm span-to-height ratio ≥1.05; mitral valve prolapse on strict echocardiographic criteria; and aortic root dilatation with a Z-score above +2. Postural orthostatic tachycardia syndrome is not one of the twelve items; it is a frequent companion of hEDS rather than a diagnostic criterion.
- Feature B: Positive family history — one or more first-degree relatives independently meeting the criteria.
- Feature C: Musculoskeletal complications — at least one of: musculoskeletal pain in two or more limbs recurring daily for at least 3 months, chronic widespread pain for at least 3 months, or recurrent joint dislocations or frank joint instability without trauma.
At least two of the three feature clusters are required.
Criterion 3 — Exclusion of alternative diagnoses
All of these prerequisites are met: no unusual skin fragility (which points to other Ehlers-Danlos syndrome types); other Ehlers-Danlos syndrome subtypes (classical, vascular, dermatosparaxis, kyphoscoliotic, etc.), Marfan syndrome, Loeys-Dietz, osteogenesis imperfecta, and other heritable and acquired connective tissue disorders are ruled out — by history, examination and, when indicated, a genetic panel. In someone with an acquired connective tissue disease such as lupus or rheumatoid arthritis, hEDS additionally needs both Features A and B; Feature C cannot be counted.
6. Mast Cell Activation Syndrome Within the Triad
Mast cells sit at every tissue interface where the body meets the outside world — skin, gut lining, airways, genitourinary tract — and they communicate constantly with autonomic nerves and connective tissue. When the connective tissue scaffolding is abnormal and the autonomic nervous system is dysregulated, mast cells appear to lose their usual regulatory restraint.
Common mast cell activation syndrome symptoms in the triad:
- Flushing, especially after meals, heat, stress, or exercise
- Hives, dermatographism, chronic itch
- Gastrointestinal (GI) reactions — nausea, cramping, diarrhea, bloating after specific foods or “random” triggers
- Anaphylaxis-like episodes without a classic immunoglobulin E-mediated allergen
- Food-dependent exercise-induced anaphylaxis — fine at rest, fine eating alone, but a reaction when the two combine
- Chronic sinus congestion, throat clearing, reactive airways
- Menstrual-cycle-linked symptom flares (estrogen primes mast cells)
Screening tests
- Serum tryptase — drawn at baseline and, ideally, during a symptomatic flare. A rise of 20% + 2 ng/mL above baseline during a flare is one of the validated mast cell activation syndrome criteria.
- 24-hour urine N-methylhistamine, prostaglandin D2 (PGD2), and leukotriene E4 (LTE4) — chilled collection, with the patient off antihistamines where safe.
Cross-link: mast cell activation syndrome Testing Guide.
7. Screening for the Other Two
When Postural Orthostatic Tachycardia Syndrome Is Diagnosed
A Beighton score costs nothing and takes about two minutes. A score of ≥5 is the usual point for referral to an Ehlers-Danlos syndrome-aware geneticist or rheumatologist. The mast cell side is screened with a baseline serum tryptase and a 24-hr urine N-methylhistamine (plus PGD2 and LTE4 where available).
When Mast Cell Activation Syndrome Is Diagnosed
A home NASA lean test (see Tilt Table and NASA Lean Test) is the usual first check. A heart-rate rise of ≥30 bpm within 10 minutes of standing is a strong postural orthostatic tachycardia syndrome signal and the usual threshold for a formal workup. A Beighton score can be checked the same day.
When hEDS or HSD Is Diagnosed
A NASA lean test at home screens for postural orthostatic tachycardia syndrome. Mast cell activation syndrome-type symptoms — flushing, food reactions, chronic rashes, migraines, unexplained anaphylaxis — are the reason for the mast cell activation syndrome workup above. Some specialists take a baseline tryptase even without symptoms, because it sets an individual reference point for the future.
8. Shared Comorbidities Beyond the Core 3
The triad is often the center of a larger constellation. Conditions that cluster with one or more of the three at rates well above baseline include:
- Small intestinal bacterial overgrowth (SIBO) and irritable bowel syndrome (IBS) — autonomic dysmotility plus connective tissue laxity of the gut wall. See small intestinal bacterial overgrowth.
- Chronic migraine and new daily persistent headache
- Fibromyalgia and chronic widespread pain
- Myalgic encephalomyelitis/chronic fatigue syndrome (ME/CFS)
- Endometriosis and adenomyosis
- Interstitial cystitis / bladder pain syndrome
- Temporomandibular joint (TMJ) dysfunction and jaw subluxation
- Cervicocranial instability and craniocervical junction disorders
- Tethered cord syndrome
- Chiari I malformation
Not every patient has every one. But three of these on one chart fits the clustering described above better than coincidence does.
9. Why Treating Only One Often Stalls
Clinicians experienced with the triad describe progress stalling when someone has all three and only one is treated.
- Treating only postural orthostatic tachycardia syndrome misses the mast cell activation that can trigger autonomic flares with meals, menstruation, or a virus.
- Treating only mast cell activation syndrome still leaves the crash on standing, because the hemodynamic problem is not addressed.
- Managing only hypermobility with physical therapy (PT) and bracing leaves the autonomic and immune layers untouched, and people describe each PT session leaving them horizontal for three days.
The three feed each other in a closed loop. Loose vessel walls produce venous pooling, which produces postural orthostatic tachycardia syndrome. Mast cell mediators directly stimulate sympathetic outflow, worsening postural orthostatic tachycardia syndrome. A postural orthostatic tachycardia syndrome flare degranulates mast cells via autonomic signaling, which worsens mast cell activation syndrome. Mechanical joint instability keeps baseline pain and inflammation high, which primes mast cells and exhausts the autonomic reserve. None of the loops close unless all three are being addressed.
10. Integrated Treatment Strategy
Clinicians experienced in the triad tend to sequence interventions roughly in this order:
Step 1 — Mast cell stabilization first
Reducing the baseline trigger load pays dividends on everything else. An H1 + H2 blocker stack (a second-generation H1 such as cetirizine or fexofenadine plus an H2 such as famotidine), often with a mast cell stabilizer (cromolyn sodium before meals, quercetin, or luteolin), lowers the background hum enough that the postural orthostatic tachycardia syndrome interventions actually work.
Step 2 — Fluid and salt loading
The 2015 Heart Rhythm Society expert consensus statement lists up to 2–3 liters of water and 10–12 g of table salt (sodium chloride) a day as something that “may be considered” for postural orthostatic tachycardia syndrome — a class IIb, or weaker, recommendation. Those are grams of salt, not sodium: table salt is about 40% sodium, so 10–12 g of salt carries roughly 4–5 g of sodium. The same statement calls an intravenous infusion of up to 2 liters of saline reasonable for short-term flares, while regular, repeated saline infusions are not recommended. See Salt and Hydration Protocol.
Step 3 — Compression and recumbent exercise
Waist-high 20–30 mmHg compression during upright time. Recumbent and water-based reconditioning (the Levine / Dallas protocol). See Compression and Exercise Program.
Step 4 — Subtype-targeted medications
Beta blockers, ivabradine, midodrine, fludrocortisone, pyridostigmine — selection depends on the postural orthostatic tachycardia syndrome subtype (hyperadrenergic, neuropathic, hypovolemic). See Medications Guide and Subtypes.
Step 5 — Joint protection
PT focused on proprioception and joint stabilization, not on stretching. Bracing during flares. Programmes steer away from end-range hyperextension. Isometric and closed-chain strengthening build the ligamentous support the collagen cannot provide on its own.
Step 6 — Address the gut overlap
Bloating, reflux, or post-prandial symptoms in triad patients are a common reason for a small intestinal bacterial overgrowth workup. See small intestinal bacterial overgrowth.
11. Finding Providers Who Understand the Triad
There are not enough of them.
- The Ehlers-Danlos Society Healthcare Provider Directory — the most comprehensive international listing of Ehlers-Danlos syndrome-aware clinicians.
- Dysautonomia International physician list — postural orthostatic tachycardia syndrome and autonomic-focused providers, searchable by state.
- The Mast Cell Disease Society — directory of allergists and immunologists familiar with mast cell activation syndrome.
- The Ehlers-Danlos Society “zebra network” — patient-maintained peer recommendations.
Virtual consults are common given specialist scarcity; many of the leading clinicians see patients from across the country by telehealth. Waitlists of 3 to 12 months are common for top-tier specialists. In the meantime, a well-informed primary care doctor paired with PT, a dietitian, and a sympathetic allergist can cover most of the early management.
12. Pregnancy, Surgery, and Anesthesia in the Triad
Pregnancy
Hormonal shifts, plasma volume changes, and mechanical loading can trigger or dramatically worsen all three conditions. Postural orthostatic tachycardia syndrome frequently unmasks in pregnancy or postpartum. Mast cell activation syndrome can flare spectacularly with estrogen surges. Joint instability worsens with relaxin-driven ligament softening. Pregnancies in triad patients are best co-managed with a maternal-fetal medicine specialist who knows the pattern.
Surgery
hEDS tissue holds sutures poorly and bleeds more than expected. Postural orthostatic tachycardia syndrome worsens post-operatively from bed rest, fluid shifts, and pain. Mast cell activation syndrome patients can react to anesthetic agents, preservatives, latex, adhesives, and intravenous (IV) contrast.
Anesthesia
Agents commonly flagged for caution: succinylcholine, morphine, codeine, meperidine, atracurium, and many neuromuscular blockers with histamine-releasing profiles. Agents generally better tolerated: fentanyl, propofol, rocuronium, midazolam, and dexmedetomidine. Local anesthetics often need to be dosed higher in hEDS because they appear to be cleared or distributed differently in hypermobile tissue — which is why it is raised with the anesthesiologist before surgery.
Pre-op letters to the anesthesia team are critical. The Ehlers-Danlos Society publishes template pre-op letters that list the patient’s diagnoses, known triggers, safer agent lists, and positioning precautions, for use at surgical consultations.
13. Children and Adolescents
In children, hypermobility typically shows up first — often years before the autonomic and mast cell pieces declare themselves. Signs that parents and pediatricians watch for:
- Chronic joint pain, especially knees and ankles, that comes and goes
- Easy bruising without a bleeding disorder workup abnormality
- Chronic headaches, especially orthostatic or exertional
- Fainting, near-fainting, or dizziness on standing in hot showers, in line, or first thing in the morning
- “Picky eating” that turns out to be food reactions — flushing, tummy aches, throat tickling, hives
- Recurrent hernias, rectal prolapse, or dental crowding in a flexible child
Early identification lets families front-load joint protection, proprioceptive strengthening, salt and hydration habits, and trigger awareness before the crash years hit — which for many patients is the late teens and early twenties.
Key Research Papers
- Malfait F, et al. The 2017 international classification of the Ehlers-Danlos syndromes. Am J Med Genet. 2017;175C(1):8–26. — doi:10.1002/ajmg.c.31552
- Hakim A, O’Callaghan C, De Wandele I, Stiles L, Pocinki A, Rowe P. Cardiovascular autonomic dysfunction in Ehlers-Danlos syndrome-Hypermobile type. Am J Med Genet C Semin Med Genet. 2017;175(1):168–174. — PubMed PMID: 28160388
- Seneviratne SL, et al. Mast cell disorders in Ehlers-Danlos syndrome. Am J Med Genet. 2017. — doi:10.1002/ajmg.c.31555
- Arnold AC, Ng J, Raj SR. Postural tachycardia syndrome — diagnosis, physiology, and prognosis. Auton Neurosci. 2018;215:3–11. — PubMed PMID: 29523389
- Sheldon RS, Grubb BP 2nd, Olshansky B, et al. 2015 heart rhythm society expert consensus statement on the diagnosis and treatment of postural tachycardia syndrome, inappropriate sinus tachycardia, and vasovagal syncope. Heart Rhythm. 2015;12(6):e41–e63. — PubMed PMID: 25980576
- The Ehlers-Danlos Society. Diagnostic Criteria for Hypermobile Ehlers-Danlos Syndrome (hEDS): checklist of the 2017 criteria (Malfait and colleagues). — ehlers-danlos.com (PDF)
PubMed Topic Searches
Curated PubMed topic searches for the triad. Each link opens a live PubMed query so you always see the most current studies.
- PubMed: POTS and EDS hypermobility
- PubMed: MCAS and EDS
- PubMed: Hypermobility and autonomic dysfunction
- PubMed: Beighton score and hypermobility
- PubMed: Mast cell activation and hypermobility
- PubMed: POTS, MCAS, and Ehlers-Danlos
- PubMed: Hereditary alpha-tryptasemia and TPSAB1
- PubMed: hEDS 2017 diagnostic criteria
Connections
- Neurology
- Postural Orthostatic Tachycardia Syndrome Overview
- Mast Cell Activation Syndrome
- Small Intestinal Bacterial Overgrowth
- Postural Orthostatic Tachycardia Syndrome Subtypes
- Medications Guide
- Compression and Exercise
- Tilt Table Test
- Salt and Hydration
- Vagus Nerve and Autonomic Retraining
- Low Dose Naltrexone for Postural Orthostatic Tachycardia Syndrome
- Ehlers-Danlos Syndrome
- Fibromyalgia
- Myalgic Encephalomyelitis/Chronic Fatigue Syndrome
- Alpha-Gal Syndrome
- Mast Cell Activation Syndrome Testing Guide
- Brain Fog
- Lightheadedness
- Fibromyalgia and Myalgic Encephalomyelitis/Chronic Fatigue Syndrome Overlap