⚠ Evidence warning: Clinical trials or other evidence do not support the claims that daily humming, gargling, cold-water face dunks and cold exposure raise baseline vagal tone and stabilize postural orthostatic tachycardia syndrome, that morning heart rate variability (RMSSD) typically rises from 15-30 ms to 50-80 ms with this practice, and that commercial brain-retraining programs help postural orthostatic tachycardia syndrome. This page keeps it as a report of what people, websites or other media say.
Vagus Nerve and Autonomic Retraining for Postural Orthostatic Tachycardia Syndrome (POTS)
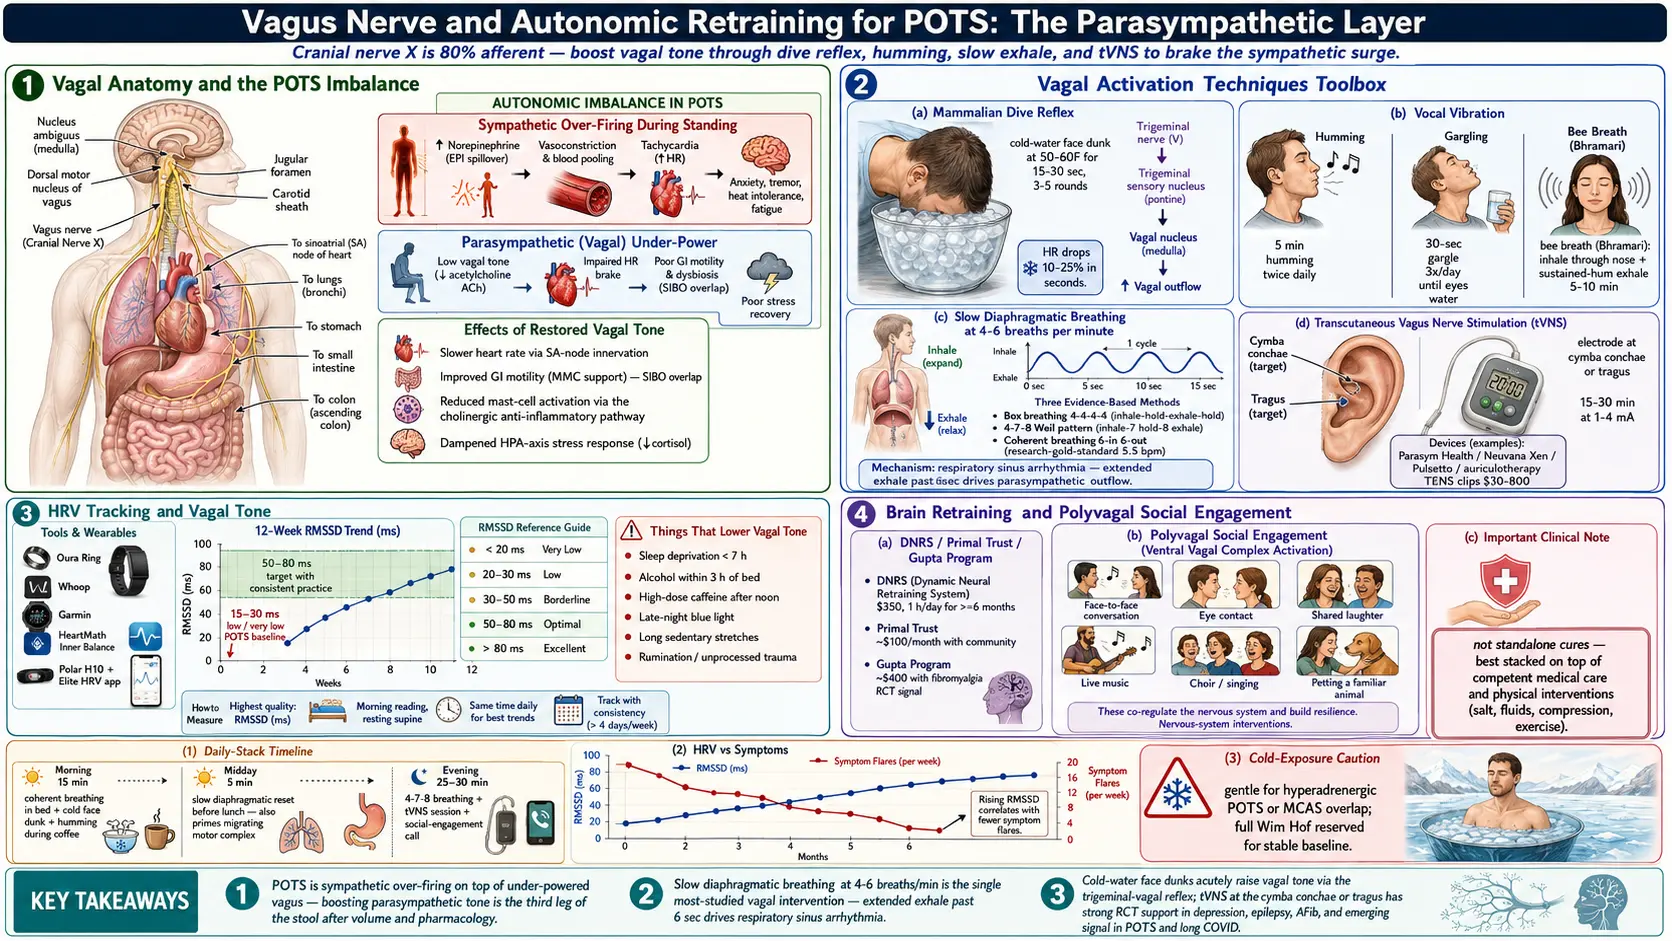
Table of Contents
- Why the Vagus Nerve Matters for Postural Orthostatic Tachycardia Syndrome
- How to Measure Vagal Tone
- The Dive Reflex (Cold-Water Face Dunk)
- Humming, Chanting, Gargling
- Slow Diaphragmatic Breathing
- Transcutaneous Vagus Nerve Stimulation (tVNS)
- Cold Exposure Beyond Face Dunks
- Brain Retraining Programs
- Polyvagal Theory and Social Engagement
- Things That Lower Vagal Tone
- Integration Strategy — A Daily Vagal Practice
- Measuring Results
- What This Is Not
- Key Research Papers
- Featured Videos
1. Why the Vagus Nerve Matters for Postural Orthostatic Tachycardia Syndrome
The vagus nerve is cranial nerve X — the longest nerve in the body and the main highway of the parasympathetic “rest and digest” nervous system. It wanders from the brainstem down through the neck, heart, lungs, and gut, carrying roughly 80% afferent (body-to-brain) and 20% efferent (brain-to-body) fibers.
In postural orthostatic tachycardia syndrome (POTS), the autonomic balance is broken in a specific way: the sympathetic (fight-or-flight) branch is over-firing, while the parasympathetic branch — chiefly the vagus — is under-powered. Standing up, which should produce a modest sympathetic surge that is quickly braked by vagal tone, instead produces a runaway tachycardia that nothing slows down.
Boosting vagal tone does several things that matter for postural orthostatic tachycardia syndrome at once: it slows heart rate through direct sinoatrial-node innervation, improves gastrointestinal motility (relevant to the large overlap between postural orthostatic tachycardia syndrome and small intestinal bacterial overgrowth, SIBO), reduces mast-cell activation via the cholinergic anti-inflammatory pathway, and dampens the hypothalamic-pituitary-adrenal-axis stress response. This isn't mystical. It's anatomy.
The practical implication: the vagal layer is a real, measurable, trainable system. Most postural orthostatic tachycardia syndrome treatment focuses on volume (salt, fluids, compression) and pharmacology (beta-blockers, ivabradine, midodrine, fludrocortisone). The vagal layer is the third leg of the stool, and for many patients it's the one that finally stabilizes their baseline.
2. How to Measure Vagal Tone
Heart rate variability (HRV) is the most practical proxy for vagal tone available to consumers. HRV is the beat-to-beat variation in heart rate — higher variability means the vagus is actively modulating the sinus node, which is the healthy pattern. A metronomically steady heartbeat is a sick heartbeat.
Consumer devices that track HRV include:
- Wearable heart-rate-variability rings — overnight RMSSD (root mean square of successive differences between heartbeats, the usual HRV number); trend data
- Wrist-worn trackers — continuous, some subscription-based
- Sports watches — HRV status feature on newer models
- Biofeedback sensors — earlobe or finger sensor; pair biofeedback with training
- Chest-strap heart monitors paired with an HRV app — the lowest-cost route
Most postural orthostatic tachycardia syndrome patients start with a morning RMSSD in the 15-30 ms range (considered low to very low). With consistent practice across the techniques below, moving into the 50-80 ms range over several months is a realistic target, and it typically tracks with symptom improvement.
3. The Dive Reflex (Cold-Water Face Dunk)
The mammalian dive reflex is the fastest way to acutely raise vagal tone. Mechanism: cold water on the forehead, cheeks, and around the eyes stimulates the trigeminal nerve, which synapses onto the vagal nucleus in the brainstem and triggers a rapid bradycardia — the heart rate can drop 10-25% in seconds.
The usual method: a bowl of cold tap water plus a handful of ice cubes (about 50-60°F). After a breath, the face is immersed from forehead to chin for 15-30 seconds, then lifted for a breath, 3-5 times in a row.
People use it during a postural orthostatic tachycardia syndrome flare, a tachycardia episode, or a rising panic response — it is described as working within one cycle. Used daily as a morning ritual, it is also described as raising tonic vagal baseline over a 4-8 week horizon. Where face immersion isn't practical, a cold gel pack held over the forehead and cheeks for 30-60 seconds is described as producing a smaller but measurable version of the same reflex.
4. Humming, Chanting, Gargling
The vagus branches through the throat, innervating the muscles of the soft palate, pharynx, and larynx. Vibrating those tissues mechanically stimulates vagal afferents — this is why singers, chanters, and meditators across every tradition end up discovering vocal vibration as a nervous-system tool.
Humming
The usual practice is 5 minutes of sustained “mmmmm” at a pitch that sits comfortably in the chest, twice daily. The felt sense is a buzz in the sinuses and upper throat.
Gargling
The usual practice is 30 seconds with plain water, 3 times a day, hard enough to make the eyes water. Practitioners describe watering eyes as a sign of vagal activation — the nerve firing.
Chanting “Om” or Singing
Long slow exhalations amplify the vagal effect because the parasympathetic system is already activated by extended exhale. Chanting combines the vibration and the slow-exhale mechanisms simultaneously.
Bee Breath (Bhramari Pranayama)
Classical yogic humming breath: the inhale is through the nose and the exhale is a sustained hum, with the fingers optionally closing the ears to amplify the internal vibration. Practised for 5-10 minutes in the morning — one of the most consistently effective vagal practices in published breathing studies.
5. Slow Diaphragmatic Breathing
Slow diaphragmatic breathing is the single most-studied vagal intervention, and the effect size is large enough that it shows up on HRV monitors within minutes.
The mechanism is called respiratory sinus arrhythmia: heart rate naturally rises on inhale (sympathetic) and falls on exhale (parasympathetic). Extending the exhale past roughly 6 seconds drives parasympathetic outflow through the nucleus ambiguus.
The usual practice: 4-6 breaths per minute, for 5-10 minutes, 2-3 times daily, with one hand on the belly to check that the diaphragm — not the chest — is doing the work.
Patterns commonly used:
- Box breathing — 4 in, 4 hold, 4 out, 4 hold
- 4-7-8 breathing — inhale 4, hold 7, exhale 8 (Andrew Weil's pattern)
- Coherent breathing — about 5.5 seconds in, 5.5 seconds out (the research-gold-standard 5.5 breaths per minute)
Breathing-pacer apps (some free) and meditation apps offer guided pacing; a plain metronome app set to 10 beats per minute serves the same purpose.
6. Transcutaneous Vagus Nerve Stimulation (tVNS)
The auricular branch of the vagus surfaces at the cymba conchae and tragus of the outer ear — one of the only places the vagus is accessible through skin. tVNS devices deliver small electrical pulses at that location, producing cortical and brainstem vagal activation without surgery.
Devices
- Ear vagus-nerve stimulators — consumer ear-clip devices that deliver pulses to the outer ear
- Stimulating earbuds — pulsed current synced to music
- Neck-worn stimulators — target the vagus in the neck (cervical vagus)
- Hybrid devices — electrical stimulation combined with other biosignal protocols
- Auriculotherapy TENS clips — inexpensive generic ear-clip electrodes hooked to a standard TENS (transcutaneous electrical nerve stimulation) unit
The vagus nerve stimulator that the U.S. Food and Drug Administration approved for stroke rehabilitation is an implanted device (premarket approval P210007, listed by the FDA as “Stimulator, autonomic nerve, implanted for stroke rehabilitation”), not an ear device.
Protocol
Home users typically run 15-30 minutes per day, starting at 1-2 mA and turning the current up until a clear tingle or mild pulsation is felt with no pain or burning; most users are described as settling in the 2-4 mA range. The one sham-controlled trial in postural orthostatic tachycardia syndrome (below) used a different schedule: 1 hour daily at 20 Hz, with the current set 1 mA below the discomfort threshold.
Evidence
According to a 2022 review, it is implanted vagus nerve stimulation in the neck — which needs surgery — that is approved for the treatment of epilepsy, depression, obesity and stroke rehabilitation. A 2018 review describes “preliminary evidence” that vagus nerve stimulation is a promising add-on treatment for depression that has not responded to other treatment. Those approvals do not transfer automatically to ear devices.
What is not known about ear stimulation. The 2022 review explains that several sensory nerves, with overlapping territories, supply the outer ear: the ear branch of the vagus, the auriculotemporal nerve, the great auricular nerve and, to some extent, the lesser occipital nerve. Vagus nerve stimulation requires activation of A-beta (Aβ) nerve fibers, and these are far less common in the ear branch of the vagus than in the vagus in the neck. For that reason the best stimulation sites, settings and treatment schedules for ear stimulation “need to be further explored.”
The first sham-controlled trial in postural orthostatic tachycardia syndrome. In 2024 Stavrakis and colleagues published a double-blind randomized trial in women with postural orthostatic tachycardia syndrome (12 given active stimulation at the tragus, 14 given sham stimulation at the ear lobe). An ear clip delivered stimulation either to the tragus (active, 12 women) or to the ear lobe (sham, 14 women) for 1 hour a day for 2 months. At 2 months the rise in heart rate on standing was 17.6 beats per minute in the active group versus 31.7 in the sham group (P = 0.01). Anti-adrenergic autoantibodies and inflammatory cytokines were lower and heart rate variability was better in the active group, and no device-related side effects were seen. The researchers wrote that further studies are warranted. The risk profile is excellent.
Cost
$300-800 for medical-grade devices; $30-60 for auriculotherapy clips plus a basic TENS unit. The cheaper setup is a low-cost way to test individual response before buying a more polished device.
7. Cold Exposure Beyond Face Dunks
Beyond the acute dive reflex, broader cold exposure builds tonic vagal capacity:
- Cold showers — 30-60 seconds of cold at the end of a normal warm shower
- Ice packs on chest or back of neck — 2-5 minutes while seated
- Popular breathing-plus-cold-plunge methods — advanced; described as giving a powerful HRV lift
Cold can backfire in some patients. Cold stress can trigger mast-cell flares in patients with concurrent mast cell activation syndrome (MCAS), and can transiently spike catecholamines in the hyperadrenergic postural orthostatic tachycardia syndrome subtype. In people with either condition whose baseline is currently unstable, cold exposure beyond the face dunk carries that flare risk.
8. Brain Retraining Programs
Systematic limbic-retraining programs have a decidedly mixed reputation, partly because they get marketed with cure-all language they don't deserve. The underlying neuroscience — that a chronically sensitized limbic system can be retrained through structured, repeated exposure and state-shift practice — is real. Neuroplasticity is not imaginary, and the overlap between chronic-illness populations and altered limbic reactivity is well-documented.
These programs are not standalone cures. They are generally presented as an add-on to medical care and the physical interventions (salt, fluids, compression, exercise reconditioning).
Commercial brain-retraining programs
Several commercial brain-retraining programs are sold, in different formats:
- DVD or streaming courses — around $350-400. One widely used course asks for 1 hour per day for a minimum of 6 months and has a large anecdotal following in the postural orthostatic tachycardia syndrome, mast cell activation syndrome, and multiple-chemical-sensitivity communities; another was originally developed for myalgic encephalomyelitis/chronic fatigue syndrome (ME/CFS) and fibromyalgia.
- Monthly subscriptions — around $100 a month, with an online community, live calls, and polyvagal and somatic work layered on top of the retraining core.
- Apps — pain-focused retraining delivered by phone.
- Short in-person seminars — one short-format seminar program has drawn controversy.
What the trials show
No trial of these programs in postural orthostatic tachycardia syndrome is cited here. Two randomized trials have tested programs of this kind in related conditions:
- Fibromyalgia and chronic fatigue (2012). A single-blind randomized trial at a tertiary-care fibromyalgia and chronic-fatigue clinic added a 2.5-hour “amygdala retraining” course, with tools adapted from an existing program and a home-study video course, to standard care. Of the 44 randomized patients who completed baseline assessments, only 21 completed the study (14 on standard care and 7 in the retraining group). The retraining group had statistically significant improvements in self-reported physical health, energy, pain, symptom distress and fatigue scores compared with standard care alone.
- Adolescents with chronic fatigue syndrome (2018). An open (unblinded) randomized trial of 100 young people aged 12-18 with mild or moderate chronic fatigue syndrome/ME added a commercial brain-retraining program to specialist medical care (51 were randomized to the program). Physical function, measured on the questionnaire-based 36-Item Short-Form Health Survey physical function scale, was better with the program at 6 months (adjusted difference 12.5 points) and improved further at 12 months (15.1 points); fatigue and anxiety were lower at 6 months. The outcomes were questionnaires answered by the participants, and the trial was not blinded.
All of these programs ask for daily commitment. Users commonly describe 2-6 months before a clear shift, and testimonials promising faster results go beyond what users typically report.
9. Polyvagal Theory and Social Engagement
Stephen Porges's polyvagal theory reframes the vagus into three evolutionary layers, of which the most recent — the ventral vagal complex — is the one engaged by safe social connection.
The practical takeaway is small and profound: face-to-face conversation, eye contact, shared laughter, live music, and singing with other people directly stimulate ventral vagal tone. Chronic illness is isolating, and isolation degrades vagal tone in a measurable feedback loop. Deliberate social contact — even 20 minutes of real conversation with one person — is a nervous-system intervention, not a luxury.
Things that count: a weekly meal with a friend, a choir or singing group, a video call with eye contact (not text chat), petting a familiar animal, playing with a child. Things that don't: doomscrolling, parasocial video watching, text threads.
Polyvagal theory is disputed. A 2023 review by Grossman argues that each of the theory’s five basic premises has been shown to be “either untenable or highly implausible” based on the available scientific literature. The theory leans on one measurement — respiratory sinus arrhythmia, the rise and fall of heart rate with each breath — and the review calls treating it as equivalent to general vagal tone “a category mistake”: it is an approximate index of vagal activity, not vagal activity itself.
10. Things That Lower Vagal Tone
Everything above works faster when the vagal drains are plugged:
- Chronic sleep deprivation (below 7 hours)
- Alcohol — especially within 3 hours of bed; crushes overnight HRV
- High-dose caffeine, particularly after noon
- Screen time in bed and late-night blue light
- Stimulant medications used poorly or at too high a dose
- Long sedentary stretches (the vagus tracks with movement)
- Rumination, catastrophizing, unprocessed trauma
Addressing these is slower, less glamorous, and cumulative — and often the reason a perfectly good daily practice doesn't move the HRV needle.
11. Integration Strategy — A Daily Vagal Practice
An example of how the practices above are combined into a daily routine:
Morning (15 minutes):
- 5 minutes of coherent breathing (about 5.5 seconds in / 5.5 seconds out) before getting out of bed
- Cold-water face dunk — 3 rounds of 20 seconds
- 5 minutes of humming or bee breath while making coffee or tea
Midday (5 minutes):
- Slow diaphragmatic breathing reset before lunch — this also primes the migrating motor complex and supports digestion
Evening (25-30 minutes):
- tVNS for 20 minutes while watching TV or reading
- Gargling with water before brushing teeth, 30 seconds
- Screens off 1 hour before bed
Weekly:
- 1-2 cold showers (30-60 seconds at the end)
- Intentional in-person social time — one meaningful conversation minimum
- One session of a structured brain-retraining practice, for people following a program
12. Measuring Results
The measures commonly tracked, as weekly averages rather than single data points:
- Morning HRV (RMSSD) — primary metric
- Standing heart rate at 1, 3, and 10 minutes — the core postural orthostatic tachycardia syndrome signal
- Symptom diary — presyncope episodes, brain fog days, crash days
- NASA Lean Test monthly as an objective standing-tolerance benchmark
The timeline usually described is 4-8 weeks before HRV begins to shift and 3-6 months before symptom patterns meaningfully change, with daily consistency described as mattering more than weekly intensity.
13. What This Is Not
This is not a replacement for medications, compression garments, or salt-and-fluid protocols. It is not a cure for severe postural orthostatic tachycardia syndrome. It is not a substitute for addressing mast cell activation syndrome or Ehlers-Danlos syndrome (EDS) comorbidity. And it is emphatically not a suggestion that postural orthostatic tachycardia syndrome is psychological or that you could meditate your way out of it — the dysautonomia is physiological, the mechanism for vagal intervention is physiological, and the evidence is physiological.
What it is: a near-zero-cost, near-zero-side-effect adjunct with genuine mechanistic backing and a growing clinical evidence base. For patients who can't tolerate medications because of mast cell activation syndrome crossreactivity or who face financial barriers to specialist care, it's often the most effective lever available. For patients already on good pharmacology, it's the layer that often pushes stability from “functional” to “actually living.”
Key Research Papers
- Porges SW. Polyvagal theory: a biobehavioral journey to sociality. Compr Psychoneuroendocrinol. 2021;7:100069. — doi:10.1016/j.cpnec.2021.100069
- Breit S, Kupferberg A, Rogler G, Hasler G. Vagus nerve as modulator of the brain-gut axis in psychiatric and inflammatory disorders. Front Psychiatry. 2018. — doi:10.3389/fpsyt.2018.00044
- Hilz MJ. Transcutaneous vagus nerve stimulation — a brief introduction and overview. Auton Neurosci. 2022;243:103038. — doi:10.1016/j.autneu.2022.103038
- Koopman FA, Chavan SS, Miljko S, et al. Vagus nerve stimulation inhibits cytokine production and attenuates disease severity in rheumatoid arthritis. Proc Natl Acad Sci U S A. 2016;113(29):8284–8289. — doi:10.1073/pnas.1605635113
- Stavrakis S, Chakraborty P, Farhat K, et al. Noninvasive vagus nerve stimulation in postural tachycardia syndrome: a randomized clinical trial. JACC Clin Electrophysiol. 2024;10(2):346–355. — PubMed PMID: 37999672
- Grossman P. Fundamental challenges and likely refutations of the five basic premises of the polyvagal theory. Biol Psychol. 2023;180:108589. — PubMed PMID: 37230290
- Toussaint LL, Whipple MO, Abboud LL, Vincent A, Wahner-Roedler DL. A mind-body technique for symptoms related to fibromyalgia and chronic fatigue. Explore (NY). 2012;8(2):92–98. — PubMed PMID: 22385563
- Crawley EM, Gaunt DM, Garfield K, et al. Clinical and cost-effectiveness of the Lightning Process in addition to specialist medical care for paediatric chronic fatigue syndrome: randomised controlled trial. Arch Dis Child. 2018;103(2):155–164. — PubMed PMID: 28931531
PubMed Topic Searches
Curated PubMed topic searches — live queries that surface the newest peer-reviewed work on each topic.
Connections
- Neurology
- Postural Orthostatic Tachycardia Syndrome Overview
- Postural Orthostatic Tachycardia Syndrome Subtypes
- Medications Guide
- Compression and Exercise
- Salt and Hydration
- Tilt Table Test
- Low Dose Naltrexone for Postural Orthostatic Tachycardia Syndrome
- Postural Orthostatic Tachycardia Syndrome/Mast Cell Activation Syndrome/EDS Triad
- Mast Cell Activation Syndrome
- Small Intestinal Bacterial Overgrowth
- Myalgic Encephalomyelitis/Chronic Fatigue Syndrome
- Fibromyalgia
- Anxiety
- Gut-Brain Axis
- Arrhythmia
- Triggers and Flare Management
- Postural Orthostatic Tachycardia Syndrome Diet