Postural Orthostatic Tachycardia Syndrome (POTS) Medications Guide
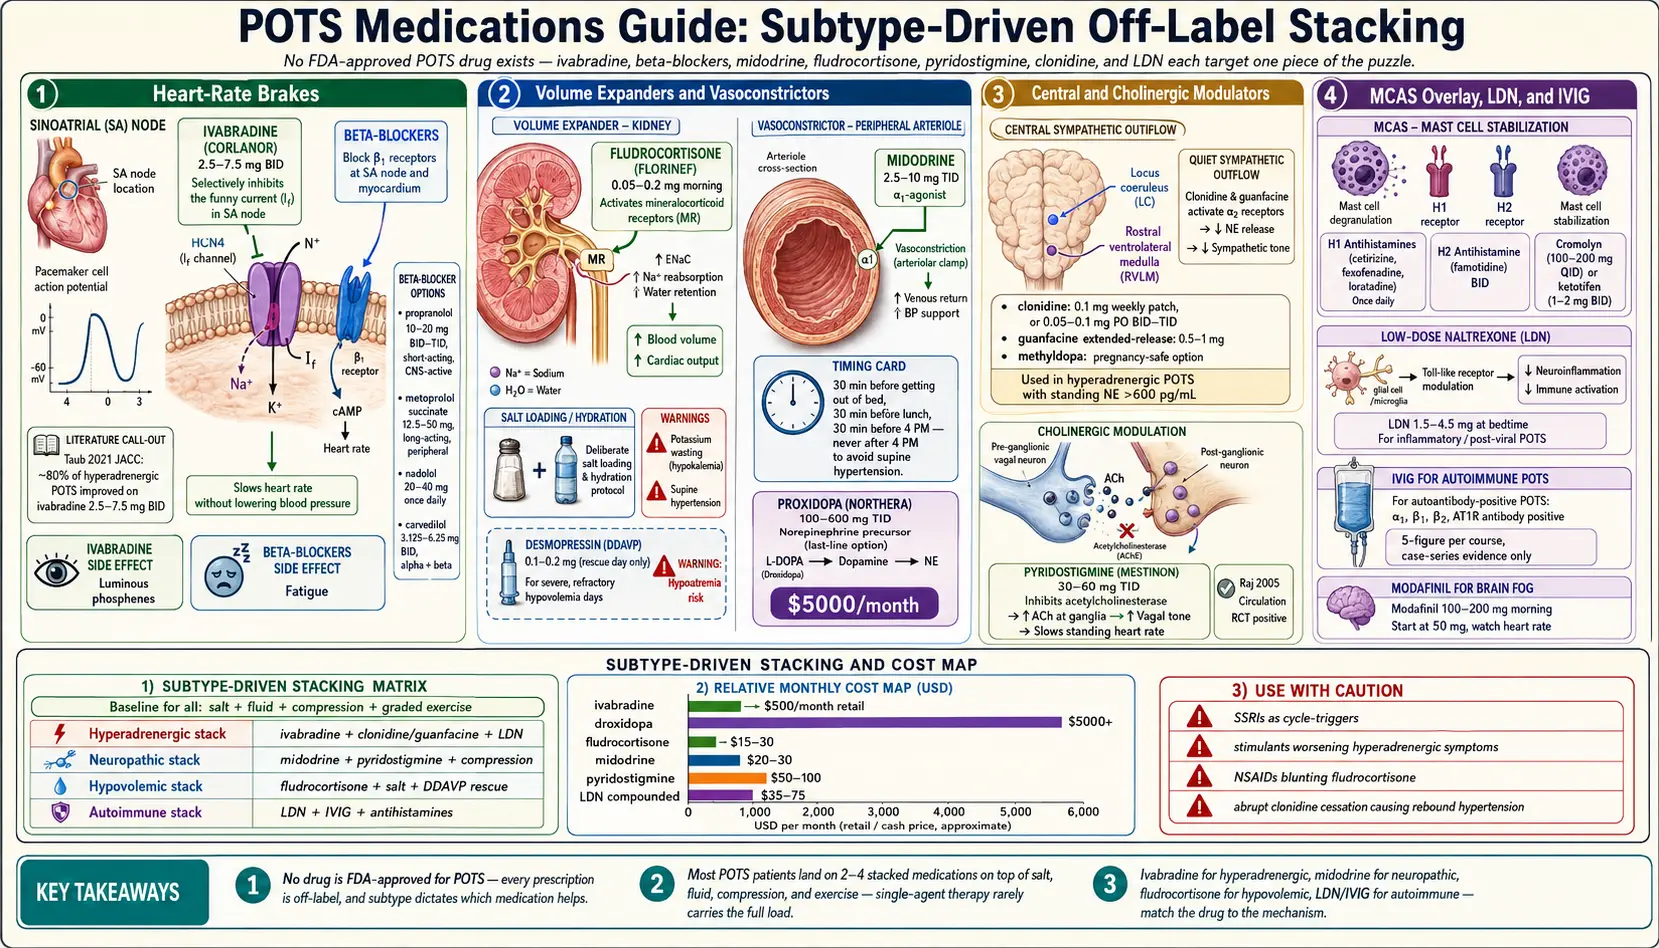
Table of Contents
- There Is No “Postural Orthostatic Tachycardia Syndrome Drug”
- Heart-Rate-Focused Meds
- Blood-Volume-Focused Meds
- Vasoconstrictor Meds
- Central-Acting Meds
- Cholinergic Meds
- Mast Cell / Allergic Overlay
- Specialty & Emerging
- Combinations Reported by Subtype
- Medicines Reported to Worsen Symptoms
- How Insurance Approval Works
- How to Know a Med Is Working
- Key Research Papers
- Connections
- Featured Videos
1. There Is No “Postural Orthostatic Tachycardia Syndrome Drug”
Most postural orthostatic tachycardia syndrome (POTS) patients eventually learn that there is no U.S. Food and Drug Administration-approved medication for postural orthostatic tachycardia syndrome. Not one. Every drug a cardiologist or neurologist prescribes for it — ivabradine, midodrine, fludrocortisone, propranolol, pyridostigmine, clonidine — is used off-label. That word matters because it shapes insurance denials, pharmacist questions, and how much guidance comes with the prescription.
The reason this field is so fragmented is that postural orthostatic tachycardia syndrome isn’t one disease. It’s a shared final pathway — standing heart rate rises ≥30 bpm — reached by at least four different underlying mechanisms. That’s why your friend got midodrine and you got ivabradine, and why both of you might be correctly treated. Subtype drives drug choice. See Subtypes for the full breakdown.
The other reality: most postural orthostatic tachycardia syndrome patients end up on 2–4 medications stacked, plus salt, fluid, compression, and exercise. A single pill rarely carries the full load. This guide is a map of tools, not a decision tree with one right answer.
The research behind these tools is thin. A 2025 systematic review of 21 randomized trials (750 patients, 2000–2023) found that many small trials have tested propranolol, midodrine, pyridostigmine and ivabradine, as well as desmopressin, melatonin, atomoxetine, modafinil, sertraline and intravenous immunoglobulin, but none large enough to settle which drugs should come first. The review describes the 2015 Heart Rhythm Society and 2020 Canadian Cardiovascular Society guidelines as resting on weak evidence and clinical expertise, and the authors of a 2026 trial likewise describe the condition as lacking approved drug therapies.
2. Heart-Rate-Focused Meds
These drugs target the tachycardia itself — the fast standing heart rate that defines postural orthostatic tachycardia syndrome. They don’t fix blood volume or vasoconstriction; they just put the brakes on the pulse.
Ivabradine
Ivabradine is widely used for hyperadrenergic postural orthostatic tachycardia syndrome and, in specialist practice, increasingly across subtypes when insurance allows. It inhibits the funny (If) current in the sinoatrial node, which slows heart rate without lowering blood pressure and without the fatigue hit of beta-blockers. For patients whose standing blood pressure (BP) is already borderline low, that specificity is the difference between tolerating the drug and being crushed by it.
Typical dose: 2.5–7.5 mg twice daily. It is commonly started at 2.5 mg twice daily and raised every 2 weeks according to pulse response. The Taub 2021 randomized trial (Journal of the American College of Cardiology) was a placebo-controlled crossover study in 22 people with hyperadrenergic postural orthostatic tachycardia syndrome (95.5% women), each taking ivabradine for one month and placebo for one month. Heart rate fell significantly on ivabradine compared with placebo, two quality-of-life scores (physical functioning and social functioning) improved, and no significant slow pulse or low blood pressure was reported.
Cost: Ivabradine was once sold only under its brand name; DailyMed, the U.S. National Library of Medicine’s drug-label database, now lists generic ivabradine tablets from several manufacturers. Most commercial insurers cover it when a postural orthostatic tachycardia syndrome or inappropriate sinus tachycardia diagnosis is documented, often only after a prior authorization the first time.
Side effects: The signature one is luminous phosphenes — brief visual flashes or halos, especially when looking at bright lights. They usually fade in a few weeks. Too high a dose slows the pulse too much (bradycardia); practitioners describe lowering the dose when the resting pulse falls below 50.
What the FDA label says: it lists these reasons not to use ivabradine (contraindications): acute decompensated heart failure, clinically significant low blood pressure, sick sinus syndrome, sinoatrial block or third-degree heart block without a working pacemaker, clinically significant bradycardia, severe liver impairment, pacemaker dependence, and use with strong cytochrome P450 3A4 (CYP3A4) inhibitors, drugs that block the liver enzyme that clears it. Atrial fibrillation is a warning rather than a contraindication: the label states that ivabradine increases the risk of atrial fibrillation (5.0% versus 3.9% per patient-year on placebo in the SHIFT heart-failure trial) and that it is stopped if atrial fibrillation develops. The label also warns of harm to an unborn baby (fetal toxicity): in pregnant rats it caused embryo-fetal toxicity and heart malformations, and the label advises women who can become pregnant to use effective contraception while taking it.
Beta-Blockers
Before ivabradine arrived, beta-blockers were the default for postural orthostatic tachycardia syndrome, and they’re still the cheapest, most widely available option. The trade-off is that they lower blood pressure along with heart rate, and they sap energy in some patients — a real problem when fatigue is already the dominant symptom.
Propranolol 10–20 mg BID-TID is the most commonly prescribed. Short-acting, crosses the blood-brain barrier, which helps if anxiety overlaps the postural orthostatic tachycardia syndrome picture and hurts if fatigue already dominates. Low doses (10 mg) are often enough; not everyone needs 40 mg three times daily.
Metoprolol succinate 12.5–50 mg daily is long-acting and mostly stays out of the brain — a gentler option for patients who get foggy on propranolol. The succinate (extended-release) form gives smoother coverage than tartrate.
Nadolol 20–40 mg daily is very long-acting and non-selective, which makes it useful for patients who wake up at 3 AM in a tachycardia surge. One dose covers the full 24-hour cycle.
Carvedilol 3.125–6.25 mg BID combines alpha and beta blockade. Good for the hyperadrenergic patient with wildly swinging blood pressures — the alpha effect damps the pressor spikes that pure beta-blockers can’t touch.
Side effects across the class: fatigue (huge issue in postural orthostatic tachycardia syndrome — this is the main reason patients migrate to ivabradine), bronchospasm in asthmatics, worsening of depression, reduced exercise tolerance, cold hands and feet. Beta-blockers are tapered over about a week rather than stopped abruptly.
Ivabradine and Propranolol Compared (2026 Trial)
A 2026 randomized crossover trial (Uppal and colleagues, JACC: Advances) gave 28 women with postural orthostatic tachycardia syndrome four weeks each of ivabradine, propranolol and placebo, ending each phase with a 10-minute head-up tilt test. Peak standing heart rate was 99 beats per minute on ivabradine and 100 on propranolol, versus 118 on placebo; the two drugs did not differ from each other on heart rate. Ivabradine raised systolic blood pressure during tilt more than propranolol did (4.9 versus 1.9 mm Hg). Of 22 recorded preferences, every participant preferred one of the drugs over placebo, split 59% ivabradine and 41% propranolol, a difference that was not statistically significant. The authors note that the heart-rate effect was consistent while effects on symptoms and quality of life varied from person to person.
3. Blood-Volume-Focused Meds
Many postural orthostatic tachycardia syndrome patients are chronically hypovolemic — measurably low circulating plasma volume, often 10–30% below normal. Raising volume raises preload and drops the compensatory tachycardia. Salt and fluid are the foundation; these drugs are the pharmacologic amplifier.
Fludrocortisone
Fludrocortisone is a synthetic mineralocorticoid. It tells the kidneys to retain sodium, which pulls water with it and expands plasma volume. Works best when paired with deliberate salt loading (see Salt & Hydration Protocol) — no sodium in, nothing for the drug to act on.
Typical dose: 0.05–0.2 mg every morning. It is usually started at 0.05 mg and adjusted by symptoms and blood tests. Doses above 0.2 mg rarely help more and rapidly increase side effects.
Cost: Cheap generic, about $15–30/month.
Best for: Hypovolemic subtype and low-renin patients (some postural orthostatic tachycardia syndrome specialists draw a renin/aldosterone ratio before starting to confirm).
Side effects: Potassium loss is the big one — practitioners describe adding potassium-rich foods or a low-dose potassium tablet and checking a basic metabolic panel (blood salts and kidney function) at 2 weeks, then every 3 months. Edema, weight gain, supine hypertension, and headache are common. Long-term use can suppress the hypothalamic-pituitary-adrenal (HPA) axis, which is why it is tapered rather than stopped abruptly.
Desmopressin
Desmopressin is a synthetic vasopressin analog. It tells the kidneys to hold water, rapidly expanding volume. It is used as a rescue medication, not a daily one — occasional doses for especially demanding days (long flights, weddings, heat waves).
Typical dose: 0.1–0.2 mg orally as needed, once daily maximum.
Daily use carries a real hazard. Chronic use can produce dangerous hyponatremia (low blood sodium) — sodium levels low enough to cause seizures. Specialists treat use of desmopressin more than 2–3 times a week as a sign the regimen needs review.
4. Vasoconstrictor Meds
In the neuropathic postural orthostatic tachycardia syndrome phenotype, standing causes too much blood to pool in the lower body because small peripheral vessels don’t constrict properly. Vasoconstrictor drugs put the squeeze back on those vessels, pushing blood back toward the heart.
Midodrine
Midodrine is an alpha-1 adrenergic agonist. It binds directly to the peripheral vasculature and makes small arteries clamp down. It’s the workhorse for neuropathic postural orthostatic tachycardia syndrome — cheap, effective, and fast-acting (onset in 30 minutes, duration 3–4 hours).
Typical dose: 2.5–10 mg three times daily. It is usually started at 2.5 mg three times daily and raised gradually.
Timing matters because midodrine works for a short window. A commonly described schedule:
- 30 minutes before getting out of bed (some people set an alarm, take it, and lie back down until it works)
- 30 minutes before lunch
- 30 minutes before 4 PM
- Last dose by 4 PM — later doses raise the risk of supine hypertension (high blood pressure when lying down) at night
Cost: Generic, roughly $20–30/month.
Side effects: The famous one is scalp tingling or goosebumps — harmless, just the alpha receptors on scalp and skin doing their job. Supine hypertension is the real risk, which is why a dose is not followed by lying flat for the night. Urinary retention can occur in older men with prostatic hypertrophy.
Droxidopa
Droxidopa is a synthetic norepinephrine precursor that the body converts into NE. It’s U.S. Food and Drug Administration-approved for neurogenic orthostatic hypotension (Parkinson’s, multiple system atrophy, pure autonomic failure) — not postural orthostatic tachycardia syndrome. In pure postural orthostatic tachycardia syndrome it’s reserved for refractory cases where midodrine has failed and volume expansion isn’t enough.
Typical dose: 100–600 mg three times daily.
Cost: High. Retail runs $5,000+/month. Insurance approval for postural orthostatic tachycardia syndrome (versus neurogenic orthostatic hypotension) is often difficult. The manufacturer runs a patient assistance program.
5. Central-Acting Meds
Hyperadrenergic postural orthostatic tachycardia syndrome is driven by too much sympathetic output from the brain — standing norepinephrine levels often exceed 600 pg/mL. Central alpha-2 agonists quiet the sympathetic outflow upstream, before it reaches the heart and vessels.
Clonidine
Clonidine is an alpha-2 agonist that acts in the brainstem to reduce norepinephrine release. It is commonly added for hyperadrenergic postural orthostatic tachycardia syndrome when ivabradine alone isn’t enough.
Typical dose: 0.1 mg weekly patch (often preferred for its smooth 7-day levels with no peak-trough swings), or 0.05–0.1 mg orally BID-TID.
Because the oral form sedates, it is often taken at bedtime, where it can knock out the middle-of-the-night adrenergic surges that wake hyperadrenergic patients drenched in sweat.
Side effects: Dry mouth (very common), drowsiness, orthostatic dizziness if dosed too aggressively, and — critically — rebound hypertension if stopped abruptly, which is why clonidine is tapered over a week or more.
Guanfacine
Guanfacine is clonidine’s better-behaved cousin — same mechanism, less sedation, longer half-life. Patients who can’t tolerate clonidine’s drowsiness often do well on guanfacine.
Typical dose: 0.5–1 mg daily, often as the extended-release form.
Methyldopa
Methyldopa is an older centrally acting agent, now mostly used because it’s pregnancy-safe. If a pregnant postural orthostatic tachycardia syndrome patient needs symptom control, methyldopa is one of the few options with a long track record.
6. Cholinergic Meds
Pyridostigmine
Pyridostigmine is an acetylcholinesterase inhibitor — it blocks the enzyme that breaks down acetylcholine, leaving more ACh available at neuromuscular junctions and (crucially for postural orthostatic tachycardia syndrome) at autonomic ganglia. The net effect is enhanced vagal tone, which slows heart rate selectively during standing without lowering it to dangerous levels at rest.
Typical dose: 30–60 mg three times daily. It is usually started at 30 mg once or twice daily to gauge gastrointestinal (GI) tolerance, then raised.
Evidence: The Raj 2005 randomized crossover trial (Circulation) gave 17 people with postural orthostatic tachycardia syndrome a single 30 mg dose of pyridostigmine on one morning and a placebo on another. Two hours after the dose, standing heart rate was 100 beats per minute on pyridostigmine versus 111 on placebo; symptom scores over the following 4 hours fell more than with placebo, and blood pressure did not change significantly. Because it tested one dose over 4 hours, it shows a short-term effect, not months of benefit — but it makes pyridostigmine one of the few postural orthostatic tachycardia syndrome medicines with a positive randomized controlled trial (RCT).
Side effects: Cholinergic as expected — abdominal cramping, diarrhea, increased salivation, occasional muscle twitching. Starting low and raising slowly limits gastrointestinal effects. Specialists describe it as often working even when adrenergic-targeted drugs have failed.
7. Mast Cell / Allergic Overlay
An underappreciated reality: many postural orthostatic tachycardia syndrome patients also have mast cell activation syndrome (MCAS). If flushing, itching, food reactions, or unexplained anaphylaxis-like episodes sit alongside the orthostatic symptoms, treating the mast cells often improves the postural orthostatic tachycardia syndrome — sometimes dramatically.
The typical stack is H1 blocker (cetirizine, fexofenadine, or loratadine daily) + H2 blocker (famotidine BID) + a mast cell stabilizer (cromolyn or ketotifen). Low-dose naltrexone fits here too. For the full workup and treatment map see postural orthostatic tachycardia syndrome-MCAS-EDS Triad and mast cell activation syndrome.
8. Specialty & Emerging
Low-Dose Naltrexone
Low dose naltrexone (LDN) is used at 1.5–4.5 mg nightly for inflammatory and autoimmune-leaning postural orthostatic tachycardia syndrome phenotypes — especially post-viral cases where cytokine dysregulation appears central. Works on both neuroinflammation and mast cells. Full detail at Low-Dose Naltrexone for postural orthostatic tachycardia syndrome.
Intravenous Immunoglobulin (IVIG)
IVIG is used for autoantibody-positive postural orthostatic tachycardia syndrome — patients with demonstrated adrenergic receptor autoantibodies (alpha-1, beta-1, beta-2) or angiotensin II type 1 receptor (AT1R) antibodies. Dramatic, life-changing responses have been described in uncontrolled case series. Infusion-center logistics and cost (five figures per course) make this a last-line option, not a first move.
The first randomized controlled trial, iSTAND (Vernino and colleagues, 2024), treated 30 people with presumed autoimmune postural orthostatic tachycardia syndrome with eight infusions over 12 weeks: 16 received IVIG and 14 received albumin, a comparison infusion that also adds fluid volume. Symptom scores (COMPASS-31) improved in both groups and did not differ between them; 46.7% responded to IVIG versus 38.5% to albumin, a difference that was not statistically significant. Side effects were common but usually mild and similar in both groups. The authors suggest the improvement in both groups may partly reflect the volume effect of any infusion.
Modafinil
Modafinil 100–200 mg in the morning gets used off-label for postural orthostatic tachycardia syndrome brain fog. Evidence is mixed — some patients love it, others find it amplifies tachycardia and jitter. Where it is tried, starting at 50 mg with heart-rate checks is described.
9. Combinations Reported by Subtype
Real-world postural orthostatic tachycardia syndrome treatment is layered. The table shows combinations specialists describe using for the four main subtypes — reported practice, not tested regimens — each one assuming baseline salt, fluid, compression, and graded exercise are already in place. The 2025 review of 21 randomized trials found that the trials so far have been small and that large trials are still needed to know whether beta-blockers, midodrine and pyridostigmine should be used first.
| Subtype | Combination Described | Notes |
|---|---|---|
| Hyperadrenergic | Ivabradine + clonidine patch + low dose naltrexone | High-dose salt can worsen blood pressure spikes. Supine hypertension (HTN) is watched for. |
| Neuropathic | Midodrine + fludrocortisone + pyridostigmine + compression + salt | The classic “pool in the legs” phenotype. Vasoconstriction + volume is the goal. |
| Hypovolemic | Fludrocortisone + high-dose salt/fluid ± midodrine | Renin/aldosterone is often checked; many of these patients have low renin. |
| Mixed / post-viral | Ivabradine or low-dose propranolol first → midodrine added if needed → mast cell activation syndrome/autoimmune features addressed | Treatment targets the triggering infection and immune activation, not just the tachycardia. |
These are examples of reported practice, not prescriptions. Specialists describe settling on a combination through repeated tilt-table or NASA lean tests, a careful symptom diary, and — importantly — a postural orthostatic tachycardia syndrome-literate clinician willing to iterate.
10. Medicines Reported to Worsen Symptoms
Some commonly prescribed medicines can make postural orthostatic tachycardia syndrome worse.
- Selective serotonin reuptake inhibitors (SSRIs). They help some patients (especially with comorbid anxiety) and wreck others — particularly the hyperadrenergic subtype, where pushing serotonin can amplify sympathetic tone. Sertraline 25–50 mg is the most commonly tried, usually started low with heart-rate checks.
- Stimulants (mixed amphetamine salts, lisdexamfetamine, methylphenidate). Frequently prescribed for “brain fog” and frequently reported to backfire, because they raise heart rate and blood pressure directly. Where they are used, it is usually for brain fog that has resisted everything else, at the bottom of the dose range.
- Tricyclics (amitriptyline, nortriptyline). Heavy anticholinergic burden, orthostatic hypotension, sedation. Rarely the right choice for a postural orthostatic tachycardia syndrome patient.
- Proton-pump inhibitors. Chronic acid suppression feeds small intestinal bacterial overgrowth (SIBO), and small intestinal bacterial overgrowth commonly worsens autonomic symptoms. Shorter courses limit this effect.
- Opioids. Cause constipation, which slows gut transit, which feeds small intestinal bacterial overgrowth, which feeds autonomic dysfunction. The cascade is real.
11. How Insurance Approval Works
Most postural orthostatic tachycardia syndrome meds are cheap generics — midodrine, fludrocortisone, pyridostigmine, propranolol, clonidine, metoprolol. The two that most often meet insurance friction are ivabradine (generic tablets now exist alongside the brand) and droxidopa ($5,000+/month). These points bear on approval:
- Postural orthostatic tachycardia syndrome has its own ICD-10 code: G90.A. “Postural orthostatic tachycardia syndrome” got its own code in 2022. Before that, claims were coded under generic autonomic dysfunction (G90.9) or orthostatic hypotension (I95.1) — both of which insurers flag as vague. G90.A is specific enough that prior authorization reviewers can identify the diagnosis.
- Tilt-table or 10-minute NASA lean test results give objective hemodynamic documentation, which carries more weight than any narrative. See Tilt Table & NASA Lean Test.
- Guideline statements. The 2015 Heart Rhythm Society expert consensus statement and the 2020 Canadian Cardiovascular Society guidelines describe the off-label treatments used in postural orthostatic tachycardia syndrome; a 2025 systematic review of 21 randomized trials notes that these guidelines rest on weak evidence and clinical expertise.
- Manufacturer copay and assistance programs exist for brand-name ivabradine and droxidopa; neither is widely advertised.
- Specialist offices. The patient organisation Dysautonomia International keeps a list of clinicians who treat postural orthostatic tachycardia syndrome. Offices that see many such patients handle prior authorizations routinely; generalist offices often have less experience with them.
12. How to Know a Med Is Working
Feelings alone are a poor guide. Postural orthostatic tachycardia syndrome symptoms fluctuate day to day with weather, hormones, hydration, and sleep, so a “good week” doesn’t mean the drug is working and a “bad day” doesn’t mean it isn’t. Objective markers used to judge a medicine:
- Drop in standing heart rate by at least 15 bpm on repeat NASA lean test
- Drop in symptom diary scores across 2–4 weeks (brain fog, presyncope, fatigue, palpitations)
- Ability to complete a 10-minute NASA lean test without crashing
- Functional capacity gain — standing longer in the shower, tolerating errands, returning to part-time work
Clinicians commonly give each new medicine 4–6 weeks at the target dose before judging it, because shorter trials mistake noise for signal, and change one medicine at a time so that the effect of each can be told apart.
Key Research Papers
- Taub PR, et al. Randomized trial of ivabradine in patients with hyperadrenergic postural orthostatic tachycardia syndrome. JACC. 2021;77(7):861-871. — doi:10.1016/j.jacc.2020.12.029
- Raj SR, et al. Acetylcholinesterase inhibition improves tachycardia in postural tachycardia syndrome. Circulation. 2005;111(21):2734-2740. — doi:10.1161/circulationaha.104.497594
- Raj SR. Postural tachycardia syndrome (POTS). Circulation. 2013;127(23):2336-2342. — doi:10.1161/CIRCULATIONAHA.112.144501
- Sheldon RS, et al. 2015 Heart Rhythm Society expert consensus statement on the diagnosis and treatment of POTS. Heart Rhythm. 2015. — doi:10.1016/j.hrthm.2015.03.029
- Vernino S, Hopkins S, Bryarly M, Hernandez RS, Salter A. Randomized controlled trial of intravenous immunoglobulin for autoimmune postural orthostatic tachycardia syndrome (iSTAND). Clinical Autonomic Research. 2024;34(1):153-163. — PubMed PMID: 38311655
- Kwok CS, Lee S, Hall M, Qureshi AI, Lip GYH, Loke YK, Raj SR, Holroyd E. The evidence for treatments for postural orthostatic tachycardia syndrome: a systematic review of randomized trials. Trends in Cardiovascular Medicine. 2025;35(8):517-527. — PubMed PMID: 40653179
- Uppal J, Deol P, Giri P, Singh A, Hamzeh R, Qi J, Chew DS, Runte M, Sheldon RS, Raj SR. A randomized crossover trial of ivabradine, propranolol, and placebo in postural orthostatic tachycardia syndrome: a detailed description. JACC: Advances. 2026;5(6 Pt 2):102795. — PubMed PMID: 42132710
- Ivabradine tablets and oral solution: full prescribing information (brand-name label, revised November 2025). DailyMed, U.S. National Library of Medicine. — DailyMed label
PubMed Topic Searches
Curated PubMed topic searches — each link opens a live query so you always see the most recent literature.
- PubMed: Ivabradine for POTS
- PubMed: Midodrine for postural tachycardia
- PubMed: Fludrocortisone for POTS
- PubMed: Pyridostigmine for POTS
- PubMed: Propranolol for postural tachycardia
- PubMed: Clonidine for hyperadrenergic POTS
- PubMed: Droxidopa for orthostatic syndromes
- PubMed: POTS autoantibodies and IVIG
Connections
- Neurology
- Postural Orthostatic Tachycardia Syndrome Overview
- Postural Orthostatic Tachycardia Syndrome Subtypes
- Low Dose Naltrexone for Postural Orthostatic Tachycardia Syndrome
- Tilt Table Test
- Salt and Hydration Protocol
- Postural Orthostatic Tachycardia Syndrome/Mast Cell Activation Syndrome/EDS Triad
- Compression and Exercise Program
- Vagus Nerve and Autonomic Retraining
- Mast Cell Activation Syndrome
- Small Intestinal Bacterial Overgrowth
- Arrhythmia
- Low-Dose Naltrexone (Remedy)
- Thyroid Disorders
- Fibromyalgia
- Myalgic Encephalomyelitis/Chronic Fatigue Syndrome
- Fatigue
- Lightheadedness
- Orthostatic Intolerance in Myalgic Encephalomyelitis/Chronic Fatigue Syndrome (ME/CFS)