⚠ Evidence warning: Clinical trials or other evidence do not support the claim that low-dose naltrexone retrains the neuroimmune system and gives about one in three people with fibromyalgia meaningful relief. This page keeps it as a report of what people, websites or other media say.
Low-Dose Naltrexone for Fibromyalgia
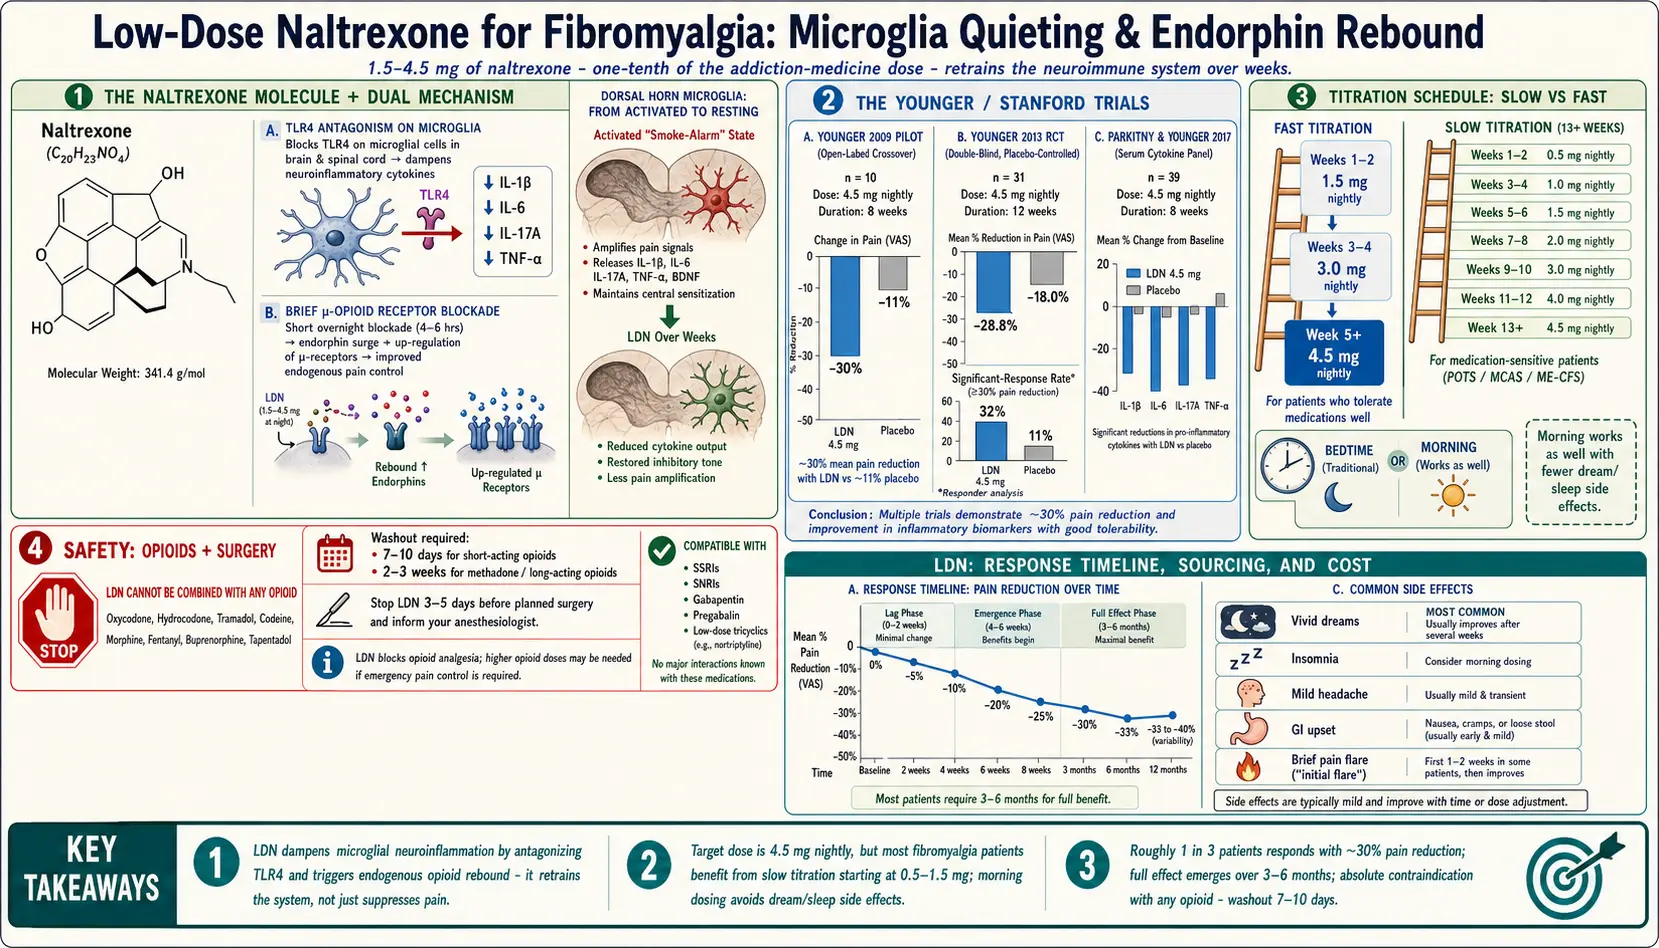
Table of Contents
- What Low-Dose Naltrexone Is
- How Low Dose Naltrexone Works in Fibromyalgia
- The Younger / Stanford Trials
- Larger Trials Since 2023
- Typical Dosing — Where to Start and Where to Land
- Slow vs Fast Titration Schedules
- Compounding Pharmacies, Cost, and Insurance
- Side Effects — What to Expect
- Drug Interactions — Opioids and Surgery
- Morning vs Bedtime — The Timing Debate
- What “Working” Looks Like
- When Low Dose Naltrexone Is Stopped
- Practical Points for Starting
- Key Research Papers
- Connections
- Featured Videos
What Low-Dose Naltrexone Is
Naltrexone is an old drug: the U.S. Food and Drug Administration approved the 50 mg tablet in 1984 for opioid dependence and added alcohol dependence in 1994. At that dose it is a powerful opioid-receptor blocker — it keeps heroin, oxycodone, and the body's own endorphins from docking onto nerve cells for 24 hours at a time.
Low-dose naltrexone is the same molecule given at roughly one-tenth the dose — typically 1.5 to 4.5 mg, taken once a day. At this dose the drug behaves completely differently. Instead of paralyzing the opioid system, it produces a brief blockade lasting four to six hours, then washes out. During that window the body senses low endorphin signaling and ramps up its own production. When the drug is gone, endorphin levels rebound above baseline.
Low dose naltrexone (LDN) is an off-label prescription in the United States. No drug company owns it (the patent expired decades ago), so no sponsor has paid for the expensive Phase III trials needed for a fibromyalgia label. Some physicians still treat low dose naltrexone as a “fringe” therapy. The trial evidence is mixed: small early crossover trials were positive, while larger placebo-controlled trials published since 2023 did not find a clinically meaningful benefit (see Larger Trials Since 2023).
How Low Dose Naltrexone Works in Fibromyalgia
Fibromyalgia is, at its core, a disease of amplified pain signaling in the central nervous system (see central sensitization). The volume knob on pain is turned up, and a big part of that volume is controlled by microglia — the immune cells of the brain and spinal cord.
When microglia are chronically activated, they pump out inflammatory cytokines (interleukin-6 (IL-6), tumor necrosis factor-alpha, interleukin-1 beta (IL-1β)) and pro-inflammatory chemicals that sensitize the nerves around them. Imagine a smoke alarm wired to an amplifier: every tiny input becomes a siren. This is why a light touch, a cool breeze, or a sound can register as pain in fibromyalgia.
Low dose naltrexone appears to calm that alarm through two distinct actions:
- TLR4 antagonism on microglia. Naltrexone (in its non-opioid stereoisomer and likely the regular one too) blocks Toll-like receptor 4 (TLR4) on microglial cells. TLR4 is a major “danger signal” receptor. Blocking it tells microglia to stand down and stop pumping out inflammatory cytokines. This is thought to be the main pain-quieting mechanism.
- Transient opioid blockade → endorphin rebound. The short, partial opioid blockade briefly reduces activity at mu-opioid receptors. The brain responds by upregulating both endorphin production and opioid-receptor sensitivity. Over weeks, the body's own pain-control system becomes more responsive.
In short, low dose naltrexone is not a painkiller the way ibuprofen or an opioid is. It does not suppress pain while you take it. It retrains the neuroimmune system over weeks to generate less pain in the first place.
The Younger / Stanford Trials
The modern low dose naltrexone story in fibromyalgia was largely built by Jarred Younger, PhD, first at Stanford and now at the University of Alabama at Birmingham. Two small but careful studies put low dose naltrexone on the map:
Younger 2009 (pilot, single-blind crossover). Ten women with fibromyalgia who were not taking opioids had 2 weeks of placebo followed by 8 weeks of low dose naltrexone 4.5 mg nightly, without being told when the switch happened (single-blind). Overall fibromyalgia symptom scores dropped by about 30% more than on placebo, and average pain, fatigue and stress also improved. In laboratory tests, pressure and heat pain thresholds improved. A higher baseline erythrocyte sedimentation rate (a blood marker of inflammation) predicted over 80% of the differences in how people responded. The paper is small but carefully done and was the first controlled hint that low dose naltrexone helps fibromyalgia specifically.
Younger 2013 (randomized, double-blind, placebo-controlled crossover). Thirty-one women completed twelve weeks of low dose naltrexone versus placebo. Low dose naltrexone reduced daily pain by roughly 28.8%, compared with 18.0% for placebo (P = 0.016). Roughly 32% of low dose naltrexone-treated participants met the threshold for a significant response (a significant drop in pain plus a significant drop in either fatigue or sleep problems), versus 11% on placebo. Mood and general satisfaction with life improved; fatigue and sleep did not. Side effects were mild. The authors wrote that parallel-group randomized trials were still needed to settle whether the drug works.
Parkitny & Younger 2017. A follow-up 10-week single-blind crossover study in eight women measured blood (plasma) cytokines before and after eight weeks of low dose naltrexone and found reductions in interleukin-1β, interleukin-6, IL-17A, tumor necrosis factor-alpha, and others. Pain fell 15% and overall symptoms 18%. This gave the first biological fingerprint to back up the clinical results: lower inflammatory signaling alongside the symptom relief. The cytokines were not compared with a placebo group, so the study cannot rule out a placebo response.
These early trials were small by pharma standards — tens of patients, not thousands. No drug company has run a Phase III trial for a fibromyalgia label, but larger randomized placebo-controlled trials have since been done in Denmark (2024, 99 women) and Spain (2026, 98 women, 12 months), after a 58-person Danish crossover trial in 2023; none found a clinically relevant benefit over placebo (see Larger Trials Since 2023). A 2024 meta-analysis that pooled 4 randomized trials (222 patients) reported a small reduction in pain scores (mean difference −0.86 points). Alongside the trials are open-label case series and patient reports; users and prescribers describe a consistent signal: roughly one in three fibromyalgia patients gets meaningful relief, the drug is cheap, and the side-effect profile is mild.
Larger Trials Since 2023
Three randomized, double-blind, placebo-controlled trials published since 2023 tested low dose naltrexone in fibromyalgia:
- Denmark, 2023 (crossover). 58 people with fibromyalgia took 4.5 mg or placebo once a day for about three weeks each, with a washout in between. The differences in fibromyalgia impact scores and in summed pain ratings were small and not significant (P = 0.3 and P = 0.4); the authors found no clinically relevant pain-relieving effect.
- Denmark, 2024. 99 women aged 18–64 took 6 mg or placebo for 12 weeks. Pain fell 1.3 points on the drug and 0.9 points on placebo (on an 11-point scale); the 0.34-point difference was not significant (p = 0.27). Side effects were about as common on the drug (84%) as on placebo (86%). The authors reported that low dose naltrexone might improve the memory problems linked to fibromyalgia and suggested future trials look at this.
- Spain, 2026 (INNOVA study). 98 women took 4.5 mg or placebo, added to their usual treatment, and were followed for 12 months. At 3 months pain had fallen 0.33 points on the drug and 0.64 points on placebo. The drug was well tolerated — side effects, mostly mild and short-lived, were reported by 68.8% on the drug and 72% on placebo, with no treatment-related serious events — but it showed no clinically meaningful benefit over placebo at short- or long-term follow-up.
Typical Dosing — Where to Start and Where to Land
The standard target dose in fibromyalgia is 4.5 mg once daily. Almost every published trial and almost every experienced low dose naltrexone prescriber aims there. Some patients do better at slightly lower (3.0 mg) or slightly higher (up to 6 mg) doses, but 4.5 mg is the anchor.
Prescribers usually do not start at 4.5 mg. Practitioners describe jumping straight to the target as the single biggest reason patients quit low dose naltrexone in the first two weeks — vivid dreams, insomnia, and headaches are reported to be far worse without titration.
A typical starting dose is 0.5 mg to 1.5 mg. From there the dose climbs over several weeks toward 4.5 mg, pausing or dropping back if side effects flare.
Low dose naltrexone comes as a capsule, a sublingual tablet, or a liquid from a compounding pharmacy. The liquid is the most flexible — it can be measured in 0.5 mg increments — and is popular with sensitive patients. Capsules are most common and perfectly fine for most people.
Slow vs Fast Titration Schedules
Two mainstream schedules exist. Neither is “right” the choice depends on how sensitive you are to new medications.
Fast titration (for most people).
- Weeks 1–2: 1.5 mg nightly.
- Weeks 3–4: 3.0 mg nightly.
- Week 5 onward: 4.5 mg nightly.
Slow titration (for medication-sensitive patients, which includes many fibromyalgia patients and anyone with coexisting postural orthostatic tachycardia syndrome (POTS), mast cell activation syndrome (MCAS), or myalgic encephalomyelitis/chronic fatigue syndrome (ME/CFS)).
- Weeks 1–2: 0.5 mg nightly.
- Weeks 3–4: 1.0 mg nightly.
- Weeks 5–6: 1.5 mg nightly.
- Weeks 7–8: 2.0 mg nightly.
- Weeks 9–10: 3.0 mg nightly.
- Weeks 11–12: 4.0 mg nightly.
- Week 13 onward: 4.5 mg nightly.
In these schedules, a dose increase that causes a flare — worse pain, worse sleep, new headaches — is followed by a drop back to the previous dose for another two weeks before trying again. There is no prize for getting to 4.5 mg quickly. The target matters; the timeline does not.
Compounding Pharmacies, Cost, and Insurance
Low-dose naltrexone is not manufactured commercially. The commercial oral naltrexone tablet is 50 mg, which is impractical to break into 4.5 mg pieces (a 380 mg long-acting injection given every 4 weeks also exists). Instead, the prescription goes to a compounding pharmacy, which measures out a tiny amount of pure naltrexone and mixes it into a capsule base (typically microcrystalline cellulose; many prescribers and patients request a filler without lactose or calcium carbonate, which they describe as blunting absorption).
Compounding pharmacies in several U.S. states make low dose naltrexone, and several ship nationwide. Typical cost is $35–$70 per month out of pocket.
Insurance rarely covers low dose naltrexone. Because it is off-label and compounded, most U.S. insurance plans deny it outright. A few plans reimburse a percentage under “compounded medications” riders. Health savings account (HSA) and flexible spending account (FSA) funds can usually be used for it with a prescription.
Many compounding pharmacies offer a cash-pay discount for a three-month supply, and many have a preferred capsule filler for sensitive patients — microcrystalline cellulose and sucrose are usually described as the safest choices.
Side Effects — What to Expect
Compared with most pain medications, low dose naltrexone is remarkably well tolerated. Most side effects appear in the first two to four weeks and fade as the body adapts.
- Vivid dreams. By far the most common. Dreams become louder, longer, stranger — sometimes interesting, sometimes unpleasant. Usually fades within two to four weeks. When dreams are disturbing, prescribers commonly move the dose from bedtime to morning (see timing debate).
- Insomnia or fragmented sleep. Trouble falling or staying asleep during the first week or two of each dose increase. Usually transient. When it persists, morning dosing is the usual change.
- Headache. Usually mild, front-of-head, resolves with hydration and a slower titration.
- Gastrointestinal (GI) upset. Mild nausea, loose stools, or bloating. Users report that taking the dose with a small amount of food (a cracker or a spoonful of yogurt) helps.
- Temporary pain or fatigue flare. Some fibromyalgia patients feel worse for the first one to two weeks before improving. Protocols describe continuing through a tolerable flare and dropping back one dose step when it is severe.
Serious adverse events are rare. Low dose naltrexone does not cause weight gain, sexual dysfunction, dependence, tolerance, or withdrawal. Long-term use (five-plus years) has not produced a signal for organ toxicity in the published cohorts.
Pooled trial data. A 2024 meta-analysis of 4 randomized trials (222 patients) found vivid dreams and nausea more common on low dose naltrexone than on placebo, with no difference from placebo in serious adverse events, headache, diarrhea or dizziness.
Drug Interactions — Opioids and Surgery
This is the most important safety section in the article.
Low dose naltrexone and opioids do not mix. Someone taking any opioid medication — oxycodone, hydrocodone, tramadol, codeine, morphine, fentanyl, buprenorphine, tapentadol — cannot start low dose naltrexone safely. Naltrexone will displace the opioid from its receptors and can trigger an abrupt, severe withdrawal reaction. This includes over-the-counter cough syrups containing codeine and some diarrhea medicines (loperamide in high doses, diphenoxylate).
For someone on an opioid who wants to try low dose naltrexone, the opioid is tapered off first, under supervision of the prescriber who started it. The 50 mg naltrexone tablet label states a minimum opioid-free period of 7 to 10 days, including opioid-containing medicines, before starting naltrexone, and says people switching from buprenorphine or methadone may be vulnerable to withdrawal for as long as two weeks; the injectable naltrexone label adds that the withdrawal may be severe enough to require hospitalization. A typical gap used in practice between the last opioid dose and the first low dose naltrexone dose is 7–10 days for short-acting opioids and 2–3 weeks for methadone or long-acting formulations, set case by case by the prescriber.
Surgery planning. Because low dose naltrexone blocks opioid receptors for several hours after each dose, surgical anesthesiologists cannot rely on normal amounts of opioid pain medication during or after an operation. Common practice among prescribers is to stop low dose naltrexone at least 3–5 days before a planned surgery and to make sure the anesthesiologist knows it was being taken. After surgery it is restarted only once post-operative opioids are fully stopped — typically one to two weeks later, starting again at a low dose.
In emergency surgery, the team needs to know about naltrexone right away. Anesthesia can be managed with non-opioid options (ketamine, regional blocks, nonsteroidal anti-inflammatory drugs (NSAIDs)) and higher-than-usual opioid doses if required; the label for full-dose (50 mg) naltrexone warns that when opioids must be given, the amount needed may be greater than usual and the resulting breathing suppression (respiratory depression) deeper and longer-lasting.
Other drug interactions are minimal. Low dose naltrexone is compatible with selective serotonin reuptake inhibitors (SSRIs), serotonin-norepinephrine reuptake inhibitors (SNRIs), gabapentin, pregabalin, low-dose tricyclics (amitriptyline, nortriptyline), muscle relaxants, and all of the common fibromyalgia medications except opioids.
Morning vs Bedtime — The Timing Debate
For two decades, low dose naltrexone was dosed almost exclusively at bedtime. The theory was that endorphin release peaks around 2–4 a.m., so a brief opioid blockade late at night would maximize the rebound.
In practice, the bedtime dose is the reason many fibromyalgia patients quit. Vivid dreams, sleep fragmentation, and restless-legs sensations are all more likely at night. Because fibromyalgia patients already have non-restorative sleep (see sleep article), anything that worsens sleep is a dealbreaker.
The modern consensus — supported by open-label experience — is that morning dosing works just as well for pain reduction, with far fewer sleep side effects. Many low dose naltrexone-experienced prescribers now start patients on morning dosing by default.
Adjustments prescribers describe:
- When sleep is already fragile, starting with morning dosing.
- When bedtime dosing brings dream or insomnia problems, switching to morning for two weeks before giving up on low dose naltrexone entirely.
- When both timings cause side effects, split dosing: half the dose in the morning, half at noon.
What “Working” Looks Like
Low dose naltrexone is slow. It is not a pill you take and feel an hour later. Realistic expectations are critical to not giving up before it has had a chance.
- Weeks 1–2: side effects (vivid dreams, insomnia) often outweigh benefit. Some patients feel slightly worse.
- Weeks 4–6: side effects fade. Subtle improvements: a little less morning stiffness, slightly more stamina, dropping one nap, sleeping thirty minutes longer.
- Weeks 8–12: responders notice a real drop in baseline pain, usually 20–40%. Fewer bad-pain days. Flares are less intense and shorter.
- Months 3–6: full effect. Some patients continue improving through month six.
In the 2013 Younger trial, the whole group's pain fell by about 29% on the drug versus 18% on placebo, and 32% met the trial's definition of a responder (11% on placebo). That is not a cure. It is a meaningful improvement — the difference between housebound and functional, between disabled and part-time working. Combined with sleep work, pacing, and nutrient repletion (see nutrient gaps), the total quality-of-life improvement can be substantial.
Response is usually tracked with a simple daily 0–10 pain score, logged in a notebook or phone app, starting two weeks before low dose naltrexone begins and continuing for three months. Without a written record, it is nearly impossible to tell whether a slow, steady shift is real.
When Low Dose Naltrexone Is Stopped
Low dose naltrexone does not work for everyone. In the 2013 crossover trial of 31 women, roughly one in three patients (32%) met the response definition on the drug, versus 11% on placebo. The other two-thirds notice little change.
Prescribers commonly use three months at 4.5 mg as the decision point. After twelve weeks of the full target dose taken consistently, with pain and fatigue tracked daily and no pattern of improvement, low dose naltrexone is considered unlikely to help. Stopping is straightforward — no taper is required.
Before stopping, prescribers commonly check that the trial of the drug included:
- The full 4.5 mg target dose (not stuck at 3.0 mg because of side effects).
- Both morning and bedtime timings.
- A cellulose-based capsule (some patients fail on lactose or calcium carbonate fillers and succeed after switching).
- At least twelve weeks at target dose.
A small subset of patients respond only at doses slightly above 4.5 mg (up to 6 mg). For partial responders at 4.5 mg, some prescribers try one month at 6 mg before stopping.
Practical Points for Starting
- A prescriber who knows low dose naltrexone. Many rheumatologists and pain specialists are comfortable with it. Functional medicine and integrative clinics almost always are. Patient charities keep searchable lists of low dose naltrexone-experienced prescribers worldwide.
- A compounding pharmacy experienced with low dose naltrexone, often with a microcrystalline cellulose filler.
- A low starting dose. Titration schedules reach 4.5 mg over weeks rather than in week one, even though 4.5 mg is the target dose.
- Daily tracking of pain, sleep, and fatigue — a simple 0–10 score for each.
- A start outside a fibromyalgia flare. The first two weeks are noisy enough; adding low dose naltrexone on top of a flare makes side effects hard to interpret.
- One change at a time. Starting low dose naltrexone the same week as a new selective serotonin reuptake inhibitor (SSRI), a new diet, or a new supplement stack makes it hard to tell what is doing what.
- A medical-alert card noting naltrexone use, for emergency surgery or emergency-room opioid treatment. The naltrexone tablet label tells patients to carry identification that alerts medical personnel to naltrexone use.
Key Research Papers
- Younger J, Noor N, McCue R, Mackey S. Low-dose naltrexone for the treatment of fibromyalgia: findings of a small, randomized, double-blind, placebo-controlled, counterbalanced, crossover trial assessing daily pain levels. Arthritis Rheum. 2013;65(2):529–538. — doi:10.1002/art.37734
- Younger J, Mackey S. Fibromyalgia symptoms are reduced by low-dose naltrexone: a pilot study. Pain Med. 2009;10(4):663–672. — doi:10.1111/j.1526-4637.2009.00613.x
- Parkitny L, Younger J. Reduced pro-inflammatory cytokines after eight weeks of low-dose naltrexone for fibromyalgia. Biomedicines. 2017;5(2):16. — doi:10.3390/biomedicines5020016
- Younger J, Parkitny L, McLain D. The use of low-dose naltrexone (LDN) as a novel anti-inflammatory treatment for chronic pain. Clin Rheumatol. 2014;33(4):451–459. — doi:10.1007/s10067-014-2517-2
- Bested K, Jensen LM, Andresen T, et al. Low-dose naltrexone for treatment of pain in patients with fibromyalgia: a randomized, double-blind, placebo-controlled, crossover study. Pain Rep. 2023;8(4):e1080. — PubMed PMID: 38226027
- Due Bruun K, Christensen R, Amris K, et al. Naltrexone 6 mg once daily versus placebo in women with fibromyalgia: a randomised, double-blind, placebo-controlled trial. Lancet Rheumatol. 2024;6(1):e31–e39. — PubMed PMID: 38258677
- Rodríguez-Freire C, Navarrete J, Rozadilla-Sacanell A, et al. Efficacy of Low-Dose Naltrexone in Women With Fibromyalgia Syndrome: A 12-Month Randomised, Double-Blind, Placebo-Controlled Single-Centre Clinical Trial (INNOVA Study). Eur J Pain. 2026;30(6):e70321. — PubMed PMID: 42385209
- Vatvani AD, Patel P, Hariyanto TI, Yanto TA. Efficacy and safety of low-dose naltrexone for the management of fibromyalgia: a systematic review and meta-analysis of randomized controlled trials with trial sequential analysis. Korean J Pain. 2024;37(4):367–378. — PubMed PMID: 39344363
PubMed Topic Searches
For further reading, the following PubMed topic searches return current peer-reviewed work on low dose naltrexone in fibromyalgia and related neuroimmune pain conditions:
- PubMed: Low-dose naltrexone and fibromyalgia
- PubMed: Naltrexone, TLR4, and microglial activation
- PubMed: Low-dose naltrexone for chronic pain
- PubMed: Naltrexone and inflammatory cytokines
- PubMed: Fibromyalgia and neuroinflammation
- PubMed: Naltrexone and endorphin rebound
- PubMed: LDN dosing and titration
- PubMed: LDN in ME/CFS and overlapping conditions
Connections
- Orthopedics
- Nutrient Gaps in Fibromyalgia
- Low-Dose Naltrexone: History and Origins — how a 50 mg addiction drug became a 4.5 mg immune therapy — Bernard Bihari’s 1985 acquired immunodeficiency syndrome (AIDS) observation, the Penn State opioid-growth-factor work, and how low dose naltrexone spread through compounding pharmacies.
- Postural Orthostatic Tachycardia Syndrome
- Sleep and Non-Restorative Sleep
- Central Sensitization Explained
- Chronic Fatigue Syndrome
- Fibromyalgia Overview
- Chronic Pain
- Mast Cell Activation Syndrome
- Fibromyalgia and Myalgic Encephalomyelitis/Chronic Fatigue Syndrome Overlap
- ACR 2016 Diagnostic Criteria
- Small-Fiber Neuropathy Overlap
- Exercise Pacing and Graded Movement
- Low-Dose Naltrexone for Postural Orthostatic Tachycardia Syndrome — the same drug and dose range aimed at dysautonomia rather than widespread pain — who responds, who should avoid it, and how it is layered onto beta-blockers, ivabradine, and salt loading.
- Low-Dose Naltrexone
- Crohn's Disease
- Insomnia
- Fatigue
- Cannabis and Cannabidiol for Fibromyalgia