Constipation

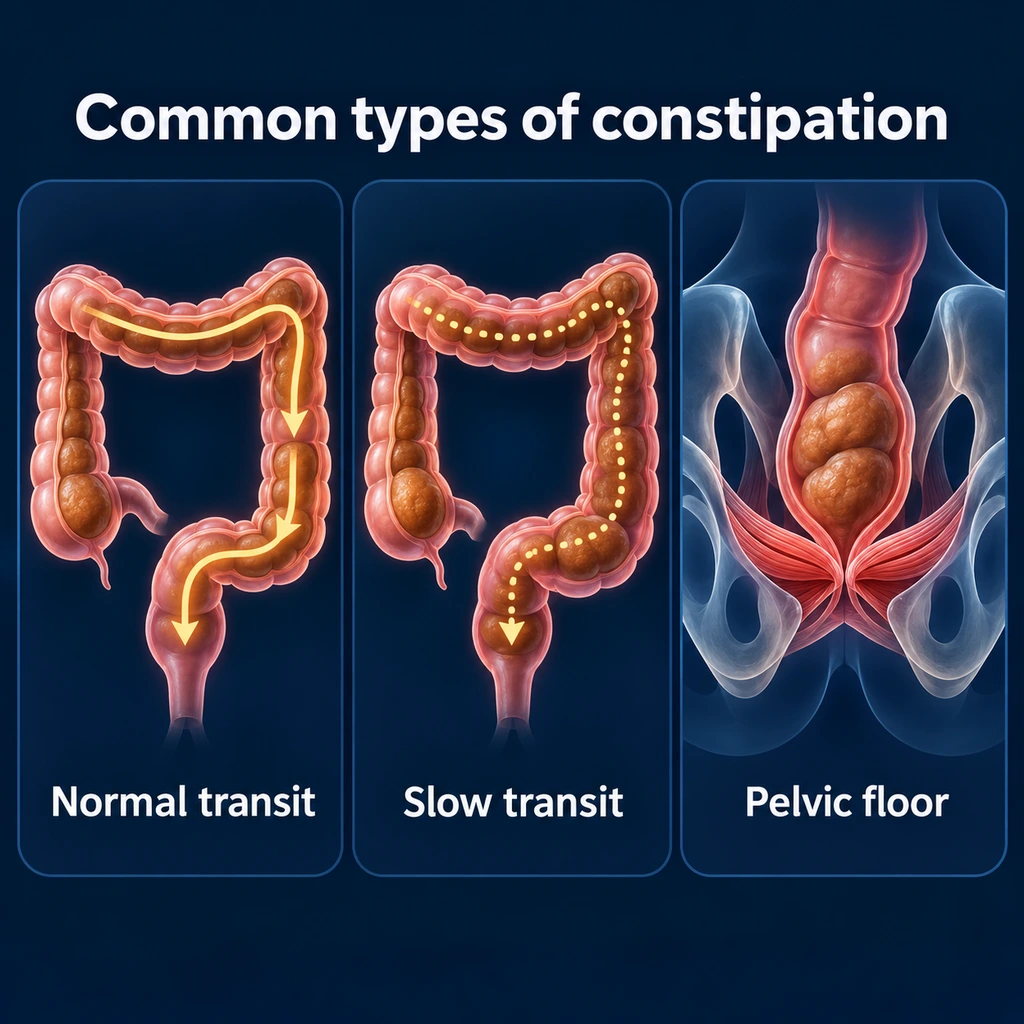
Table of Contents
Overview
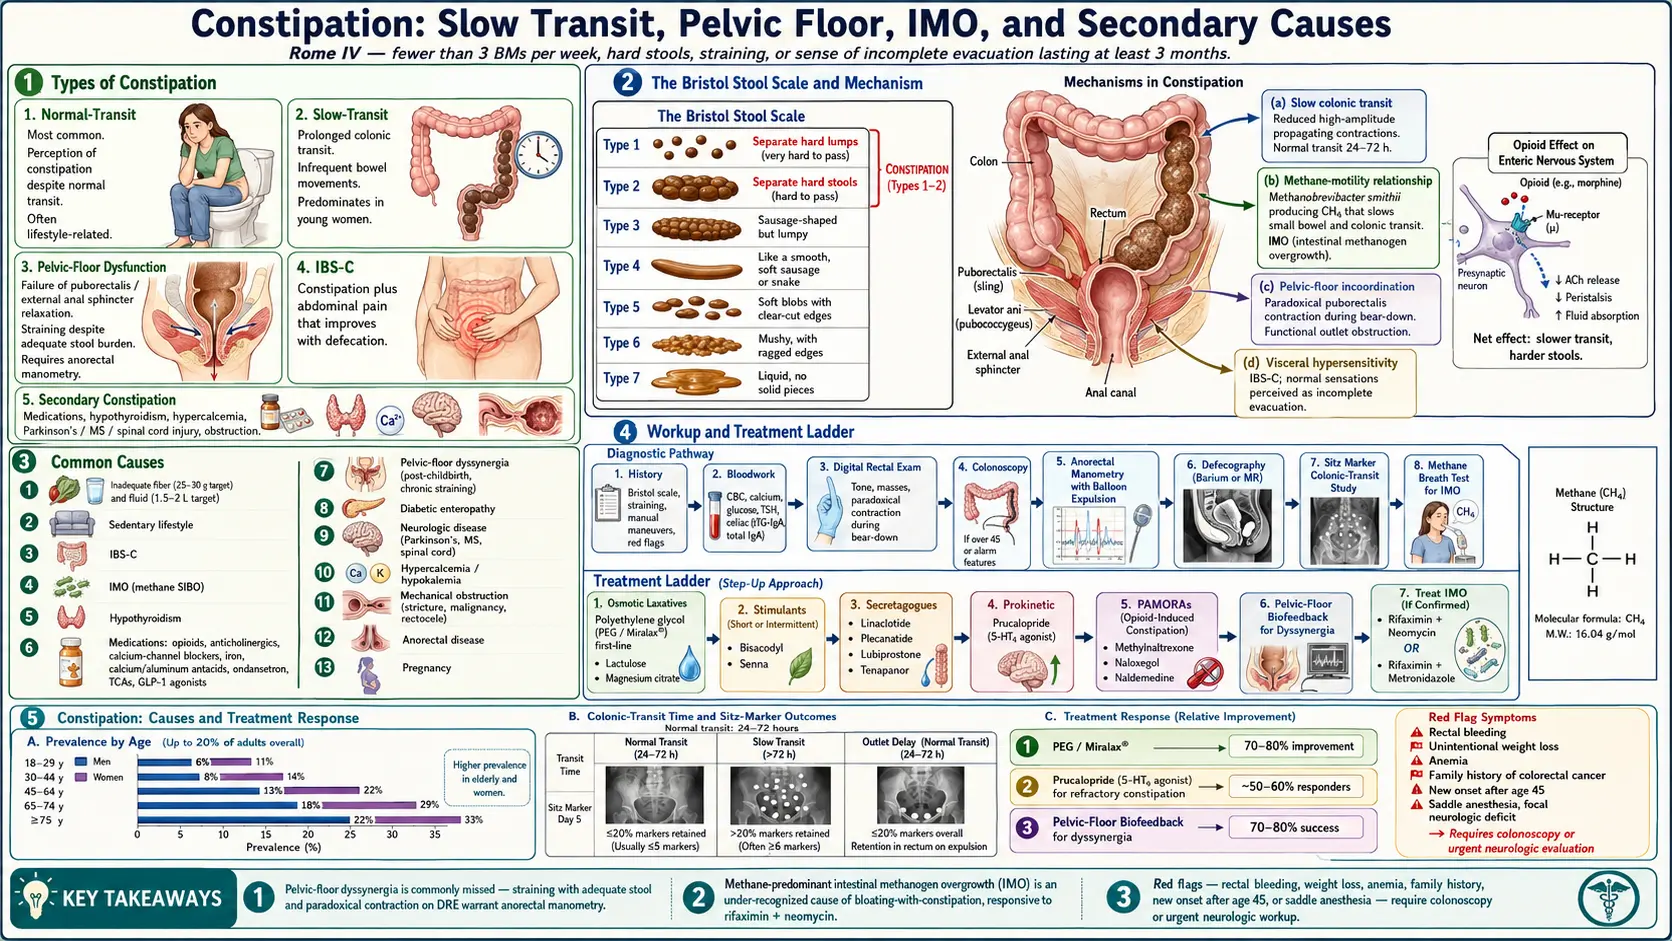
Constipation is one of the most common gastrointestinal (GI) complaints, affecting up to 20 percent of adults at any given time. The Rome IV definition is fewer than three bowel movements per week, hard or lumpy stools, sense of incomplete evacuation, straining, or need for manual maneuvers, persisting at least three months. Constipation is rarely a single disease and often involves several contributors at once: slow colonic transit, pelvic-floor dysfunction, dietary factors, medications, and metabolic conditions like hypothyroidism. Researchers describe methane-predominant intestinal methanogen overgrowth (IMO), the methane-driven cousin of small intestinal bacterial overgrowth (SIBO), as one contributor in adults with bloating-prevalent constipation.
Types of Constipation
- Normal-transit constipation — the most common type; transit time is normal but the patient perceives constipation. Often functional, related to lifestyle.
- Slow-transit constipation — prolonged colonic transit, infrequent bowel movements, often resistant to fiber and laxatives. Predominates in young women.
- Pelvic-floor dysfunction (defecatory disorders) — failure of the pelvic-floor muscles to relax during defecation; presents with straining and incomplete evacuation despite adequate stool. Often missed without anorectal manometry.
- Irritable bowel syndrome (IBS) with constipation (constipation-predominant irritable bowel syndrome, IBS-C) — constipation plus abdominal pain that improves with defecation.
- Secondary constipation — from medications, hypothyroidism, hypercalcemia, neurologic disease (Parkinson's, multiple sclerosis (MS), spinal cord injury), bowel obstruction, anorectal disease.
Common Causes
- Inadequate fiber and fluid intake — the most common modifiable cause.
- Sedentary lifestyle — movement promotes colonic motility.
- Constipation-predominant irritable bowel syndrome — functional disorder with constipation and abdominal pain.
- Intestinal methanogen overgrowth (IMO / methane small intestinal bacterial overgrowth) — methane production from Methanobrevibacter smithii slows colonic transit and produces constipation, often with bloating.
- Hypothyroidism — classic cause of constipation along with fatigue and cold intolerance.
- Medications — opioids (universal), anticholinergics, calcium-channel blockers, iron, calcium and aluminum antacids, ondansetron, tricyclics, glucagon-like peptide-1 (GLP-1) agonists.
- Pelvic-floor dyssynergia — abnormal coordination of the pelvic-floor muscles; common after childbirth and in chronic straining.
- Diabetic enteropathy — autonomic neuropathy slows colonic motility.
- Neurologic disease — Parkinson's, multiple sclerosis, spinal cord injury, autonomic dysfunction.
- Hypercalcemia and hypokalemia — both impair smooth-muscle function.
- Mechanical obstruction — colonic stricture, malignancy, hernia, rectocele.
- Anorectal disease — fissure, hemorrhoid pain causing voluntary withholding.
- Pregnancy — progesterone slows gastrointestinal motility; iron supplementation aggravates.
Mechanisms
- Slow colonic transit — reduced high-amplitude propagating contractions; normal transit is roughly 24–72 hours from mouth to anus.
- Methane and the methane-motility relationship — methane gas produced by archaea slows small-bowel and colonic transit; explains the bloating-with-constipation pattern.
- Pelvic-floor incoordination — failure to relax the puborectalis or external anal sphincter during defecation; produces functional outlet obstruction.
- Visceral hypersensitivity — in constipation-predominant irritable bowel syndrome; normal sensations are perceived as constipation or incomplete evacuation.
- Reduced colonic water absorption — the guanylate cyclase-C agonists (linaclotide, plecanatide) and the chloride-channel activator lubiprostone all work by increasing intestinal fluid secretion to soften stool.
- Opioid receptor activation in the gut — opioid receptors in the enteric nervous system slow motility independently of central effects; treated with peripherally acting mu-opioid receptor antagonists (PAMORAs).
Evaluation
- History — stool frequency and form (Bristol scale), straining, incomplete evacuation, manual maneuvers, blood in stool, weight loss, medications, family history.
- Bloodwork — complete blood count (CBC), calcium, glucose, thyroid-stimulating hormone (TSH); celiac serology is added when there are other gastrointestinal symptoms.
- Digital rectal exam — checks tone, masses, presence of stool; helps screen for pelvic-floor dyssynergia (paradoxical contraction with bear-down).
- Colonoscopy — recommended at age 45 and earlier with alarm features (rectal bleeding, weight loss, anemia, family history).
- Anorectal manometry with balloon expulsion — for refractory constipation; identifies dyssynergia.
- Defecography (barium or MR) — for suspected rectocele, intussusception, dyssynergia.
- Radiopaque marker (transit) study — measures colonic transit time.
- Hydrogen / methane breath test — for IMO when bloating is prominent. See the Breath Test Guide.
Management
- Diet and lifestyle — commonly described measures are 25–30 g of fiber a day, 1.5–2 L of fluid, regular physical activity, and a regular toilet time after meals (using the gastrocolic reflex).
- Dietary guideline (2025) — the first full dietary guideline for chronic constipation in adults, from the British Dietetic Association, was built from four systematic reviews covering 75 randomized trials. It made recommendation statements for cheap foods and drinks as well as supplements: kiwifruit, prunes, rye bread, high-mineral water, fiber supplements, probiotics, synbiotics, magnesium oxide, senna and kiwifruit supplements. It made no recommendations for whole-diet approaches because the evidence was lacking.
- Osmotic laxatives — polyethylene glycol 3350, lactulose, magnesium citrate. The 2023 American Gastroenterological Association–American College of Gastroenterology guideline on chronic idiopathic constipation gives polyethylene glycol a strong recommendation.
- Stimulant laxatives — bisacodyl, senna; safe for short- to medium-term use despite older concerns.
- Secretagogues — linaclotide, plecanatide, lubiprostone for chronic idiopathic constipation and constipation-predominant irritable bowel syndrome. In two 12-week trials of linaclotide (1,276 people with chronic constipation), 16–21% of people on linaclotide reached the main goal (3 or more complete bowel movements a week plus an increase of at least one, in 9 of 12 weeks) compared with 3–6% on placebo; diarrhea led 4.2% of people on linaclotide to stop.
- Tenapanor — a different kind of drug, an inhibitor of the gut sodium/hydrogen exchanger NHE3, tested in constipation-predominant irritable bowel syndrome. In its 12-week phase 3 trial (606 people), 27.0% on tenapanor versus 18.7% on placebo met the main goal (less abdominal pain plus more complete bowel movements); diarrhea led 6.5% to stop.
- Prokinetic — prucalopride (5-HT4 agonist) for slow-transit constipation refractory to laxatives.
- PAMORAs — methylnaltrexone, naloxegol, naldemedine for opioid-induced constipation.
- Pelvic-floor biofeedback — the treatment of choice for pelvic-floor dyssynergia.
- Methane-targeted therapy — combination rifaximin + neomycin (or rifaximin + metronidazole) for confirmed IMO; herbal antimicrobials as an alternative; see Rifaximin Protocols and Herbal Antimicrobials.
- Underlying causes — levothyroxine for hypothyroidism, magnesium correction, and a review of constipating medicines are the usual treatments of the cause.
- Surgery — subtotal colectomy is a last resort for severe slow-transit constipation refractory to all medical therapy.
What the 2023 medicine guideline says. The 2023 American Gastroenterological Association–American College of Gastroenterology guideline on medicines for chronic idiopathic constipation in adults made strong recommendations for polyethylene glycol, sodium picosulfate, linaclotide, plecanatide and prucalopride, and conditional recommendations for fiber, lactulose, senna, magnesium oxide and lubiprostone. It names medicine cost and availability, along with patient preferences, as part of the decision. Polyethylene glycol, fiber, senna and magnesium oxide are sold over the counter.
Warning Signs and Alarm Features
- Rectal bleeding, melena, or persistent change in bowel habits in someone over 45.
- Unintentional weight loss greater than 5 percent of body weight.
- Anemia or iron deficiency without obvious source.
- Family history of colon cancer or inflammatory bowel disease (IBD).
- Severe abdominal pain, distension, or vomiting (rule out obstruction).
- New constipation in an older adult that does not respond to standard measures.
- Constipation with neurologic symptoms (saddle anesthesia, leg weakness) — rule out cauda equina.
Connections
- All Symptoms
- Lactulose — How the Laxative Actually Works (In-Depth)
- IMO & Methane Constipation
- Irritable Bowel Syndrome
- Thyroid Disorders
- Small Intestinal Bacterial Overgrowth
- Bloating
- Herbal Antimicrobials
- Abdominal Pain
- Small Intestinal Bacterial Overgrowth Breath Test Guide
- Rifaximin Protocols
- Magnesium
- Prunes (Natural Laxative)
- Prunes for Constipation Relief
- Pears (Natural Laxative)
- Pears for Constipation Relief
- Hashimoto's Thyroiditis
- Chronic Diarrhea
- Diabetes
- Parkinson's Disease
- Irritable Bowel Syndrome Subtypes (Rome IV)
- Small Intestinal Bacterial Overgrowth Root Causes
- Prokinetics and Relapse Prevention
- Irritable Bowel Syndrome Medications Guide
- Hemorrhoids
- Potassium Deficiency and Constipation — how low potassium slows the bowel and when it signals ileus.
- Senna (Stimulant Laxative)
- Herbs covered on this site that discuss this condition: Haritaki (Terminalia chebula) · Carum / Ajwain (Trachyspermum ammi) · Plantain (Herb) · Aloe Vera · Vietnamese Balm (Elsholtzia ciliata)
- Discussed in depth on these pages: Tamarind for Digestive Health and Constipation
- Natural Remedies
Key Research Papers
Historical Background
Constipation has been described in medical literature for millennia, but the modern era of evidence-based therapy began with the 1960s development of polyethylene glycol, the 2006 approval of lubiprostone, and the 2012 approval of linaclotide. Pelvic-floor biofeedback emerged from anorectal manometry research in the 1980s. The 2020 ACG guideline on small intestinal bacterial overgrowth recognized methane-predominant overgrowth (IMO) as a discrete entity contributing to constipation.
Key Research Papers
- Pimentel M, Saad RJ, Long MD, Rao SSC. ACG clinical guideline: small intestinal bacterial overgrowth. American Journal of Gastroenterology. 2020;115(2):165-178. — PubMed PMID: 32023228
- Bharucha AE, Lacy BE. Mechanisms, evaluation, and management of chronic constipation. Gastroenterology. 2020;158(5):1232-1249. — doi:10.1053/j.gastro.2019.12.034
- Lembo AJ, Schneier HA, Shiff SJ, et al. Two randomized trials of linaclotide for chronic constipation. New England Journal of Medicine. 2011;365(6):527-536. — doi:10.1056/nejmoa1010863
- Camilleri M, Kerstens R, Rykx A, Vandeplassche L. A placebo-controlled trial of prucalopride for severe chronic constipation. New England Journal of Medicine. 2008;358(22):2344-2354. — doi:10.1056/nejmoa0800670
- Rao SSC, Welcher KD, Leistikow JS. Obstructive defecation: a failure of rectoanal coordination. American Journal of Gastroenterology. 1998;93(7):1042-1050. — doi:10.1111/j.1572-0241.1998.00326.x
- Chang L, Chey WD, Imdad A, et al. American Gastroenterological Association-American College of Gastroenterology Clinical Practice Guideline: Pharmacological Management of Chronic Idiopathic Constipation. Gastroenterology. 2023;164(7):1086-1106. — PubMed PMID: 37211380
- Mearin F, Lacy BE, Chang L, et al. Bowel disorders. Gastroenterology. 2016;150(6):1393-1407. — doi:10.1053/j.gastro.2016.02.031
- Locke GR, Pemberton JH, Phillips SF. American Gastroenterological Association medical position statement: guidelines on constipation. Gastroenterology. 2000;119(6):1761-1766. — doi:10.1053/gast.2000.20390
- Sharma A, Rao SSC. Constipation: pathophysiology and current therapeutic approaches. Handbook of Experimental Pharmacology. 2017;239:59-74. — doi:10.1007/164_2016_111
- Pimentel M, Lin HC, Enayati P, et al. Methane, a gas produced by enteric bacteria, slows intestinal transit and augments small intestinal contractile activity. American Journal of Physiology-Gastrointestinal and Liver Physiology. 2006;290(6):G1089-G1095. — doi:10.1152/ajpgi.00574.2004
- Dimidi E, van der Schoot A, Barrett K, et al. British Dietetic Association Guidelines for the Dietary Management of Chronic Constipation in Adults. Journal of Human Nutrition and Dietetics. 2025;38(5):e70133. — PubMed PMID: 41081513
- Chey WD, Lembo AJ, Rosenbaum DP. Efficacy of Tenapanor in Treating Patients With Irritable Bowel Syndrome With Constipation: A 12-Week, Placebo-Controlled Phase 3 Trial (T3MPO-1). American Journal of Gastroenterology. 2020;115(2):281-293. — PubMed PMID: 31934897
- Gonzalez-Martinez MA, Ortiz-Olvera NX, Mendez-Navarro J. Novel pharmacological therapies for management of chronic constipation. Journal of Clinical Gastroenterology. 2014;48(1):21-28. — PubMed PMID: 24172177
PubMed Topic Searches
Featured Videos