⚠ Evidence warning: Clinical trials or other evidence do not support the claims that post-infectious autoimmune damage is the most common cause of relapsing bacterial overgrowth, that lifelong prokinetics replace antibiotics, that visceral manipulation, abdominal self-massage or vagus-nerve exercises treat it, that a thyroid-stimulating hormone above 2.5 or reverse T3 explains relapse, and that hypermobile Ehlers-Danlos syndrome, postural orthostatic tachycardia and mast cell activation form a recognized triad. This page keeps it as a report of what people, websites or other media say.
Small Intestinal Bacterial Overgrowth (SIBO) Root Causes: Why It Keeps Coming Back
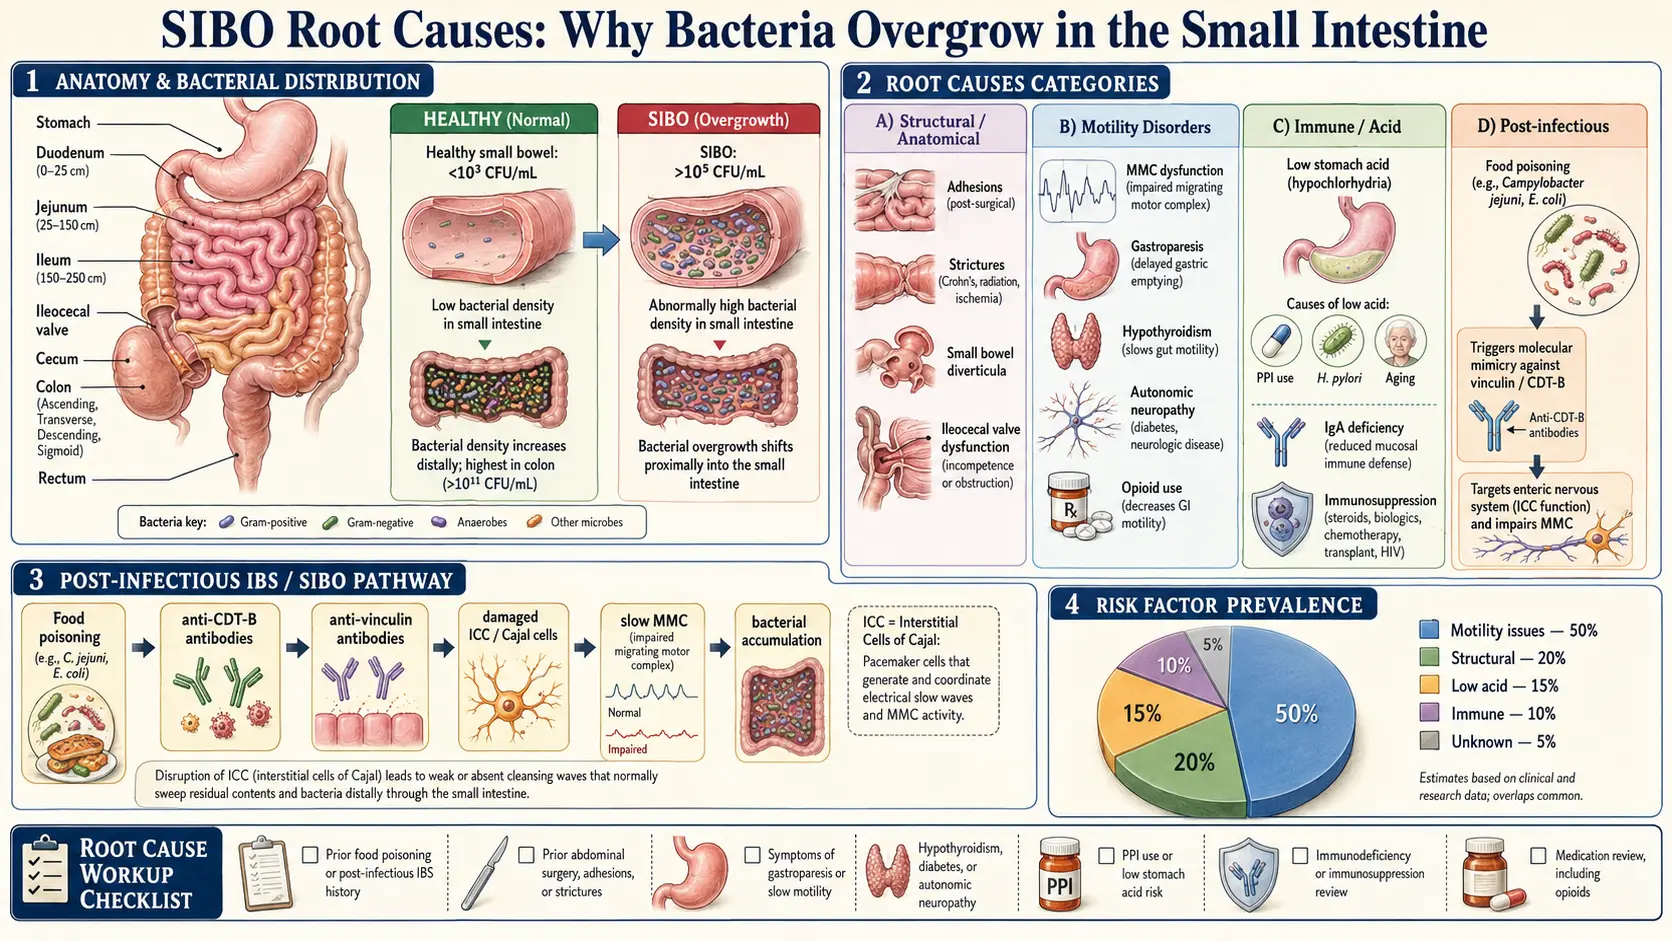
Table of Contents
- Why Small Intestinal Bacterial Overgrowth Is a Symptom, Not a Diagnosis
- Post-Infectious Irritable Bowel Syndrome (by far the most common)
- Ileocecal Valve (ICV) Dysfunction
- Abdominal Adhesions
- Hypothyroidism (including subclinical)
- Chronic Proton Pump Inhibitor Use
- Ehlers-Danlos Syndrome and Hypermobility
- Diabetes and Autonomic Neuropathy
- Scleroderma / Systemic Sclerosis
- Structural Causes (Less Common but Important)
- Stress, Vagus Nerve, and the Brain-Gut Axis
- Food Poisoning History Taking
- The Root-Cause Workup (a practical list)
- Key Research Papers
- Connections
- Featured Videos
1. Why Small Intestinal Bacterial Overgrowth Is a Symptom, Not a Diagnosis
If you’ve been treated for small intestinal bacterial overgrowth (SIBO) three times and it keeps coming back, you’re not broken. Something upstream is broken.
Small intestinal bacterial overgrowth is not really a diagnosis. It’s what happens when the body’s defenses against bacteria colonizing the small intestine fail. Finding which defense failed is the actual diagnosis. Everything else is whack-a-mole.
The small intestine is supposed to be nearly sterile. It stays that way because of a stack of overlapping defenses: stomach acid kills incoming bacteria, the migrating motor complex (MMC) sweeps the small bowel clean between meals, the ileocecal valve keeps colonic bacteria from washing backward, bile and pancreatic enzymes are bacteriostatic, and secretory immunoglobulin A (IgA) mops up what survives. When one or more of those defenses fails, bacteria move in, ferment your food, and you get the bloating, gas, diarrhea, or constipation that sent you to the doctor.
Here is the part most patients are never told: rifaximin, herbal antimicrobials, and the elemental diet all kill bacteria. None of them restore the defense that failed. In the study behind the relapse figure, 80 people cleared by rifaximin tested positive again in 12.6%, 27.5% and 43.7% of cases at 3, 6 and 9 months. Three things predicted relapse there: older age (odds ratio 1.09), a past appendectomy (odds ratio 5.9) and chronic use of acid-blocking proton pump inhibitors (odds ratio 3.52), and digestive symptoms returned along with the positive breath test. Practitioners who use the root-cause model read this as neither bad luck nor your fault — to them it’s the predictable result of killing the bugs without fixing the upstream problem.
This article is a walk through the upstream problems. Practitioners describe finding yours as the way out of cycling antibiotics and into treating the actual disease.
2. Post-Infectious Irritable Bowel Syndrome (by far the most common)
This is the single most under-diagnosed cause of chronic, relapsing small intestinal bacterial overgrowth. If you can point to a specific gastroenteritis episode — a bad shrimp in Mexico, a chicken sandwich from a gas station, a stomach bug that went through the family — and your gut was never quite the same afterward, you very likely have post-infectious irritable bowel syndrome (IBS).
The Autoimmune Mechanism
Acute food poisoning from Campylobacter jejuni, Salmonella, Shigella, enterotoxigenic E. coli, or norovirus can trigger a chain reaction that outlasts the infection by years or decades. The bacteria on that list produce a toxin called cytolethal distending toxin B (CdtB). Your immune system makes antibodies against CdtB — which is what it’s supposed to do.
Proponents of this model describe the problem this way: CdtB is structurally similar to a human intestinal protein called vinculin, which lives in the interstitial cells of Cajal (ICC) — the pacemaker cells of the small intestine. Through a process called molecular mimicry, the anti-CdtB antibodies cross-react and begin attacking vinculin, producing anti-vinculin antibodies that damage your own pacemaker cells.
The research behind this is a rat study. In rats infected with Campylobacter jejuni, antibody levels and loss of vinculin tracked the number of infections and the development of bacterial overgrowth. Human gut tissue was used only for staining, where the anti-CdtB antibodies bound the same cells. The study reports these as correlations; it did not show antibodies damaging pacemaker cells in people.
Proponents describe the result as a permanent slowing of the MMC; the rat study measured antibody levels, vinculin and overgrowth, not how long any slowing lasts. The bowel’s “housekeeping wave” becomes weak and infrequent, bacteria are never swept clear, and small intestinal bacterial overgrowth becomes the steady state of your gut. You can eradicate the bacteria all day long — the motility defect is still there, so the bacteria come back.
The Antibody Blood Test
An antibody blood test (about $250) measures both anti-CdtB and anti-vinculin antibodies. The test’s developers, comparing 100 people with diarrhea-predominant irritable bowel syndrome with 31 with inflammatory bowel disease, report specificities of 93.5% and 90.9% with sensitivities of 43.0% and 52.2%, so about half of people with the condition test negative. Assuming a 57% starting probability, they calculate a probability above 98% of diarrhea-predominant irritable bowel syndrome rather than inflammatory bowel disease when both antibodies are positive. That figure is not one for post-infectious disease or for bacterial overgrowth.
The test has been independently challenged. In Australian community and outpatient groups the antibodies did not separate irritable bowel syndrome from organic bowel disease, and anti-vinculin did not differ from healthy people.
Practitioners who use the test read a positive result this way: the root cause is autoimmune damage to the MMC, and the long-term strategy is not more antibiotics but permanent prokinetic support (low-dose naltrexone, prucalopride, low-dose erythromycin, ginger) to compensate for the pacemaker damage. See Prokinetics and Relapse Prevention for the specific agents and protocols.
Practitioners report that this diagnosis alone — knowing that your small intestinal bacterial overgrowth is autoimmune, not a character flaw or a dietary sin — is often a watershed moment for patients. It reframes the illness from “I keep failing treatment” to “I have a chronic autoimmune condition that requires ongoing management.”
3. Ileocecal Valve (ICV) Dysfunction
The ileocecal valve is a one-way sphincter between the end of the small intestine (terminal ileum) and the start of the colon (cecum). It exists specifically to prevent the dense colonic bacterial population — on the order of 1011 to 1012 organisms per gram of stool — from backflowing into the small bowel, which is supposed to be a thousand times less populated.
When the ICV stays open, flaps incompetently, or has been surgically removed, colonic bacteria wash backward and recolonize the distal ileum. You eradicate them, and within weeks they seep back in from the other side.
Common Causes of ICV Dysfunction
- Prior abdominal surgery, especially appendectomy (the appendix sits right next to the ICV, and surgical scarring can tether or distort the valve)
- Chronic constipation (sustained colonic distension stretches the valve open)
- Crohn’s disease of the terminal ileum (inflammation and scarring directly destroy the valve)
- Pelvic floor dysfunction and chronic straining
- Post-infectious scarring after severe gastroenteritis or C. difficile colitis
Treatment
Osteopathic / visceral manipulation by a trained osteopath or physical therapist is the most common non-surgical approach. Many functional practitioners also teach patients the “Gut Bug Massage” — a gentle self-massage over the lower right abdomen (where the ICV sits, roughly halfway between your belly button and your right hip bone) performed before meals to encourage the valve to close. Surgical correction of a failing ICV is rare and reserved as a last resort, because abdominal surgery creates new adhesions that can create their own motility problems.
4. Abdominal Adhesions
Every time the abdomen is opened — C-section, appendectomy, endometriosis excision, hernia repair, gallbladder removal — the body lays down scar tissue (adhesions) as it heals. These bands of fibrous tissue can physically tether loops of small intestine to each other, to the abdominal wall, or to pelvic organs. Pelvic inflammatory disease and endometriosis create their own adhesion patterns without any surgery at all.
Adhesions don’t just cause pain. They create mechanical bottlenecks: narrow passages where intestinal contents slow down, bacteria accumulate, and the MMC’s sweeping contractions can’t fully clear the segment. It’s a plumbing problem, not a microbiome problem.
How to Diagnose
- Magnetic resonance enterography or computed tomography (CT) enterography: can show kinking, tethering, or focal dilation upstream of a narrowed segment
- Upper gastrointestinal (GI) series with small bowel follow-through: shows delayed transit and abnormal loop positions in real time
- Visceral osteopathic exam: a trained clinician can often feel restricted mobility of bowel loops through the abdominal wall
Treatment Options
Visceral manipulation (including a named manual physical therapy protocol) is a manual therapy specifically developed for post-surgical and endometriosis-related adhesions. The published data come from studies co-authored by the method’s developers and report reduced obstructive symptoms and better self-reported quality of life: in a controlled study, 103 treated people with recurrent adhesive small bowel obstruction reported significantly fewer repeat obstructions than 136 untreated controls (total obstructions P = 0.0003, partial P = 0.0076), with five of six questionnaire domains improved, alongside an earlier small prospective study and two case reports. None of these abstracts measures motility. Pelvic floor physical therapy helps where pelvic adhesions are involved. Adhesiolysis surgery — cutting the adhesions — is a blunt tool: it creates new adhesions as it heals, and the cost-benefit has to be weighed carefully. It’s usually reserved for patients with documented partial obstruction or severe pain.
5. Hypothyroidism (including subclinical)
This one is enormous and routinely missed. One study of 50 people with a history of overt hypothyroidism from autoimmune thyroiditis found a positive glucose breath test in 27 of 50 (54%), against 2 of 40 controls (5%). Bloating, flatulence and abdominal discomfort improved after rifaximin, while thyroid hormone levels did not change. No study cited here covers subclinical disease. Thyroid hormone — specifically active T3 — powers intestinal smooth muscle contraction. When T3 is low, peristalsis slows, the MMC weakens, and bacteria accumulate.
The Full Thyroid Panel
Practitioners who use this model describe a thyroid-stimulating hormone (TSH) alone as not enough and order: thyroid-stimulating hormone, Free T3, Free T4, reverse T3, thyroid peroxidase (TPO) antibodies, and thyroglobulin (TG) antibodies. Reverse T3 (a metabolically inactive form) rises during stress and illness and can blunt T3’s effects even when T4 looks fine. TPO and TG antibodies identify Hashimoto’s thyroiditis, which can produce symptoms years before thyroid-stimulating hormone crosses the diagnostic threshold.
The “Subclinical” Trap
Standard lab reference ranges label a thyroid-stimulating hormone of 4.5 as normal. Many thyroid specialists consider a thyroid-stimulating hormone above 2.5 suboptimal, especially when paired with symptoms — fatigue, cold intolerance, hair thinning, constipation, weight gain, and (of course) bloating and relapsing small intestinal bacterial overgrowth. These practitioners see a thyroid-stimulating hormone of 3.8 called normal, with small intestinal bacterial overgrowth that won’t stop, as a reason for a second opinion. See Thyroid Disorders for a full workup guide.
6. Chronic Proton Pump Inhibitor Use (Omeprazole, Pantoprazole, etc.)
Proton pump inhibitors (PPIs) — omeprazole, pantoprazole, esomeprazole, lansoprazole — raise gastric pH above 4 and effectively eliminate the acid barrier that kills swallowed bacteria. They were designed for 4 to 8 weeks of use. Millions of patients have been on them for 10 or 20 years.
Chronic proton pump inhibitor use goes with higher odds of small intestinal bacterial overgrowth: a pooled odds ratio of 2.282 (95% confidence interval 1.238–4.205) in a 2013 meta-analysis, and 1.71 (1.20–2.43) in a larger one of 19 studies and 7,055 people, whose authors call the increase moderate. In the 2013 analysis the link held with aspirate culture (odds ratio 7.587) and not with the glucose breath test (odds ratio 1.93, 0.69–5.42). Up to 50% of chronic proton pump inhibitor users have measurable small intestinal bacterial overgrowth. Without a working acid barrier, every mouthful of salad or sip of tap water seeds the small intestine with organisms that healthy stomach acid would have killed in seconds.
How to Come Off Proton Pump Inhibitors Safely
A 2022 American Gastroenterological Association expert review states that when these drugs are stopped, either dose tapering or abrupt discontinuation can be considered, and that people coming off long-term use may develop short-lived upper digestive symptoms from rebound acid hypersecretion. A 2013 systematic review found that 44% of volunteers with no symptoms before treatment had acid-related symptoms up to 4 weeks after stopping, generally mild to moderate; three studies in people with reflux disease found no signs of rebound symptoms, though their methods were weak. Practitioners describe rebound lasting 2 to 8 weeks, and patients concluding they “need” the drug and going back on it. The taper they describe looks like this:
- A taper over 4 to 8 weeks: the dose halved, then every other day, then stopped
- An H2 blocker for the transition: famotidine 20–40 mg at bedtime, described as covering nocturnal acid without the microbiome effects of a proton pump inhibitor
- Temporary coating agents for breakthrough symptoms: sodium alginate after meals, sucralfate 1 g before meals
- Work on the upstream cause: hiatal hernia, H. pylori infection, food triggers (coffee, alcohol, chocolate, spicy, fatty), late-night eating, obesity, tight waistbands
Not everyone is a candidate for stopping. The same 2022 review states that people with severe erosive esophagitis, esophageal ulcer or peptic stricture, and those with Barrett’s esophagus, eosinophilic esophagitis or idiopathic pulmonary fibrosis, should generally not be considered for stopping, and that people at high risk of upper gastrointestinal bleeding should not be considered. It rests the decision on the lack of a reason for the drug, not on concern about its side effects.
Some practitioners say most patients on chronic proton pump inhibitors never needed them in the first place — and if they did, the underlying driver was never addressed.
7. Ehlers-Danlos Syndrome and Hypermobility Spectrum
If you’re unusually flexible, bruise easily, get lightheaded when you stand up, and have a gut that just won’t behave — this cluster deserves a serious look. Hypermobile Ehlers-Danlos Syndrome (hEDS) and the broader Hypermobility Spectrum Disorder (HSD) are connective tissue disorders in which collagen is structurally fragile. That fragility affects the smooth muscle and fascia of the gut just as much as it affects joints.
A loose, overly compliant intestinal wall doesn’t contract cleanly. Motility patterns become disorganized, the MMC loses amplitude, and bacteria set up shop. Many hEDS patients develop gastroparesis, chronic constipation, and chronic relapsing small intestinal bacterial overgrowth.
The Triad
Patients and some clinicians describe a triad that comes with hEDS:
- hEDS / HSD — joint hypermobility, soft stretchy skin, poor wound healing
- Postural Orthostatic Tachycardia Syndrome (POTS) — dizziness and racing heart on standing, driven by autonomic dysfunction and vascular compliance problems
- Mast Cell Activation Syndrome (MCAS) — food reactions, flushing, hives, unexplained allergic-style symptoms
If you’re flexible and dizzy and bloated, you may well have this cluster. A Beighton score assessment (a 9-point test of joint hypermobility; 5 or more in adults is suggestive) and a geneticist or an Ehlers-Danlos syndrome-literate rheumatologist are the route to formal hEDS classification.
8. Diabetes and Autonomic Neuropathy
A 2022 pooled analysis of 14 studies and 1,417 people with diabetes put small intestinal bacterial overgrowth at 29% (95% confidence interval 20–39%): 25% in type 1 and 30% in type 2. The odds ratio against controls, 2.91, was not statistically significant (0.82–10.32, p = 0.1). A wider spread of 8% to 44% is also quoted, with the higher numbers said to be in long-standing or poorly controlled disease. The mechanism is diabetic autonomic neuropathy: chronic hyperglycemia damages the small, unmyelinated autonomic nerves that control the MMC and gastric emptying. The result is gastroparesis upstream and small intestinal bacterial overgrowth downstream.
Treatment is twofold: tight glycemic control (hemoglobin A1c (HbA1c) ideally below 7.0 for motility preservation, lower for the youngest patients) and prokinetics to compensate for the nerve damage. Once the nerves are dead they don’t come back, so the strategy is prevention in early diabetes and chronic prokinetic support in established autonomic neuropathy.
9. Scleroderma / Systemic Sclerosis
Small intestinal bacterial overgrowth was found in 43.1% of 51 people with systemic sclerosis in a 2009 study. Pooled analyses give 34% (95% confidence interval 27–42%, 14 studies) and 39.9% (33.1–47.1%, 28 studies, with authors warning the reliability of the evidence may be low); by test, 56% on the lactulose breath test, 27% on the glucose breath test and 35% on aspirate culture. Odds against controls were 12.51 and 9.6 — among the highest of any medical condition. The underlying mechanism is direct: the autoimmune fibrosis that thickens scleroderma patients’ skin also fibroses the smooth muscle of the esophagus, stomach, and small intestine. Muscle that’s been replaced by scar tissue doesn’t contract. The MMC fails and bacteria overgrow.
Scleroderma-associated small intestinal bacterial overgrowth is generally not curable in the usual sense. The long-term plan practitioners describe is cycling rifaximin — typically a 2-week course once a month, or alternating rifaximin and herbal antimicrobials month to month — combined with a prokinetic and dietary management. The goal shifts from eradication to symptom control.
In pooled data on scleroderma, rifaximin cleared the overgrowth in 77.8% of people against 44.8% with rotating antibiotics. In the 2009 study, 3 months of rotating norfloxacin and metronidazole cleared it in 52.4%, with improved bowel symptoms.
10. Structural Causes (Less Common but Important)
A minority of patients have a physical abnormality that creates a bacterial hideout antibiotics can’t reach.
- Small intestinal diverticulosis — outpouchings in the jejunum or ileum where bacteria nest and re-seed the lumen. Visible on small-bowel imaging.
- Surgical blind loops — after Billroth II gastrectomy or Roux-en-Y gastric bypass, a defunctionalized loop of bowel receives no digestive flow and becomes a bacterial reservoir.
- Strictures — from Crohn’s disease, chronic nonsteroidal anti-inflammatory drug (NSAID) use, or radiation enteritis. Contents dam up behind the narrowing and bacteria proliferate.
- Intestinal malrotation — a congenital anomaly where the bowel didn’t rotate normally in utero. Often caught in childhood, but mild cases can present in adulthood as chronic small intestinal bacterial overgrowth with odd loop positions on imaging.
If you have a surgical history, significant Crohn’s disease, or breath-test findings that don’t match a straightforward small-bowel pattern, imaging (magnetic resonance enterography is the workhorse) is the usual next test.
11. Stress, Vagus Nerve, and the Brain-Gut Axis
This is the cause people roll their eyes at — and then it turns out to be their answer. Chronic sympathetic (“fight-or-flight”) overdrive directly inhibits the MMC via vagal withdrawal. The vagus nerve is the primary parasympathetic driver of gut motility; when it’s chronically suppressed by stress, trauma, or anxiety, the MMC never fires cleanly.
This is not airy-fairy. It’s well-documented in the motility literature. Patients with histories of severe stress, post-traumatic stress disorder (PTSD), eating disorders, or prolonged illness frequently have measurably weakened MMCs that don’t normalize until the vagal tone is rebuilt. Techniques with actual evidence include slow diaphragmatic breathing, cold-water face immersion, humming and gargling (stimulate the vagus via the pharyngeal branches), and gut-directed hypnotherapy programs, including app-based ones. See Prokinetics and Relapse Prevention for the specific vagal-tone protocols.
12. Food Poisoning History Taking
The one question practitioners put to every small intestinal bacterial overgrowth patient is: “Did any of this start after you got food poisoning?”
Most gastrointestinal visits skip it. The classic post-infectious pattern looks like this:
- A specific gastroenteritis episode — often travel-related (“Delhi belly,” cruise ship norovirus), shellfish, raw chicken, undercooked eggs, contaminated produce
- The acute illness resolves in 3 to 7 days
- For 3 to 6 months afterward, the patient has “irritable bowel syndrome-like” symptoms that are usually dismissed as post-viral
- Those symptoms never fully resolve, and over the following year the picture evolves into frank, relapsing small intestinal bacterial overgrowth
Practitioners ask for the timeline in writing, with approximate dates. They regard this history plus a positive antibody blood test as essentially confirming post-infectious small intestinal bacterial overgrowth, and the long-term treatment plan pivots from repeated antimicrobials to chronic prokinetics plus low-dose naltrexone. That’s a completely different disease trajectory than “another round of rifaximin.”
13. The Root-Cause Workup (a practical list)
Practitioners who work on repeated relapses describe ordering most of these by a third relapse.
- Three-gas breath test — establishes the gas subtype (hydrogen, methane, hydrogen sulfide) and baseline severity
- Antibody blood test — anti-vinculin + anti-CdtB, to identify post-infectious autoimmune small intestinal bacterial overgrowth
- Full thyroid panel — thyroid-stimulating hormone, Free T3, Free T4, reverse T3, thyroid peroxidase and thyroglobulin antibodies
- Hemoglobin A1c and fasting insulin — identifies diabetes, pre-diabetes, and insulin resistance
- Comprehensive metabolic panel + celiac panel (tissue transglutaminase immunoglobulin A with total immunoglobulin A) — rules out celiac, liver disease, kidney disease
- Beighton hypermobility score — a 2-minute bedside screen for hEDS / HSD
- Magnetic resonance enterography — if adhesions, strictures, diverticula, or Crohn’s are suspected
- Comprehensive stool test (a commercial stool panel) — screens for dysbiosis, pathogens, pancreatic elastase, calprotectin
- Medication review — proton pump inhibitors, opioids, anticholinergics, glucagon-like peptide-1 (GLP-1) agonists, tricyclic antidepressants (all slow motility)
Key Research Papers
Peer-reviewed literature on the underlying drivers of small intestinal bacterial overgrowth — post-infectious autoimmunity, motility disorders, structural anomalies, connective-tissue disease, and medication-related risk. Each citation links to the paper by DOI or PubMed record.
- Pimentel M, Morales W, Pokkunuri V, et al. Autoimmunity Links Vinculin to the Pathophysiology of Chronic Functional Bowel Changes Following Campylobacter jejuni Infection in a Rat Model. Digestive Diseases and Sciences. 2015;60(5):1195–1205. — doi:10.1007/s10620-014-3435-5
- Pimentel M, Saad RJ, Long MD, Rao SSC. ACG Clinical Guideline: Small Intestinal Bacterial Overgrowth. American Journal of Gastroenterology. 2020;115(2):165–178. — doi:10.14309/ajg.0000000000000501
- Bures J, Cyrany J, Kohoutova D, et al. Small Intestinal Bacterial Overgrowth Syndrome. World Journal of Gastroenterology. 2010;16(24):2978–2990. — doi:10.3748/wjg.v16.i24.2978
- Pimentel M, Soffer EE, Chow EJ, Kong Y, Lin HC. Lower Frequency of MMC Is Found in IBS Subjects with Abnormal Lactulose Breath Test, Suggesting Bacterial Overgrowth. Digestive Diseases and Sciences. 2002;47(12):2639–2643. — doi:10.1023/A:1021039032413
- Lin HC. Small Intestinal Bacterial Overgrowth: A Framework for Understanding Irritable Bowel Syndrome. JAMA. 2004;292(7):852–858. — doi:10.1001/jama.292.7.852
- Marie I, Ducrotté P, Denis P, Menard JF, Levesque H. Small Intestinal Bacterial Overgrowth in Systemic Sclerosis. Rheumatology. 2009;48(10):1314–1319. — doi:10.1093/rheumatology/kep226
- Lo WK, Chan WW. Proton Pump Inhibitor Use and the Risk of Small Intestinal Bacterial Overgrowth: A Meta-Analysis. Clinical Gastroenterology and Hepatology. 2013;11(5):483–490. — doi:10.1016/j.cgh.2012.12.011
- Lauritano EC, Bilotta AL, Gabrielli M, et al. Association between Hypothyroidism and Small Intestinal Bacterial Overgrowth. Journal of Clinical Endocrinology & Metabolism. 2007;92(11):4180–4184. — doi:10.1210/jc.2007-0606
- Reddymasu SC, McCallum RW. Small Intestinal Bacterial Overgrowth in Gastroparesis: Are There Any Predictors? Journal of Clinical Gastroenterology. 2010;44(1):e8–e13. — doi:10.1097/mcg.0b013e3181aec746
- Cuoco L, Salvagnini M. Small Intestine Bacterial Overgrowth in Irritable Bowel Syndrome: A Retrospective Study with Rifaximin. Minerva Gastroenterologica e Dietologica. 2006;52(1):89–95. PubMed PMID: 16554709
- Rao SSC, Bhagatwala J. Small Intestinal Bacterial Overgrowth: Clinical Features and Therapeutic Management. Clinical and Translational Gastroenterology. 2019;10(10):e00078. — doi:10.14309/ctg.0000000000000078
- Pimentel M, Wallace D, Hallegua D, et al. A Link between Irritable Bowel Syndrome and Fibromyalgia May Be Related to Findings on Lactulose Breath Testing. Annals of the Rheumatic Diseases. 2004;63(4):450–452. — doi:10.1136/ard.2003.011502
- Roland BC, Ciarleglio MM, Clarke JO, et al. Small Intestinal Transit Time Is Delayed in Small Intestinal Bacterial Overgrowth. Journal of Clinical Gastroenterology. 2015;49(7):571–576. — doi:10.1097/MCG.0000000000000257
- Lauritano EC, Gabrielli M, Scarpellini E, et al. Small intestinal bacterial overgrowth recurrence after antibiotic therapy. American Journal of Gastroenterology. 2008;103(8):2031–2035. — PubMed PMID: 18802998
- Morales W, Rezaie A, Barlow G, Pimentel M. Second-Generation Biomarker Testing for Irritable Bowel Syndrome Using Plasma Anti-CdtB and Anti-Vinculin Levels. Digestive Diseases and Sciences. 2019;64(11):3115–3121. — PubMed PMID: 31152332
- Talley NJ, Holtmann G, Walker MM, et al. Circulating Anti-cytolethal Distending Toxin B and Anti-vinculin Antibodies as Biomarkers in Community and Healthcare Populations With Functional Dyspepsia and Irritable Bowel Syndrome. Clinical and Translational Gastroenterology. 2019;10(7):e00064. — PubMed PMID: 31356481
- Rice AD, Patterson K, Reed ED, et al. Decreasing recurrent bowel obstructions, improving quality of life with physiotherapy: Controlled study. World Journal of Gastroenterology. 2018;24(19):2108–2119. — PubMed PMID: 29785079
- Rice AD, Patterson K, Reed ED, et al. Treating Small Bowel Obstruction with a Manual Physical Therapy: A Prospective Efficacy Study. BioMed Research International. 2016;2016:7610387. — PubMed PMID: 26989690
- Rice AD, King R, Reed ED, Patterson K, Wurn BF, Wurn LJ. Manual Physical Therapy for Non-Surgical Treatment of Adhesion-Related Small Bowel Obstructions: Two Case Reports. Journal of Clinical Medicine. 2013;2(1):1–12. — PubMed PMID: 26237678
- Su T, Lai S, Lee A, He X, Chen S. Meta-analysis: proton pump inhibitors moderately increase the risk of small intestinal bacterial overgrowth. Journal of Gastroenterology. 2018;53(1):27–36. — PubMed PMID: 28770351
- Targownik LE, Fisher DA, Saini SD. AGA Clinical Practice Update on De-Prescribing of Proton Pump Inhibitors: Expert Review. Gastroenterology. 2022;162(4):1334–1342. — PubMed PMID: 35183361
- Lødrup AB, Reimer C, Bytzer P. Systematic review: symptoms of rebound acid hypersecretion following proton pump inhibitor treatment. Scandinavian Journal of Gastroenterology. 2013;48(5):515–522. — PubMed PMID: 23311977
- Feng X, Li XQ. The prevalence of small intestinal bacterial overgrowth in diabetes mellitus: a systematic review and meta-analysis. Aging (Albany NY). 2022;14(2):975–988. — PubMed PMID: 35086065
- Feng X, Li XQ, Jiang Z. Prevalence and predictors of small intestinal bacterial overgrowth in systemic sclerosis: a systematic review and meta-analysis. Clinical Rheumatology. 2021;40(8):3039–3051. — PubMed PMID: 33426631
- Shah A, Pakeerathan V, Jones MP, et al. Small Intestinal Bacterial Overgrowth Complicating Gastrointestinal Manifestations of Systemic Sclerosis: A Systematic Review and Meta-analysis. Journal of Neurogastroenterology and Motility. 2023;29(2):132–144. — PubMed PMID: 37019859
PubMed Topic Searches
Live PubMed queries that update as new papers are indexed.
- PubMed: post-infectious IBS and vinculin
- PubMed: ileocecal valve and SIBO
- PubMed: abdominal adhesions and obstruction
- PubMed: SIBO and hypothyroidism
- PubMed: SIBO and proton pump inhibitors
- PubMed: Ehlers-Danlos and GI disease
- PubMed: SIBO in scleroderma / systemic sclerosis
- PubMed: diabetic autonomic neuropathy and the gut
- PubMed: vagus nerve and gut motility
Connections
- Gastroenterology
- The Gut Barrier & Your Microbiome — interactive animation
- Small Intestinal Bacterial Overgrowth Overview
- Prokinetics and Relapse Prevention
- Herbal Antimicrobials
- Elemental Diet
- Rifaximin Protocols
- Low-FODMAP Diet
- Hydrogen vs Methane vs Hydrogen Sulfide
- Breath Test Guide
- Postural Orthostatic Tachycardia Syndrome
- Mast Cell Activation Syndrome
- Thyroid Disorders
- Diabetes
- Irritable Bowel Syndrome
- Celiac Disease
- Crohn's Disease
- Alpha-Gal Syndrome
- Gut Healing
- Ehlers-Danlos Syndrome
- Herbs covered on this site that discuss this condition: Barberry (Berberis vulgaris) · Boswellia · Elecampane · Manuka Honey (Leptospermum scoparium)