Hypokalemia and Constipation: Low Potassium and a Sluggish Gut
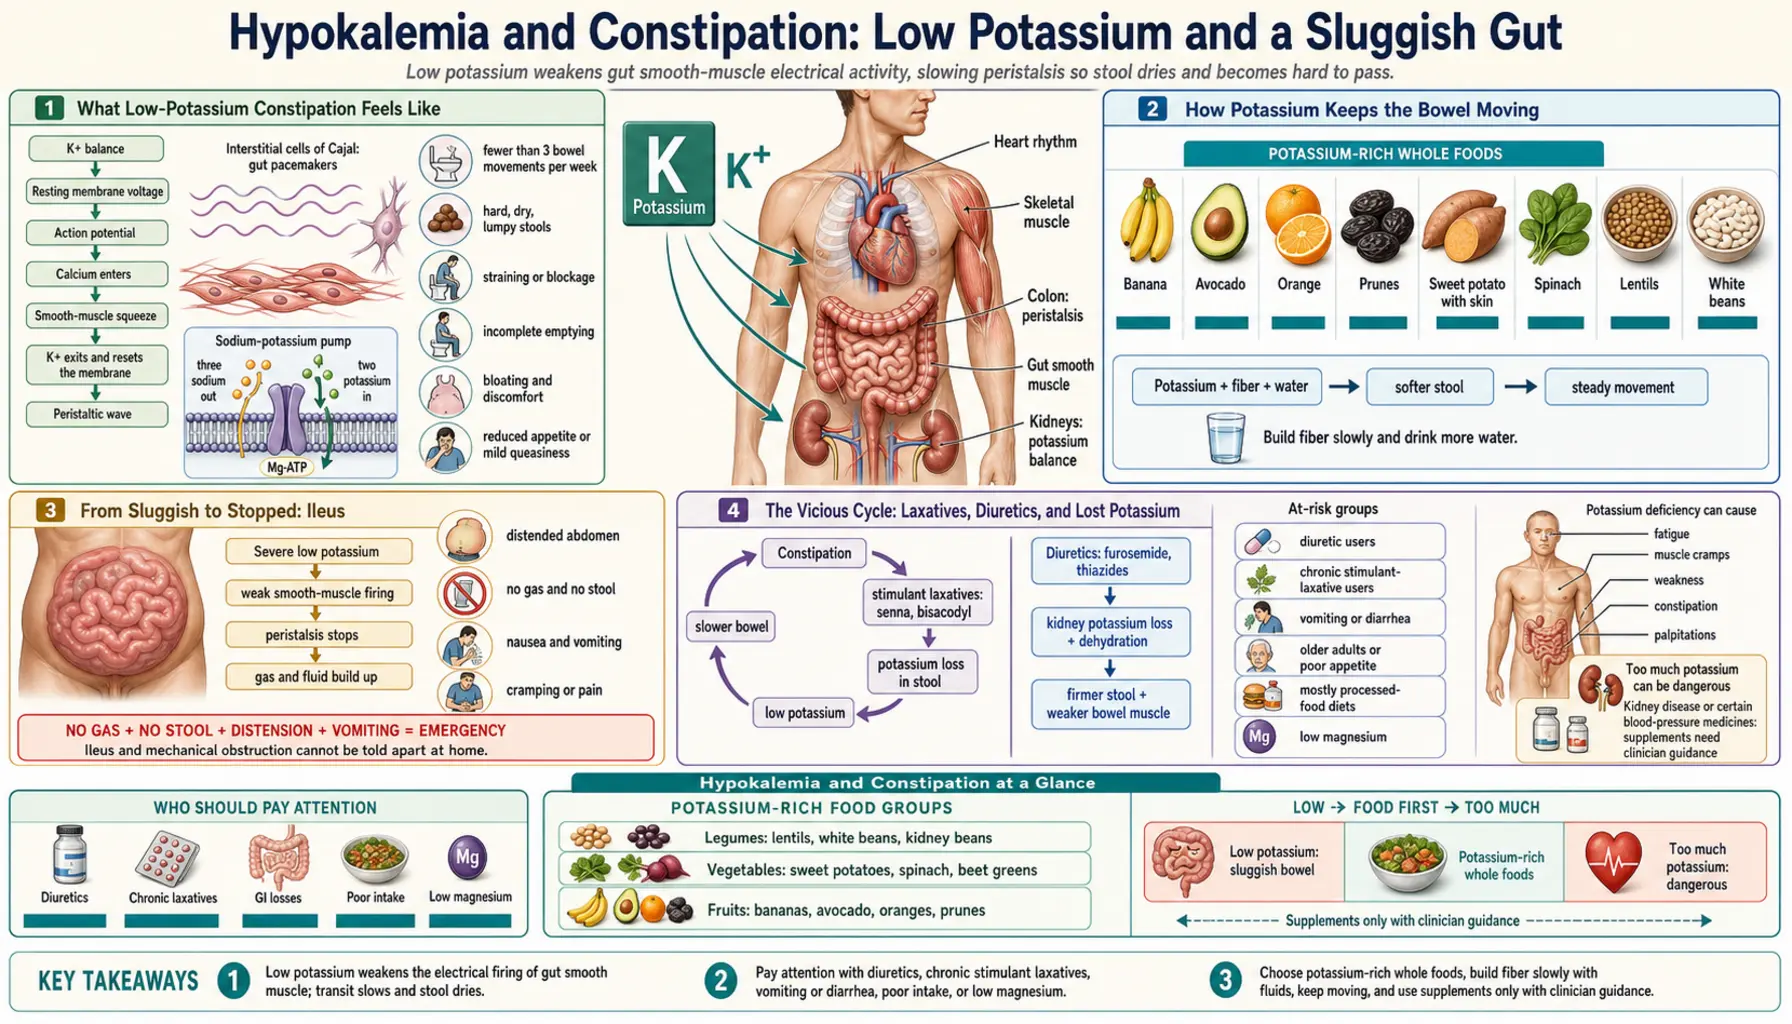
The bowel is a muscle — a long, coiled tube of smooth muscle that squeezes its contents along in slow, rhythmic waves called peristalsis. Like every muscle, it runs on electricity, and that electricity depends on potassium. When potassium runs low, those waves weaken: stool moves too slowly, sits too long, dries out, and becomes hard and difficult to pass. People notice it as fewer bowel movements, straining, bloating, and a frustrating sense of never quite emptying. A 2018 clinical review lists constipation or intestinal paralysis (ileus) among the signs of severe hypokalemia — ileus being a dangerous state in which the bowel almost stops. Clinical reviews describe the management of hypokalemia as finding and treating its cause and replacing the lost potassium; low-potassium constipation is one part of that picture.
Interactive Visualization The Sodium–Potassium Pump — why you have a voltage Run the pump that gives every cell its charge — three sodium out, two potassium in, on Mg-ATP — then drop the magnesium and see exactly why low potassium refuses to correct. Launch →
Table of Contents
- What Low-Potassium Constipation Feels Like
- How Potassium Keeps the Bowel Moving
- From Sluggish to Stopped: Ileus
- The Vicious Cycle: Laxatives, Diuretics, and Lost Potassium
- Common Causes
- The Magnesium Overlap
- How Low Potassium Is Tested
- What the Research Reports on Food, Fiber, Fluids, and Potassium Repletion
- Warning Signs Clinical Sources Describe
- Key Research Papers
- Connections
- Featured Videos
What Low-Potassium Constipation Feels Like
Constipation is one of the quieter consequences of low potassium, and it is easy to miss because the symptoms overlap with so many everyday digestive complaints. There is no single sensation that says "this is your potassium" — but when a sluggish bowel shows up alongside fatigue, muscle cramps, or weakness, or in someone taking water pills or laxatives, low potassium is one of the possibilities clinical reviews list.
People with hypokalemia-related constipation commonly describe:
- Fewer bowel movements than usual — going every two, three, or more days after having been regular. Clinical criteria for constipation (the Rome criteria described in the 2013 AGA technical review) combine several symptoms — infrequent stools, straining, hard stools, incomplete emptying — rather than stool frequency alone.
- Hard, dry, lumpy stools — the longer stool sits in the colon, the more water gets reabsorbed from it, so it becomes firm, pellet-like, and difficult to pass.
- Straining and a feeling of blockage — needing to push hard, sometimes for several minutes, and feeling as though something is stuck at the exit.
- Incomplete emptying — the nagging sense that the rectum is never fully evacuated, with repeated trips to the toilet and little result.
- Bloating, fullness, and abdominal discomfort — gas and stool backing up produce a swollen, heavy, uncomfortable belly that often eases briefly after a bowel movement.
- Reduced appetite and mild queasiness — a backed-up, sluggish gut can dull hunger and produce some nausea. Nausea is a substantial symptom in its own right when potassium falls; it has its own page in this cluster — see Hypokalemia and Nausea.
Two honest caveats. First, constipation is enormously common and usually has nothing to do with potassium — low fiber, low fluid, inactivity, travel, ignoring the urge, and many medications (opioids being the classic example) are far more frequent culprits. Second, when low potassium is involved, it rarely acts alone: a 2018 review reports that more than half of clinically significant hypokalemia comes with magnesium deficiency, which makes the low potassium harder to correct. The picture is most convincing when constipation appears together with other signs of low potassium and a plausible cause such as diuretic use, vomiting, diarrhea, or chronic laxative use.
How Potassium Keeps the Bowel Moving
To understand why low potassium slows the bowel, picture how the gut actually moves its contents. The wall of the intestine is wrapped in layers of smooth muscle. To push food and stool forward, this muscle contracts in a coordinated, traveling squeeze — the ring of muscle tightens behind the contents and relaxes ahead of it, so the bolus is milked along the tube. Repeated over and over, this produces the slow waves of peristalsis that move material from stomach to colon to rectum.
Every one of those contractions is an electrical event. Muscle cells, including the smooth muscle of the gut, hold a small voltage across their outer membrane — the inside is electrically negative compared with the outside. This resting voltage is built and maintained largely by potassium: the cell pumps potassium in and sodium out, and potassium then leaks back out through tiny channels, and that controlled leak is what sets the negative resting charge. When a contraction is needed, the membrane briefly flips its charge (an "action potential"), calcium floods in, and the muscle squeezes. Then potassium flows back out to reset the membrane so it is ready to fire again.
Potassium therefore does two jobs in gut muscle at once: it sets the stable starting voltage the muscle needs in order to fire cleanly, and its outward flow is what ends each contraction and re-arms the muscle for the next wave. The gut also has its own built-in pacemaker cells — the interstitial cells of Cajal — that generate rhythmic electrical "slow waves" and set the tempo of peristalsis, and these too depend on a normal balance of ions across their membranes.
When potassium outside the cells falls, the resting voltage becomes more negative, and the muscle is harder to excite. Clinical reviews describe the result in severe hypokalemia as reduced gut motility, ranging from constipation to intestinal paralysis: contents move down the tube too slowly. And here is the part patients feel directly — the large bowel absorbs mainly water, as a 2010 review of laxative abuse summarizes it. The longer stool lingers in a slow colon, the more water is pulled out of it, so it arrives at the rectum hard, dry, and hard to pass. Slow transit and dehydrated stool are the two mechanical reasons low potassium produces constipation.
This is the same family of mechanism behind low potassium's effects elsewhere — weak skeletal muscle and cramps come from the very same loss of clean electrical firing in muscle. The bowel is simply the smooth-muscle version of that story.
From Sluggish to Stopped: Ileus
If potassium falls far enough, the bowel does not just slow down — it can effectively stop. This is called ileus (more precisely, a paralytic or adynamic ileus): the smooth muscle becomes so under-powered that peristalsis ceases, and nothing moves forward. It is one of the recognized complications of severe hypokalemia and a genuine medical emergency. Hypokalemia is defined as a serum potassium below 3.5 mmol/L (normal range 3.5–5.0); a 2018 clinical review grades it mild at 3.0–3.4, moderate at 2.5–2.9 and severe below 2.5 mmol/L, notes that symptoms generally do not appear until potassium is below 3.0 unless it falls rapidly, and lists constipation or intestinal paralysis among the signs of severe hypokalemia. A 2017 systematic review of 14 published cases of colonic pseudo-obstruction with secretory diarrhea and potassium loss reported a median serum potassium of 2.4 mmol/L (range 1.9–3.1); three of the 14 patients died.
Ileus looks and feels very different from ordinary constipation. The hallmarks are:
- A distended, swollen abdomen — because gas and fluid pile up behind the stalled segment with nowhere to go.
- No passage of gas and no stool at all — not "less than usual" but a complete halt. The inability to pass gas is an especially important warning sign.
- Nausea and vomiting — as the upper gut backs up. (Ileus is one of the places the constipation and nausea stories overlap; the shared mechanism is covered on the Hypokalemia and Nausea page — this page does not repeat it.)
- Cramping, bloating, and abdominal discomfort or pain.
A critical point for safety: the symptoms of paralytic ileus can be nearly identical to those of a mechanical bowel obstruction — an actual physical blockage from a tumor, scar tissue, a twist, or impacted stool. From the outside, "no gas, no stool, distended, vomiting" can mean either one, and the two are managed very differently. Telling them apart takes in-person evaluation, usually with imaging and blood tests, to separate paralytic ileus (treated by correcting the potassium and other electrolytes, resting the bowel, and treating the cause) apart from a true obstruction (which may need a procedure or surgery). See the red-flags section below.
The Vicious Cycle: Laxatives, Diuretics, and Lost Potassium
Two kinds of medicine connect to low-potassium constipation from both sides: laxatives, when they are overused, and diuretics. The research on each is set out below, including where the commonly told story of a "laxative trap" goes further than the evidence.
Laxative abuse — heavy, prolonged use beyond what a constipated bowel needs, most often of stimulant laxatives (senna, bisacodyl) — is a recognized cause of hypokalemia: reviews list chronic laxative abuse among the gastrointestinal routes of potassium loss, and a 2010 review of laxative abuse describes electrolyte and acid–base changes that can become life-threatening. One group of overusers it describes is middle-aged or older people who begin taking laxatives for constipation and continue to overuse them. Because low potassium itself slows the gut, a loop is possible: a 2023 case report describes laxatives worsening hypokalemia and contributing to colonic distension in a 67-year-old man with acute colonic pseudo-obstruction. The evidence does not show such a loop at ordinary doses. A 2005 review of constipation myths concluded that stimulant laxatives at recommended doses are unlikely to harm the colon, that tolerance to them is uncommon, that there is no indication of "rebound constipation" after stopping, and that the laxative dependence some patients have is not the result of prior laxative use.
A very similar loop runs through diuretics ("water pills" such as furosemide and the thiazides, taken for blood pressure, heart failure, or swelling). A 2015 review names diuretic use, with gastrointestinal losses, as a common cause of low potassium; these drugs make the kidney excrete more potassium along with the extra fluid and salt. They can also cause fluid loss, a second possible contributor to hard stool. The two can combine: a 1999 case report describes a man on daily furosemide with a history of laxative abuse whose potassium fell to 1.7 mmol/L after a bout of gastroenteritis, causing paralysis of the legs that resolved as potassium was restored.
The 2010 laxative-abuse review describes management as identifying what drives the overuse, stopping the stimulant laxatives and replacing them with fibre or osmotic products to re-establish normal bowel movements, with serum electrolytes checked. For chronic constipation in general, the 2023 AGA–ACG guideline made strong recommendations for polyethylene glycol, sodium picosulfate (a stimulant laxative), linaclotide, plecanatide and prucalopride, and conditional recommendations for fiber, lactulose, senna, magnesium oxide and lubiprostone — so stimulant laxatives used as studied are a recognized option, and the concern in the research is heavy overuse combined with ongoing potassium loss. Decisions about laxatives, diuretics and supplements belong with a clinician.
Common Causes
Low potassium severe enough to slow the bowel usually has an identifiable cause. The big ones to think about:
- Diuretics ("water pills"). Thiazide and loop diuretics are among the common causes of low potassium, because they increase potassium loss in the urine. Constipation can plausibly follow both from the potassium loss and from the fluid loss these drugs can cause.
- Laxative overuse. As described above, chronic laxative abuse is listed among the gastrointestinal causes of potassium loss.
- Vomiting and diarrhea. This sounds paradoxical — diarrhea is the opposite of constipation — but bouts of vomiting or diarrhea (a stomach bug, food poisoning, ongoing GI illness) flush large amounts of potassium out of the body. Case reports going back to the 1950s, known in English by their titles, describe hypokalemia with paralytic ileus in gastroenteritis and after prolonged diarrhea.
- Poor intake. Diets low in fruits, vegetables, beans, and other whole foods deliver little potassium and little fiber. A 2018 review notes that hypokalemia usually comes from increased losses or shifts of potassium into cells, and less commonly from low intake alone, although the kidney is far better at raising than lowering its potassium excretion, so inadequate intake can lead to depletion.
- Hyperaldosteronism and related hormonal causes. Conditions in which the body makes too much of the hormone aldosterone (such as Conn's syndrome) drive the kidney to waste potassium continuously. Genuine licorice (containing glycyrrhizin) and Cushing's syndrome are also listed among the renal causes of potassium loss. Clinical reviews describe treating the underlying hormonal cause in these cases.
- Magnesium depletion. Low magnesium frequently accompanies low potassium and makes it hard for the body to hold onto potassium at all — important enough to get its own section below.
Several of these overlap with the other symptoms in this cluster. The same diuretic that constipates one person triggers muscle cramps in another and bone-tired fatigue in a third — one electrolyte problem with many faces.
The Magnesium Overlap
You cannot tell the full story of low-potassium constipation without magnesium, for two distinct reasons.
First, low magnesium and low potassium travel together. The same situations that waste potassium — diuretics, vomiting, diarrhea, poor intake, alcohol use — also waste magnesium, so the two deficiencies frequently coexist. A 2018 review reports that more than half of clinically significant hypokalemia comes with magnesium deficiency, most often in people taking loop or thiazide diuretics. A 2007 review of the mechanism explains that low magnesium inside kidney cells releases a brake on a potassium channel (ROMK) in the distal nephron, so more potassium is secreted into the urine; magnesium deficiency aggravates hypokalemia and makes it refractory to potassium treatment, though magnesium deficiency alone does not necessarily cause hypokalemia.
Second, magnesium also helps the bowel directly — by a completely separate mechanism from its potassium connection. Magnesium salts (magnesium oxide, magnesium hydroxide, magnesium citrate) act as osmotic agents: they are poorly absorbed, so they draw water into the colon, softening stool and gently stimulating movement. For magnesium oxide, a 2019 placebo-controlled trial in 34 Japanese women with mild-to-moderate chronic constipation (0.5 g three times daily for 28 days) found overall improvement in 70.6% on magnesium oxide versus 25.0% on placebo, with shorter colonic transit time; the 2023 AGA–ACG guideline gives magnesium oxide a conditional recommendation. Magnesium therefore bears on this kind of constipation in two separate ways: through the kidney's handling of potassium, and as an osmotic agent in the bowel.
The hazards are documented. Large laxative doses of magnesium can cause diarrhea, which itself loses potassium. In people with reduced kidney function magnesium can build up to dangerous levels: a 2019 case series describes four older adults with kidney impairment who developed symptomatic hypermagnesemia from magnesium oxide taken for constipation, one fatally, and a 2023 case-control study in older patients found low creatinine clearance to be the significant risk factor, with higher magnesium oxide doses a further consideration. Magnesium itself is covered on Magnesium and Magnesium Replenishment pages.
How Low Potassium Is Tested
Because constipation has so many causes, the value of testing is in confirming whether low potassium is genuinely part of a person's picture — and in catching the other electrolyte and organ problems that travel with it. The basic work-up is a routine blood test.
- A basic blood panel. The core test is a Comprehensive Metabolic Panel (CMP) — a single blood draw that reports serum potassium along with sodium, chloride, bicarbonate, glucose, and kidney markers (creatinine and BUN). It shows in one snapshot whether potassium is low and how the kidneys, which govern potassium balance, are doing. A basic metabolic panel (BMP) covers the same electrolytes if a CMP is not ordered.
- Magnesium. Magnesium is not included on a standard CMP and must be requested separately. A 1990 laboratory study of 1,033 specimens sent for electrolytes found that physicians had requested magnesium for only 8 of the 53 specimens that were low in both magnesium and potassium (15%); its authors recommended routine magnesium measurement whenever electrolytes are analyzed.
- One honest limitation. The blood test measures potassium in the bloodstream, but potassium is mainly an intracellular ion; a 2011 review notes that a mere 1% shift in its distribution across cell membranes can change the plasma level by 50%. The blood level is therefore an indirect window on body stores, and results are interpreted alongside symptoms, medications, and diet — not in isolation.
- Looking for a cause. Depending on the findings, a clinician may review the medication list (especially diuretics and laxatives), check urine electrolytes to see whether potassium is being lost through the kidney, or test for hormonal causes such as excess aldosterone when low potassium is unexplained or stubborn.
If constipation is severe, new, or accompanied by the red-flag features below, the evaluation widens beyond electrolytes to look directly at the bowel.
What the Research Reports on Food, Fiber, Fluids, and Potassium Repletion
Clinical reviews describe treating hypokalemia by correcting its cause and replacing potassium; for constipation, trials and guidelines have tested fiber, osmotic laxatives and other agents. What each line of research reports:
Potassium-rich whole foods. Whole fruits, vegetables and legumes deliver potassium together with fiber and water. Foods commonly listed as rich in potassium include:
- Fruits — bananas, avocado, oranges, cantaloupe, apricots, and dried fruits like prunes and figs (in a 2011 crossover trial in 40 adults with constipation, prunes improved weekly complete bowel movements and stool consistency more than psyllium did).
- Vegetables — sweet potatoes (with skin), regular potatoes, spinach, beet greens, squash, and tomatoes.
- Legumes — lentils, white beans, kidney beans, and other pulses, which supply both potassium and fiber.
- For a fuller, organized list, see Potassium-Rich Foods.
Fiber. A 2016 meta-analysis of seven randomized trials in chronic idiopathic constipation found that 77% of patients given fiber supplements responded, against 44% on placebo; fiber increased stool frequency and softened stools but also increased flatulence, and the authors rated the overall quality of evidence as low. A 2005 review notes that many patients with more severe constipation get worse symptoms when dietary fiber is increased.
Fluids. The same 2005 review found no evidence that constipation can be treated by increasing fluid intake unless there is evidence of dehydration — which is the situation after diuretic-related fluid loss or a bout of vomiting or diarrhea.
Movement. The 2005 review reports that in older people constipation may correlate with decreased physical activity, with many cofactors, and that programs to increase activity as part of broader rehabilitation may help.
Correcting the potassium (and magnesium) itself. Clinical reviews describe addressing the underlying cause — a diuretic, ongoing GI losses, laxative overuse — and repleting potassium and, where needed, magnesium. A 2018 review describes oral potassium for mild to moderate hypokalemia (2.5–3.5 mmol/L) and intravenous potassium with ECG monitoring below 2.5 mmol/L, with magnesium corrected as well. Too much potassium is itself dangerous: kidney disease and medicines that block the renin–angiotensin–aldosterone system (such as ACE inhibitors and angiotensin-receptor blockers) are recognized causes of hyperkalemia. In the United States, potassium-salt tablets supplying 100 mg or more of potassium each carry prescription labeling under federal rule 21 CFR 201.306, whose required warning describes small-bowel lesions — stenosis, ulceration, obstruction, bleeding and perforation — reported with coated potassium tablets. For the constipation itself, the 2023 AGA–ACG guideline's strong recommendations include polyethylene glycol, an osmotic laxative. Decisions about potassium and other supplements belong with a clinician.
Warning Signs Clinical Sources Describe
Most constipation is a nuisance, not an emergency. Clinical sources single out a few patterns for prompt evaluation — and one of them is a true emergency.
Signs of a stopped bowel (ileus or obstruction), a medical emergency:
- No stool and no gas for an extended period, especially with a swollen, distended abdomen and vomiting. This combination can mean paralytic ileus from severe low potassium or a mechanical bowel obstruction, and the two cannot be told apart at home — clinicians treat both as needing urgent in-person assessment.
- Severe, worsening abdominal pain or a belly that is rigid and tender to touch.
Features clinical sources list as reasons for prompt (non-emergency) evaluation:
- Blood in the stool — bright red, dark, or black, tarry stools — or unexplained weight loss along with the constipation. The 2013 AGA technical review lists blood in stool, unexplained anemia, weight loss and an abdominal or rectal mass as alarm features.
- Severe muscle weakness, an irregular or pounding heartbeat, or palpitations occurring alongside the constipation. These suggest potassium has fallen low enough to affect heart and skeletal muscle, which is more serious than the bowel symptom alone. See Heart Palpitations and Arrhythmia.
- A sudden, persistent change in bowel habits (new constipation that does not let up over a few weeks), constipation alternating with diarrhea, or stools that have become persistently thin or pencil-like.
- Constipation in someone taking diuretics or chronic laxatives — a setting in which reviews describe checking potassium and magnesium.
- Constipation that does not respond to a genuine trial of more fiber, fluids, and movement.
Of these, the no-gas/no-stool-with-distension-and-vomiting picture, blood in the stool, and constipation alongside cardiac or severe muscle symptoms are the patterns clinical sources treat as most urgent.
Key Research Papers
- Gennari FJ (1998). Hypokalemia. New England Journal of Medicine;339(7):451-458. — DOI: 10.1056/NEJM199808133390707. — doi:10.1056/NEJM199808133390707
- Kardalas E, Paschou SA, Anagnostis P, Muscogiuri G, Siasos G, Vryonidou A (2018). Hypokalemia: a clinical update. Endocrine Connections;7(4):R135-R146. — DOI: 10.1530/EC-18-0109. — doi:10.1530/EC-18-0109
- Unwin RJ, Luft FC, Shirley DG (2011). Pathophysiology and management of hypokalemia: a clinical perspective. Nature Reviews Nephrology;7(2):75-84. — DOI: 10.1038/nrneph.2010.175. — doi:10.1038/nrneph.2010.175
- Palmer BF (2015). Regulation of Potassium Homeostasis. Clinical Journal of the American Society of Nephrology;10(6):1050-1060. — DOI: 10.2215/CJN.08580813. — doi:10.2215/CJN.08580813
- Viera AJ, Wouk N (2015). Potassium Disorders: Hypokalemia and Hyperkalemia. American Family Physician;92(6):487-495. — PubMed PMID: 26371733
- Lembo A, Camilleri M (2003). Chronic Constipation. New England Journal of Medicine;349(14):1360-1368. — DOI: 10.1056/NEJMra020995. — doi:10.1056/NEJMra020995
- Bharucha AE, Pemberton JH, Locke GR (2013). American Gastroenterological Association Technical Review on Constipation. Gastroenterology;144(1):218-238. — DOI: 10.1053/j.gastro.2012.10.028. — doi:10.1053/j.gastro.2012.10.028
- Sanders KM, Koh SD, Ward SM (2006). Interstitial Cells of Cajal as Pacemakers in the Gastrointestinal Tract. Annual Review of Physiology;68:307-343. — DOI: 10.1146/annurev.physiol.68.040504.094718. — doi:10.1146/annurev.physiol.68.040504.094718
- Camilleri M (2012). Peripheral Mechanisms in Irritable Bowel Syndrome. New England Journal of Medicine;367(17):1626-1635. — DOI: 10.1056/NEJMra1207068. — doi:10.1056/NEJMra1207068
- Mori S, Tomita T, Fujimura K, et al. (2019). A Randomized Double-blind Placebo-controlled Trial on the Effect of Magnesium Oxide in Patients With Chronic Constipation. Journal of Neurogastroenterology and Motility;25(4):563-575. — DOI: 10.5056/jnm18194. — doi:10.5056/jnm18194
- Christodoulides S, Dimidi E, Fragkos KC, Farmer AD, Whelan K, Scott SM (2016). Systematic review with meta-analysis: effect of fibre supplementation on chronic idiopathic constipation in adults. Alimentary Pharmacology & Therapeutics;44(2):103-116. — DOI: 10.1111/apt.13662. — doi:10.1111/apt.13662
- Crockett SD, Greer KB, Heidelbaugh JJ, et al. (2019). American Gastroenterological Association Institute Guideline on the Medical Management of Opioid-Induced Constipation. Gastroenterology;156(1):218-226. — DOI: 10.1053/j.gastro.2018.07.016. — doi:10.1053/j.gastro.2018.07.016
- Whang R, Ryder KW (1990). Frequency of hypomagnesemia and hypermagnesemia. Requested vs routine. JAMA;263(22):3063-3064. — PubMed PMID: 2342219
- Huang CL, Kuo E (2007). Mechanism of hypokalemia in magnesium deficiency. Journal of the American Society of Nephrology;18(10):2649-2652. — PubMed PMID: 17804670
- Müller-Lissner SA, Kamm MA, Scarpignato C, Wald A (2005). Myths and misconceptions about chronic constipation. American Journal of Gastroenterology;100(1):232-242. — PubMed PMID: 15654804
- Roerig JL, Steffen KJ, Mitchell JE, Zunker C (2010). Laxative abuse: epidemiology, diagnosis and management. Drugs;70(12):1487-1503. — PubMed PMID: 20687617
- Iftikhar N, Rehman Khalid MO, Ghori U (2023). Ogilvie Syndrome Secondary Due To Underlying Hypokalaemia And Anticholinergics: Case Report And Brief Review Of The Literature. Journal of the Pakistan Medical Association;73(11):2277-2279. — PubMed PMID: 38013547
- Bazerbachi F, Haffar S, Szarka LA, Wang Z, Prokop LJ, Murad MH, Camilleri M (2017). Secretory diarrhea and hypokalemia associated with colonic pseudo-obstruction: A case study and systematic analysis of the literature. Neurogastroenterology & Motility;29(11):e13120. — PubMed PMID: 28580600
- Schlesinger B (1953). Hypokalemia and paralytic ileus in gastroenteritis [in French]. Archives Françaises de Pédiatrie;10(2):178-185. — PubMed PMID: 13058455
- Boehner H (1965). Paralytic ileus with hypokalemia following diarrhea of more than a month duration [in German]. Die Medizinische Welt;18:1002-1004. — PubMed PMID: 14291118
- Rudolf J, Würker M, Neveling M, Grond M, Haupt WF, Heiss WD (1999). Hypokalemic paralysis in furosemide therapy and simultaneous laxative abuse [in German]. Medizinische Klinik;94(7):391-394. — PubMed PMID: 10437370
- Chang L, Chey WD, Imdad A, et al. (2023). American Gastroenterological Association-American College of Gastroenterology Clinical Practice Guideline: Pharmacological Management of Chronic Idiopathic Constipation. Gastroenterology;164(7):1086-1106. — PubMed PMID: 37211380
- Palmer BF (2004). Managing hyperkalemia caused by inhibitors of the renin-angiotensin-aldosterone system. New England Journal of Medicine;351(6):585-592. — PubMed PMID: 15295051
- Yamaguchi H, Shimada H, Yoshita K, et al. (2019). Severe hypermagnesemia induced by magnesium oxide ingestion: a case series. CEN Case Reports;8(1):31-37. — PubMed PMID: 30136128
- Ishii H, Sawada R, Shiomi M, Shibuya K (2023). A case-control study showing low creatinine clearance and high magnesium intake as risk factors for hypermagnesemia in older individuals. Magnesium Research;36(2):23-30. — PubMed PMID: 37897255
- Attaluri A, Donahoe R, Valestin J, Brown K, Rao SS (2011). Randomised clinical trial: dried plums (prunes) vs. psyllium for constipation. Alimentary Pharmacology & Therapeutics;33(7):822-828. — PubMed PMID: 21323688
PubMed Topic Searches
Connections
- All Minerals
- The Sodium–Potassium Pump — interactive animation
- Hypokalemia (Symptom Hub)
- Hypokalemia and Nausea
- Hypokalemia and Fatigue
- Hypokalemia and Muscle Weakness
- Hypokalemia and Muscle Cramps
- Potassium Overview
- Potassium-Rich Foods
- Magnesium
- Magnesium Replenishment
- Comprehensive Metabolic Panel
- Kidney Disease
- Heart Palpitations
- Bananas
- Sweet Potatoes
- Lentils
- Constipation — the full symptom page covering every cause, not just low potassium.