Mitochondrial Dysfunction & Energy Metabolism in Myalgic Encephalomyelitis/Chronic Fatigue Syndrome (ME/CFS)
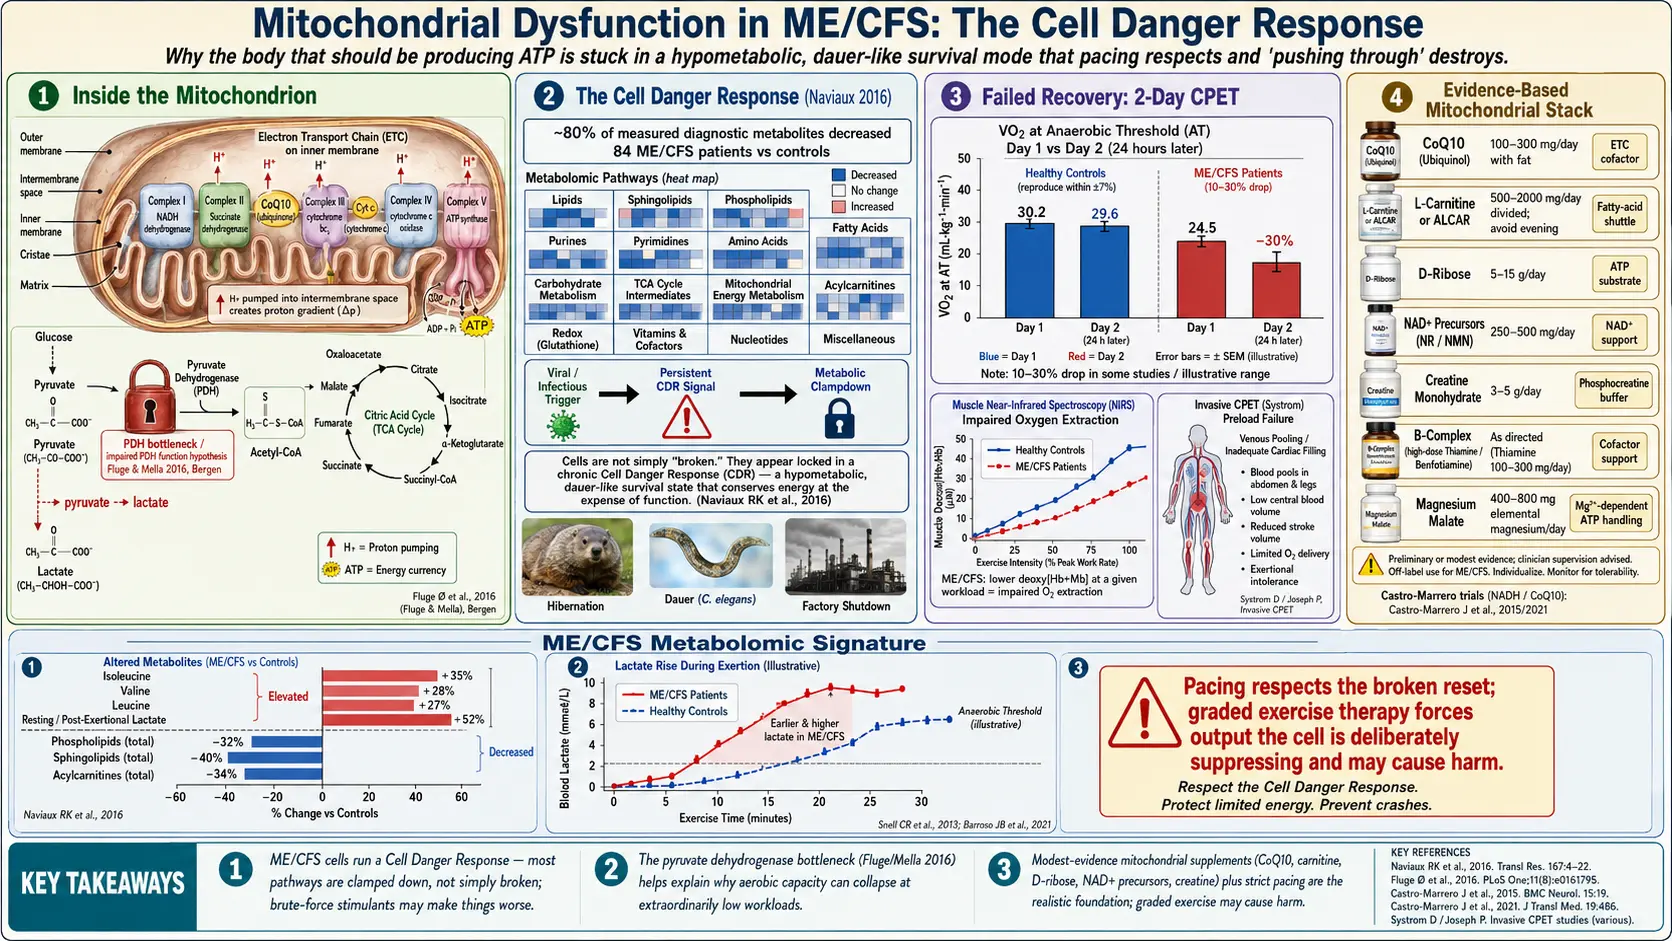
If you have myalgic encephalomyelitis/chronic fatigue syndrome (ME/CFS), you already know something is wrong with how your body makes and uses energy. A shower can wipe you out for a day. A short walk can cost you a week. A good morning can collapse into a bedbound afternoon for reasons that make no sense to anyone who has never lived it. This page explains what researchers have actually measured inside the cells, muscles, and bloodstream of myalgic encephalomyelitis/chronic fatigue syndrome patients — why your energy system is not just "tired" but genuinely broken — and what, if anything, supplements and pacing can do about it.
The short version: your mitochondria (the tiny energy factories inside almost every cell) are not producing, recovering, or switching fuel sources the way healthy mitochondria do. That is not a metaphor. It has been measured in breath tests, blood tests, muscle biopsies, and invasive cardiopulmonary exercise tests. Understanding the biology is the foundation for why pacing works and "push through it" does not.
Table of Contents
- The Core Finding: Cells Fail to Recover After Exertion
- The 2-Day CPET — The Single Most Damning Test
- Naviaux and the Cell Danger Response
- Adenosine Triphosphate Production and the Pyruvate Dehydrogenase Bottleneck
- Amino Acids, Lipids, and Lactate
- Muscle Oxygen Extraction and Preload Failure
- Mitochondrial Supplements — What Actually Has Evidence
- The Pacing Imperative
- Differentiating from Primary Mitochondrial Disease
- Why "Push Through It" Makes It Worse
- Key Research Papers
- PubMed Topic Searches
- Connections
- Featured Videos
The Core Finding: Cells Fail to Recover After Exertion
In a healthy person, mitochondria produce adenosine triphosphate (ATP) (the molecule cells spend as energy) by burning glucose, fat, or amino acids with oxygen. You exert yourself, the system works hard, and within hours to a day the mitochondria are reset and ready to perform again. Fitness improves with use.
In myalgic encephalomyelitis/chronic fatigue syndrome this reset is broken. After exertion — physical, cognitive, emotional, or orthostatic — aerobic capacity drops rather than recovering. The cells appear to switch into a defensive, low-output state that persists for days. That low-output state is the biological footprint of post-exertional malaise (PEM), the hallmark symptom of the illness.
This is not deconditioning. Deconditioned people get better with graded exercise. Myalgic encephalomyelitis/chronic fatigue syndrome patients get worse. It is also not depression — depressed people who exercise usually feel better afterward, not catastrophically worse 24–72 hours later. The timing, reproducibility, and measurability of the response make this a metabolic disorder, not a motivational one.
The 2-Day CPET — The Single Most Damning Test
Researchers at the Workwell Foundation developed a two-day cardiopulmonary exercise test (CPET) that is used as an objective measure of myalgic encephalomyelitis/chronic fatigue syndrome energy dysfunction. Here is how it works:
- Day 1: The patient does a maximal exercise test on a stationary bike while breath gases, heart rate, and workload are measured. Key readings are VO2 max (peak oxygen uptake) and VO2 at the anaerobic/ventilatory threshold (VO2 AT) — the workload at which the body shifts from burning fat and oxygen to burning sugar without enough oxygen.
- Day 2: Exactly 24 hours later, the patient repeats the identical test.
In healthy people (even sedentary and deconditioned ones), Day 2 numbers are nearly identical to Day 1, or slightly better from a warm-up effect. In myalgic encephalomyelitis/chronic fatigue syndrome patients, VO2 at the anaerobic threshold drops, often by 10–30%. Workload at the same heart rate falls. The threshold where the cells are forced to burn sugar anaerobically arrives much sooner.
No other disease reliably reproduces this pattern. Heart failure, chronic obstructive pulmonary disease (COPD), and sedentary controls all perform the same or better on Day 2. The 2-Day CPET is the closest thing myalgic encephalomyelitis/chronic fatigue syndrome has to a biomarker. See the 2-Day CPET and Objective Testing article for the clinical and disability-claim details — including the fact that the test itself can set off a severe PEM crash.
Naviaux and the Cell Danger Response
In 2016, Robert Naviaux and colleagues at UC San Diego published a metabolomic study of 84 people: 45 myalgic encephalomyelitis/chronic fatigue syndrome patients and 39 age- and sex-matched healthy controls. They measured 612 metabolites from 63 biochemical pathways in blood plasma and found a striking and counterintuitive pattern: myalgic encephalomyelitis/chronic fatigue syndrome patients showed a generalized hypometabolic signature. Patients had abnormalities in 20 metabolic pathways, and 80% of the metabolites that told patients apart from controls were lower than normal.
Naviaux described this as a dauer-like state — a biological parallel to the hibernation-like survival mode that roundworms (C. elegans) enter when the environment turns hostile. In that mode, the organism slows nearly every metabolic pathway to survive a stressor. Naviaux's hypothesis is that myalgic encephalomyelitis/chronic fatigue syndrome reflects a Cell Danger Response (CDR) that got triggered — often by a post-viral event, infection, or severe stressor — and never turned off.
Practically, this means the cells are not "failing" in a classical mitochondrial-disease sense of broken machinery. They are acting as if the machinery is fine but the command from above is "do not produce, we are under attack." The metabolic brakes are clamped on. That distinction matters for treatment: brute-force mitochondrial stimulants are unlikely to fix a downshifted cell, and may make things worse by forcing output the cell is deliberately suppressing.
A 2024 deep-phenotyping study of post-infectious myalgic encephalomyelitis/chronic fatigue syndrome at the U.S. National Institutes of Health (NIH) (Walitt and colleagues, Nature Communications) reported immune signs of chronic antigen stimulation (more naive and fewer switched-memory B cells), differences between men and women in blood-cell gene expression and metabolic pathways, and a change in “effort preference” linked to dysfunction of brain regions that may involve the catechol (catecholamine) chemical-messenger pathway.
Adenosine Triphosphate Production and the Pyruvate Dehydrogenase Bottleneck
Two independent research lines converge on a specific bottleneck inside the mitochondrion.
Myhill, Booth, and McLaren-Howard (2009, 2012, 2013) developed an adenosine triphosphate profile test that measures how efficiently white blood cells produce and recycle adenosine triphosphate. Their published results in myalgic encephalomyelitis/chronic fatigue syndrome cohorts consistently showed reduced adenosine triphosphate output and impaired recycling, with the degree of impairment correlating roughly with symptom severity. Their 2009 study compared 71 patients from a private medical practice specialising in chronic fatigue syndrome with 53 healthy controls; only 1 of the 71 patients overlapped the normal range, and the authors present the test as a guide to choosing dietary supplements, drugs and detoxification. The test is controversial — it is not widely replicated outside their group — but the direction of the finding matches the rest of the literature.
Øystein Fluge and Olav Mella (2016) in Bergen, Norway published a seminal paper on 200 myalgic encephalomyelitis/chronic fatigue syndrome patients and 102 healthy people showing that patients have lower blood levels of the amino acids that fuel the citric acid cycle (mainly in women), while simultaneously appearing to have impaired function of the pyruvate dehydrogenase (PDH) complex. PDH is the gatekeeper enzyme that converts pyruvate (from glucose) into acetyl-CoA, the fuel that enters the citric acid cycle and powers oxidative adenosine triphosphate production.
When PDH is throttled, the cell cannot burn sugar aerobically. It must either burn alternative fuels (amino acids, ketones, fats) or dump pyruvate into lactate and shunt energy anaerobically — which is wasteful and produces an acid load. In white blood cells from both sexes, the study found increased gene activity (mRNA expression) of PDH kinases 1, 2 and 4 — the enzymes that switch PDH off — along with sirtuin 4 and PPARδ. Muscle precursor cells (myoblasts) grown in serum from severely ill patients increased their mitochondrial respiration and released excessive lactate. Men with the illness had higher blood 3-methylhistidine, a marker of the body breaking down its own protein. The amino-acid changes were not explained by symptom severity, illness duration, age, body mass index or activity level. Fluge and Mella proposed that an autoimmune process, or metabolic signalling, lies behind this PDH switch-off. Their group has since explored immunomodulatory treatments targeting this axis.
The practical takeaway: the bottleneck is at the entry to the aerobic engine, not the engine itself. That is why myalgic encephalomyelitis/chronic fatigue syndrome patients often hit their anaerobic threshold at extraordinarily low workloads — sometimes below the energy cost of simply standing up.
Amino Acids, Lipids, and Lactate
Metabolomic studies (Naviaux, Fluge/Mella, Germain, Armstrong, and others) have consistently found:
- Altered amino acid profiles — particularly those that can bypass PDH to feed the citric acid cycle directly (isoleucine, valine, leucine, glutamate). Patients appear to be compensating by burning amino acids for energy.
- Reduced phospholipids and sphingolipids — structural fats that make up cell and mitochondrial membranes. This echoes the "dauer" picture of a cell in shutdown.
- Elevated resting or post-exertional lactate — not dramatic enough to trigger a mitochondrial-disease diagnosis, but consistently above control levels, and rising abnormally fast during even mild exertion.
- Reduced acylcarnitines — markers that track fatty-acid transport into the mitochondrion.
None of these findings alone is specific enough to diagnose myalgic encephalomyelitis/chronic fatigue syndrome. But the pattern — a cell running on the wrong fuels, dumping lactate early, and rationing membrane lipids — is reproducible across labs.
Muscle Oxygen Extraction and Preload Failure
Energy is not just about cellular machinery. It is also about delivery. Two vascular findings complicate the pure mitochondrial story:
Impaired oxygen extraction at the muscle level. Studies using near-infrared spectroscopy and arterial/venous blood sampling have shown that myalgic encephalomyelitis/chronic fatigue syndrome patients extract less oxygen from their blood during exercise than controls. The cells are not pulling oxygen out efficiently — possibly because the mitochondria that would consume it are downregulated, and possibly because microvascular blood flow is disordered.
Preload failure on invasive CPET. David Systrom's group at Brigham and Women's Hospital has run invasive cardiopulmonary exercise tests (with pulmonary-artery catheters) on hundreds of myalgic encephalomyelitis/chronic fatigue syndrome and orthostatic-intolerance patients. The dominant finding is preload failure — the heart is not being adequately filled with blood during exercise, often because blood is pooling in the abdomen and legs due to autonomic dysfunction. The heart pumps what it receives, so cardiac output caps out at low workloads even with a structurally normal heart.
This overlaps heavily with postural orthostatic tachycardia syndrome (POTS) and small-fiber neuropathy. Many patients have both a cellular (mitochondrial) and a vascular (preload) limit to their energy envelope. Treating one without the other rarely works.
Not simply inactivity. A 2026 study in Nature Communications (Charlton and colleagues) compared exercise tests and muscle samples from long COVID and myalgic encephalomyelitis/chronic fatigue syndrome patients with those of healthy volunteers after 60 days of strict bed rest, and with healthy age- and sex-matched controls. Bed rest shrank the healthy volunteers’ muscles without changing their fibre types. Both patient groups had more glycolytic (sugar-burning) muscle fibres, and myalgic encephalomyelitis/chronic fatigue syndrome patients showed shrinking of type I (endurance) fibres. Because the patients’ muscle differed from that of healthy people after bed rest, the authors concluded that physical inactivity alone cannot explain the lower exercise capacity in these illnesses.
Mitochondrial Supplements — What Actually Has Evidence
Online myalgic encephalomyelitis/chronic fatigue syndrome communities circulate long supplement stacks. Most of the evidence is modest — small trials, open-label studies, anecdote — but the biological rationale is plausible and the risk is generally low. The doses below are the ranges described in patient communities and practitioner protocols; trial doses are given where a trial exists. A realistic honest summary:
- Coenzyme Q10 (CoQ10) / ubiquinol, 100–300 mg/day. Electron-transport-chain cofactor. An 8-week randomized, placebo-controlled trial in 73 patients (Castro-Marrero and colleagues, 2015) gave coenzyme Q10 200 mg/day plus reduced nicotinamide adenine dinucleotide (NADH) 20 mg/day; fatigue impact scores fell compared with placebo, and blood cells showed higher NAD+/NADH, coenzyme Q10, adenosine triphosphate and citrate synthase. Ubiquinol (the reduced form) is better absorbed than standard ubiquinone. It is fat-soluble, and practitioners describe taking it with a meal that contains fat.
- L-carnitine or acetyl-L-carnitine (ALCAR), 500–2000 mg/day. Carries fatty acids into the mitochondrion. Small studies have shown benefit; acetyl-L-carnitine crosses into the brain and may help cognitive symptoms. Practitioners describe divided morning and midday doses, as some people report that evening doses disturb sleep.
- D-ribose, 5–15 g/day (divided). A sugar that feeds directly into adenosine triphosphate synthesis. A 41-patient open-label, uncontrolled pilot study in chronic fatigue syndrome and fibromyalgia (Teitelbaum and colleagues, 2006) gave 5 g three times a day; about 66% of patients reported significant improvement, with an average 45% rise in energy scores. Modest evidence; it was well tolerated in that study, it tastes sweet, and some patients report it disrupts blood sugar.
- Nicotinamide adenine dinucleotide (NAD+) precursors — nicotinamide riboside (NR) or nicotinamide mononucleotide (NMN), 250–500 mg/day. Nicotinamide adenine dinucleotide is essential for the citric acid cycle. The evidence in myalgic encephalomyelitis/chronic fatigue syndrome specifically is limited but mechanistically reasonable. Expensive.
- Creatine monohydrate, 3–5 g/day. Buffers adenosine triphosphate in muscle and brain. Cheap, extensively studied in other contexts, now being trialed in long-term fatigue syndromes for cognitive benefit. Safe long-term in typical doses.
- B-complex (especially thiamine/B1, riboflavin/B2, niacinamide/B3). These are cofactors throughout energy metabolism. High-dose thiamine (e.g., benfotiamine 300 mg) has a small but intriguing evidence base. Inexpensive.
- Magnesium malate, 400–800 mg elemental magnesium/day (divided). Magnesium is a cofactor for adenosine triphosphate; malate feeds the citric acid cycle. People with overlapping fibromyalgia pain describe using it. The Institute of Medicine’s tolerable upper intake level for magnesium from supplements is 350 mg/day for adults and children over 8, so this range is above it; diarrhoea is the main adverse effect of high supplemental doses, and people with impaired kidney function are at greater risk of magnesium toxicity.
Honest expectations: patients who respond describe a roughly 10–25% improvement in baseline function on a well-chosen stack. Nobody is cured by supplements. Patients and practitioners describe adding them one at a time over 2–4 weeks each, so that the effect of each one — helpful, neutral or harmful — can be told apart, and dropping anything that shows no benefit after 8 weeks.
The Pacing Imperative
Given the biology above, pacing is not optional lifestyle advice — it is the single intervention with the strongest evidence base and the clearest mechanism.
The logic is simple. Your anaerobic threshold is abnormally low. Once you cross it, the cell switches to inefficient anaerobic metabolism, pumps out lactate, triggers the cell danger response, and drives a PEM crash that can last days to weeks. Each crash may cause an accumulating downward step in baseline function. Avoiding crashes is therefore a neuroprotective and mitochondrial-protective strategy, not an indulgence.
Pacing, as clinicians and patients describe it, means staying below the anaerobic threshold as much as possible. Tools include heart-rate monitoring (many clinicians use a simple ceiling around 60% of [220 − age] as a starting point), activity logs, rest before and after any demand, and aggressive use of recumbent postures. The aim is to stay inside the energy envelope and slowly expand it over months, rather than pushing it.
Differentiating from Primary Mitochondrial Disease
A common question: is myalgic encephalomyelitis/chronic fatigue syndrome actually an undiagnosed primary mitochondrial disease (a classical genetic disorder like MELAS or mitochondrial myopathy)? Almost always, no.
Primary mitochondrial diseases usually show:
- Onset in childhood or adolescence (though adult-onset forms exist).
- Multi-organ involvement with hard structural findings — deafness, stroke-like episodes, optic nerve damage, cardiomyopathy, diabetes, ptosis, external ophthalmoplegia.
- Persistently and markedly elevated lactate (often 3× upper limit of normal) with high lactate/pyruvate ratio.
- Diagnostic findings on muscle biopsy (ragged red fibers, COX-negative fibers, reduced respiratory-chain enzyme activity) or on mtDNA sequencing (specific heteroplasmic mutations).
- A family history that follows maternal inheritance.
Myalgic encephalomyelitis/chronic fatigue syndrome does not typically show these features. A muscle biopsy and mitochondrial genetic testing are usually not part of the standard workup. They are generally pursued only when there is a clinical signal suggesting primary mitochondrial disease — persistent very high lactate, neurological deficits, cardiomyopathy, hearing loss, or a strong maternal family history.
The better framing: myalgic encephalomyelitis/chronic fatigue syndrome is a functional mitochondrial and metabolic disorder — the machinery is intact but the regulation is off — rather than a structural one.
Why "Push Through It" Makes It Worse
For decades, patients were told that myalgic encephalomyelitis/chronic fatigue syndrome was essentially deconditioning with a psychological overlay, and that graded exercise therapy (GET) would fix it. The 2011 PACE trial promoted this view. It has since been thoroughly critiqued on methodological grounds, and in 2021 the UK's NICE guideline was rewritten to explicitly remove GET as a recommended therapy for myalgic encephalomyelitis/chronic fatigue syndrome. The U.S. Centers for Disease Control and Prevention (CDC) has made a similar move. The Institute of Medicine and the Mayo Clinic have made similar moves.
The biology explains why. When you push past your anaerobic threshold:
- You force the cell into inefficient anaerobic metabolism that it cannot sustain.
- Lactate and metabolic byproducts rise.
- The cell danger response is reinforced rather than resolved.
- PEM begins, often 12–72 hours later, and persists for days.
- Repeated crashes appear to lower the baseline over time. Some patients progress from mild to severe or very severe myalgic encephalomyelitis (ME) after a series of pushed-through episodes.
That is not theoretical. It is the common arc described by patient registries and long-term observational cohorts. On this biology, what matters most for the mitochondria in myalgic encephalomyelitis/chronic fatigue syndrome is not a supplement. It is staying within the energy envelope, avoiding crashes, and giving the cell the environment it is signalling it needs.
Key Research Papers
- Naviaux RK, et al. Metabolic features of chronic fatigue syndrome. PNAS. 2016. — The hypometabolic/dauer signature paper. — doi:10.1073/pnas.1607571113
- Fluge Ø, Mella O, et al. Metabolic profiling indicates impaired pyruvate dehydrogenase function in myalgic encephalopathy/chronic fatigue syndrome. JCI Insight. 2016. — The PDH-bottleneck paper. — doi:10.1172/jci.insight.89376
- Myhill S, Booth NE, McLaren-Howard J. Chronic fatigue syndrome and mitochondrial dysfunction. Int J Clin Exp Med. 2009. — The ATP profile cohort. — PubMed PMID: 19436827
- VanNess JM, Snell CR, Stevens SR. Diminished cardiopulmonary capacity during post-exertional malaise. Journal of Chronic Fatigue Syndrome. 2007;14(2):77–85. — 2-day CPET methodology and findings. — doi:10.1300/J092v14n02_07
- Oldham WM, Lewis GD, Opotowsky AR, Waxman AB, Systrom DM. Unexplained Exertional Dyspnea Caused by Low Ventricular Filling Pressures: Results from Clinical Invasive Cardiopulmonary Exercise Testing. Pulm Circ. 2016;6(1):55–62. — Preload failure in unexplained exertional intolerance. — doi:10.1086/685054
- Castro-Marrero J, Cordero MD, Segundo MJ, et al. Does oral coenzyme Q10 plus NADH supplementation improve fatigue and biochemical parameters in chronic fatigue syndrome? Antioxid Redox Signal. 2015;22(8):679–685. — doi:10.1089/ars.2014.6181
- Teitelbaum JE, Johnson C, St Cyr J. The use of D-ribose in chronic fatigue syndrome and fibromyalgia: a pilot study. J Altern Complement Med. 2006;12(9):857–862. — PubMed PMID: 17109576
- Walitt B, Singh K, LaMunion SR, et al. Deep phenotyping of post-infectious myalgic encephalomyelitis/chronic fatigue syndrome. Nat Commun. 2024;15(1):907. — PubMed PMID: 38383456
- Charlton BT, Slaghekke A, Appelman B, et al. Skeletal muscle properties in long COVID and ME/CFS differ from those induced by bed rest. Nat Commun. 2026;17(1):9125. — PubMed PMID: 42649155
- Institute of Medicine. Dietary Reference Intakes for Calcium, Phosphorus, Magnesium, Vitamin D, and Fluoride. Washington, DC: National Academies Press; 1997. — Chapter 6, Magnesium: tolerable upper intake level. — doi:10.17226/5776
PubMed Topic Searches
For further reading, these PubMed searches return current peer-reviewed work on myalgic encephalomyelitis/chronic fatigue syndrome energy metabolism:
Connections
- Neurology
- Myalgic Encephalomyelitis/Chronic Fatigue Syndrome Overview
- Post-Viral Triggers: Epstein-Barr Virus and Others
- Post-Exertional Malaise
- 2-Day CPET and Objective Testing
- Pacing and the Energy Envelope
- Severe and Very Severe Myalgic Encephalomyelitis
- Orthostatic Intolerance in Myalgic Encephalomyelitis/Chronic Fatigue Syndrome
- Myalgic Encephalomyelitis/Chronic Fatigue Syndrome Diagnostic Criteria
- Low Dose Naltrexone, Abilify and Experimental Therapies
- Postural Orthostatic Tachycardia Syndrome
- Mast Cell Activation Syndrome
- Fibromyalgia
- Fatigue
- Magnesium
- Creatine
- Lyme Disease