Pacing and the Energy Envelope in Myalgic Encephalomyelitis/Chronic Fatigue Syndrome (ME/CFS)
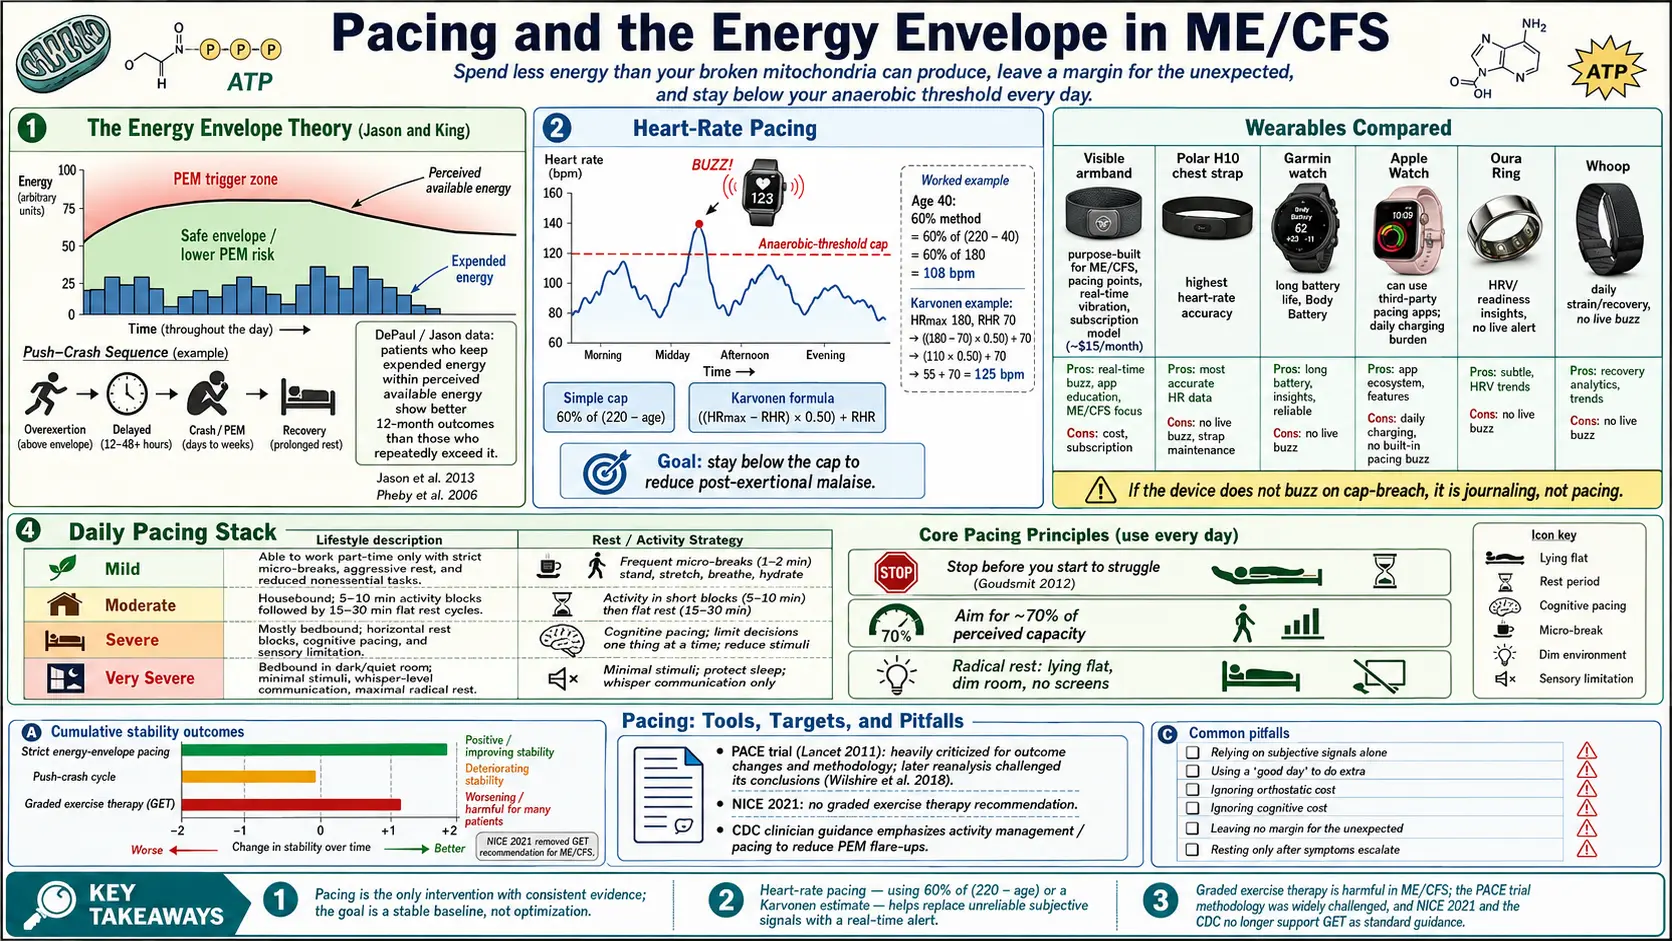
Table of Contents
- What Pacing Actually Means
- The Energy Envelope Theory (Jason & King)
- How Heart-Rate Pacing Works
- How a Personal Heart-Rate Cap Is Found
- Types of Wearable Heart-Rate Devices
- The “Stop Before You Start to Struggle” Rule
- Aggressive Rest and Horizontal vs Upright
- Tracking Payback
- Daily Schedules Patients Describe by Severity
- Cognitive and Social Pacing
- Medication Support for Pacing
- What Patient Surveys and NICE Report About Graded Exercise Therapy
- The PACE Trial Controversy in Brief
- Common Pitfalls
- What the Research on Pacing Shows So Far
- Key Research Papers
- Connections
- Featured Videos
What Pacing Actually Means
Pacing is the self-management approach patients with myalgic encephalomyelitis/chronic fatigue syndrome (ME/CFS) most often report as helpful: in large patient surveys it had the highest reported benefit of any approach (44%–82% of respondents) and the lowest rate of reported harm (Geraghty 2019). A 2023 scoping review of 17 pacing studies found that eleven reported benefits, four reported no effect and two reported a detrimental effect, and judged the studies of poor to fair quality (Sanal-Hayes 2023). Patients describe pacing not as "listening to the body" but as a concrete, measurable practice: spending less energy in a day than the body can produce, and leaving a margin for the unexpected. Going past that margin brings on post-exertional malaise (PEM) — the hallmark crash that patients describe lasting 48 hours, two weeks, or permanently lowering their baseline.
Patients often compare daily energy to a bank account that does not refill reliably overnight. A healthy person's account tops up to full every morning. In myalgic encephalomyelitis/chronic fatigue syndrome, overnight recovery is partial and unpredictable, and an overdraft is costly. In this picture pacing is the household budget that keeps the account out of overdraft. Pushing through is what patients describe as the trap; the aim of pacing is to stay inside the envelope so the baseline stabilizes and, patients report, may slowly expand over months to years.
The Energy Envelope Theory (Jason & King)
The formal framework behind pacing was developed by Leonard Jason and colleagues at DePaul University in the 1990s and refined through the 2000s and 2010s. Their energy envelope theory (Jason 2008; Jason 2013) proposes that people with myalgic encephalomyelitis/chronic fatigue syndrome have a fixed daily envelope of perceived available energy and a corresponding level of expended energy. Symptoms stabilize or improve when expended energy stays at or below perceived available energy. Symptoms worsen whenever expended energy exceeds it.
In a 2008 study the group measured a daily "energy quotient" (expended energy divided by perceived energy); spending beyond perceived energy went with more fatigue, pain, depression, anxiety and disability and a lower quality of life (Jason 2008). In a 2011 study of 44 adults, those who were within their energy envelope before treatment improved more in physical functioning and fatigue than those outside it (Brown 2011). Pacing is not a cure, and the researchers note that little formal research has been done on the theory, which rests largely on support from the patient community (Jason 2008).
In this framework the envelope is what the body can actually do today — not what a person expects of themselves, not what they could do last year, and not what others expect. Patients describe it as set by physiology, not willpower.
How Heart-Rate Pacing Works
Patients report that pacing by feel alone ("I feel okay, I'll keep going") often fails, because myalgic encephalomyelitis/chronic fatigue syndrome blunts the normal warning signals: by the time tiredness is felt, the limit has often already been passed and a crash is on its way. Heart-rate pacing replaces those signals with an objective number that can be watched in real time.
The core idea: myalgic encephalomyelitis/chronic fatigue syndrome patients hit their anaerobic threshold (AT) — the point at which the body switches from aerobic to anaerobic metabolism — at very low workloads, often at heart rates a healthy person would consider resting. Practitioners of heart-rate pacing hold that crossing AT is what triggers PEM, and that keeping the heart rate below AT for most of the day lowers the chance of a crash.
Two common ways patients estimate AT without a lab test:
- 60% of predicted maximum heart rate (HRmax). The formula is HRmax = 220 − age, multiplied by 0.60. A 40-year-old's cap would be (220 − 40) × 0.60 = 108 bpm. Simple and rough; patients describe it as a conservative starting point.
- Karvonen AT estimate. Uses the person's resting heart rate (RHR) for a more personalized cap: AT ≈ ((HRmax − RHR) × 0.50) + RHR. For a 40-year-old with a RHR of 70: ((180 − 70) × 0.50) + 70 = 125 bpm. The Karvonen method tends to run slightly higher than the flat-60% rule.
Patients commonly start with the lower of the two, so that the alarm trips before AT is exceeded, not after.
How a Personal Heart-Rate Cap Is Found
The gold standard is a 2-day CPET (cardiopulmonary exercise test), where a maximal test is done one day and repeated 24 hours later, and the lab measures the actual AT on day two — which in myalgic encephalomyelitis/chronic fatigue syndrome is typically 10–30% lower than day one. This is discussed in detail in the 2-Day CPET article. A CPET gives a hard number, but it is expensive ($2,000–$4,000), not widely available, and the test itself can trigger a significant PEM crash. Some patients undergo it for the diagnostic documentation; for others the crash risk rules it out.
Most people find their cap by trial and error. The steps patients describe:
- A starting cap from the formula (60% HRmax).
- Two weeks of wearing a continuous heart-rate (HR) monitor, noting every time the cap is breached.
- A note of every PEM episode and the activity that preceded it by 24–72 hours (PEM is famously delayed).
- Lowering the cap by 5–10 bpm when crashes keep coming despite "staying within" it.
- Keeping a cap that has held stable for several weeks; patients describe stability, not optimization, as the goal, and do not raise it.
Patients report that the cap moves. It often drops during a viral illness, after stressful events, in hot weather, or around menstruation. Some patients run two caps: a "good day" cap and a "bad day" cap 10–15 bpm lower.
Types of Wearable Heart-Rate Devices
Heart-rate pacing depends on a device that gives an alert in real time when the cap is breached; patients point out that a daily summary comes too late, after the activity is over. The main device types:
- A pacing app paired with a chest or arm heart-rate sensor — some are built specifically for myalgic encephalomyelitis/chronic fatigue syndrome, Long COVID, and postural orthostatic tachycardia syndrome (POTS), with continuous optical heart rate, an in-app points system for daily energy, a morning heart-rate-variability (HRV) readiness score, and vibration alerts at a user-set heart-rate cap, all organized around energy envelope ideas. Some charge a monthly subscription, which patients describe as a real barrier.
- A chest-strap heart-rate monitor — chest straps measure the heart's electrical signal and are generally more accurate than wrist sensors. Paired with a watch or with heart-rate / heart-rate-variability apps on a phone, they give close-to-medical readings. The strap is worn under clothing, which some patients find uncomfortable during bed rest.
- Smartwatches — many offer a built-in high-heart-rate alert that vibrates at a set threshold, customizable zones, and, on some models, battery life of days to weeks. Some show a watch's built-in energy score, which patients treat as a rough energy proxy. Others support third-party pacing apps but need daily charging, which then has to fit into the day.
- Smart rings — strong for overnight HRV and readiness, weaker for real-time alerts (no display, no buzz). Patients use them alongside another device for live pacing.
- Screenless fitness bands — daily "strain" scores and HRV trends but no real-time buzz for exceeding a cap, so they complement rather than replace a watch or armband.
The feature patients name as most important is a vibration alert when the cap is crossed; a device that does not buzz, as patients put it, records the day rather than paces it.
The “Stop Before You Start to Struggle” Rule
This phrase, popularized by Ellen Goudsmit (2012) in her pacing research, is one of the rules patients with myalgic encephalomyelitis/chronic fatigue syndrome cite most often. Patients report that by the time strain is felt — heavy legs, brain fog thickening, hands shaking on the cup — the line has already been crossed. The body's warning system in myalgic encephalomyelitis/chronic fatigue syndrome is delayed and unreliable.
How patients put the rule into practice:
- Stopping a 20-minute task at 10 minutes to rest.
- Breaking activity into blocks: 5–10 minutes of activity, 15–30 minutes flat rest, repeated.
- Lying down as soon as the heart-rate alert buzzes, without finishing the sentence or the dishwasher; patients describe the next 30 seconds as mattering more than the task.
- Planning to underachieve: aiming for about 70% of what seems possible, with the other 30% as the margin that keeps them stable.
Aggressive Rest and Horizontal vs Upright
"Rest" for a healthy person means sitting on the couch watching TV. "Rest" for someone with myalgic encephalomyelitis/chronic fatigue syndrome usually means lying flat in a dim, quiet room with no screens. This is sometimes called aggressive rest therapy (ART) and is particularly important for patients with any overlap with postural orthostatic tachycardia syndrome or other orthostatic intolerance.
Why horizontal matters: upright posture itself is work. The heart has to pump blood against gravity to the brain, and in myalgic encephalomyelitis/chronic fatigue syndrome plus postural orthostatic tachycardia syndrome that is enough to push HR above AT just from sitting at a desk. Lying flat removes the orthostatic load. Symptoms that feel relentless while sitting frequently fade within 10–20 minutes of lying down.
A hierarchy of rest, from most to least restorative:
- Flat supine, dark room, no input (eyes closed or covered, earplugs). The reset button.
- Flat supine, dim room, audio only (music, podcast, audiobook at low volume).
- Reclined (45° or less), dim room. Acceptable maintenance rest.
- Upright sitting, screen on. Patients count this as activity within the envelope, not rest.
Add-ons patients use to deepen rest: an eye mask, a weighted blanket (light weight only — heavy blankets raise HR), compression garments for orthostatic support while transitioning upright (see the postural orthostatic tachycardia syndrome compression program), and a cool room (heat tolerance is usually poor).
Tracking Payback
"Payback" is the delayed cost of today's activity — the PEM crash that arrives 24–72 hours later. Because the delay is long and variable, people routinely blame today's crash on today's activity and miss the real culprit from two days ago.
Patients report that a minimal tracking log kept for 4–8 weeks usually reveals the pattern. A typical daily log records:
- Activities (with duration) and any HR breaches.
- Upright minutes total.
- Symptom score 0–10 (fatigue, brain fog, pain, sleep quality).
- Any notable triggers: poor sleep, stress, heat, menstrual phase, alcohol, infection.
Patients keep these logs in symptom-tracking apps, in a pacing app paired with a heart-rate sensor, or in a simple paper diary. After a few weeks, patients describe seeing that a Wednesday crash tracks back to Monday's grocery run, not Tuesday's nap, and they adjust the envelope accordingly.
Daily Schedules Patients Describe by Severity
These are examples of the day patients describe at each severity level, not prescriptions; every envelope is different.
Mild (50–70% function)
- Wake, eat a small breakfast sitting or reclined, 20 min flat rest.
- One block of desk work or light activity, 60–90 min, HR-monitored.
- 30–45 min flat rest.
- Short errand or light household task, 30–45 min.
- Lunch + 30 min flat rest.
- Second activity block, 60–90 min.
- Flat rest before dinner.
- Quiet evening, screen time capped, lights down by 10pm.
Moderate (25–50% function, mostly housebound)
- Wake, breakfast in bed or reclined, 30–60 min flat rest.
- One 20–30 min activity block (shower OR meal prep OR one phone call — one, not all).
- 60–90 min flat rest, dark and quiet.
- Another small activity block in the afternoon.
- Most of the day is rest with short activity islands, not the reverse.
- Grocery delivery, disposable plates on bad days, shower seat in the shower.
Severe (under 25% function, mostly bedbound)
- Most of the day flat in a dark, quiet room.
- Meals delivered to the bedside. A bedside commode may replace trips to the bathroom.
- Social contact limited to minutes per day, at low volume.
- Screens off or heavily limited (blue-light glasses, lowest brightness).
- Caregiving support for washing, feeding, and medication.
- More in the severe/very severe myalgic encephalomyelitis (ME) article.
Cognitive and Social Pacing
Brains run on energy too. In myalgic encephalomyelitis/chronic fatigue syndrome, cognitive exertion triggers PEM just as reliably as physical exertion, and people often discover this the hard way after a long work call, a tax return, or a family video chat. Concentration, reading, driving, and emotional conversations all draw from the same envelope.
Cognitive pacing as patients describe it:
- Chunking. 15–25 minutes of focused mental work, then 15–30 minutes flat rest with eyes closed.
- Limiting input. One stimulus at a time: no music while reading, no multi-tab web browsing, no podcast while cooking.
- Scheduling hard cognitive tasks for the best time of day, usually mid-morning.
- Budgeting conversations. A 30-minute phone call with a parent is not free; patients count it.
Social pacing is its own category. Social interaction in myalgic encephalomyelitis/chronic fatigue syndrome is cognitively and emotionally expensive, and the emotional cost is often larger than the physical. Many patients limit themselves to one social contact per day, with most contacts by text or short voice note rather than live video. Patients describe saying no as part of managing the illness, not rudeness.
Medication Support for Pacing
Medications do not replace pacing, but clinicians who treat the condition describe a few that can lower the heart-rate cost of daily life and make pacing more practical. The doses below are the ranges reported in that use.
- Low-dose beta blockers (propranolol 10–40 mg, or atenolol) — lower resting and exertional HR, particularly useful for patients with postural orthostatic tachycardia syndrome overlap. Can shift what was a 125-bpm activity into a 95-bpm activity, expanding the envelope without adding workload. Beta blockers also lower blood pressure, which matters for people whose blood pressure is already low.
- Ivabradine — a heart-rate-lowering drug that acts on the sinus node without affecting blood pressure. Increasingly used in postural orthostatic tachycardia syndrome and myalgic encephalomyelitis/chronic fatigue syndrome where beta blockers are poorly tolerated.
- Salt and fluid loading (3–10 g sodium/day, 2–3 L fluid) — expands blood volume, reduces HR spikes on standing, reduces how much of the envelope upright posture uses up.
- Fludrocortisone (0.1–0.2 mg) — a steroid that retains sodium and expands plasma volume; described as second-line for orthostatic overlap. Its label notes that it raises blood pressure and increases potassium loss in the urine.
- Midodrine — raises blood pressure via vasoconstriction; used where low blood pressure (BP) drives the HR climb. Its label warns that it can cause a marked rise in blood pressure while lying down (supine hypertension).
- Low-Dose Naltrexone — 1.5–4.5 mg at bedtime. Anti-inflammatory and neuromodulatory effects; a subset of patients report reduced PEM severity and slightly larger envelopes. More in the low dose naltrexone (LDN) and experimental therapies article.
None of these are cures. All except salt and fluid are prescription drugs, and each one changes heart rate, blood pressure or blood volume, the same measures that pacing tracks.
What Patient Surveys and NICE Report About Graded Exercise Therapy
Graded Exercise Therapy (GET) is the structured program of gradually increasing exercise duration and intensity that, for decades, was recommended to myalgic encephalomyelitis/chronic fatigue syndrome patients by mainstream medicine. It is the opposite of pacing: it rests on the assumption that fatigue is driven by deconditioning, an assumption patient groups and the 2021 NICE guideline reject, and it raises activity beyond the envelope.
A large patient survey (1,428 respondents), compared with other patient surveys covering 16,665 people, found that graded exercise therapy brought large negative responses in 54%–74% of patients, cognitive behavioural therapy helped a small share (8%–35%), and pacing had the highest reported benefit (44%–82%) and the lowest negative response rate (Geraghty 2019). Many patients date a permanent drop in baseline to a GET program.
The Cochrane review of exercise therapy (8 randomized trials, 1,518 people) found that exercise probably reduced fatigue at the end of treatment compared with usual care, but rated the evidence on serious adverse reactions as "very low" certainty. Its searches ran only to May 2014, and every trial diagnosed patients with the 1994 Centers for Disease Control and Prevention criteria or the Oxford criteria, or both; the authors note that patients diagnosed with other criteria may respond differently. A December 2024 editorial note states that the planned update of the review with patient involvement "has now been discontinued" (Larun 2024).
In October 2021, the UK's NICE guideline NG206 for myalgic encephalomyelitis/chronic fatigue syndrome explicitly removed GET as a recommended treatment and warned against "any programme that uses fixed incremental increases in physical activity or exercise." The guideline also rejected Cognitive Behavioural Therapy as a curative treatment (while permitting it as a supportive tool for living with a chronic illness). The guideline is available at nice.org.uk/guidance/ng206.
The U.S. Centers for Disease Control and Prevention (CDC) removed GET and cognitive behavioral therapy (CBT) from its myalgic encephalomyelitis/chronic fatigue syndrome information pages in 2017. The 2015 report of the Institute of Medicine (IOM, now the National Academy of Medicine) that defined Systemic Exertion Intolerance Disease (SEID) centered PEM as the core feature — which patient groups argue makes any therapy that provokes PEM a poor fit for the illness.
A recommendation of GET for myalgic encephalomyelitis/chronic fatigue syndrome in 2026 follows guidance that NICE withdrew in 2021; the NICE guideline now describes an energy-management (pacing) approach instead.
The PACE Trial Controversy in Brief
The PACE trial (Lancet 2011) was the headline study behind the GET/CBT recommendation. It reported that GET and cognitive behavioral therapy were moderately effective for "chronic fatigue." After years of patient advocacy and a freedom-of-information lawsuit, the raw data were released in 2016 and re-analyzed by independent researchers.
Critics reported that the trial had lowered its thresholds for "recovery" and "improvement" during the study, so that a patient could qualify as "recovered" while still meeting the original entry criteria for disabling fatigue. A 2018 re-analysis using the original protocol-specified procedures (Wilshire 2018) found a significant effect of treatment group on the protocol's primary outcome, but the CBT and GET groups "did not significantly outperform the Control group after correcting for the number of comparisons specified in the trial protocol"; rates of recovery were "consistently low and not significantly different across treatment groups"; significant effects on secondary measures were almost entirely confined to self-report measures; and these effects "did not endure beyond two years." The trial's population was also heterogeneous, relying on the broad Oxford criteria that do not require PEM — meaning many participants likely did not have myalgic encephalomyelitis/chronic fatigue syndrome at all.
The re-analysis authors concluded that the modest effects on self-report measures "do not exceed what could be reasonably accounted for by participant reporting biases" (Wilshire 2018). Many in the myalgic encephalomyelitis/chronic fatigue syndrome research and patient community now cite PACE as a cautionary tale in outcome-switching and criterion creep, and its critics count these re-analyses among the evidence behind the 2021 NICE reversal.
Common Pitfalls
- The "good day" trap. Feeling unusually well, a patient cleans the kitchen, answers three emails and goes for a short walk; payback hits on Wednesday. Patients describe treating good days as days for rest, not catch-up.
- The gradual creep. Adding five minutes of activity a week can mean, after two months, 40 minutes more per day than the envelope allows — and a crash.
- Ignoring cognitive load. Physical activity is paced, but a five-hour tax session brings a crash anyway.
- Unpaced showers. A hot shower can put HR over AT for 10–15 minutes straight. Patients use a shower seat, lukewarm water and short showers, and some wash in sections on different days.
- Unpaced meals. Digestion itself costs energy and drops blood pressure. Patients describe eating smaller meals more often, reclined if needed.
- Refusing to use aids. Mobility aids (wheelchair for airport travel, shower seat, grabber tools) are envelope extenders, not defeats.
What the Research on Pacing Shows So Far
The first scoping review of pacing studies (Sanal-Hayes 2023) screened 177 titles and abstracts and included 17 studies, only three of them randomized controlled trials; the rest were an uncontrolled trial, a case series and observational studies. It found that the literature has no agreed definition of pacing, though it typically means regulating activity to avoid post-exertional malaise, and that studies mostly delivered pacing through education sessions and activity diaries. Eleven studies reported benefits, four no effect and two a detrimental effect compared with the control group. Because the designs, outcome measures and quality (poor to fair) varied so much, the authors judged the literature "insufficient to inform treatment practises," and called for randomized trials of objectively measured, digital pacing over longer periods.
Key Research Papers
- Jason L, Muldowney K, Torres-Harding S. The Energy Envelope Theory and myalgic encephalomyelitis/chronic fatigue syndrome. AAOHN J. 2008;56(5):189–195. — PubMed PMID: 18578185
- Jason LA, Brown M, Brown A, Evans M, Flores S, Grant-Holler E, Sunnquist M. Energy Conservation/Envelope Theory Interventions to Help Patients with Myalgic Encephalomyelitis/Chronic Fatigue Syndrome. Fatigue. 2013;1(1-2):27–42. — PubMed PMID: 23504301
- Brown M, Khorana N, Jason LA. The role of changes in activity as a function of perceived available and expended energy in nonpharmacological treatment outcomes for ME/CFS. J Clin Psychol. 2011;67(3):253–260. — PubMed PMID: 21254053
- Geraghty K, Hann M, Kurtev S. Myalgic encephalomyelitis/chronic fatigue syndrome patients' reports of symptom changes following cognitive behavioural therapy, graded exercise therapy and pacing treatments: Analysis of a primary survey compared with secondary surveys. J Health Psychol. 2019;24(10):1318–1333. — PubMed PMID: 28847166
- Sanal-Hayes NEM, Mclaughlin M, Hayes LD, Mair JL, Ormerod J, Carless D, Hilliard N, Meach R, Ingram J, Sculthorpe NF. A scoping review of 'Pacing' for management of Myalgic Encephalomyelitis/Chronic Fatigue Syndrome (ME/CFS): lessons learned for the long COVID pandemic. J Transl Med. 2023;21(1):720. — PubMed PMID: 37838675
- Larun L, Brurberg KG, Odgaard-Jensen J, Price JR. Exercise therapy for chronic fatigue syndrome. Cochrane Database Syst Rev. 2024;12(12):CD003200. — PubMed PMID: 39697147
- Wilshire CE, Kindlon T, Courtney R, Matthees A, Tuller D, Geraghty K, Levin B. Rethinking the treatment of chronic fatigue syndrome-a reanalysis and evaluation of findings from a recent major trial of graded exercise and CBT. BMC Psychol. 2018;6(1):6. — PubMed PMID: 29562932
- NICE Guideline NG206. Myalgic encephalomyelitis (or encephalopathy)/chronic fatigue syndrome: diagnosis and management. National Institute for Health and Care Excellence. 2021.
- Goudsmit EM, Nijs J, Jason LA, Wallman KE. Pacing as a strategy to improve energy management in myalgic encephalomyelitis/chronic fatigue syndrome: a consensus document. Disabil Rehabil. 2012. — doi:10.3109/09638288.2011.635746
- Wernham C, Pheby D, Saffron L. Risk factors for the development of severe ME/CFS. Journal of Chronic Fatigue Syndrome. 2004;12(2):47–50. — doi:10.1300/J092v12n02_05
PubMed Topic Searches
For further reading, the following PubMed topic searches return current peer-reviewed work on pacing, the energy envelope, heart-rate-based self-management, and PEM prevention in myalgic encephalomyelitis/chronic fatigue syndrome:
- PubMed: Energy envelope theory and ME/CFS
- PubMed: Pacing in myalgic encephalomyelitis
- PubMed: Heart-rate pacing and anaerobic threshold in ME/CFS
- PubMed: Post-exertional malaise prevention strategies
- PubMed: Graded exercise therapy harms in ME/CFS
- PubMed: PACE trial re-analyses and methodology
- PubMed: Two-day CPET findings in ME/CFS
- PubMed: Orthostatic intolerance and heart rate in ME/CFS
Connections
- Neurology
- Myalgic Encephalomyelitis/Chronic Fatigue Syndrome Overview
- Post-Exertional Malaise
- 2-Day CPET and Objective Testing
- Severe and Very Severe Myalgic Encephalomyelitis
- Low Dose Naltrexone, Aripiprazole and Experimental Therapies
- Myalgic Encephalomyelitis/Chronic Fatigue Syndrome Diagnostic Criteria
- Orthostatic Intolerance in Myalgic Encephalomyelitis/Chronic Fatigue Syndrome
- Post-Viral Triggers: Epstein-Barr Virus and Others
- Mitochondrial Dysfunction and Energy Metabolism
- Postural Orthostatic Tachycardia Syndrome
- Postural Orthostatic Tachycardia Syndrome Compression and Exercise Program
- Mast Cell Activation Syndrome
- Fibromyalgia
- Fibromyalgia Exercise Pacing and Graded Movement
- Chronic Pain
- Stress Management
- Sleep Hygiene
- Fatigue