2-Day CPET and Objective Testing for Myalgic Encephalomyelitis/Chronic Fatigue Syndrome (ME/CFS)
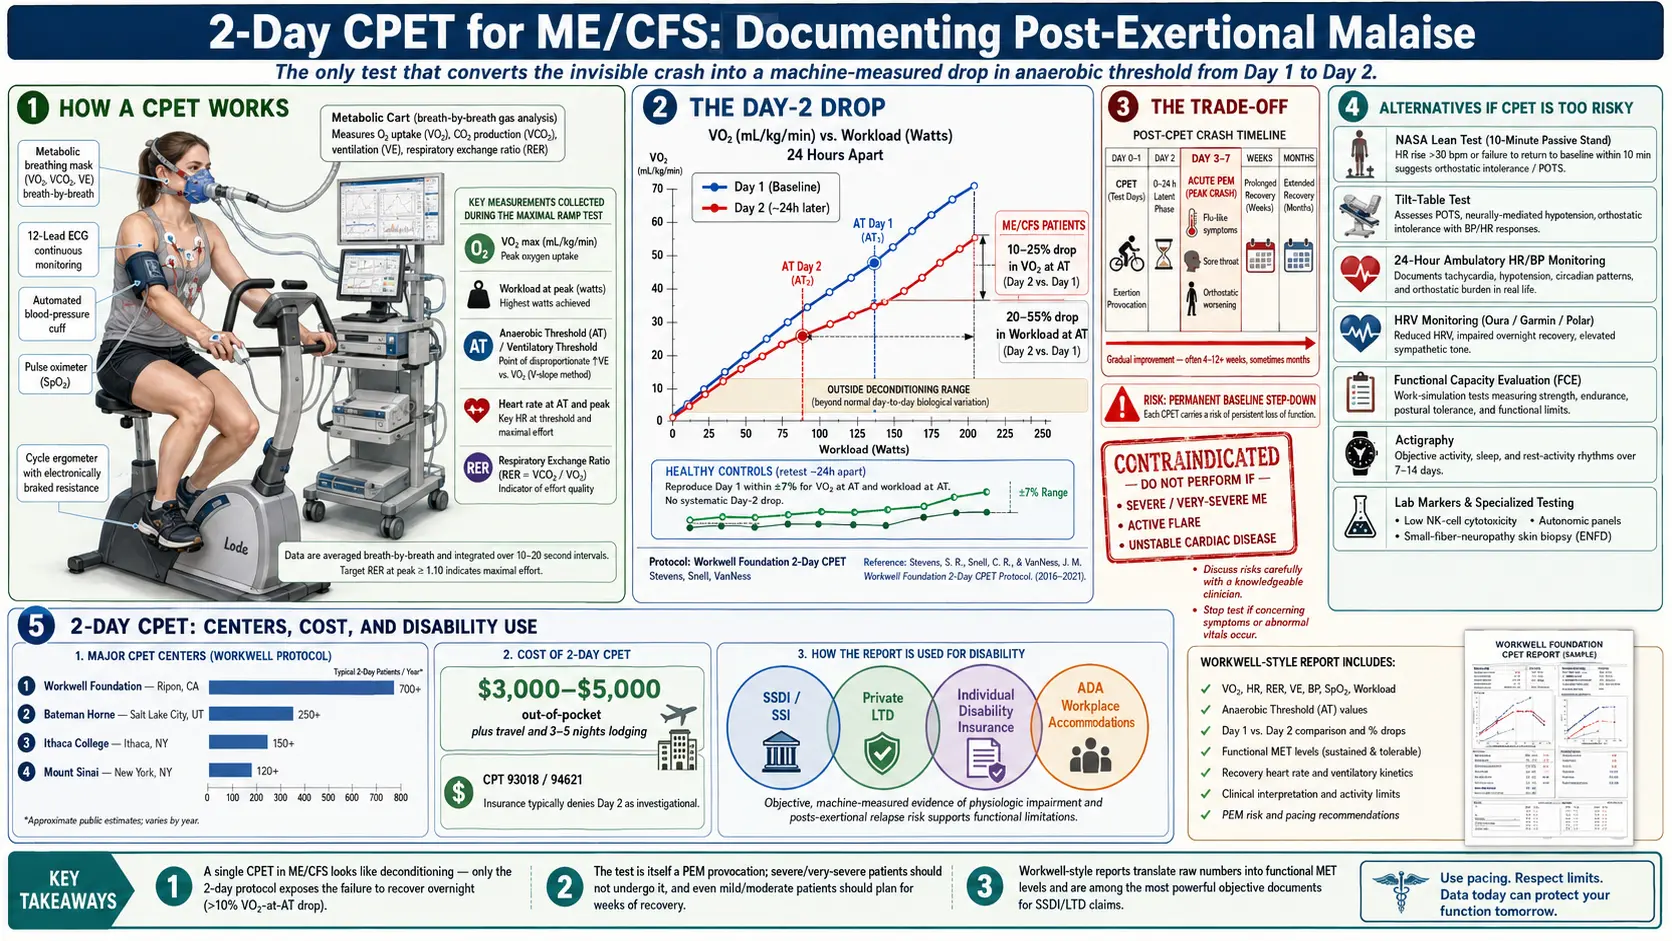
Table of Contents
- Why Objective Testing Matters
- What a CPET Actually Is
- Why Two Days — The Day-2 Drop
- The Day-2 Numbers That Count
- The Trade-Off — This Test Can Crash You
- Who Is Appropriate (and Who Is Not)
- Where 2-Day CPETs Are Done
- Cost, Insurance, and Paying Out of Pocket
- How Patients Prepare for the Test
- Using the Results for Disability Claims
- Alternatives for People Too Sick for CPET
- Autonomic Panels, Natural Killer Cells, and Other Objective Markers
- How Patients Weigh the Decision
- Key Research Papers
- Connections
- Featured Videos
Why Objective Testing Matters
If you have myalgic encephalomyelitis/chronic fatigue syndrome (ME/CFS), you have probably heard some version of this sentence from a doctor: "Your labs look fine." Complete blood count normal. Metabolic panel normal. Thyroid normal. Inflammatory markers normal. And yet you cannot work, cannot shower without resting, cannot walk to the mailbox without paying for it two days later. The gap between how you feel and what shows up on standard tests is one of the hardest parts of this illness — not only because of the symptoms themselves, but because that gap is used against you by disability insurers, employers, family members, and sometimes your own clinicians.
Objective testing is the bridge. It is how you turn the invisible crash into a number on a page. And in myalgic encephalomyelitis/chronic fatigue syndrome, the single most powerful piece of objective evidence we have is the two-day cardiopulmonary exercise test, or 2-day CPET. It is the only test that reliably documents post-exertional malaise (PEM) — the defining feature of myalgic encephalomyelitis/chronic fatigue syndrome — as a measurable physiological failure rather than a subjective complaint.
This article is written for patients considering whether a 2-day CPET makes sense for them, what the test actually involves, how to prepare, what it costs, how to use the results, and — just as importantly — when not to do it. Because this test is not free in any sense. It is expensive in dollars, and it is expensive in health. For the wrong patient on the wrong day, it can trigger a crash that lasts weeks or months. For the right patient it can be the single document that gets a disability claim approved or finally convinces a skeptical physician that the illness is real.
What a CPET Actually Is
A cardiopulmonary exercise test is a standard piece of cardiology and pulmonology. You sit on a stationary bike (or, less commonly, walk on a treadmill) while a technician measures everything your body does as the resistance gradually increases. You wear a mask that captures every breath. A 12-lead electrocardiogram (ECG) tracks your heart rhythm. A blood pressure cuff cycles automatically. A pulse oximeter clips to your finger. A pedal cadence monitor times your revolutions.
The test runs until you cannot go further — a "maximal" effort ending in volitional exhaustion, usually 8 to 12 minutes of pedaling. During that time the equipment records, breath by breath:
- VO2 max — the peak volume of oxygen your body can use per minute, normalized to body weight (mL/kg/min). This is the classic measure of aerobic fitness.
- Workload at peak — the watts of resistance you were pedaling against when you stopped.
- Anaerobic threshold (AT), also called the ventilatory threshold — the point at which your body shifts from aerobic to anaerobic metabolism. This is the workload you can sustain for hours in daily life without accumulating oxygen debt.
- Heart rate at AT and at peak, respiratory exchange ratio, oxygen pulse, ventilatory efficiency.
In a healthy sedentary adult, these numbers form a predictable pattern. In a deconditioned person, the numbers are low but the pattern is preserved. In myalgic encephalomyelitis/chronic fatigue syndrome, the pattern itself breaks on Day 2 — and that is the whole point of running the test twice.
Why Two Days — The Day-2 Drop
A single CPET on a person with myalgic encephalomyelitis/chronic fatigue syndrome often looks unremarkable. Our bodies can produce one maximal effort. Muscles contract, heart rate climbs, lungs move air, and the numbers fall within the wide range that could pass as "deconditioning" on a cardiologist's report. That is exactly why a single-day CPET is not enough — and exactly why disability insurers who know what they are doing will dismiss it.
The magic of the 2-day protocol, pioneered by the Workwell Foundation (Staci Stevens, Christopher Snell, Mark VanNess) in the early 2000s, is that it forces the body to do what daily life forces it to do: perform again the next day. The patient comes back approximately 24 hours later and does the entire test over. A healthy person — and, in published studies, people with several other conditions, including heart failure and mild-to-moderate chronic obstructive pulmonary disease — reproduces their Day-1 numbers closely: the 2018 methods paper by Stevens and colleagues puts normal test-retest variation in oxygen use and workload at the anaerobic threshold at about 7–12%. The body recovers its capacity overnight. That is what healthy aerobic systems do.
People with myalgic encephalomyelitis/chronic fatigue syndrome do not. On Day 2, VO2 at anaerobic threshold and workload at anaerobic threshold drop measurably, sometimes dramatically. This is not fatigue. It is not lack of effort (respiratory exchange ratio confirms maximal effort on both days). It is an objective, reproducible failure of aerobic energy production to recover after a modest exercise challenge. That failure is post-exertional malaise, caught in the act and quantified to two decimal places.
The Day-2 Numbers That Count
The published studies converge on a few key findings:
- In healthy controls, Day-2 VO2 at anaerobic threshold reproduces Day 1 within about 7–12% (normal test-retest variation, Stevens 2018).
- In myalgic encephalomyelitis/chronic fatigue syndrome patients, Day-2 VO2 at AT drops by an average of 10% to 25%, with many patients dropping more.
- Workload at AT (the watts a person can sustain without going anaerobic) drops similarly, often by 20% to 55%.
- The drop is reproducible across studies (Snell 2013, Keller 2014, VanNess 2007, Stevens 2018) and across testing centers.
- Stevens 2018 treats a Day-2 change as abnormal when it is larger than normal test-retest variation (about 7–12% for VO2 and workload at AT). In Keller 2014, 22 patients’ Day-2 VO2 at the ventilatory threshold fell by an average of 15.8% and workload at the threshold by 21.3%.
Translated into daily life: if a patient’s workload at anaerobic threshold falls from 75 watts on Day 1 to 45 watts on Day 2, the test has documented that after one ordinary-looking exertion they lost 40% of their sustainable capacity overnight. Patients describe the same pattern at home: able to shower on Monday, attempting to cook dinner on Tuesday, and flattened on Wednesday. The test is catching what their daily life already shows.
The Trade-Off — This Test Can Crash You
Here is the part most articles gloss over. The 2-day CPET is, by design, a PEM provocation. The patient is asked to push to volitional exhaustion twice inside 24 hours, specifically so that the crash shows up on the instruments. That crash does not politely end when you step off the bike.
Patients commonly report:
- A "normal" myalgic encephalomyelitis/chronic fatigue syndrome crash in the days immediately after — cognitive fog, flu-like symptoms, sore throat, swollen lymph nodes, muscle pain, orthostatic worsening, sleep disturbance.
- Extended recovery of weeks to months before returning to their pre-test baseline.
- In some cases, a permanent step-down in baseline function — they never fully return to where they were before the test.
Experienced centers describe this to patients before booking. It is not a complication; it is the mechanism. PEM cannot be documented without triggering PEM. The question each patient faces is whether their body, at their stage of illness, can tolerate the provocation in exchange for the data.
For someone mildly affected who is fighting for disability benefits, returning to work conversations, or trying to get a skeptical specialist to take them seriously, patients often describe the trade as worth it. For someone moderately affected who is just barely holding their life together, the risk of a permanent worsening is real. For severe and very severe patients, experienced centers regard this test as contraindicated outright — see the severe and very severe myalgic encephalomyelitis (ME) article.
Who Is Appropriate (and Who Is Not)
The informal rule described by experienced ME/CFS testing centers: a patient who cannot reliably walk into the clinic, change clothes, pedal a bike to exhaustion, and do it again 24 hours later without requiring hospitalization or months of recovery is not considered a candidate.
Generally considered appropriate:
- Mild myalgic encephalomyelitis/chronic fatigue syndrome — ambulatory, can work part-time or manage household tasks with pacing.
- Moderate myalgic encephalomyelitis/chronic fatigue syndrome — mostly housebound but can do a few hours of light activity per day.
- Patients pursuing Social Security Disability, long-term disability insurance claims, or workplace accommodations where objective documentation is pivotal.
- Patients whose clinicians will not accept the diagnosis without "hard" evidence.
Generally considered not appropriate:
- Severe or very severe myalgic encephalomyelitis/chronic fatigue syndrome — mostly or fully bedbound, require help with basic daily activities.
- Patients in an active crash or flare.
- Patients with unstable cardiac disease, uncontrolled hypertension, or other standard cardiology contraindications to maximal exercise testing.
- Patients whose disability claim is already progressing on other documentation and for whom the test adds marginal benefit relative to the risk.
Experienced centers do not run this test on a patient they consider too sick, and patients who judge themselves too sick for it commonly decline or defer it.
Where 2-Day CPETs Are Done
The number of centers with experience running the myalgic encephalomyelitis/chronic fatigue syndrome 2-day protocol is small. They include:
- Workwell Foundation (Ripon, California) — a nonprofit ME/CFS organization whose researchers developed the protocol; it produces disability-oriented reports written in the language insurers and administrative judges read.
- Bateman Horne Center (Salt Lake City, Utah) — a nonprofit myalgic encephalomyelitis/chronic fatigue syndrome and fibromyalgia center that runs 2-day CPETs as part of broader diagnostic workups.
- Some academic exercise-physiology labs and specialist clinics, including some post-viral illness clinics, which run 2-day CPETs with myalgic encephalomyelitis/chronic fatigue syndrome-experienced exercise physiologists.
A handful of academic cardiology labs will also run a 2-day CPET if a referring physician writes a specific protocol request, but reports from non-specialist labs frequently misinterpret the Day-2 drop or fail to report anaerobic-threshold numbers at all. A report that does not state VO2 at AT and workload at AT for both days, side by side, does not show the Day-2 drop that an ME/CFS CPET is meant to measure.
Cost, Insurance, and Paying Out of Pocket
Patients report paying between $3,000 and $5,000 out of pocket for the 2-day test, depending on the center and whether a clinical interpretation is bundled. Additional costs typically include travel, lodging for 3 to 5 nights (arrival day, two testing days, at least one recovery day before attempting the trip home), and a companion.
Insurance coverage is the exception, not the rule:
- Most insurers consider the second day of testing "investigational" for myalgic encephalomyelitis/chronic fatigue syndrome and deny it.
- Day 1 is sometimes reimbursable under standard CPET CPT codes (93018, 94621), especially when ordered by a cardiologist to rule out cardiac disease.
- Some patients successfully submit appeals after the fact, particularly when the test results are pivotal to an approved disability claim.
- Health savings account (HSA) and flexible spending account (FSA) dollars generally cover the test.
Patients describe planning for the full cost up front and treating any insurance reimbursement as a bonus.
How Patients Prepare for the Test
Preparation starts weeks before. The aim is for the patient to arrive as close to their personal baseline as possible so the Day-1 numbers reflect their actual capacity rather than a flare.
- Rigorous pacing for two to four weeks beforehand. This is the opposite of "training" — the aim is to arrive rested, not conditioned. See the pacing and energy-envelope article for the underlying framework.
- Medication adjustments per the center's protocol. Beta-blockers, stimulants, and some autonomic medications alter heart-rate and ventilatory responses, and testing centers may ask for some to be held for 24 to 48 hours. Stopping some medicines suddenly carries its own risk: beta-blocker labels warn that abrupt stopping has been followed by worsening chest pain (angina) and, in some cases, heart attacks, especially in people with heart disease, which is why holds are arranged in writing by the testing center and the prescriber.
- Travelling a day early and resting. Patients and centers describe keeping a flight and a test out of the same 24-hour window.
- A companion. Patients describe being unable to navigate an airport or drive safely after Day 2, and sometimes after Day 1, so a spouse, parent, adult child, or paid caregiver usually handles the logistics.
- Hydration and electrolytes. Many myalgic encephalomyelitis/chronic fatigue syndrome patients also have orthostatic intolerance (see the orthostatic intolerance article). Patients report that arriving dehydrated worsens both the test experience and the recovery.
- Recovery time. Patients describe keeping the weeks after the test clear of anything important and expecting to be flat.
- Sleep plans on the road. Patients describe booking a quiet hotel room with blackout curtains and a flexible check-out time in case they cannot leave on schedule.
Using the Results for Disability Claims
The reason most patients pay for a 2-day CPET is to build a disability file. The report, properly written, is one of the most powerful single documents in myalgic encephalomyelitis/chronic fatigue syndrome adjudication for two reasons: it is objective (machine-measured), and it speaks a language insurance medical directors already understand (they use single-day CPETs routinely for cardiac and pulmonary claims).
A useful report translates the numbers into functional capacity. Instead of stopping at "VO2 at AT dropped 22%," it says: "The patient's sustainable workload on Day 2 corresponds to a metabolic equivalent (MET) level of 2.5, which is below the threshold for sustained sedentary desk work and consistent with a disability determination of unable to perform any substantial gainful activity on a reproducible daily basis."
The test is used successfully in:
- Social Security Disability Insurance (SSDI) and Supplemental Security Income (SSI) claims, where administrative law judges increasingly recognize the 2-day CPET as addressing the "reproducibility" standard for sustained work.
- Private long-term disability (LTD) claims under employer-sponsored policies, where insurers often demand functional capacity evidence beyond physician opinion.
- Individual disability insurance policies, which tend to have even stricter documentation requirements.
- Workplace accommodation requests under the Americans with Disabilities Act (ADA).
Specialist ME/CFS testing centers produce reports written specifically for this purpose. A non-specialist cardiology lab may supply raw data without the functional-capacity narrative, leaving the patient’s attorney or physician to do the translation work — sometimes badly.
Alternatives for People Too Sick for CPET
For patients for whom the 2-day CPET is too risky, too expensive, or too far to travel to, there are gentler objective tests that contribute meaningful evidence. None individually carries the weight of a 2-day CPET, but a combination builds a credible file.
- NASA Lean Test (10-minute passive stand test). Free, requires no equipment beyond a blood pressure cuff, can be done at home with a partner. Documents orthostatic intolerance by measuring heart rate and blood pressure at baseline (supine) and every minute for 10 minutes of quiet standing. A sustained heart-rate rise of 30 beats per minute or more (40 bpm in adolescents), or a systolic blood pressure drop of 20 mmHg or more, is abnormal. See the postural orthostatic tachycardia syndrome (POTS) deep-dive article on tilt-table and NASA Lean testing for the protocol.
- Tilt-table test. The formal, hospital-based version of the NASA Lean Test. Recognized by cardiology and neurology, often covered by insurance. Useful when postural orthostatic tachycardia syndrome or orthostatic hypotension is prominent. See the postural orthostatic tachycardia syndrome overview.
- 24-hour ambulatory heart-rate and blood-pressure monitoring. Documents the day-to-day reality of orthostatic dysfunction in ways a single clinic measurement cannot.
- Heart rate variability (HRV) monitoring. Consumer heart-rate monitors and heart-rate-variability apps track overnight HRV and morning readiness. Trends showing persistently low HRV and suppressed readiness on days following even minor activity are consistent with autonomic dysfunction. Not diagnostic on their own, but useful as pattern evidence.
- Functional Capacity Evaluation (FCE). A full-day standardized evaluation run by an occupational or physical therapist who measures lifting, carrying, sitting tolerance, standing tolerance, and repetitive tasks. Widely used in disability determinations. Patients report that many FCE examiners do not understand PEM and score the patient's "good" effort without noting the crash that follows; patient advocates describe asking for a two-day FCE where possible, with PEM explicitly documented.
- Actigraphy. Wrist-worn accelerometers log activity continuously for one to four weeks, producing a paper trail of how much — or how little — the person actually moves. Inexpensive, non-provoking, and hard to argue with.
- Symptom diaries with wearable data. Not flashy, but contemporaneous daily logs of step counts, heart rate, and symptoms carry real weight when paired with any of the above.
Autonomic Panels, Natural Killer Cells, and Other Objective Markers
Beyond exercise-based testing, a few laboratory and physiologic measures are consistently abnormal in myalgic encephalomyelitis/chronic fatigue syndrome and can round out an objective workup:
- Natural killer (NK) cell function. Low natural killer cell cytotoxicity is one of the most reproducible laboratory abnormalities in myalgic encephalomyelitis/chronic fatigue syndrome across studies and decades. The test (often labeled "natural killer cell function" or "NK-cell activity") measures how effectively a person's natural killer cells kill target cells in vitro — not simply how many you have. Low function suggests a persistent immune dysregulation consistent with the post-viral pathophysiology of the illness. Available through some commercial laboratories; not always covered by insurance.
- Autonomic function panels. Sudomotor testing (QSART), deep-breathing heart-rate variability, Valsalva ratio, and tilt-table together form a formal autonomic battery available at some academic neurology autonomic labs and specialist clinics. Abnormal findings document the small-fiber and autonomic component of the illness.
- Skin biopsy for small-fiber neuropathy. A 3 mm punch biopsy of the lower leg, stained for intraepidermal nerve fiber density, can document small-fiber neuropathy, which is common in myalgic encephalomyelitis/chronic fatigue syndrome and overlapping conditions such as fibromyalgia.
- Cognitive testing. Formal neuropsychological batteries — ideally repeated before and after a provocation such as exercise or cognitive load — can document the cognitive component of PEM.
- Basic immune and inflammatory labs. While complete blood count (CBC) and CMP are typically normal, some patients show low morning cortisol, reactivated herpes-family viruses (Epstein-Barr virus, HHV-6), low immunoglobulin G (IgG) subclasses, or elevated cytokines. See post-viral triggers for context.
None of these replaces the 2-day CPET as evidence of PEM, but in combination they build a convergent picture. For disability purposes in particular, a file showing abnormal natural killer function, abnormal autonomic testing, abnormal NASA Lean Test, and an actigraphy record of profoundly limited activity can approach the weight of a CPET without the crash risk.
How Patients Weigh the Decision
The questions patients and clinicians describe weighing before a 2-day CPET:
- Whether the person is in the mild-to-moderate range, and whether their physical situation allows two days of maximal effort plus weeks of recovery.
- Whether there is a specific, high-stakes use for the report — a pending SSDI hearing, a long-term disability appeal, a contested diagnosis with a specialist.
- Whether gentler objective evidence (NASA Lean Test, tilt-table, natural killer function, actigraphy) has already been gathered and the file is still insufficient.
- Whether travel, companionship, and recovery time can be arranged without destabilizing the rest of the person's life.
- Whether the person is prepared for the possibility of a prolonged crash, including the possibility that their baseline does not fully return.
When most of these hold, patients and clinicians describe the 2-day CPET as one of the most powerful tools available in this illness. When several do not, they describe starting with the alternatives and building the objective file piece by piece. A disability claim almost never rises or falls on a single test. The goal is a coherent, reproducible, machine-measured record of an illness that standard medicine was not built to see — and there is more than one road to that record.
Key Research Papers
- VanNess JM, Snell CR, Stevens SR. Diminished cardiopulmonary capacity during post-exertional malaise. Journal of Chronic Fatigue Syndrome. 2007;14(2):77-85. — doi:10.1300/j092v14n02_07
- Snell CR, Stevens SR, Davenport TE, VanNess JM. Discriminative validity of metabolic and workload measurements for identifying people with chronic fatigue syndrome. Phys Ther. 2013. — doi:10.2522/ptj.20110368
- Keller BA, Pryor JL, Giloteaux L. Inability of myalgic encephalomyelitis/chronic fatigue syndrome patients to reproduce VO2 peak indicates functional impairment. J Transl Med. 2014. — doi:10.1186/1479-5876-12-104
- Stevens S, Snell C, Stevens J, Keller B, VanNess JM. Cardiopulmonary exercise test methodology for assessing exertion intolerance in myalgic encephalomyelitis/chronic fatigue syndrome. Front Pediatr. 2018. — doi:10.3389/fped.2018.00242
PubMed Topic Searches
For further reading, these PubMed topic searches return current peer-reviewed work on exercise testing, autonomic evaluation, and objective biomarkers in myalgic encephalomyelitis/chronic fatigue syndrome:
- PubMed: Two-day CPET in chronic fatigue syndrome
- PubMed: Post-exertional malaise and cardiopulmonary exercise testing
- PubMed: Anaerobic threshold in myalgic encephalomyelitis
- PubMed: Natural killer cell function in chronic fatigue syndrome
- PubMed: Tilt-table testing and orthostatic intolerance in ME/CFS
- PubMed: NASA Lean Test and orthostatic evaluation
- PubMed: Functional capacity evaluation in chronic fatigue syndrome
- PubMed: Small-fiber neuropathy and chronic fatigue syndrome
Connections
- Neurology
- Myalgic Encephalomyelitis/Chronic Fatigue Syndrome Overview
- Post-Viral Triggers: Epstein-Barr Virus and Others
- Severe and Very Severe Myalgic Encephalomyelitis
- Orthostatic Intolerance in Myalgic Encephalomyelitis/Chronic Fatigue Syndrome
- Post-Exertional Malaise
- Pacing and the Energy Envelope
- Myalgic Encephalomyelitis/Chronic Fatigue Syndrome Diagnostic Criteria
- Low Dose Naltrexone, Abilify and Experimental Therapies
- Mitochondrial Dysfunction and Energy Metabolism
- Postural Orthostatic Tachycardia Syndrome
- Tilt-Table and NASA Lean Test
- Fibromyalgia
- Mast Cell Activation Syndrome
- Chronic Pain
- Fatigue
- Complete Blood Count
- Inflammatory Markers
- Lab Tests