Inflammatory Bowel Disease (IBD)
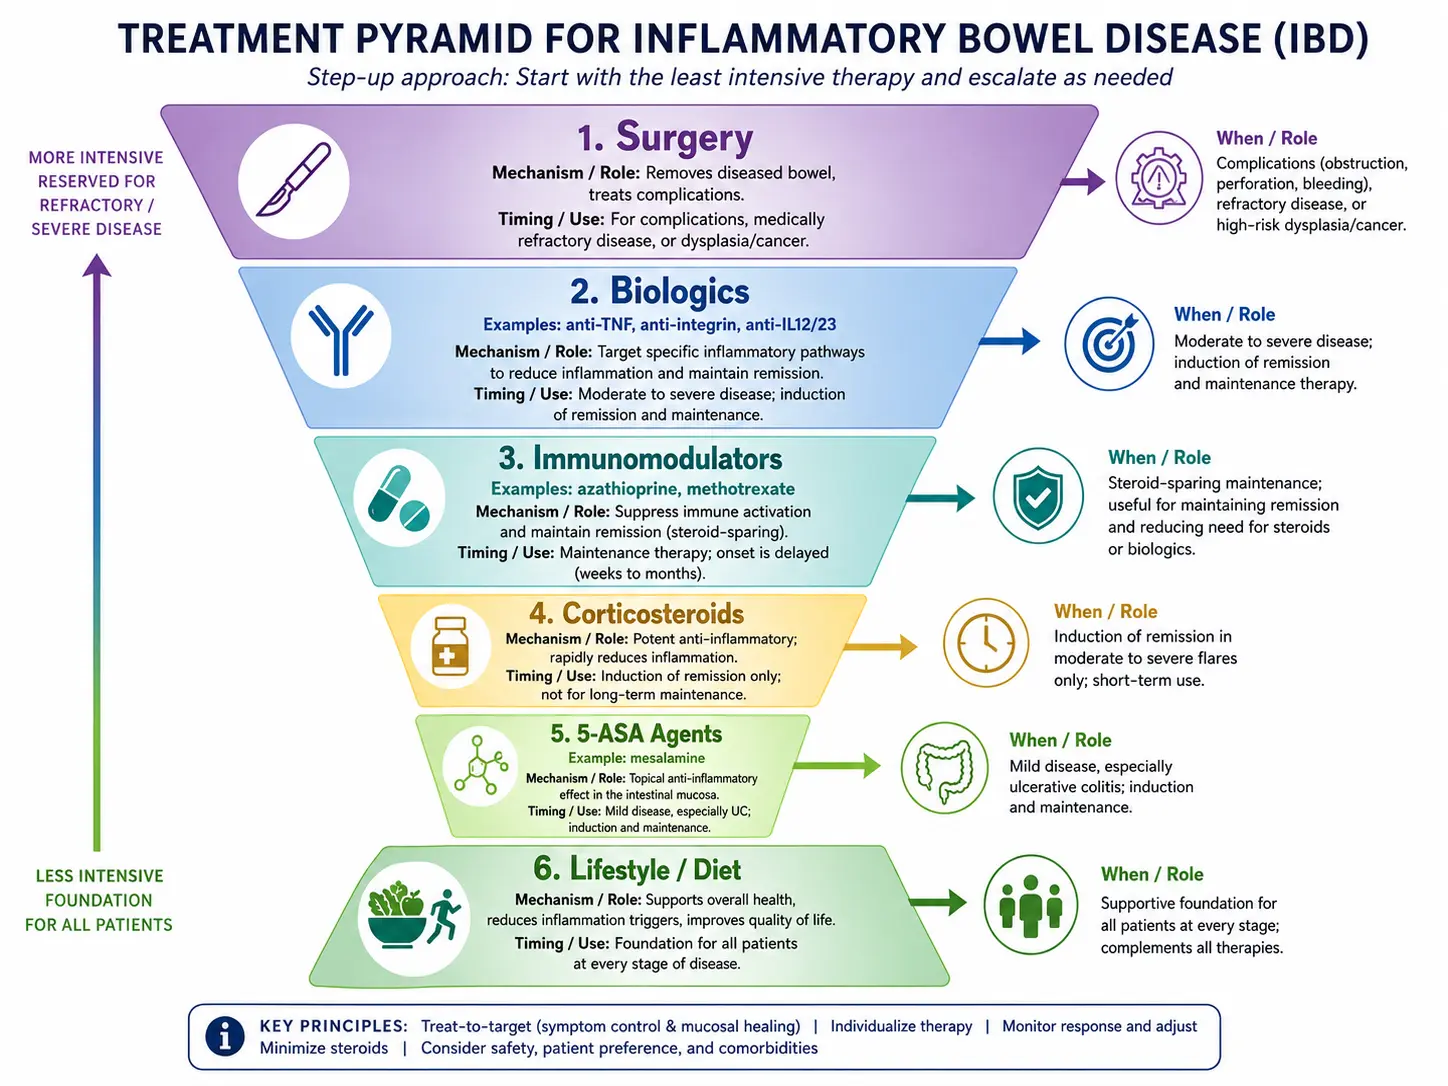
Table of Contents
Deep-Dive Articles
The articles below go beyond this overview into diagnosis, biologics, diet, surgery, and the extraintestinal side of IBD. Written for patients and caregivers, with real research citations.
Crohn's vs Ulcerative Colitis
Location, depth of inflammation, skip lesions vs continuous disease, and why the distinction drives treatment choice.
Read the deep dive →Diagnostic Workup
Fecal calprotectin, colonoscopy with biopsy, MR enterography, and how to tell IBD from IBS or infection.
Read the deep dive →Biologics: TNF, IL-23, Integrins
Infliximab, adalimumab, ustekinumab, risankizumab, vedolizumab — how each class works, side-effect profile, and sequencing.
Read the deep dive →JAK Inhibitors & S1P Modulators
Tofacitinib, upadacitinib, ozanimod, etrasimod — oral small molecules for UC, when they fit, and the black-box warnings.
Read the deep dive →Diet for IBD
Specific Carbohydrate Diet, Mediterranean, CDED, and enteral nutrition — what the trials actually show.
Read the deep dive →Surgery Decisions
Ileocecal resection, colectomy with J-pouch, ostomy — when surgery is considered and what life looks like after.
Read the deep dive →Extraintestinal Manifestations
Arthritis, uveitis, erythema nodosum, PSC — the IBD symptoms that show up outside the gut.
Read the deep dive →Fatigue, Anemia & Nutrients
Iron deficiency, B12, vitamin D, and why fatigue persists even when inflammation is controlled.
Read the deep dive →Pregnancy & IBD
Fertility, what the research reports on biologics and small molecules in pregnancy and lactation, flare risk, and PIANO-registry data.
Read the deep dive →What is Inflammatory Bowel Disease (IBD)?
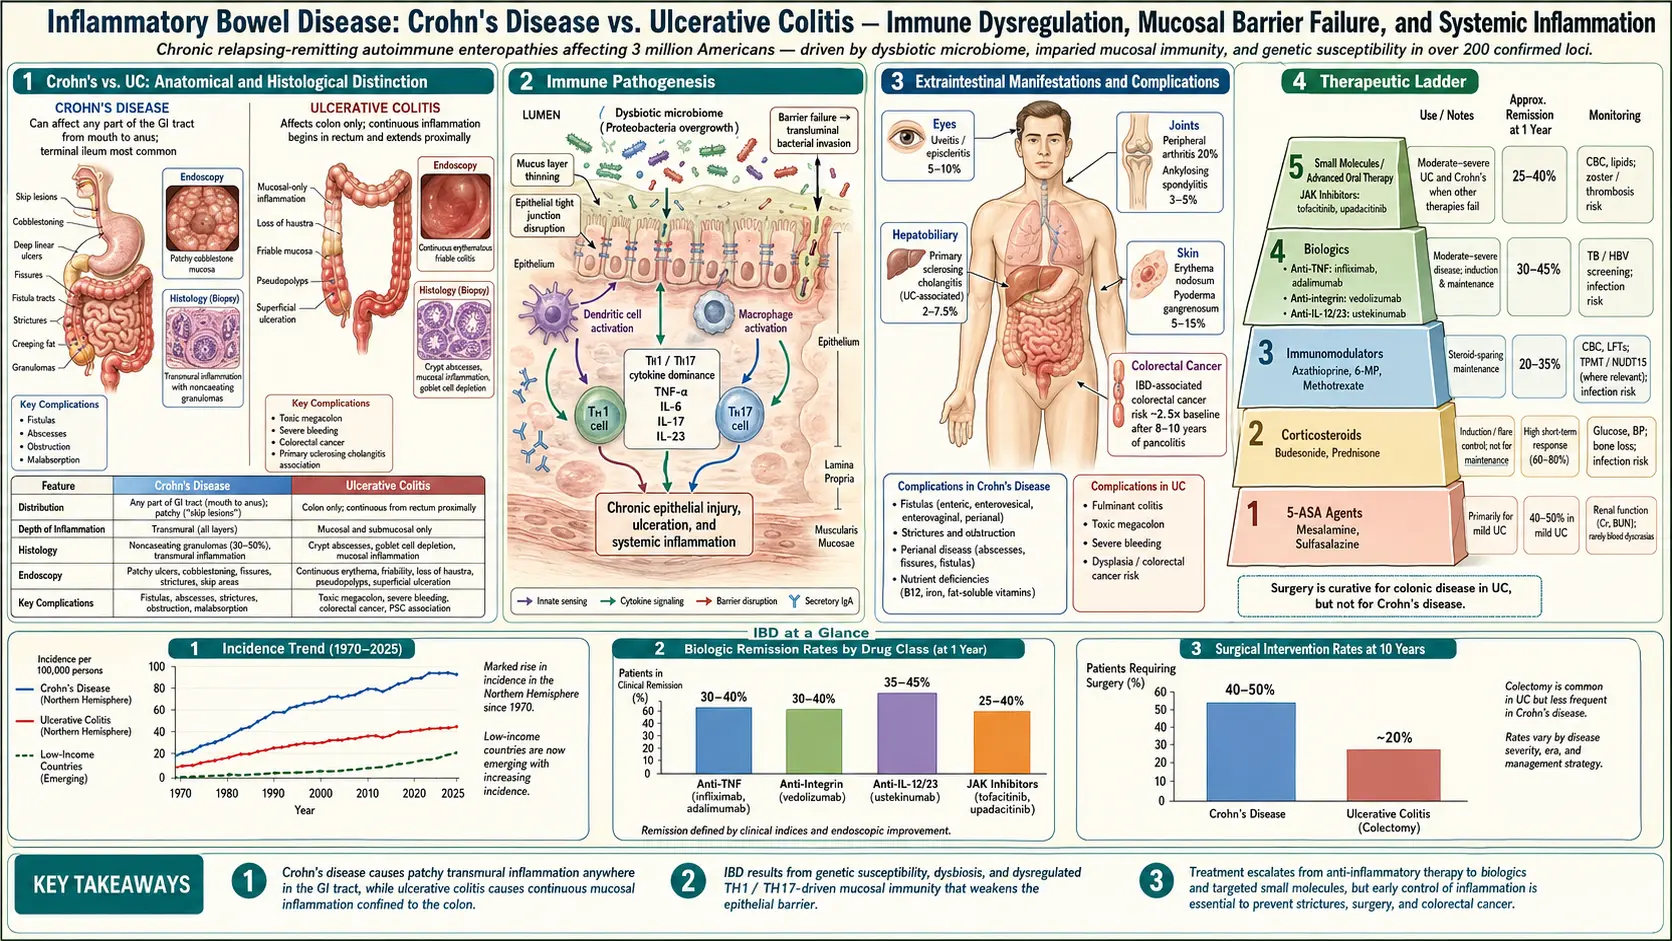
Inflammatory bowel disease (IBD) is an umbrella term for chronic inflammatory conditions of the gastrointestinal (GI) tract. Its two common forms are Crohn's disease and ulcerative colitis (Jostins 2012). The 2025 American College of Gastroenterology (ACG) guidelines describe each as an idiopathic inflammatory disorder of unknown cause (Lichtenstein 2025; Rubin 2025). Torres and colleagues' 2017 Lancet seminar describes Crohn's disease as possibly resulting from a complex interplay between genetic susceptibility, environmental factors and altered gut microbiota, leading to dysregulated innate and adaptive immune responses; Ungaro and colleagues' 2017 Lancet review describes ulcerative colitis as multifactorial, involving genetic predisposition, defects in the gut's epithelial barrier, dysregulated immune responses and environmental factors.
How common it is. Ng and colleagues' 2017 Lancet systematic review of population-based studies found the highest reported prevalence in Europe (ulcerative colitis 505 per 100,000 in Norway; Crohn's disease 322 per 100,000 in Germany) and North America (ulcerative colitis 286 per 100,000 in the USA; Crohn's disease 319 per 100,000 in Canada), with IBD prevalence above 0.3% in North America, Oceania and many European countries. Most studies from North America and Europe reported stable or decreasing incidence, while since 1990 incidence has been rising in newly industrialised countries in Africa, Asia and South America; the authors described IBD as a global disease with accelerating incidence in newly industrialised countries whose societies have become more westernised (Ng 2017).
Types of IBD
1. Crohn's Disease
- Inflammation through the bowel wall: the ACG guideline describes its defining finding as focal, asymmetric, transmural granulomatous inflammation of the GI tract — inflammation that can run through the full thickness of the bowel wall (Lichtenstein 2025).
- Where it occurs: population-based studies from Norway and Minnesota cited by the ACG guideline found ileal (end of the small intestine), ileocolonic or colonic disease in roughly one-third of patients each, with up to a quarter also having upper GI involvement; only 6–14% changed location over time.
- Patchy inflammation: clues the guideline lists for telling Crohn's colitis from ulcerative colitis include discontinuous involvement with skip areas, sparing of the rectum, deep or linear ulcers, strictures, fistulas and granulomatous inflammation; granulomas are found on biopsy in only a minority of patients.
2. Ulcerative Colitis
- The colon and rectum: Ordás and colleagues describe ulcerative colitis as a chronic inflammatory disorder of the colonic mucosa (the inner lining) that starts in the rectum and generally extends upward in a continuous manner through part or all of the colon; some patients with proctitis or left-sided colitis have a separate caecal patch of inflammation (Ordás 2012).
- Rectal involvement: the ACG guideline notes that the rectum is spared in fewer than 5% of adults at diagnosis, but in up to a third of children with colitis onset (Rubin 2025).
- Course: the guideline describes the course as most often relapsing and remitting, with flares alternating with periods of remission (Rubin 2025).
Common Symptoms of IBD
Features the 2025 ACG guidelines list include:
- Chronic diarrhea — the most common symptom of Crohn's disease, although some patients do not have it (Lichtenstein 2025).
- Abdominal pain — in Crohn's often in the right lower abdomen and worse after eating (Lichtenstein 2025).
- Blood in the stool, more frequent stools and bowel urgency — the features the ulcerative colitis guideline names as raising suspicion of the disease (Rubin 2025).
- Fatigue — described as very prevalent in Crohn's, attributed to the inflammation itself, anemia, or vitamin and mineral deficiencies (Lichtenstein 2025).
- Weight loss and fever, and growth failure in younger patients (Lichtenstein 2025).
- Features outside the gut — arthritis, skin conditions (pyoderma gangrenosum, erythema nodosum), eye inflammation (uveitis, scleritis, episcleritis) and primary sclerosing cholangitis (Lichtenstein 2025).
Causes and Risk Factors
- Genetics and family history: 8–14% of people with ulcerative colitis have a family history of IBD, and first-degree relatives have four times the risk (Ungaro 2017). A 2012 genome-wide meta-analysis of more than 75,000 cases and controls brought the total to 163 IBD risk loci, most contributing to both Crohn's disease and ulcerative colitis, and found considerable overlap with susceptibility loci for mycobacterial infection (Jostins 2012). Variants of the NOD2 gene associated with Crohn's disease were reported in 2001 (Hugot 2001).
- Immune system response: both Lancet reviews describe dysregulated immune responses as part of the disease process (Torres 2017; Ungaro 2017).
- Environment and diet: incidence has been rising in newly industrialised countries as their societies have become more westernised (Ng 2017). In a 21-country cohort of 116,087 adults, eating five or more servings of ultra-processed food a day, compared with less than one, was associated with a higher risk of IBD (hazard ratio 1.82, 95% CI 1.22–2.72), with consistent results for Crohn's disease and ulcerative colitis; intakes of white meat, red meat, dairy, starch, fruit, vegetables and legumes were not associated with IBD (Narula 2021). These are associations, not proven causes.
- Age: IBD can begin at any age. For ulcerative colitis, the ACG guideline describes onset as peaking in the third decade of life (Rubin 2025), while the 2017 Lancet review gives a peak between ages 30 and 40 and reports no difference between the sexes (Ungaro 2017).
- Smoking: smoking acts differently in the two diseases. In a 2006 meta-analysis, current smoking was associated with Crohn's disease (odds ratio 1.76, 95% CI 1.40–2.22), while current smoking was associated with a lower risk of ulcerative colitis (odds ratio 0.58) and former smoking with a higher one (odds ratio 1.79) (Mahid 2006). The ACG Crohn's guideline states that smoking exacerbates disease activity and accelerates recurrence (Lichtenstein 2025); the ulcerative colitis guideline lists recent smoking cessation among possible triggers of the disease (Rubin 2025).
Diagnosis
The ACG Crohn's guideline states that there are no truly pathognomonic features: the diagnosis is made clinically, by integrating history and examination, laboratory tests, endoscopy, pathology and imaging, and no single laboratory test can make it (Lichtenstein 2025). The tests the guidelines describe:
- Blood tests: an initial evaluation for inflammation, anemia, dehydration and malnutrition (Lichtenstein 2025).
- Stool tests: in active symptoms, testing for faecal pathogens and Clostridioides difficile and a marker of gut inflammation such as faecal calprotectin; the Crohn's guideline recommends a calprotectin cutoff of more than 50–100 µg/g to separate inflammatory from non-inflammatory disease (Lichtenstein 2025).
- Endoscopy: for ulcerative colitis, colonoscopy with examination of the end of the small bowel and biopsies of affected and unaffected areas confirms the diagnosis (Rubin 2025); a 2019 review describes ileocolonoscopy with biopsy as the only way to make a definitive diagnosis (Gajendran 2019). Capsule endoscopy is described as a useful adjunct for small-bowel Crohn's disease (Lichtenstein 2025).
- Imaging: the Crohn's guideline describes small-bowel imaging as part of the initial work-up for suspected Crohn's disease, describing CT enterography as comparable with MR enterography and MR enterography as preferred in people younger than 35 and those likely to need repeated scans, because it involves no radiation (Lichtenstein 2025).
Treatment Options
The 2025 ACG guidelines organise treatment by which disease a person has, how active it is and the risk of progression. The statements below are reported as the guidelines and reviews publish them; decisions about medicines belong with a clinician.
- Medications:
- Aminosalicylates (5-ASAs): established in ulcerative colitis — the guideline recommends or suggests rectal and/or oral 5-ASA, chosen by the extent of inflammation, for mildly to moderately active disease, and oral 5-ASA (at least 1.5 g a day) to maintain remission in left-sided or extensive disease (Rubin 2025). In Crohn's disease the guideline recommends against oral mesalamine for induction or maintenance (strong recommendation, moderate evidence), noting that 5-ASAs remain widely prescribed for Crohn's despite considerable evidence of their lack of efficacy (Lichtenstein 2025).
- Corticosteroids: used to induce remission. Both guidelines recommend against them for maintenance: in Crohn's, corticosteroids were not effective at maintaining remission in a meta-analysis of 403 patients (Lichtenstein 2025), and the ulcerative colitis guideline recommends against systemic, colon-release or topical corticosteroids for maintenance (Rubin 2025).
- Immunomodulators: azathioprine and mercaptopurine (thiopurines) and methotrexate. Because thiopurines take 8–12 weeks to act, the Crohn's guideline recommends against them for induction, suggests them or methotrexate for maintenance after steroid induction, and recommends TPMT testing before a thiopurine is started (Lichtenstein 2025). In ulcerative colitis, the guideline recommends against thiopurine or methotrexate monotherapy for induction, suggests thiopurines for maintenance after steroid-induced remission, and suggests against methotrexate for maintenance (Rubin 2025).
- Biologic therapies: antibodies against specific parts of the immune response. Anti-TNF drugs (infliximab, adalimumab, and certolizumab pegol in Crohn's or golimumab in ulcerative colitis); vedolizumab, which blocks the gut-homing integrin α4β7; ustekinumab (IL-12/23); and the IL-23 inhibitors risankizumab, mirikizumab and guselkumab are each recommended for moderately to severely active disease in the 2025 guidelines (Lichtenstein 2025; Rubin 2025). In Crohn's, infliximab combined with a thiopurine is recommended over either drug alone (Lichtenstein 2025). The landmark trials are summarised on the Crohn's disease and ulcerative colitis pages.
- Oral small molecules: the JAK inhibitors tofacitinib and upadacitinib and the S1P receptor modulators ozanimod and etrasimod are recommended for moderately to severely active ulcerative colitis (Rubin 2025); upadacitinib is recommended in Crohn's disease for patients previously exposed to anti-TNF drugs (Lichtenstein 2025).
- Antibiotics: the Crohn's guideline states that antibiotics are not an effective treatment for luminal inflammatory Crohn's disease and are not used as primary therapy; they are used for complications, for example added to biologics or thiopurines for perianal fistulas (Lichtenstein 2025).
- Diet: the American Gastroenterological Association's 2024 clinical practice update states that no diet has consistently been found to decrease the rate of flares in adults with IBD, and that a diet low in red and processed meat may reduce ulcerative colitis flares but has not been found to reduce relapse in Crohn's disease. Its first best-practice statement describes a Mediterranean diet rich in a variety of fresh fruits and vegetables, monounsaturated fats, complex carbohydrates and lean proteins, and low in ultra-processed foods, added sugar and salt, for overall health in people with IBD unless there is a contraindication. It describes exclusive enteral nutrition (a liquid formula as the only food) as effective for inducing remission in Crohn's disease, with stronger evidence in children than adults (Hashash 2024). A systematic review of 23 randomised trials of fibre found the evidence of benefit limited and weak, and no evidence that fibre intake needs to be restricted in IBD, excluding overt bowel obstruction (Wedlake 2014). The International Organization for the Study of IBD (IOIBD) has issued expert-opinion guidance on foods and food additives to increase or decrease (Levine 2020). Diet is covered in the Diet for IBD deep dive.
- Emulsifiers: in mice, the emulsifiers carboxymethylcellulose and polysorbate-80 induced low-grade inflammation and promoted colitis in mice predisposed to it (Chassaing 2015). In a 4-week double-blind feeding trial of 24 adults with active Crohn's disease, a high- and a low-emulsifier diet showed no statistically significant differences in outcomes, and the authors concluded that recommendations to avoid emulsifiers in active Crohn's are not supported (Fitzpatrick 2025); a larger 154-patient trial, so far reported only as a conference abstract, reported emulsifier restriction as effective (Bancil 2025). The human trial evidence is small and not yet consistent.
- Stress, anxiety and depression: the Crohn's guideline recommends assessing and managing them as part of care because of increased risks of disease activity and health-care use, and reports that up to a third of people with IBD report anxiety and a quarter depressive symptoms (Lichtenstein 2025); the ulcerative colitis guideline describes screening for anxiety and depression (Rubin 2025).
- Surgery:
- For Crohn's disease: the guideline describes surgery as not a failure of medication; the most common reason for removing a section of bowel is a small-bowel obstruction from a fibrotic stricture, and strictureplasty is a bowel-preserving option. Surgery does not cure Crohn's: the risk of endoscopic recurrence after resection approaches 90% (Lichtenstein 2025).
- For ulcerative colitis: restorative proctocolectomy with an ileal pouch–anal anastomosis (IPAA) is described as the surgical procedure of choice for refractory disease (Rubin 2025). Up to 46% of people with an IPAA have at least one episode of pouch inflammation (pouchitis), which the Lancet review's authors say shows that colectomy should not be presented as a cure for ulcerative colitis (Ungaro 2017).
Long-Term Care: What the Guidelines Describe
- Smoking: current smoking is associated with Crohn's disease (odds ratio 1.76) but with a lower risk of ulcerative colitis (odds ratio 0.58) (Mahid 2006). The ACG Crohn's guideline states that people with Crohn's who stop smoking have fewer flares and less need for corticosteroids and immunomodulators, and describes counselling current smokers about cessation (Lichtenstein 2025); the ulcerative colitis guideline lists recent smoking cessation among possible relapse triggers (Rubin 2025).
- Taking medicines as prescribed: the ulcerative colitis guideline reports that non-adherence is common — about 40% in the community — and is associated with a higher risk of relapse (Rubin 2025).
- NSAIDs: the Crohn's guideline states that NSAIDs may exacerbate disease activity and that their routine use is viewed with caution (Lichtenstein 2025); the ulcerative colitis guideline lists NSAID use among possible triggers (Rubin 2025).
- Monitoring inflammation: the ulcerative colitis guideline describes faecal calprotectin as an appropriate surrogate for endoscopy in assessing and monitoring inflammation of the bowel lining (Rubin 2025).
- Nutrition: the AGA update describes regular screening for malnutrition in everyone with IBD and monitoring for vitamin D and iron deficiency (Hashash 2024).
- Colorectal cancer surveillance: the Crohn's guideline recommends routine endoscopic surveillance in Crohn's colitis (strong recommendation, moderate evidence) and describes surveillance from diagnosis in people with primary sclerosing cholangitis (Lichtenstein 2025); in ulcerative colitis, the risk is related mainly to more extensive and longstanding inflammation (Rubin 2025).
- Decisions about medicines, diet and monitoring belong with the clinician who knows the person's disease.
Complications of IBD
- Strictures and bowel obstruction: most people with Crohn's disease present without strictures or penetrating disease, but in population-based cohorts up to half had developed an intestinal complication (stricture, abscess, fistula or phlegmon) within 20 years of diagnosis (Lichtenstein 2025).
- Fistulas and abscesses: about 25% of people with Crohn's develop a perirectal complication, a fistula and/or a perirectal abscess (Lichtenstein 2025).
- Severe colitis: in acute severe ulcerative colitis, toxic megacolon, perforation, uncontrolled severe bleeding and multi-organ dysfunction are the absolute indications for surgery (Rubin 2025).
- Colorectal cancer: risk is raised with colonic Crohn's disease, rising with the duration and extent of colonic involvement, primary sclerosing cholangitis, a family history of colorectal cancer and the severity of ongoing inflammation (Lichtenstein 2025). In ulcerative colitis, the Lancet review reports that the risk has decreased over time and may be approaching that of the general population, but remains raised with long disease duration, primary sclerosing cholangitis and uncontrolled inflammation (Ungaro 2017).
- Malnutrition: the AGA update describes dietary restrictions, together with the complications of IBD, as able to cause malnutrition, which it calls under-recognised in IBD (Hashash 2024).
- Extraintestinal manifestations and primary sclerosing cholangitis: peripheral arthritis is the most common extraintestinal manifestation; primary sclerosing cholangitis, a disease of the bile ducts, and pyoderma gangrenosum are more common in ulcerative colitis than in Crohn's disease (Ungaro 2017).
- Blood clots: the risk of venous thromboembolism in IBD is increased three to four times, and more so during a hospital admission for a flare (Ungaro 2017).
Key Research Papers
Historical Background
Kirsner's 1988 historical review concludes that ulcerative colitis and Crohn's disease probably first appeared as isolated cases several centuries ago, but did not attract medical interest as definable entities until the latter half of the 19th century, and that the early history of ulcerative colitis is entangled with infectious colitis (Kirsner 1988). Samuel Wilks is credited with first describing ulcerative colitis, in 1859 (Gajendran 2019). In October 1932, Crohn and colleagues published “Regional ileitis: a pathologic and clinical entity” in JAMA. In 2001, Hugot and colleagues identified variants of the NOD2 gene associated with susceptibility to Crohn's disease (Hugot 2001); by 2012 a genome-wide meta-analysis had brought the total of IBD risk loci to 163 (Jostins 2012).
- Ng SC, Shi HY, Hamidi N, et al. Worldwide incidence and prevalence of inflammatory bowel disease in the 21st century: a systematic review. The Lancet. 2017;390(10114):2769-2778. — doi:10.1016/S0140-6736(17)32448-0 (PubMed PMID: 29050646)
- Jostins L, Ripke S, Weersma RK, et al. Host-microbe interactions have shaped the genetic architecture of inflammatory bowel disease. Nature. 2012;491(7422):119-124. — doi:10.1038/nature11582 (PubMed PMID: 23128233)
- Abraham C, Cho JH. Inflammatory bowel disease. N Engl J Med. 2009;361(21):2066-2078. — doi:10.1056/NEJMra0804647 (PubMed PMID: 19923578)
- Hugot JP, Chamaillard M, Zouali H, et al. Association of NOD2 leucine-rich repeat variants with susceptibility to Crohn's disease. Nature. 2001;411(6837):599-603. — doi:10.1038/35079107 (PubMed PMID: 11385576)
- de Souza HSP, Fiocchi C, Iliopoulos D. The IBD interactome: an integrated view of aetiology, pathogenesis and therapy. Nat Rev Gastroenterol Hepatol. 2017;14(12):739-749. — doi:10.1038/nrgastro.2017.110 (PubMed PMID: 28831186)
- Sandborn WJ, Feagan BG, Rutgeerts P, et al. Vedolizumab as induction and maintenance therapy for Crohn's disease (GEMINI 2). N Engl J Med. 2013;369(8):711-721. — doi:10.1056/NEJMoa1215739 (PubMed PMID: 23964933)
- Feagan BG, Sandborn WJ, Gasink C, et al. Ustekinumab as induction and maintenance therapy for Crohn's disease. N Engl J Med. 2016;375(20):1946-1960. — doi:10.1056/nejmoa1602773 (PubMed PMID: 27959607)
- Gomollón F, Dignass A, Annese V, et al. 3rd European evidence-based consensus on the diagnosis and management of Crohn's disease 2016: Part 1: diagnosis and medical management (ECCO). J Crohns Colitis. 2017;11(1):3-25. — doi:10.1093/ecco-jcc/jjw168 (PubMed PMID: 27660341)
- Rubin DT, Ananthakrishnan AN, Siegel CA, et al. ACG clinical guideline: ulcerative colitis in adults. Am J Gastroenterol. 2019;114(3):384-413. Updated by the 2025 guideline below. — doi:10.14309/ajg.0000000000000152 (PubMed PMID: 30840605)
- Kaplan GG. The global burden of IBD: from 2015 to 2025. Nat Rev Gastroenterol Hepatol. 2015;12(12):720-727. — doi:10.1038/nrgastro.2015.150 (PubMed PMID: 26323879)
- Ananthakrishnan AN, Bernstein CN, Iliopoulos D, et al. Environmental triggers in IBD: a review of progress and evidence. Nat Rev Gastroenterol Hepatol. 2018;15(1):39-49. — doi:10.1038/nrgastro.2017.136 (PubMed PMID: 29018271)
- Ordas I, Eckmann L, Talamini M, Baumgart DC, Sandborn WJ. Ulcerative colitis. The Lancet. 2012;380(9853):1606-1619. — doi:10.1016/S0140-6736(12)60150-0 (PubMed PMID: 22914296)
- Torres J, Mehandru S, Colombel JF, Peyrin-Biroulet L. Crohn's disease. The Lancet. 2017;389(10080):1741-1755. — doi:10.1016/S0140-6736(16)31711-1 (PubMed PMID: 27914655)
- Ungaro R, Mehandru S, Allen PB, Peyrin-Biroulet L, Colombel JF. Ulcerative colitis. The Lancet. 2017;389(10080):1756-1770. — doi:10.1016/S0140-6736(16)32126-2 (PubMed PMID: 27914657)
- Lichtenstein GR, Loftus EV, Afzali A, et al. ACG clinical guideline: management of Crohn's disease in adults. Am J Gastroenterol. 2025;120(6):1225-1264. — doi:10.14309/ajg.0000000000003465 (PubMed PMID: 40701562)
- Rubin DT, Ananthakrishnan AN, Siegel CA, Barnes EL, Long MD. ACG clinical guideline update: ulcerative colitis in adults. Am J Gastroenterol. 2025;120(6):1187-1224. — doi:10.14309/ajg.0000000000003463 (PubMed PMID: 40701556) (correction published 2026: PubMed PMID: 41384833)
- Mahid SS, Minor KS, Soto RE, Hornung CA, Galandiuk S. Smoking and inflammatory bowel disease: a meta-analysis. Mayo Clin Proc. 2006;81(11):1462-1471. — doi:10.4065/81.11.1462 (PubMed PMID: 17120402)
- Hashash JG, Elkins J, Lewis JD, Binion DG. AGA clinical practice update on diet and nutritional therapies in patients with inflammatory bowel disease: expert review. Gastroenterology. 2024;166(3):521-532. — doi:10.1053/j.gastro.2023.11.303 (PubMed PMID: 38276922)
- Levine A, Rhodes JM, Lindsay JO, et al. Dietary guidance from the International Organization for the Study of Inflammatory Bowel Diseases. Clin Gastroenterol Hepatol. 2020;18(6):1381-1392. — doi:10.1016/j.cgh.2020.01.046 (PubMed PMID: 32068150)
- Wedlake L, Slack N, Andreyev HJ, Whelan K. Fiber in the treatment and maintenance of inflammatory bowel disease: a systematic review of randomized controlled trials. Inflamm Bowel Dis. 2014;20(3):576-586. — doi:10.1097/01.MIB.0000437984.92565.31 (PubMed PMID: 24445775)
- Narula N, Wong ECL, Dehghan M, et al. Association of ultra-processed food intake with risk of inflammatory bowel disease: prospective cohort study. BMJ. 2021;374:n1554. — doi:10.1136/bmj.n1554 (PubMed PMID: 34261638)
- Chassaing B, Koren O, Goodrich JK, et al. Dietary emulsifiers impact the mouse gut microbiota promoting colitis and metabolic syndrome. Nature. 2015;519(7541):92-96. — doi:10.1038/nature14232 (PubMed PMID: 25731162) — a corrigendum was published in 2016 (PubMed PMID: 27144359)
- Fitzpatrick JA, Gibson PR, Taylor KM, et al. Clinical trial: the effects of emulsifiers in the food supply on disease activity in Crohn's disease: an exploratory double-blinded randomised feeding trial. Aliment Pharmacol Ther. 2025;61(8):1276-1289. — doi:10.1111/apt.70041 (PubMed PMID: 39967287)
- Bancil A, Rossi M, Sandall A, et al. DOP097 Emulsifier restriction is an effective therapy for active Crohn's disease: the ADDapt trial – a multi-centre, randomised, double-blind, placebo-controlled, re-supplementation trial in 154 patients. J Crohns Colitis. 2025;19(Suppl 1):i262. Conference abstract, not a full peer-reviewed paper. — doi:10.1093/ecco-jcc/jjae190.0136
- Crohn BB, et al. Regional ileitis: a pathologic and clinical entity. JAMA. 1932;99(16):1323. — doi:10.1001/jama.1932.02740680019005
- Kirsner JB. Historical aspects of inflammatory bowel disease. J Clin Gastroenterol. 1988;10(3):286-297. — doi:10.1097/00004836-198806000-00012 (PubMed PMID: 2980764)
- Gajendran M, Loganathan P, Jimenez G, et al. A comprehensive review and update on ulcerative colitis. Dis Mon. 2019;65(12):100851. — doi:10.1016/j.disamonth.2019.02.004 (PubMed PMID: 30837080)
PubMed Topic Searches
Curated PubMed topic searches of peer-reviewed literature on Inflammatory Bowel Disease (IBD). Each link opens a live PubMed query so you always see the most current studies.
- PubMed: IBD epidemiology
- PubMed: Biologic therapy in IBD
- PubMed: Microbiome dysbiosis in IBD
- PubMed: Vedolizumab in IBD
- PubMed: Ustekinumab in IBD
- PubMed: Surgical outcomes in IBD
- PubMed: CRC surveillance in IBD
- PubMed: Fecal calprotectin
- PubMed: Diet and nutrition in IBD
- PubMed: Pediatric IBD management
- PubMed: Extraintestinal manifestations
- PubMed: JAK inhibitors in IBD
Connections
- Gastroenterology
- Crohn's vs Ulcerative Colitis: Key Differences
- Diagnostic Workup: Calprotectin, Colonoscopy, MRE
- Biologics: TNF, IL-23, and Integrin Inhibitors
- JAK Inhibitors and S1P Modulators
- Diet for IBD: SCD and Mediterranean
- IBD Surgery Decisions
- Extraintestinal Manifestations: Joints, Skin, Eyes
- IBD Fatigue, Anemia, and Nutrient Deficiencies
- Pregnancy and IBD: Fertility, Medications, Outcomes
- Crohn's Disease
- Ulcerative Colitis
- SIBO
- Celiac Disease
- Irritable Bowel Syndrome
- Ankylosing Spondylitis
- Gut-Brain Axis
- Elimination Diet
- Ultra-Processed Foods
- Colorectal Cancer
- Hemorrhoids
- Herbs covered on this site that discuss this condition: Oregano (Origanum vulgare) · Slippery Elm · Tamarind (Tamarindus indica) · Turmeric (Curcuma longa)
- Dr. Bryan Ardis: Nicotine and Ulcerative Colitis
- Probiotics
Featured Videos