Crohn's Disease
Interactive Visualization The Gut Barrier & Your Microbiome Watch fibre become butyrate and butyrate tighten the gut wall — then starve the microbes and see them eat your mucus layer instead. Launch →
Table of Contents
- What is Crohn’s Disease?
- What Goes Wrong in the Gut Wall
- Where It Strikes, and the Three Behaviours
- Common Symptoms of Crohn’s Disease
- How It Varies Between People
- Causes and Risk Factors
- Diagnosis: The Tests and the Numbers
- Monitoring: Why Feeling Well Is Not Enough
- Treatment Options
- Surgery, and What It Can and Cannot Do
- Diet and Nutrition: What the Trials Show
- What the Evidence Does Not Support
- Long-Term Care: What the Guidelines Describe
- Red Flags: When It Is Urgent
- Complications of Crohn’s Disease
- Key Research Papers
- Connections
- Featured Videos
What is Crohn’s Disease?
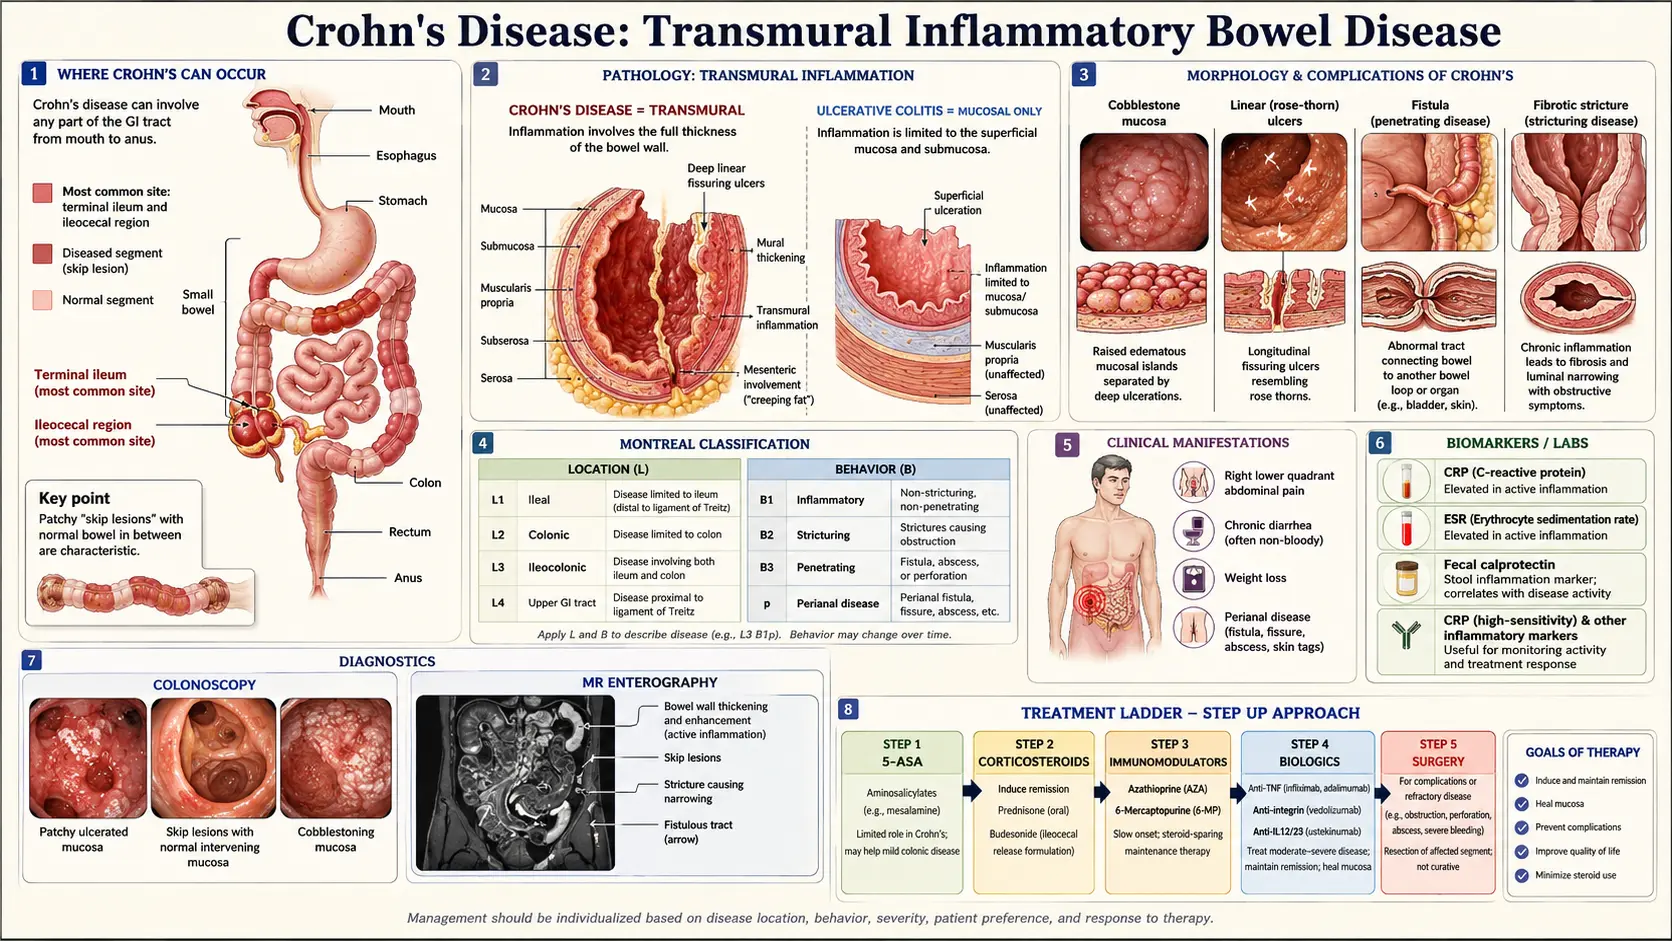
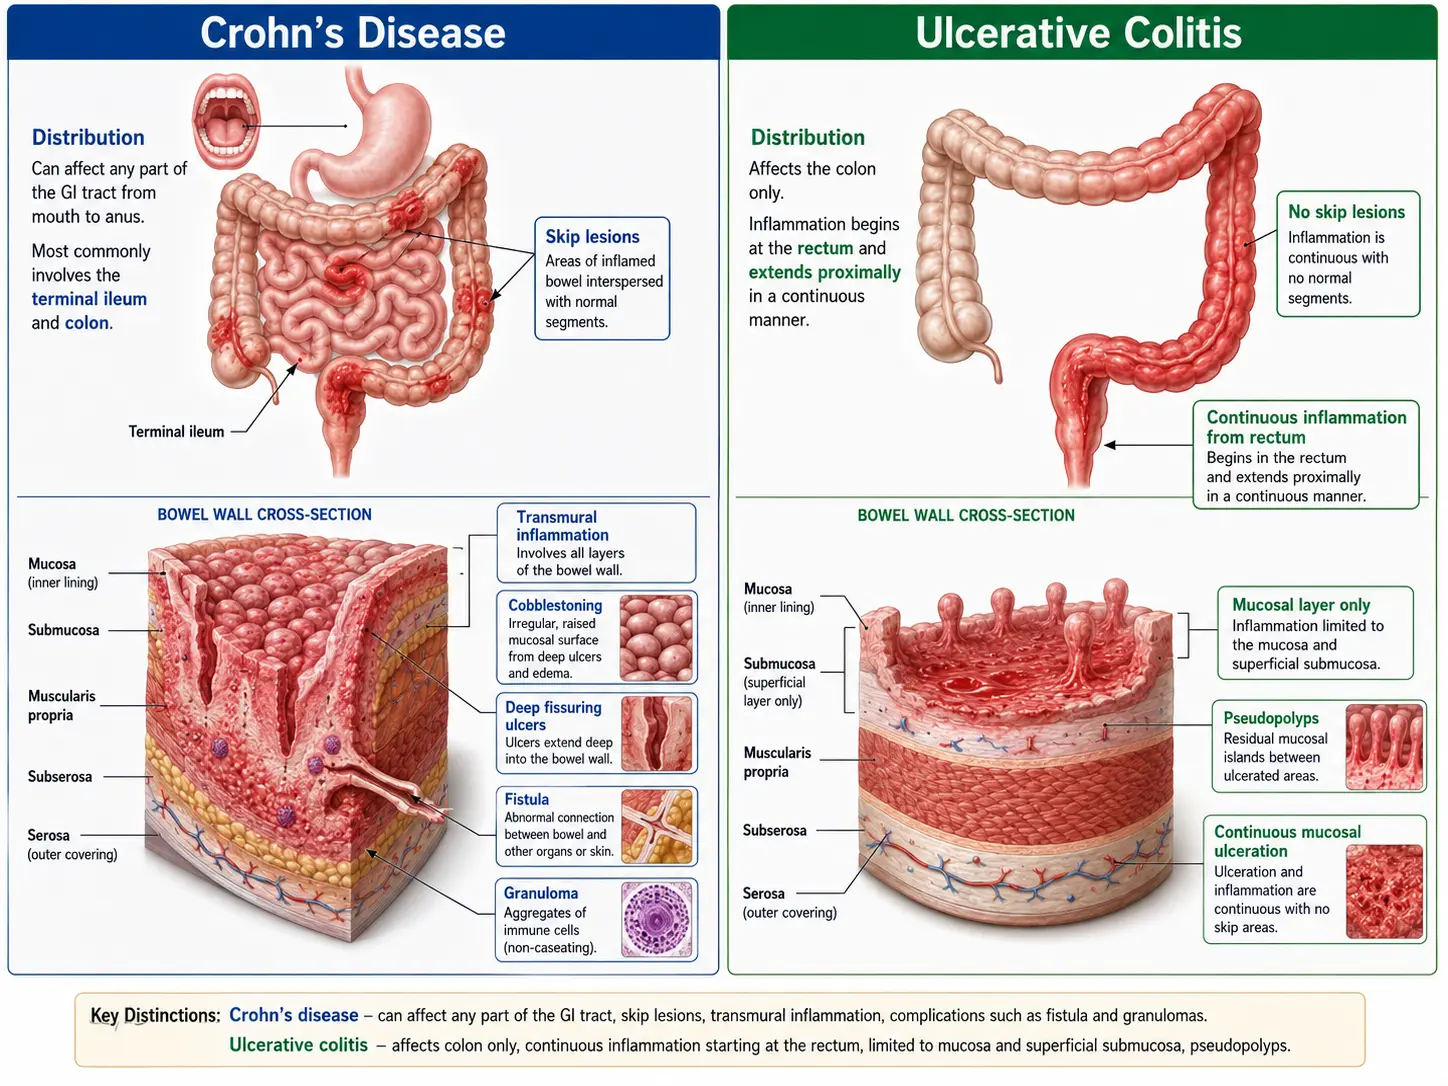
Crohn’s disease is a chronic inflammatory disease of the gastrointestinal tract. The 2025 American College of Gastroenterology (ACG) guideline describes its defining finding as focal, asymmetric, transmural granulomatous inflammation — inflammation that can run through the full thickness of the bowel wall — and states that there is no single laboratory test that can make the diagnosis.
The ACG guideline describes Crohn’s, in most cases, as a chronic, progressive, destructive disease: over time the inflammation can lead to strictures (narrowing), fistulas (abnormal tunnels, for example between bowel loops, to the bladder or to the vagina) and abscesses. Most people present with non-stricturing, non-penetrating disease, but in population-based cohorts up to half had developed one of these intestinal complications within 20 years of diagnosis. The guideline names small-bowel obstruction from a fibrotic stricture as the most common reason for an intestinal resection.
Inflammation is often patchy. Clues the ACG guideline lists for telling Crohn’s colitis apart from ulcerative colitis include discontinuous involvement with skip areas, sparing of the rectum, deep or linear ulcers, strictures, fistulas and granulomatous inflammation.
Ng and colleagues’ 2017 Lancet systematic review of population-based studies found that most studies from North America and Europe reported stable or decreasing incidence, while prevalence there exceeded 0.3%; since 1990, incidence has been rising in newly industrialised countries in Africa, Asia and South America, including Brazil and Taiwan. The authors described IBD as a global disease with accelerating incidence in newly industrialised countries whose societies have become more westernised.
What Goes Wrong in the Gut Wall
Torres and colleagues’ 2017 Lancet seminar describes Crohn’s as possibly resulting from a complex interplay between genetic susceptibility, environmental factors and altered gut microbiota, leading to dysregulated innate and adaptive immune responses. The research on each element:
- Genetic susceptibility. In 2001 Hugot and colleagues (Nature) identified variants of NOD2 associated with Crohn’s; the gene’s protein acts as an intracellular receptor for components of microbial pathogens, and the authors proposed that the variants alter recognition of these components. Jostins and colleagues’ 2012 Nature meta-analysis of more than 75,000 cases and controls brought the total to 163 IBD loci, highlighted mechanisms such as autophagy, and found considerable overlap with susceptibility loci for mycobacterial infection.
- A leaky barrier. In a prospective study of 1,420 healthy first-degree relatives of people with Crohn’s (Turpin 2020), abnormal intestinal permeability at recruitment was associated with a later Crohn’s diagnosis (hazard ratio 3.03), including when measured more than three years before diagnosis — findings the authors described as supporting a model in which altered barrier function contributes to the disease.
- An altered microbiome (dysbiosis). A reduction of the bacterium Faecalibacterium prausnitzii on resected ileal tissue was associated with a higher risk of post-operative recurrence, and the bacterium showed anti-inflammatory effects in cell and mouse models (Sokol 2008). Adherent-invasive E. coli were found in 21.7% of chronic ileal Crohn’s lesions versus 6.2% of controls, and the authors described them as associated specifically with ileal mucosa (Darfeuille-Michaud 2004).
- Environmental factors — smoking, a preceding gastroenteritis, antibiotic exposure and NSAIDs are each covered under Causes and Risk Factors below.
The drug classes used in Crohn’s each target one part of this immune response: infliximab and adalimumab block tumour necrosis factor (TNF)-α; ustekinumab blocks the p40 subunit shared by interleukin (IL)-12 and IL-23; risankizumab blocks the p19 subunit of IL-23; vedolizumab blocks α4β7 integrin, which guides immune cells into the gut; and upadacitinib inhibits the Janus kinase (JAK) signalling enzyme JAK-1.
Where It Strikes, and the Three Behaviours
Clinicians describe Crohn’s by where it occurs (location) and what it does to the bowel (behaviour); the ACG guideline uses both to estimate the risk of progression.
Location
- Ileal, ileocolonic or colonic — population-based studies from Norway and Minnesota cited by the ACG guideline found roughly one-third of patients in each group, and only a small minority (6–14%) changed location over time.
- Upper gastrointestinal involvement (oesophagus, stomach or duodenum) — up to a quarter in those studies. Ileal, ileocolonic and upper GI involvement were each significantly more likely than isolated colonic disease to progress to an intestinal complication.
- Perianal disease — fistulas and abscesses around the anus. The ACG guideline states that perianal fistulizing disease occurs in up to one-quarter of patients; population-based cohorts report 10–26%.
Behaviour
- Inflammatory (non-stricturing, non-penetrating) — 56–81% of patients at diagnosis across population-based cohorts.
- Stricturing — narrowing that can cause obstruction; 5–25% at diagnosis.
- Penetrating — fistula and abscess formation; 5–25% at diagnosis.
In an Olmsted County, Minnesota cohort cited by the guideline, the cumulative risk of developing an intestinal complication among people who started with inflammatory behaviour was 51% at 20 years. Preventing that progression is the stated aim of current treatment strategies, which Torres and colleagues describe as deep and long-lasting remission with the goal of preventing complications such as surgery.
Common Symptoms of Crohn’s Disease
The ACG guideline lists the following hallmark and presenting features:
- Chronic diarrhoea — the most common symptom, although some patients do not have it.
- Abdominal pain, often in the right lower abdomen and worse after eating.
- Fatigue — described as very prevalent, attributed to inflammation itself, anaemia, or vitamin and mineral deficiencies.
- Weight loss and fever.
- Growth failure in younger patients.
- Anaemia and recurrent fistulas.
- Perianal symptoms — rectal pain or problems with defecation may be associated with perianal disease.
- Extra-intestinal features — arthritis (axial and peripheral), skin conditions (pyoderma gangrenosum and erythema nodosum), eye inflammation (uveitis, scleritis, episcleritis) and primary sclerosing cholangitis.
How It Varies Between People
- Time to diagnosis. A 2023 meta-analysis of 101 studies (Jayasooriya) found a median time from symptom onset to diagnosis of 8.0 months in Crohn’s (6.2 months in high-income countries, 11.7 months in low-middle-income countries). In Crohn’s, delayed diagnosis was associated with higher odds of stricturing disease (OR 1.88), penetrating disease (OR 1.64) and intestinal surgery (OR 2.24).
- Risk factors for progression listed by the ACG guideline include young age at diagnosis, ileal location, initial extensive bowel involvement, perianal or severe rectal disease, deep ulcers, and a stricturing or penetrating pattern at diagnosis.
- Smoking behaves oppositely in the two forms of IBD. In Mahid and colleagues’ 2006 meta-analysis, current smoking was associated with Crohn’s (OR 1.76) and with a lower risk of ulcerative colitis (OR 0.58). The ACG guideline states that smoking exacerbates Crohn’s activity and accelerates recurrence, and that patients who stop smoking have fewer flares and less need for corticosteroids and immunomodulators.
- Symptoms and inflammation are poorly correlated. The ACG guideline cites a cross-sectional study of 164 patients in which symptom scores (CDAI) correlated neither with endoscopic scores nor with CRP, faecal calprotectin or faecal lactoferrin.
- Overlapping IBS-type symptoms. A 2020 meta-analysis (Fairbrass) found IBS-type symptoms in 32.5% of people with IBD in remission, 36.6% in Crohn’s; even when remission was confirmed endoscopically or histologically, about a quarter reported them. These symptoms were associated with higher anxiety and depression scores.
- Perianal disease has its own treatment pathway: the ACG guideline describes drainage of abscesses with setons before advanced therapy, and recommends infliximab for perianal fistulizing disease.
Causes and Risk Factors
- Genetics and family — in a Swedish nationwide study of 111,080 twins (Grännö 2026), concordance for Crohn’s was 0.30 in identical twins and 0.02 in non-identical twins, with heritability estimated at 0.78.
- Smoking — associated with Crohn’s (OR 1.76, Mahid 2006); the ACG guideline lists more surgery, more IBD hospitalisations and a penetrating phenotype among smokers.
- Migration to a high-incidence country — in Ontario, immigrants had a lower IBD incidence than non-immigrants (incidence rate ratio 0.34), but younger age at arrival increased risk, and Canadian-born children of immigrants from several regions had a risk similar to children of non-immigrants. The authors interpreted this as underlying risk being activated by earlier-life exposure to the Canadian environment (Benchimol 2015).
- Antibiotic exposure — a 2014 meta-analysis of 11 observational studies found antibiotic exposure associated with Crohn’s (OR 1.74) but not ulcerative colitis, most markedly in children (OR 2.75) (Ungaro 2014).
- A preceding gastroenteritis — in a UK primary-care cohort, IBD risk was higher after an episode of infectious gastroenteritis (hazard ratio 2.4), and the excess risk was greatest in the first year (García Rodríguez 2006).
- NSAIDs — the ACG guideline states that NSAIDs may exacerbate disease activity and can damage the small intestine.
- Diet — in a 21-country cohort of 116,087 adults, higher ultra-processed food intake was associated with a higher risk of IBD (Narula 2021); in the Nurses’ Health Study, the highest quintile of long-term fibre intake, particularly fibre from fruit, was associated with a 40% lower risk of Crohn’s (Ananthakrishnan 2013). In the Narula cohort, intake of fruit, vegetables and legumes was not associated with IBD. These are associations, not proven causes.
- Appendicectomy — a 2008 meta-analysis found a higher risk of Crohn’s after appendicectomy, highest in the first year and back to baseline after five years; the authors concluded this early excess likely reflects diagnostic problems in patients whose Crohn’s was already starting (Kaplan 2008).
- Stress, anxiety and depression — the ACG guideline describes increased risks of disease activity and health-care use among patients with these conditions and recommends assessing and managing them as part of care.
Diagnosis: The Tests and the Numbers
The ACG guideline states that Crohn’s is diagnosed clinically, with no truly pathognomonic feature: the clinician integrates history, laboratory tests, endoscopy, pathology and imaging.
Stool and blood tests
- Faecal calprotectin — a neutrophil protein measured in stool. The ACG guideline recommends a cutoff of more than 50–100 µg/g to separate inflammatory from non-inflammatory disease of the colon (strong recommendation, moderate evidence), citing a meta-analysis in which a level of 50 µg/g had a sensitivity of 88% and a specificity of 72% for distinguishing IBD from functional gut disease.
- CRP — elevated in a subset of patients; its short half-life (19 hours) makes it useful for detecting and monitoring inflammation.
- Full blood count — anaemia and a raised platelet count are the most common changes.
- Stool testing in active symptoms — the ACG guideline lists faecal pathogens, Clostridioides difficile testing and a marker of gut inflammation such as calprotectin; it notes that C. difficile infection risk may be up to five-fold higher in people with IBD.
- Assessment for anaemia, dehydration and malnutrition is part of the ACG laboratory work-up.
Endoscopy
- Ileocolonoscopy with biopsies is recommended by the ACG guideline in the assessment of suspected Crohn’s, including biopsies of normal-looking mucosa and photographs of the ileum. Classical granulomatous inflammation is seen in a minority (up to 33%) and is helpful but not required for the diagnosis.
- Upper endoscopy is described for patients with upper GI complaints.
- Capsule endoscopy is described as a useful adjunct for small-bowel disease; in patients with obstructive symptoms, the guideline describes small-bowel imaging or a patency capsule first, to lower the risk of the capsule being retained.
Imaging
- MR and CT enterography — the ACG guideline describes small-bowel imaging as part of the initial work-up, CT enterography as comparable with MR enterography, and MR enterography as preferred in people younger than 35 and in those likely to need repeated scans, because it involves no radiation.
- Intestinal ultrasound — described as a non-invasive, radiation-free way to assess the bowel wall and an adjunct for diagnosis and for monitoring response.
- CT can help direct the drainage of an abscess.
- Pelvic MRI or endoscopic ultrasound — for perianal fistulas; the guideline describes endoscopic ultrasound as more than 90% accurate and pelvic MRI as comparably accurate.
What else it might be
Conditions the ACG guideline lists as able to produce symptoms indistinguishable from active Crohn’s include bile salt diarrhoea, intestinal infection, small intestinal bacterial overgrowth, bypass from a fistula, dietary intolerances, disorders of gut–brain interaction, medication side effects, endometriosis and tuberculosis. Before anti-TNF therapy, the guideline describes pretreatment screening for infections, including testing for latent and active tuberculosis and for hepatitis B.
Monitoring: Why Feeling Well Is Not Enough
Because symptoms and inflammation can diverge, current strategies combine symptom relief with objective measures, an approach usually called treat to target. The STRIDE-II consensus of the International Organization for the Study of IBD (2021) set symptomatic relief and normalisation of serum and faecal markers (CRP and calprotectin) as short-term targets, and clinical remission and endoscopic healing as long-term targets, adding absence of disability, restored quality of life and normal growth in children.
The ACG guideline notes that few studies have examined the long-term impact of endoscopic healing, but that in early-stage Crohn’s, complete endoscopic healing after two years of therapy predicted sustained steroid-free remission three and four years out, and that mucosal healing has been associated with lower rates of surgery and hospitalisation. It describes faecal markers as potentially useful for monitoring disease activity and response to treatment.
Therapeutic drug monitoring — measuring the blood level of an anti-TNF drug and testing for anti-drug antibodies — is described by the ACG guideline as very common, especially when someone who first responded later loses response; it distinguishes mechanistic failure, immune-mediated (antibody-related) failure and non-immune-mediated failure, which point to different next steps.
Treatment Options
The 2025 ACG guideline suggests against requiring failure of conventional therapy before starting advanced therapy (conditional recommendation, low evidence). The trial results and guideline statements below are reported as published; decisions about medicines belong with a clinician.
Inducing remission
- Corticosteroids — the ACG guideline recommends oral corticosteroids for short-term induction in moderately to severely active disease, and controlled ileal-release budesonide 9 mg daily for mildly to moderately active ileocaecal disease; budesonide’s extensive first-pass metabolism in the liver minimises systemic exposure. The guideline lists severe infections, accelerated bone loss, raised blood glucose, glaucoma, weight gain, venous thromboembolism (five-fold increased risk) and cardiovascular disease among corticosteroid adverse events, even with short-term use.
- Exclusive enteral nutrition — a liquid formula as the only source of nutrition. In the 2018 Cochrane review (Narula), corticosteroids induced remission more often than enteral nutrition in adults (73% vs 45%), while in children the results favoured enteral nutrition (83% vs 61%) without reaching statistical significance in the main analysis; all of this evidence was rated very low quality, and withdrawal was most often due to inability to tolerate the formula. In a 37-child trial (Borrelli 2006), remission rates at 10 weeks were similar, but mucosal healing was more frequent with a polymeric formula (74%) than with corticosteroids (33%). The ECCO–ESPGHAN paediatric guideline lists exclusive enteral nutrition or the Crohn’s Disease Exclusion Diet with partial enteral nutrition as preferred induction options for low-risk luminal disease.
- Antibiotics — the ACG guideline states that antibiotics are not an effective treatment for luminal inflammatory Crohn’s; they are used for abscesses and other pyogenic complications, and may be added to biologics for perianal fistulas.
Maintaining remission
- Thiopurines — azathioprine and mercaptopurine. The ACG guideline recommends against them for induction because of their slow onset of action (8–12 weeks), suggests them for maintenance after steroid induction (conditional, low evidence), recommends TPMT testing before starting, and notes that NUDT15 and TPMT variants are associated with thiopurine-induced leukopenia. They are also used alongside anti-TNF drugs to reduce immunogenicity (antibody formation).
- Methotrexate — suggested by the ACG guideline for maintenance after steroid induction, up to 25 mg once weekly by injection (conditional, moderate evidence).
- Anti-TNF antibodies — infliximab, adalimumab and certolizumab pegol, recommended by the ACG guideline for induction and maintenance. In ACCENT I (Hanauer, Lancet 2002), among people who responded to a first infliximab infusion, 39% (5 mg/kg) and 45% (10 mg/kg) of those continued on infusions every 8 weeks were in remission at week 30, versus 21% switched to placebo. In SONIC (Colombel, NEJM 2010), in patients naive to both drugs, corticosteroid-free remission at week 26 was reached by 56.8% on combination therapy, 44.4% on infliximab alone and 30.0% on azathioprine alone; the ACG guideline recommends the combination over either drug alone in such patients.
- Vedolizumab — blocks α4β7 integrin. In GEMINI 2 (Sandborn, NEJM 2013), 14.5% on vedolizumab versus 6.8% on placebo were in remission at week 6, and among responders 39.0% (every 8 weeks) and 36.4% (every 4 weeks) versus 21.6% on placebo were in remission at week 52. Serious adverse events (24.4% vs 15.3%) and serious infections (5.5% vs 3.0%) were more common with vedolizumab in that trial.
- Ustekinumab — blocks the p40 subunit of IL-12 and IL-23. In the UNITI trials (Feagan, NEJM 2016), response at week 6 was higher than placebo both in people who had failed anti-TNF drugs (UNITI-1) and in those who had failed conventional therapy (UNITI-2); 53.1% (every 8 weeks) and 48.8% (every 12 weeks) versus 35.9% on placebo were in remission at week 44, with similar adverse-event rates across groups.
- Risankizumab — a selective IL-23 (p19) inhibitor. In the ADVANCE and MOTIVATE induction trials (D’Haens, Lancet 2022), all co-primary endpoints of clinical remission and endoscopic response at week 12 were met with both doses; in the FORTIFY maintenance trial (Ferrante, Lancet 2022), 52% on 360 mg versus 41% withdrawn to placebo were in clinical remission at week 52. The ACG guideline recommends risankizumab for induction and maintenance, and also recommends the IL-23 inhibitors mirikizumab and guselkumab.
- JAK inhibitors — upadacitinib is taken orally. In U-EXCEL and U-EXCEED (Loftus, NEJM 2023), clinical remission at week 12 was 49.5% vs 29.1% and 38.9% vs 21.1% versus placebo; herpes zoster was more frequent on upadacitinib and gastrointestinal perforations occurred in upadacitinib-treated patients. The ACG guideline recommends it for patients previously exposed to anti-TNF agents. The US prescribing information carries a boxed warning for serious infections, mortality, malignancy, major adverse cardiovascular events and thrombosis.
Supportive treatment
- Iron deficiency and anaemia — anaemia is among the most common blood-count changes in Crohn’s (ACG); the diagnosis and management are the subject of a dedicated 2015 European consensus (Dignass, J Crohns Colitis).
- Vitamin B12 — a 2014 systematic review of 42 studies (Battat) found that Crohn’s without ileal resection, regardless of ileal involvement, did not increase the risk of B12 deficiency; ileal resections longer than 30 cm were associated with deficiency and those shorter than 20 cm were not, and the authors concluded that only resections longer than 20 cm warrant treatment.
- Bile acid diarrhoea — the 2020 Canadian Association of Gastroenterology guideline lists terminal ileal resection as a risk factor, suggests testing in people with Crohn’s without inflammation, suggests cholestyramine as initial therapy when testing is positive, but suggests against bile acid sequestrants for patients with extensive ileal Crohn’s or resection; nearly all its recommendations rest on very low-certainty evidence.
- Bone health — a systematic review cited by the ACG guideline found a 30–40% higher fracture risk in adults with Crohn’s.
- Vaccination — the ACG guideline describes hepatitis B vaccination for seronegative patients, ideally before biologics, and other vaccinations (pneumococcal, varicella, HPV, inactivated influenza, hepatitis A, SARS-CoV-2 and herpes zoster) ideally before biologic therapy; it states that live attenuated vaccines should be avoided in people on immunomodulators or biologics.
- Skin cancer — the ACG guideline lists non-melanoma skin cancer among thiopurine adverse effects, with risk rising with ongoing use, longer exposure and older age.
Surgery, and What It Can and Cannot Do
The ACG guideline gives the 10-year cumulative risk of major abdominal surgery as 40–55%, with biologic-era studies suggesting about 30%; a meta-analysis it cites found the 10-year risk fell from 46.5% before 2000 to 26.2% after 2000. The guideline states that surgery is not considered a failure of medication.
- When surgery is required — the ACG guideline lists intractable haemorrhage, perforation, persisting or recurrent obstruction, abscess, dysplasia or cancer, and medically refractory disease. It describes surgery as an option for symptomatic disease limited to a short segment of bowel.
- Early resection versus a biologic — in the LIR!C trial (Ponsioen 2017), 143 adults with limited (under 40 cm), non-stricturing ileocaecal disease in whom conventional therapy had failed were randomised to laparoscopic resection or infliximab. Quality of life at 12 months did not differ significantly; over a median of 4 years, 37% of the infliximab group had a resection and 26% of the resection group received an anti-TNF drug. The authors concluded that resection could be considered a reasonable alternative to infliximab in this group.
- What it cannot do — cure. The ACG guideline gives a 5-year symptomatic recurrence rate after surgery of about 50% and states that the risk of endoscopic recurrence approaches 90%; it names active smoking after surgery, penetrating disease and two or more prior surgeries as the factors carrying the greatest risk.
- Post-operative monitoring — in the POCER trial (De Cruz 2015), colonoscopy at 6 months with treatment step-up for recurrence reduced endoscopic recurrence at 18 months to 49%, versus 67% with standard care; smoking increased the risk of recurrence (OR 2.4). The ACG guideline recommends anti-TNF therapy to prevent post-operative endoscopic recurrence in high-risk patients.
- Strictureplasty — widening a stricture without removing bowel; the ACG guideline describes it as a bowel-preserving option in patients at risk of short bowel syndrome.
- Perianal fistula — the ACG guideline describes draining any abscess or complex fistula, most commonly with setons placed before immunosuppression, to increase the effectiveness of advanced therapy.
- Short bowel syndrome — in an Olmsted County cohort of 147 people who had at least one resection, the median cumulative length of bowel removed was 64 cm over a median 13.6 years of follow-up (ACG guideline).
Diet and Nutrition: What the Trials Show
The ACG guideline notes that most diet-based studies were done in children, and that in adults the benefits are often not durable, with symptoms and inflammation returning on an unrestricted diet.
- Exclusive enteral nutrition. The 2018 Cochrane review found very low-quality evidence that corticosteroids are more effective than enteral nutrition in adults and that enteral nutrition may be more effective than steroids in children; in a paediatric trial, mucosal healing was more frequent with formula than with steroids (Borrelli 2006). Details are under Treatment Options above.
- The Crohn’s Disease Exclusion Diet plus partial enteral nutrition. Levine and colleagues (Gastroenterology 2019) randomised 78 children with mild-to-moderate disease. The exclusion diet with partial formula was tolerated by 97.5% versus 73.6% on exclusive enteral nutrition (the primary endpoint). Remission at week 6 did not differ significantly (75% vs 59%), but corticosteroid-free remission at week 12 was 75.6% versus 45.1%. The diet is a whole-food diet designed to reduce exposure to dietary components the authors considered harmful to the microbiome and intestinal barrier. The ACG guideline describes it as shown in several studies to induce remission, mainly in mild-to-moderate disease.
- Specific carbohydrate versus Mediterranean diet. In the DINE-CD randomised trial in adults with mild-to-moderate Crohn’s, cited by the ACG guideline, there was no difference in symptomatic remission or biomarker response between the two diets; adherence to a Mediterranean diet for at least six months was associated with improved biomarkers and quality of life.
- Diet as primary treatment — the ACG guideline states that a primary diet-based approach should be limited to patients with limited disease and a low risk of progression, with routine monitoring.
- Ultra-processed foods and emulsifiers. In Narula and colleagues’ 2021 BMJ cohort of 116,087 adults in 21 countries, eating five or more servings of ultra-processed food a day, compared with less than one, was associated with a higher risk of IBD (hazard ratio 1.82, 95% CI 1.22–2.72), consistent for Crohn’s and ulcerative colitis; the cohort recorded 90 Crohn’s cases, and the authors called for studies to identify which components contribute. In mice, the emulsifiers carboxymethylcellulose and polysorbate-80 induced low-grade inflammation with bacteria encroaching on the protective mucus layer, and promoted colitis in mice predisposed to it (Chassaing, Nature 2015). In a controlled-feeding study of 16 healthy adults, 15 g a day of carboxymethylcellulose for 11 days modestly increased abdominal discomfort after meals, reduced microbiota diversity and faecal short-chain fatty acids, and two participants showed bacterial encroachment into the inner mucus layer (Chassaing, Gastroenterology 2022). Two 2025 trials in people with Crohn’s reported different results. In a double-blind feeding trial of 24 adults with active ileal disease (Fitzpatrick, Aliment Pharmacol Ther 2025), a high- and a low-emulsifier diet showed no statistically significant differences in any outcome over 4 weeks, and the authors concluded that recommendations to avoid emulsifiers in active Crohn’s are not supported. The larger ADDapt trial (154 patients, 8 weeks), so far reported as a conference abstract rather than a full peer-reviewed paper, found a CDAI response in 49.4% on a low-emulsifier diet versus 30.7% on the same diet with emulsifiers added back (p=0.019). The human trial evidence is therefore small and not yet consistent, and the 2025 ACG guideline makes no recommendation on emulsifiers.
- Vitamin B12 — deficiency is linked to ileal resections longer than 20–30 cm rather than to ileal disease itself (Battat 2014; see Supportive Treatment above).
What the Evidence Does Not Support
- Steroids for maintenance. A Cochrane review (Steinhart 2003) found that conventional systemic corticosteroids in quiescent Crohn’s did not appear to reduce the risk of relapse over 24 months. The ACG guideline recommends against budesonide for maintenance; a Cochrane review it cites found budesonide was not effective for maintenance beyond three months.
- Oral mesalamine (5-ASA) for Crohn’s. The ACG guideline recommends against oral mesalamine for induction or maintenance in mildly to moderately active Crohn’s (strong recommendation, moderate evidence).
- Antibiotics for luminal Crohn’s. The ACG guideline states that metronidazole is not more effective than placebo for inducing remission and that ciprofloxacin has not been shown to be more effective than placebo; neither has been shown to heal the mucosa. Anti-mycobacterial therapy aimed at Mycobacterium avium subspecies paratuberculosis has not been shown to be effective for induction, maintenance or mucosal healing, and the guideline states it should not be used to treat active Crohn’s.
- Probiotics for Crohn’s. Cochrane reviews found no evidence of a difference from placebo for inducing remission (two small trials, very low certainty; Limketkai 2020) and no evidence of benefit for maintaining remission (seven small studies; Rolfe 2006).
- Faecal microbiota transplantation. The 2023 Cochrane review (Imdad) found no trials of FMT for inducing remission in Crohn’s and one 21-person maintenance study with very uncertain results; no conclusive statements could be made for Crohn’s.
- Restrictive diets as disease treatment. A 2019 Cochrane review of 18 trials (Limketkai) found the effects of the dietary interventions studied in Crohn’s uncertain, with most trials underpowered and many at high risk of bias; the DINE-CD trial found no difference between the specific carbohydrate and Mediterranean diets.
- Smoking as protective. Current smoking was associated with a lower risk of ulcerative colitis but a higher risk of Crohn’s (Mahid 2006).
- Cannabis as a disease-modifying treatment. A 2018 Cochrane review (Kafil) found three small trials (93 participants) of cannabis or cannabis oil in active Crohn’s; one reported a higher clinical response rate and another lower symptom scores, but the effects were judged uncertain and no firm conclusions on efficacy or safety could be drawn. The review’s background notes evidence of an increased risk of surgery in people with Crohn’s who use cannabis.
Long-Term Care: What the Guidelines Describe
- Smoking. The ACG guideline states that smoking exacerbates disease activity and accelerates recurrence, that people who stop have fewer flares and less need for corticosteroids and immunomodulators, and that current smokers should be counselled and offered cessation resources.
- NSAIDs. The guideline states that NSAIDs may exacerbate disease activity and that their routine use should be viewed with caution.
- Calprotectin and other objective monitoring — described as useful for monitoring activity and response, in line with the STRIDE-II targets.
- Vaccinations — ideally given before biologic therapy; live attenuated vaccines are avoided on immunomodulators or biologics (ACG).
- Colorectal cancer surveillance. The ACG guideline recommends routine endoscopic surveillance in Crohn’s colitis (strong recommendation, moderate evidence), suggested for people with at least 8 years of disease involving more than 30% of the colon, and from the time of diagnosis in people with primary sclerosing cholangitis. Risk rises with duration and extent of disease.
- Skin checks — relevant on thiopurines, which are associated with non-melanoma skin cancer (ACG).
- Mental health. The ACG guideline recommends assessing and managing stress, depression and anxiety as part of comprehensive care.
- Pregnancy. The ACG guideline describes anti-TNF agents as safe to use during preconception planning, throughout pregnancy and postpartum, and states that methotrexate should be given to women who could become pregnant only with highly effective contraception in place.
Red Flags: When It Is Urgent
Complications the ACG guideline describes as requiring surgery or urgent treatment:
- Bowel obstruction — persisting or recurrent obstruction, most often from a fibrotic stricture, is an indication for surgery.
- Abscess — listed among the indications for surgery; broad-spectrum antibiotics are used for intra-abdominal, mesenteric and perianal abscesses.
- Perforation and intractable bleeding — both listed as indications for surgery.
- Perianal abscess — the guideline describes drainage of any fistula with an abscess.
- Infection while on immunosuppression — serious infections are a listed risk of anti-TNF drugs, corticosteroids and JAK inhibitors.
- Leg swelling or chest pain — a systematic review cited by the ACG guideline found a three-fold higher risk of thromboembolism in adults with Crohn’s.
Complications of Crohn’s Disease
- Strictures and bowel obstruction.
- Fistulas — between bowel loops (enteroenteric), to the bladder (enterovesical) or the vagina (rectovaginal) — and abscesses.
- Perianal disease; pelvic sepsis from fistulizing disease can damage the anal sphincter.
- Malnutrition, and growth failure in children.
- Anaemia.
- Metabolic bone disease and fractures (30–40% higher fracture risk).
- Colorectal cancer in colonic disease, and small-bowel adenocarcinoma in small-bowel disease (relative risk at least 18-fold, ACG).
- Venous and arterial thromboembolism.
- Short bowel syndrome after repeated resections.
- Gallstones and kidney stones — both listed among extra-intestinal complications.
- Primary sclerosing cholangitis, which also raises colorectal cancer risk.
- Treatment complications — infections, including tuberculosis, and hepatitis B reactivation on immunosuppression; non-melanoma skin cancer and lymphoproliferative disorders on thiopurines (ACG); and corticosteroid toxicity.
- Anxiety and depression, associated with increased disease activity and health-care use.
Key Research Papers
Historical background
Burrill Crohn, Leon Ginzburg and Gordon Oppenheimer published “Regional ileitis: a pathologic and clinical entity” in JAMA in October 1932. Baron’s 2000 history records that Ginzburg had been studying granulomatous diseases of the bowel at Mount Sinai Hospital in New York since 1925, working with Oppenheimer, and that the two presented a paper on non-specific granulomata of the intestine “in conjunction with Dr. Burrill B. Crohn” in May 1932, the same month Crohn presented a paper on “terminal ileitis” to the American Medical Association. Earlier descriptions exist: Van Kruiningen (2020) credits Dalziel with the first pathology description of the disease, in 1913. The first anti-TNF antibody, infliximab (then called cA2), was tested in a 1997 double-blind trial in 108 patients with treatment-resistant disease: four weeks after a single infusion, 81% of those given 5 mg/kg had a clinical response, versus 17% on placebo (Targan, NEJM 1997).
Key research papers
Each citation below was checked against its PubMed record; the linked DOI resolves to the paper named.
- Crohn BB, Ginzburg L, Oppenheimer GD. Regional ileitis: a pathologic and clinical entity. JAMA. 1932;99(16):1323–1329. — doi:10.1001/jama.1932.02740680019005
- Torres J, Mehandru S, Colombel JF, Peyrin-Biroulet L. Crohn’s disease. Lancet. 2017;389(10080):1741–1755. — doi:10.1016/S0140-6736(16)31711-1 ( PubMed PMID: 27914655)
- Ng SC, Shi HY, Hamidi N, et al. Worldwide incidence and prevalence of inflammatory bowel disease in the 21st century: a systematic review of population-based studies. Lancet. 2017;390(10114):2769–2778. — doi:10.1016/S0140-6736(17)32448-0 ( PubMed PMID: 29050646)
- Jostins L, Ripke S, Weersma RK, et al. Host–microbe interactions have shaped the genetic architecture of inflammatory bowel disease. Nature. 2012;491(7422):119–124. — doi:10.1038/nature11582 ( PubMed PMID: 23128233)
- Ananthakrishnan AN, Bernstein CN, Iliopoulos D, et al. Environmental triggers in IBD: a review of progress and evidence. Nat Rev Gastroenterol Hepatol. 2018;15(1):39–49. — doi:10.1038/nrgastro.2017.136 ( PubMed PMID: 29018271)
- Hanauer SB, Feagan BG, Lichtenstein GR, et al. Maintenance infliximab for Crohn’s disease: the ACCENT I randomised trial. Lancet. 2002;359(9317):1541–1549. — doi:10.1016/S0140-6736(02)08512-4 ( PubMed PMID: 12047962)
- Colombel JF, Sandborn WJ, Reinisch W, et al. Infliximab, azathioprine, or combination therapy for Crohn’s disease (SONIC). N Engl J Med. 2010;362(15):1383–1395. — doi:10.1056/NEJMoa0904492 ( PubMed PMID: 20393175)
- Sandborn WJ, Feagan BG, Rutgeerts P, et al. Vedolizumab as induction and maintenance therapy for Crohn’s disease (GEMINI 2). N Engl J Med. 2013;369(8):711–721. — doi:10.1056/NEJMoa1215739 ( PubMed PMID: 23964933)
- Feagan BG, Sandborn WJ, Gasink C, et al. Ustekinumab as induction and maintenance therapy for Crohn’s disease (UNITI). N Engl J Med. 2016;375(20):1946–1960. — doi:10.1056/NEJMoa1602773 ( PubMed PMID: 27959607)
- D’Haens G, Panaccione R, Baert F, et al. Risankizumab as induction therapy for Crohn’s disease: results from the phase 3 ADVANCE and MOTIVATE induction trials. Lancet. 2022;399(10340):2015–2030. — doi:10.1016/S0140-6736(22)00467-6 ( PubMed PMID: 35644154)
- Ferrante M, Panaccione R, Baert F, et al. Risankizumab as maintenance therapy for moderately to severely active Crohn’s disease: results from the multicentre, randomised, double-blind, placebo-controlled, withdrawal phase 3 FORTIFY maintenance trial. Lancet. 2022;399(10340):2031–2046. — doi:10.1016/S0140-6736(22)00466-4 ( PubMed PMID: 35644155)
- Lichtenstein GR, Loftus EV, Isaacs KL, et al. ACG clinical guideline: management of Crohn’s disease in adults. Am J Gastroenterol. 2018;113(4):481–517. — doi:10.1038/ajg.2018.27 ( PubMed PMID: 29610508)
- Torres J, Bonovas S, Doherty G, et al. ECCO guidelines on therapeutics in Crohn’s disease: medical treatment. J Crohns Colitis. 2020;14(1):4–22. — doi:10.1093/ecco-jcc/jjz180 ( PubMed PMID: 31711158)
- Levine A, Wine E, Assa A, et al. Crohn’s disease exclusion diet plus partial enteral nutrition induces sustained remission in a randomized controlled trial. Gastroenterology. 2019;157(2):440–450.e8. — doi:10.1053/j.gastro.2019.04.021 ( PubMed PMID: 31170412)
- Lichtenstein GR, Loftus EV, Afzali A, et al. ACG Clinical Guideline: Management of Crohn's Disease in Adults. Am J Gastroenterol. 2025;120(6):1225–1264. — doi:10.14309/ajg.0000000000003465 ( PubMed PMID: 40701562)
- Turner D, Ricciuto A, Lewis A, et al. STRIDE-II: An Update on the Selecting Therapeutic Targets in Inflammatory Bowel Disease (STRIDE) Initiative of the International Organization for the Study of IBD (IOIBD): Determining Therapeutic Goals for Treat-to-Target strategies in IBD. Gastroenterology. 2021;160(5):1570–1583. — doi:10.1053/j.gastro.2020.12.031 ( PubMed PMID: 33359090)
- Targan SR, Hanauer SB, van Deventer SJ, et al. A short-term study of chimeric monoclonal antibody cA2 to tumor necrosis factor alpha for Crohn's disease. Crohn's Disease cA2 Study Group. N Engl J Med. 1997;337(15):1029–35. — doi:10.1056/NEJM199710093371502 ( PubMed PMID: 9321530)
- Ponsioen CY, de Groof EJ, Eshuis EJ, et al. Laparoscopic ileocaecal resection versus infliximab for terminal ileitis in Crohn's disease: a randomised controlled, open-label, multicentre trial. Lancet Gastroenterol Hepatol. 2017;2(11):785–792. — doi:10.1016/S2468-1253(17)30248-0 ( PubMed PMID: 28838644)
- De Cruz P, Kamm MA, Hamilton AL, et al. Crohn's disease management after intestinal resection: a randomised trial. Lancet. 2015;385(9976):1406–17. — doi:10.1016/S0140-6736(14)61908-5 ( PubMed PMID: 25542620)
- Steinhart AH, Ewe K, Griffiths AM, et al. Corticosteroids for maintenance of remission in Crohn's disease. Cochrane Database Syst Rev. 2003;(4):CD000301. — doi:10.1002/14651858.CD000301 ( PubMed PMID: 14583917)
- Loftus EV Jr, Panés J, Lacerda AP, et al. Upadacitinib Induction and Maintenance Therapy for Crohn's Disease. N Engl J Med. 2023;388(21):1966–1980. — doi:10.1056/NEJMoa2212728 ( PubMed PMID: 37224198)
- Narula N, Dhillon A, Zhang D, et al. Enteral nutritional therapy for induction of remission in Crohn's disease. Cochrane Database Syst Rev. 2018;4(4):CD000542. — doi:10.1002/14651858.CD000542.pub3 ( PubMed PMID: 29607496)
- Borrelli O, Cordischi L, Cirulli M, et al. Polymeric diet alone versus corticosteroids in the treatment of active pediatric Crohn's disease: a randomized controlled open-label trial. Clin Gastroenterol Hepatol. 2006;4(6):744–53. — doi:10.1016/j.cgh.2006.03.010 ( PubMed PMID: 16682258)
- van Rheenen PF, Aloi M, Assa A, et al. The Medical Management of Paediatric Crohn's Disease: an ECCO-ESPGHAN Guideline Update. J Crohns Colitis. 2021;15(2). — doi:10.1093/ecco-jcc/jjaa161 ( PubMed PMID: 33026087)
- Shouval DS, Hojsak I, Miele E, et al. Management of pediatric Crohn's disease: an ECCO-ESPGHAN guideline update. J Crohns Colitis. 2026;20(8). — doi:10.1093/ecco-jcc/jjag084 ( PubMed PMID: 42618885)
- Narula N, Wong ECL, Dehghan M, et al. Association of ultra-processed food intake with risk of inflammatory bowel disease: prospective cohort study. BMJ. 2021;374:n1554. — doi:10.1136/bmj.n1554 ( PubMed PMID: 34261638)
- Chassaing B, Koren O, Goodrich JK, et al. Dietary emulsifiers impact the mouse gut microbiota promoting colitis and metabolic syndrome. Nature. 2015;519(7541):92–6. — doi:10.1038/nature14232 ( PubMed PMID: 25731162) — a corrigendum was published in 2016 (PubMed PMID: 27144359)
- Chassaing B, Compher C, Bonhomme B, et al. Randomized Controlled-Feeding Study of Dietary Emulsifier Carboxymethylcellulose Reveals Detrimental Impacts on the Gut Microbiota and Metabolome. Gastroenterology. 2022;162(3):743–756. — doi:10.1053/j.gastro.2021.11.006 ( PubMed PMID: 34774538)
- Fitzpatrick JA, Gibson PR, Taylor KM, et al. Clinical Trial: The Effects of Emulsifiers in the Food Supply on Disease Activity in Crohn's Disease: An Exploratory Double-Blinded Randomised Feeding Trial. Aliment Pharmacol Ther. 2025;61(8):1276–1289. — doi:10.1111/apt.70041 ( PubMed PMID: 39967287)
- Bancil A, Rossi M, Sandall A, et al. DOP097 Emulsifier restriction is an effective therapy for active Crohn’s disease: the ADDapt trial – a multi-centre, randomised, double-blind, placebo-controlled, re-supplementation trial in 154 patients. J Crohns Colitis. 2025;19(Suppl 1):i262. Conference abstract, not a full peer-reviewed paper. — doi:10.1093/ecco-jcc/jjae190.0136
- Ananthakrishnan AN, Khalili H, Konijeti GG, et al. A prospective study of long-term intake of dietary fiber and risk of Crohn's disease and ulcerative colitis. Gastroenterology. 2013;145(5):970–7. — doi:10.1053/j.gastro.2013.07.050 ( PubMed PMID: 23912083)
- Mahid SS, Minor KS, Soto RE, et al. Smoking and inflammatory bowel disease: a meta-analysis. Mayo Clin Proc. 2006;81(11):1462–71. — doi:10.4065/81.11.1462 ( PubMed PMID: 17120402)
- Ungaro R, Bernstein CN, Gearry R, et al. Antibiotics associated with increased risk of new-onset Crohn's disease but not ulcerative colitis: a meta-analysis. Am J Gastroenterol. 2014;109(11):1728–38. — doi:10.1038/ajg.2014.246 ( PubMed PMID: 25223575)
- García Rodríguez LA, Ruigómez A, Panés J. Acute gastroenteritis is followed by an increased risk of inflammatory bowel disease. Gastroenterology. 2006;130(6):1588–94. — doi:10.1053/j.gastro.2006.02.004 ( PubMed PMID: 16697722)
- Kaplan GG, Jackson T, Sands BE, et al. The risk of developing Crohn's disease after an appendectomy: a meta-analysis. Am J Gastroenterol. 2008;103(11):2925–31. — doi:10.1111/j.1572-0241.2008.02118.x ( PubMed PMID: 18775018)
- Benchimol EI, Mack DR, Guttmann A, et al. Inflammatory bowel disease in immigrants to Canada and their children: a population-based cohort study. Am J Gastroenterol. 2015;110(4):553–63. — doi:10.1038/ajg.2015.52 ( PubMed PMID: 25756238)
- Grännö O, Thunberg J, Ludvigsson JF, et al. Heritability of Crohn's disease and ulcerative colitis: a Swedish nationwide population-based twin study. J Crohns Colitis. 2026;20(4). — doi:10.1093/ecco-jcc/jjag044 ( PubMed PMID: 42018767)
- Turpin W, Lee SH, Raygoza Garay JA, et al. Increased Intestinal Permeability Is Associated With Later Development of Crohn's Disease. Gastroenterology. 2020;159(6):2092–2100.e5. — doi:10.1053/j.gastro.2020.08.005 ( PubMed PMID: 32791132)
- Hugot JP, Chamaillard M, Zouali H, et al. Association of NOD2 leucine-rich repeat variants with susceptibility to Crohn's disease. Nature. 2001;411(6837):599–603. — doi:10.1038/35079107 ( PubMed PMID: 11385576)
- Sokol H, Pigneur B, Watterlot L, et al. Faecalibacterium prausnitzii is an anti-inflammatory commensal bacterium identified by gut microbiota analysis of Crohn disease patients. Proc Natl Acad Sci U S A. 2008;105(43):16731–6. — doi:10.1073/pnas.0804812105 ( PubMed PMID: 18936492)
- Darfeuille-Michaud A, Boudeau J, Bulois P, et al. High prevalence of adherent-invasive Escherichia coli associated with ileal mucosa in Crohn's disease. Gastroenterology. 2004;127(2):412–21. — doi:10.1053/j.gastro.2004.04.061 ( PubMed PMID: 15300573)
- Jayasooriya N, Baillie S, Blackwell J, et al. Systematic review with meta-analysis: Time to diagnosis and the impact of delayed diagnosis on clinical outcomes in inflammatory bowel disease. Aliment Pharmacol Ther. 2023;57(6):635–652. — doi:10.1111/apt.17370 ( PubMed PMID: 36627691)
- Fairbrass KM, Costantino SJ, Gracie DJ, et al. Prevalence of irritable bowel syndrome-type symptoms in patients with inflammatory bowel disease in remission: a systematic review and meta-analysis. Lancet Gastroenterol Hepatol. 2020;5(12):1053–1062. — doi:10.1016/S2468-1253(20)30300-9 ( PubMed PMID: 33010814)
- Battat R, Kopylov U, Szilagyi A, et al. Vitamin B12 deficiency in inflammatory bowel disease: prevalence, risk factors, evaluation, and management. Inflamm Bowel Dis. 2014;20(6):1120–8. — doi:10.1097/MIB.0000000000000024 ( PubMed PMID: 24739632)
- Sadowski DC, Camilleri M, Chey WD, et al. Canadian Association of Gastroenterology Clinical Practice Guideline on the Management of Bile Acid Diarrhea. Clin Gastroenterol Hepatol. 2020;18(1):24–41.e1. — doi:10.1016/j.cgh.2019.08.062 ( PubMed PMID: 31526844)
- Dignass AU, Gasche C, Bettenworth D, et al. European consensus on the diagnosis and management of iron deficiency and anaemia in inflammatory bowel diseases. J Crohns Colitis. 2015;9(3):211–22. — doi:10.1093/ecco-jcc/jju009 ( PubMed PMID: 25518052)
- Limketkai BN, Iheozor-Ejiofor Z, Gjuladin-Hellon T, et al. Dietary interventions for induction and maintenance of remission in inflammatory bowel disease. Cochrane Database Syst Rev. 2019;2(2):CD012839. — doi:10.1002/14651858.CD012839.pub2 ( PubMed PMID: 30736095)
- Limketkai BN, Akobeng AK, Gordon M, et al. Probiotics for induction of remission in Crohn's disease. Cochrane Database Syst Rev. 2020;7(7):CD006634. — doi:10.1002/14651858.CD006634.pub3 ( PubMed PMID: 32678465)
- Rolfe VE, Fortun PJ, Hawkey CJ, et al. Probiotics for maintenance of remission in Crohn's disease. Cochrane Database Syst Rev. 2006;(4):CD004826. — doi:10.1002/14651858.CD004826.pub2 ( PubMed PMID: 17054217)
- Imdad A, Pandit NG, Zaman M, et al. Fecal transplantation for treatment of inflammatory bowel disease. Cochrane Database Syst Rev. 2023;4(4):CD012774. — doi:10.1002/14651858.CD012774.pub3 ( PubMed PMID: 37094824)
- Kafil TS, Nguyen TM, MacDonald JK, et al. Cannabis for the treatment of Crohn's disease. Cochrane Database Syst Rev. 2018;11(11):CD012853. — doi:10.1002/14651858.CD012853.pub2 ( PubMed PMID: 30407616)
- Baron JH. Inflammatory bowel disease up to 1932. Mt Sinai J Med. 2000;67(3):174–89. — PubMed PMID: 10828902
- Van Kruiningen HJ. What the early pathologists got wrong, and right, about the pathology of Crohn's disease: a historical perspective. APMIS. 2020;128(12):621–625. — doi:10.1111/apm.13081 ( PubMed PMID: 32956512)
PubMed Topic Searches
The following PubMed topic searches surface the current peer-reviewed literature on Crohn’s disease. Each link opens a live query; results update as new papers are indexed.
- PubMed: Search: Crohn disease
- PubMed: Search: Crohn disease treat to target
- PubMed: Search: faecal calprotectin inflammatory bowel disease
- PubMed: Search: anti-TNF therapeutic drug monitoring IBD
- PubMed: Search: perianal fistulizing Crohn disease
- PubMed: Search: exclusive enteral nutrition Crohn
- PubMed: Search: Crohn disease exclusion diet
- PubMed: Search: postoperative recurrence Crohn disease prophylaxis
- PubMed: Search: MR enterography Crohn stricture
- PubMed: Search: intestinal ultrasound inflammatory bowel disease
- PubMed: Search: NOD2 Crohn disease
- PubMed: Search: bile acid malabsorption ileal resection
- PubMed: Search: IBD pregnancy biologic safety
- PubMed: Search: inflammatory bowel disease venous thromboembolism
Connections
- Gastroenterology
- The Gut Barrier & Your Microbiome — interactive animation
- Ulcerative Colitis
- Inflammatory Bowel Disease Overview
- Celiac Disease
- Irritable Bowel Syndrome
- SIBO
- Crohn's vs Ulcerative Colitis: Key Differences
- Biologics: TNF, IL-23, and Integrin Inhibitors
- JAK Inhibitors and S1P Modulators
- Diet for IBD: SCD and Mediterranean
- Extraintestinal Manifestations: Joints, Skin, Eyes
- Chronic Diarrhea
- AS and IBD Overlap
- Ankylosing Spondylitis
- Gut Healing Protocol
- Elimination Diet
- Vitamin D3
- Zinc
- Diverticulitis
- Colorectal Cancer
- Herbs covered on this site that discuss this condition: Cat's Claw (Uncaria tomentosa) · Wormwood · Andrographis (Andrographis paniculata) · Boswellia · Aloe Vera · Chamomile (Matricaria chamomilla)
- Probiotics