Vitamin D3 (Cholecalciferol): The Sunshine Hormone, Immune Commander, and Master Gene Regulator
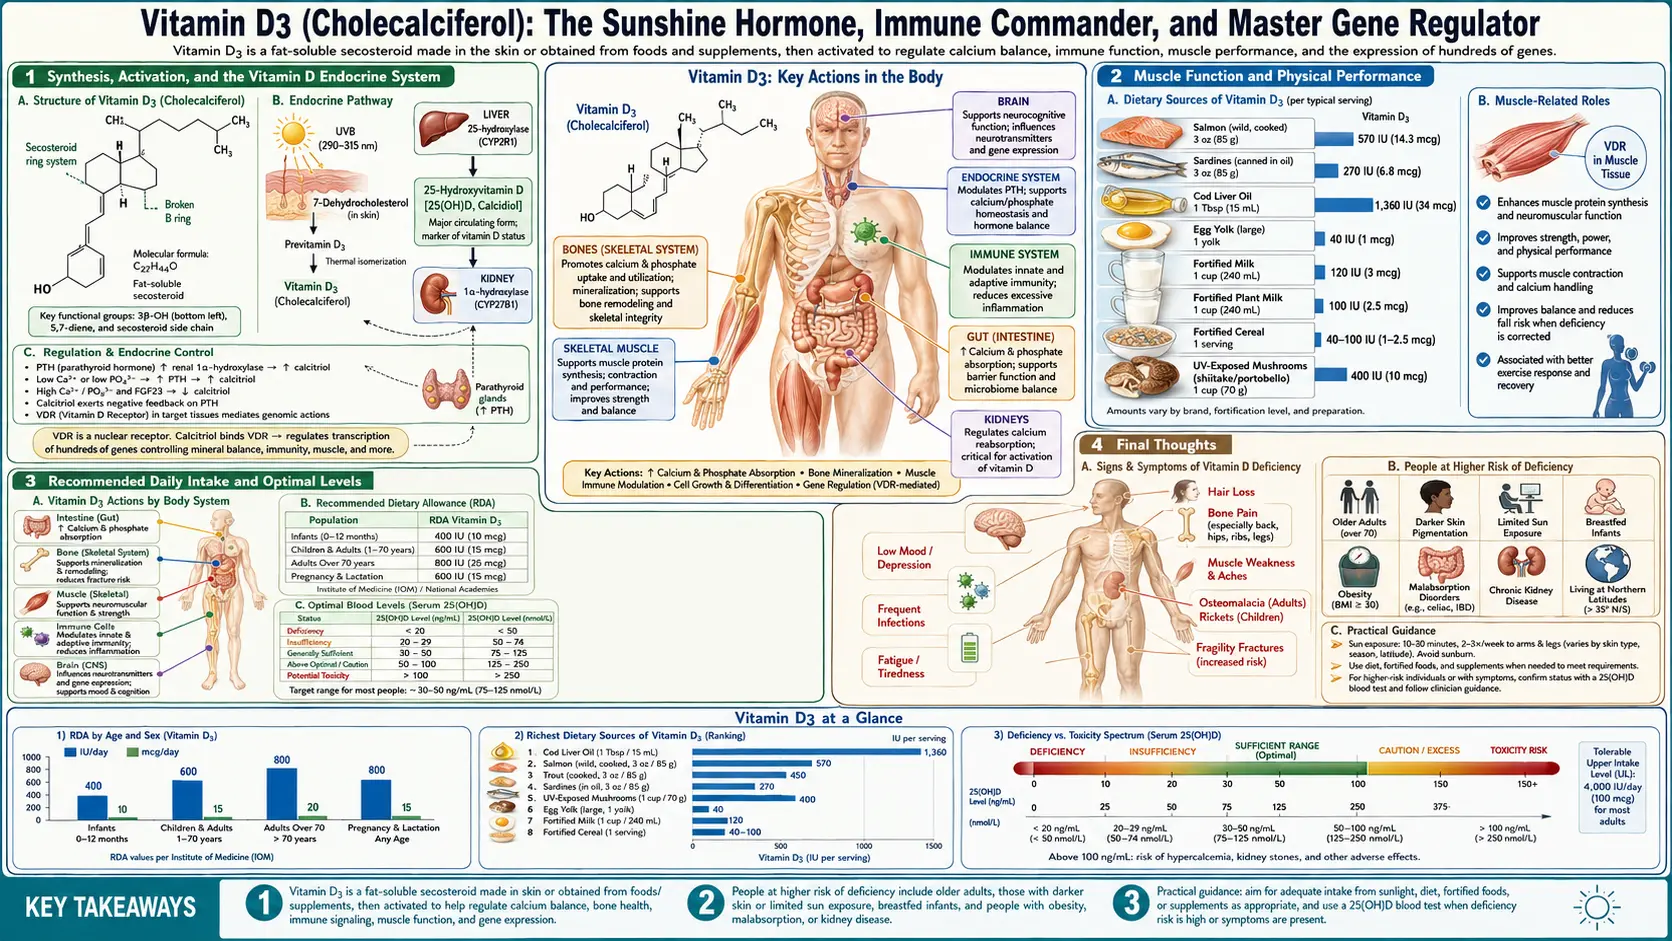
Vitamin D3, known chemically as cholecalciferol, is often described as much a hormone as a vitamin. It is a secosteroid that the skin makes when ultraviolet B (UVB) light strikes it, and that the liver and kidneys then convert into its active hormonal form, calcitriol (1,25-dihydroxyvitamin D3), which acts through the vitamin D receptor to regulate the expression of many genes. Low blood levels are common at northern latitudes, in winter, in older adults and in people with darker skin, and observational studies link low levels with osteoporosis, cancer, cardiovascular disease, autoimmune conditions, diabetes, depression, infections and earlier death. Whether supplements change those outcomes is a separate question. The 2011 Institute of Medicine (IOM) review found cause-and-effect evidence for bone health only, and large randomized trials since then — VITAL, D-Health and DO-HEALTH, in adults not selected for low vitamin D — found no reduction in cancer, cardiovascular events, fractures or death, while some trials and meta-analyses report smaller benefits for respiratory infections, autoimmune disease, cancer mortality and progression from prediabetes to diabetes. This page sets out both the biology and what the trials found.
Interactive Visualization Bone Remodeling & Calcium Balance Watch osteoclasts tunnel and osteoblasts rebuild — then drop vitamin D and see PTH quietly strip calcium out of your skeleton. Launch → Interactive Visualization How Your Skin Makes Vitamin D Hit 7-dehydrocholesterol with UVB and follow it through liver and kidney to the active hormone — then try winter, sunscreen, darker skin, or low magnesium. Launch → Interactive Visualization Sunburn & Melanin — land UV photons on DNA and watch what happens next Rain UVB onto skin and watch DNA kink into dimers — repaired, or fatal to the cell, or banked as a mutation forever — then put sunscreen on and count how many never land. Launch →Table of Contents
- Synthesis, Activation, and the Vitamin D Endocrine System
- Bone Health and Calcium-Phosphorus Homeostasis
- Immune System — Vitamin D as an Immune Modulator
- Cancer Prevention and Anticancer Mechanisms
- Mental Health — Depression, Seasonal Affective Disorder, and Cognitive Function
- Cardiovascular Health
- Blood Sugar Regulation and Diabetes
- Muscle Function and Physical Performance
- Pregnancy and Fetal Development
- Respiratory Health
- Thyroid Health
- Gut Health
- Skin Health
- Fertility and Reproductive Health
- Sources of Vitamin D3
- Recommended Daily Intake and Blood Levels
- Supplemental Forms
- Synergistic Nutrients — Proposed Partners
- Populations at Higher Risk of Deficiency
- Signs of Deficiency
- Toxicity and Safety
- Doses Described for Specific Uses
- Historical Medical Use & the Dosing Story (1926–1972)
- Final Thoughts
- Key Research Papers
- Connections
- Featured Videos
1. Synthesis, Activation, and the Vitamin D Endocrine System
Understanding Vitamin D3 begins with understanding its unique synthesis and activation pathway — a process that makes it more akin to a hormone than a traditional vitamin.
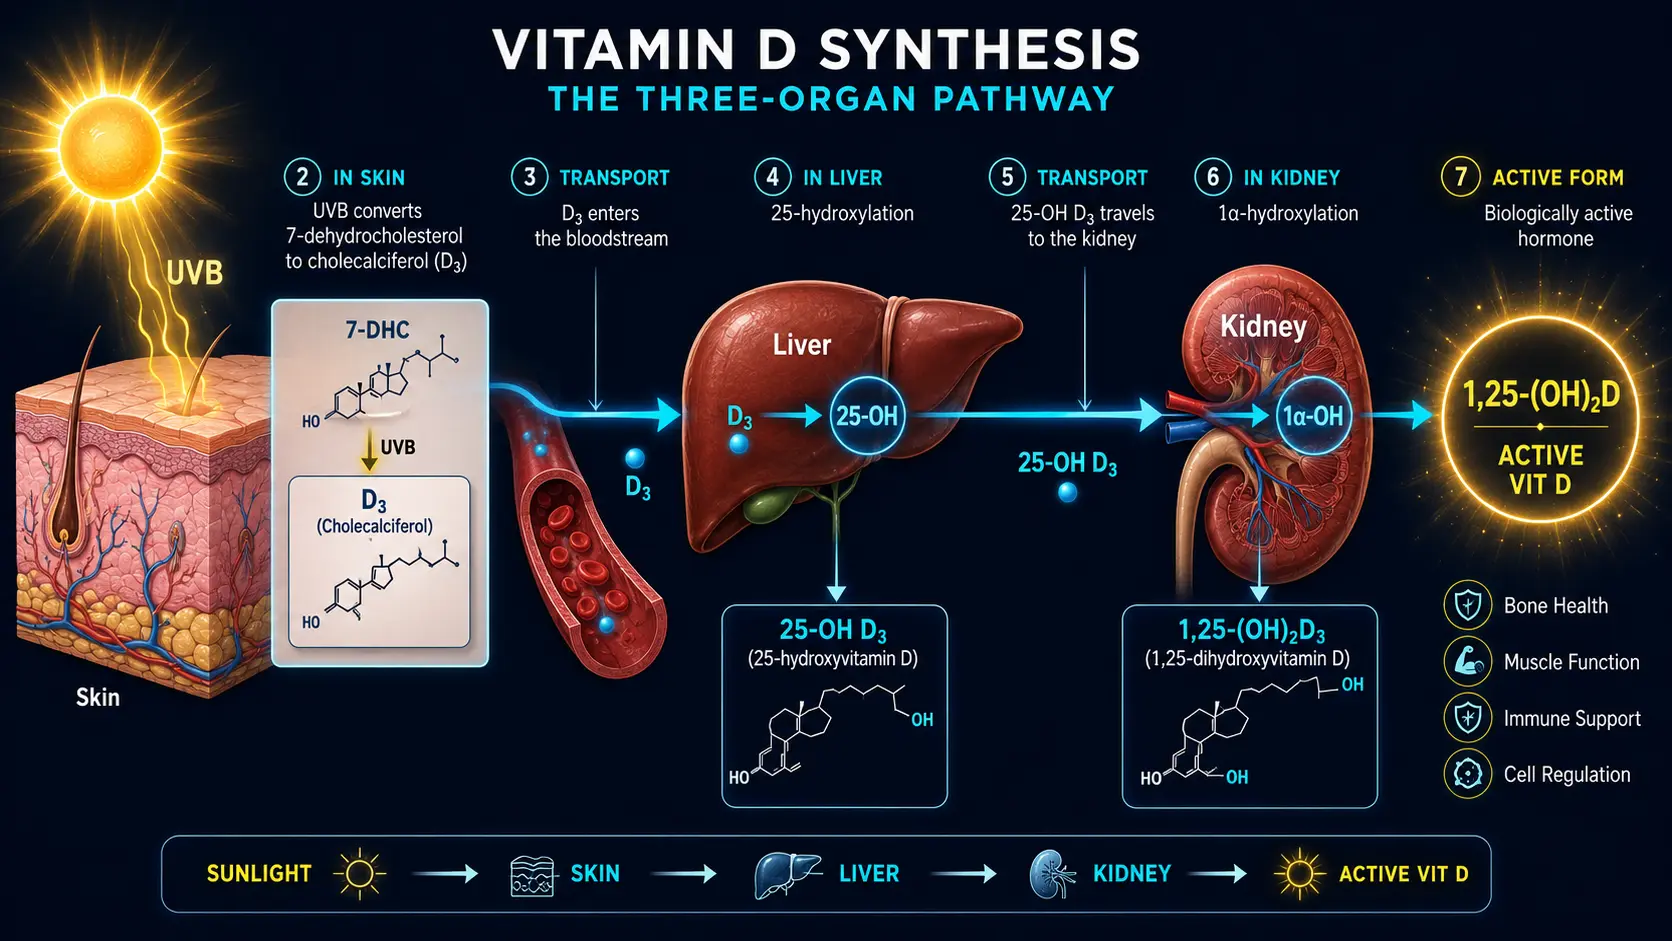
- Step 1 — Cutaneous Synthesis: When UVB radiation (wavelength 290–315 nm) strikes bare skin, it converts 7-dehydrocholesterol (a cholesterol derivative present in the epidermis) to previtamin D3, which rapidly isomerizes to cholecalciferol (Vitamin D3) through a heat-dependent reaction. This is the body's primary source of Vitamin D under natural conditions.
- Step 2 — Hepatic Hydroxylation: Cholecalciferol is transported to the liver bound to Vitamin D-binding protein (DBP), where the enzyme 25-hydroxylase (CYP2R1) converts it to 25-hydroxyvitamin D [25(OH)D] — calcidiol. This is the primary circulating form of Vitamin D and the metabolite measured in blood tests to assess Vitamin D status.
- Step 3 — Renal Activation: In the kidneys, the enzyme 1-alpha-hydroxylase (CYP27B1) converts 25(OH)D to 1,25-dihydroxyvitamin D3 [1,25(OH)₂D] — calcitriol. Calcitriol is the fully active hormonal form of Vitamin D — the form that binds to the Vitamin D Receptor (VDR) and regulates gene expression.
- Extrarenal Activation: The 1-alpha-hydroxylase enzyme is also expressed in many tissues beyond the kidneys — including immune cells, breast tissue, prostate, colon, brain, pancreas, and placenta. This means that local, tissue-level activation of Vitamin D occurs throughout the body, enabling autocrine and paracrine (local) signaling independent of renal calcitriol production. This local activation is the proposed basis for Vitamin D’s roles in immune defense and cellular regulation.
- The Vitamin D Receptor (VDR): Calcitriol exerts its biological effects by binding to the Vitamin D Receptor (VDR), a nuclear receptor that functions as a transcription factor. The VDR-calcitriol complex binds to Vitamin D Response Elements (VDREs) in the promoter regions of target genes, modulating their expression. VDRs have been found in most tissues studied, which is why researchers have looked for effects of Vitamin D beyond calcium and bone metabolism.
- Self-Regulation: The system is self-regulating. Excess sun exposure cannot produce toxic levels of Vitamin D3 because previtamin D3 and Vitamin D3 are photodegraded by continued UV exposure into inert metabolites. The kidneys tightly regulate calcitriol production based on calcium, phosphorus, and parathyroid hormone (PTH) levels. However, supplemental Vitamin D3 lacks this photodegradation safeguard, which is why toxicity — though rare — is possible with very high-dose supplementation.
2. Bone Health and Calcium-Phosphorus Homeostasis
The classical and best-established role of Vitamin D is the regulation of calcium and phosphorus metabolism — the mineral foundation of the skeletal system.
- Intestinal Calcium Absorption: Calcitriol induces the expression of calbindin, TRPV6, and other calcium transport proteins in the intestinal epithelium, increasing the active absorption of dietary calcium from the gut. In Vitamin D deficiency, the fraction of dietary calcium absorbed falls.
- Phosphorus Absorption: Vitamin D similarly enhances the intestinal absorption of phosphorus — the other critical mineral component of hydroxyapatite, the crystalline mineral that gives bone its hardness and compressive strength.
- Bone Mineralization: By ensuring adequate blood levels of calcium and phosphorus, Vitamin D enables the proper mineralization of the collagen matrix laid down by osteoblasts. Without Vitamin D, even abundant calcium intake cannot be deposited into bone effectively.
- Rickets: In children, severe Vitamin D deficiency causes rickets — a devastating failure of bone mineralization that results in soft, deformed bones, bowed legs, widened wrists, prominent frontal bossing, delayed closure of fontanelles, poor growth, dental defects, and increased fracture risk. Rickets was historically epidemic in industrial cities, and the American Academy of Pediatrics noted in 2008 that rickets from inadequate vitamin D intake and low sun exposure continues to be reported in the United States.
- Osteomalacia: The adult equivalent of rickets, osteomalacia involves the softening and weakening of mature bone due to inadequate mineralization. It presents as bone pain, muscle weakness, difficulty walking, and increased fracture risk.
- Osteoporosis: While osteoporosis is primarily a disease of bone mass loss (reduced osteoblast activity relative to osteoclast activity), Vitamin D deficiency adds to osteoporotic fracture risk by impairing calcium absorption, causing secondary hyperparathyroidism (PTH rises to mobilize calcium from bone), and reducing bone mineralization quality.
- Parathyroid Hormone (PTH) Regulation: Vitamin D suppresses PTH secretion from the parathyroid glands. When Vitamin D is deficient, PTH rises (secondary hyperparathyroidism), mobilizing calcium from bone to maintain blood calcium levels — at the direct expense of bone density.
- Fracture Prevention: Trial results depend on whether calcium is given too. A 2010 pooled analysis of seven major trials (68,517 participants) found that vitamin D alone in daily doses of 10 or 20 micrograms did not prevent fractures, while vitamin D given with calcium reduced total fractures (hazard ratio 0.92) and hip fractures. A 2019 meta-analysis likewise found no reduction in fractures with vitamin D alone, while daily vitamin D plus calcium was associated with a 6% lower risk of any fracture and a 16% lower risk of hip fracture. A 2018 meta-analysis of 81 randomized trials found no effect of vitamin D on total fracture, hip fracture, falls or bone mineral density, and in an ancillary VITAL study, 2,000 IU/day did not lower total, nonvertebral or hip fractures (hazard ratio for total fractures 0.98) in midlife and older adults not selected for deficiency, low bone mass or osteoporosis. In a 2010 trial, a single annual dose of 500,000 IU given to women aged 70 and over increased falls and fractures.
- Fall Prevention: Vitamin D has been proposed to lower the risk of falls through VDR-dependent effects on muscle protein synthesis and calcium handling in muscle fibers. Trial results are mixed: the 2018 meta-analysis of 37 trials found no effect on falls (relative risk 0.97), and the annual 500,000 IU dose increased falls.
3. Immune System — Vitamin D as an Immune Modulator
Vitamin D's role in immune regulation is the function most emphasized in natural medicine; the laboratory biology is well described, and the trial evidence is summarized below.
- Innate Immune Activation: When immune cells (macrophages, monocytes, dendritic cells) encounter a pathogen, they upregulate both the VDR and the 1-alpha-hydroxylase enzyme, locally converting circulating 25(OH)D to active calcitriol. This locally produced calcitriol induces the expression of cathelicidin (LL-37) and defensins — antimicrobial peptides that directly kill bacteria, viruses, and fungi. In a 2006 laboratory study, activating Toll-like receptors on human macrophages up-regulated the VDR and 1-alpha-hydroxylase genes, induced cathelicidin, and killed intracellular Mycobacterium tuberculosis.
- Cathelicidin (LL-37): Calcitriol induces cathelicidin expression. LL-37 disrupts microbial cell membranes, neutralizes bacterial endotoxins (LPS), exhibits antiviral activity, and modulates the inflammatory response. Vitamin D deficiency directly impairs the body's ability to produce this critical antimicrobial peptide.
- Tuberculosis — The Historical Connection: Before the discovery of antibiotics, tuberculosis was treated with sunlight exposure (heliotherapy) and cod liver oil — both of which raise Vitamin D. The cathelicidin findings offer a possible mechanism, but a 2020 trial in 8,851 vitamin D-deficient schoolchildren in Mongolia found that 14,000 IU of vitamin D3 weekly for 3 years did not lower the risk of tuberculosis infection, tuberculosis disease or acute respiratory infection.
- Respiratory Infections: A 2017 individual participant data meta-analysis (Martineau et al., BMJ) of 25 randomized controlled trials, with data for 10,933 participants, found that Vitamin D supplementation reduced the risk of acute respiratory tract infection overall (adjusted odds ratio 0.88). Protection was seen with daily or weekly dosing but not with bolus doses, and among people on daily or weekly doses it was strongest in those with baseline 25(OH)D below 25 nmol/L (adjusted odds ratio 0.30). A 2021 update of 46 trials found a smaller overall reduction (odds ratio 0.92), associated with daily doses of 400–1,000 IU; it found no significant effect in any subgroup defined by baseline vitamin D level.
- Influenza and Seasonal Respiratory Illness: Observational studies have associated low Vitamin D status with influenza and other seasonal respiratory infections, particularly in winter, when skin synthesis is minimal at higher latitudes. Observational data alone cannot show that raising Vitamin D prevents these infections; the trial results are summarized above.
- Adaptive Immune Regulation: Calcitriol modulates the adaptive immune system by suppressing excessive Th1 and Th17 pro-inflammatory responses while promoting regulatory T-cell (Treg) development and anti-inflammatory Th2 responses. This immunomodulatory balance is critical for preventing autoimmune attack against the body's own tissues.
- Autoimmune Disease: Vitamin D deficiency has been associated with increased risk and severity of multiple autoimmune diseases, including multiple sclerosis, type 1 diabetes, rheumatoid arthritis, systemic lupus erythematosus, inflammatory bowel disease, psoriasis, Hashimoto's thyroiditis, and Graves' disease. In the VITAL trial (25,871 adults aged 50 and over), 2,000 IU/day for a median of 5.3 years reduced confirmed autoimmune disease by 22% (hazard ratio 0.78, 95% CI 0.61–0.99).
- The Latitude Gradient: The incidence of autoimmune diseases, many cancers, and cardiovascular disease increases with distance from the equator — mirroring the decline in UVB exposure and Vitamin D synthesis. This geographic pattern is one line of observational evidence; it cannot separate Vitamin D from other effects of sunlight and latitude.
4. Cancer Prevention and Anticancer Mechanisms
The relationship between Vitamin D and cancer is one of the most extensively studied areas in nutritional epidemiology and molecular oncology.
- Gene Regulation: In laboratory studies, calcitriol regulates the expression of genes involved in cell proliferation, differentiation, apoptosis (programmed cell death), and angiogenesis (blood vessel formation) — all of which are dysregulated in cancer. Through VDR-mediated gene expression, Vitamin D promotes the differentiation of cancer cells toward more normal phenotypes, inhibits uncontrolled proliferation, triggers apoptosis in malignant cells, and suppresses the formation of new blood vessels that feed tumor growth.
- Colorectal Cancer: The most consistent observational association. In a 2019 pooling of 17 cohorts (5,706 cases), deficient 25(OH)D (below 30 nmol/L) was associated with a 31% higher colorectal cancer risk than levels of 50 to under 62.5 nmol/L, and levels of 75–100 nmol/L with a 19–27% lower risk; risk did not keep falling above 100 nmol/L. In the VITAL trial, 2,000 IU/day did not lower colorectal cancer incidence (hazard ratio 1.09).
- Breast Cancer: Observational studies associate higher Vitamin D status with reduced breast cancer risk, particularly for ER-positive breast cancers. In the VITAL trial, supplementation did not change breast cancer incidence (hazard ratio 1.02).
- Prostate Cancer: The evidence is mixed but evolving. Some studies suggest that both very low and very high Vitamin D levels may be associated with increased prostate cancer risk, suggesting a non-linear relationship. In VITAL, the hazard ratio for prostate cancer was 0.88, not statistically significant.
- Other Cancers: Epidemiological studies report protective associations between Vitamin D and cancers of the lung, pancreas, ovary, bladder, kidney, and non-Hodgkin lymphoma, though the strength of evidence varies.
- Cancer Incidence and Mortality in Trials: In the VITAL trial (25,871 adults, median 5.3 years), 2,000 IU/day did not lower invasive cancer (hazard ratio 0.96); death from cancer was lower but not significantly so (hazard ratio 0.83, 95% CI 0.67–1.02). A 2019 meta-analysis of randomized trials found no reduction in total cancer incidence (relative risk 0.98) but a reduction in total cancer mortality (relative risk 0.87), largely attributable to trials using daily rather than bolus dosing. In the D-Health trial of 60,000 IU once a month in 21,315 Australians aged 60 and over, all-cause mortality was unchanged (hazard ratio 1.04) and cancer mortality was not reduced (hazard ratio 1.15, 95% CI 0.96–1.39); the authors wrote that this monthly regimen “might not be appropriate in people who are vitamin D-replete.”
- Wnt/β-Catenin Pathway: In laboratory studies, calcitriol inhibits the Wnt/β-catenin signaling pathway — one of the most commonly aberrantly activated pathways in colorectal and other cancers. This is a proposed mechanism by which Vitamin D could suppress intestinal carcinogenesis.
- Immune Surveillance: Vitamin D has been proposed to enhance NK cell activity and anti-tumor immune responses, supporting the immune system's ability to detect and eliminate emerging cancer cells before they establish tumors.
5. Mental Health — Depression, Seasonal Affective Disorder, and Cognitive Function
- VDR in the Brain: Vitamin D receptors and the 1-alpha-hydroxylase enzyme are expressed throughout the brain — in the hippocampus, hypothalamus, prefrontal cortex, cerebellum, and substantia nigra — and brain cells can therefore activate Vitamin D locally.
- Depression: Low Vitamin D status is associated with depression in observational studies: a 2013 meta-analysis of 14 observational studies (31,424 participants) found lower Vitamin D levels in people with depression and an odds ratio of 1.31 for the lowest versus highest Vitamin D categories in cross-sectional studies. Trial results are mixed. A 2015 meta-analysis of nine trials (4,923 participants) found no significant reduction in depression overall; a 2019 meta-analysis of four trials in clinically diagnosed major depression reported a moderate pooled effect, but one of its four trials (Sepehrmanesh et al., 2016, Journal of Nutrition) was retracted in 2021 over concerns about the validity of its participant data; and the VITAL-DEP trial of 18,353 adults aged 50 and over found that 2,000 IU/day did not lower the risk of depression or clinically relevant depressive symptoms (hazard ratio 0.97, 95% CI 0.87–1.09). The Vitamin D3 Mood & Depression page covers these trials in detail.
- Seasonal Affective Disorder (SAD): The seasonal pattern of depression — with symptoms peaking in winter months when UVB exposure is minimal — closely mirrors the seasonal decline in Vitamin D synthesis. Some natural practitioners use Vitamin D supplementation alongside light therapy for SAD; trial evidence for this use is limited.
- Neurotransmitter Regulation: Patrick and Ames (2014) proposed that calcitriol activates transcription of the gene for tryptophan hydroxylase 2 (TPH2) — the rate-limiting enzyme for serotonin synthesis in the brain — through a vitamin D response element, while repressing the gut form, TPH1. On this hypothesis, Vitamin D deficiency could reduce brain serotonin synthesis.
- Neuroinflammation: In laboratory and animal studies, Vitamin D suppresses microglial activation and reduces neuroinflammatory cytokines (IL-6, TNF-α, IL-1β) in the brain — processes implicated in the pathophysiology of depression, anxiety, and neurodegeneration.
- Cognitive Decline and Dementia: Low Vitamin D status is associated with accelerated cognitive decline, reduced hippocampal volume, and increased risk of Alzheimer's disease and all-cause dementia. Proposed mechanisms include roles of the Vitamin D-VDR system in neuronal calcium regulation, amyloid-beta clearance and synaptic plasticity.
- Schizophrenia: Neonatal Vitamin D deficiency is associated with increased risk of schizophrenia in adulthood, suggesting a developmental programming effect. This is consistent with Vitamin D's role in brain development during fetal and neonatal life.
- Anxiety: Observational studies link low Vitamin D to increased anxiety; trial evidence on supplementation for anxiety is limited.
6. Cardiovascular Health
- VDR in Cardiovascular Tissue: VDRs are expressed in cardiomyocytes (heart muscle cells), vascular smooth muscle cells, and endothelial cells, which is why direct cardiovascular effects have been studied.
- Blood Pressure: In laboratory studies, Vitamin D suppresses the renin-angiotensin-aldosterone system (RAAS) by downregulating renin gene expression, which has been proposed as a link between deficiency and hypertension. Observational studies show inverse associations between Vitamin D levels and blood pressure, while supplementation trials have yielded mixed results; in the DO-HEALTH trial of 2,157 adults aged 70 and over, 2,000 IU/day for 3 years did not significantly change systolic or diastolic blood pressure.
- Endothelial Function: In laboratory studies, calcitriol supports endothelial nitric oxide production, reduces oxidative stress in the vascular wall, and inhibits endothelial cell inflammation.
- Atherosclerosis: Laboratory and observational studies have linked Vitamin D deficiency to vascular calcification, endothelial dysfunction, inflammation, and smooth muscle cell proliferation in arterial walls — components of atherosclerotic progression.
- Heart Failure: Low Vitamin D is highly prevalent among heart failure patients and is associated with worse functional class, higher mortality, and increased risk of adverse cardiac events. A role in myocardial calcium handling has been proposed.
- Cardiovascular Events and Mortality: Large observational studies report inverse or U-shaped relationships between Vitamin D status and cardiovascular mortality. In the VITAL trial, 2,000 IU/day did not reduce major cardiovascular events (hazard ratio 0.97) or death from cardiovascular causes (hazard ratio 1.11), and in the D-Health trial monthly dosing did not change cardiovascular mortality (hazard ratio 0.96).
- Arterial Stiffness: Vitamin D deficiency is associated with increased arterial stiffness and pulse wave velocity — independent risk factors for cardiovascular events.
7. Blood Sugar Regulation and Diabetes
- Pancreatic Beta Cell Function: VDRs are expressed on pancreatic beta cells, and in laboratory studies calcitriol enhances insulin synthesis and secretion. Vitamin D deficiency has been reported to impair beta cell function and reduces insulin release in response to glucose.
- Insulin Sensitivity: Vitamin D has been proposed to modulate insulin sensitivity in target tissues (muscle, fat, liver) through VDR-mediated gene expression and by reducing systemic inflammation that drives insulin resistance.
- Type 2 Diabetes Prevention: In the D2d randomized trial (2,423 adults with prediabetes), 4,000 IU/day did not significantly lower the risk of diabetes over a median of 2.5 years (hazard ratio 0.88, 95% CI 0.75–1.04). A 2023 individual participant data meta-analysis of three trials in prediabetes found a 15% lower risk of diabetes (hazard ratio 0.85), and the 2024 Endocrine Society guideline suggests empiric vitamin D for adults with high-risk prediabetes.
- Type 1 Diabetes: Vitamin D's immunomodulatory effects — suppressing autoreactive Th1/Th17 cells and promoting regulatory T-cells — are directly relevant to the autoimmune destruction of beta cells in type 1 diabetes. Observational studies have associated Vitamin D supplementation in infancy with a lower risk of developing type 1 diabetes.
- Gestational Diabetes: Low Vitamin D status during pregnancy is associated with increased risk of gestational diabetes. Whether supplementation lowers that risk is not settled.
- Metabolic Syndrome: Vitamin D deficiency is independently associated with metabolic syndrome — the cluster of insulin resistance, central obesity, hypertension, dyslipidemia, and elevated blood sugar that drives cardiovascular disease and type 2 diabetes.
- HbA1c: Some studies demonstrate that Vitamin D supplementation in diabetic individuals with deficiency reduces HbA1c, though the magnitude of effect varies across populations and study designs.
8. Muscle Function and Physical Performance
- VDR in Skeletal Muscle: VDRs are expressed in skeletal muscle tissue, and calcitriol directly regulates muscle protein synthesis, calcium handling, and contractile function. VDR expression in muscle declines with age, paralleling the decline in Vitamin D status and muscle function.
- Muscle Strength: Vitamin D deficiency causes proximal muscle weakness — difficulty rising from a chair, climbing stairs, or lifting objects. This weakness is often subtle and attributed to aging rather than recognized as a reversible nutritional deficiency.
- Sarcopenia: Age-related loss of muscle mass and function (sarcopenia) has been associated with Vitamin D deficiency. In the DO-HEALTH trial of adults aged 70 and over, 2,000 IU/day for 3 years did not improve physical performance (Short Physical Performance Battery).
- Fall Prevention: As noted in the bone health section, trial results on falls are mixed: the 2018 meta-analysis of 37 trials found no reduction, and a single annual 500,000 IU dose increased falls in older women.
- Athletic Performance: Studies in athletes have examined whether Vitamin D status affects muscle power, reaction time, and aerobic capacity; the evidence is not settled.
- Muscle Pain and Fibromyalgia: Diffuse musculoskeletal pain and weakness are common in Vitamin D deficiency and can be mistaken for fibromyalgia, chronic fatigue syndrome, or “growing pains” in children.
9. Pregnancy and Fetal Development
- Placental Function: The placenta expresses VDR and 1-alpha-hydroxylase, locally producing calcitriol to support immune tolerance of the fetus, implantation, placental development, and angiogenesis.
- Preeclampsia: Vitamin D deficiency in early pregnancy has been associated with a higher risk of preeclampsia; calcitriol's suppression of the RAAS, its anti-inflammatory effects, and its effects on endothelial function are proposed links. The 2024 Endocrine Society guideline suggests empiric vitamin D in pregnancy because of its potential to lower the risk of preeclampsia, intra-uterine mortality, preterm birth, small-for-gestational-age birth, and neonatal mortality.
- Gestational Diabetes: As discussed above, low Vitamin D increases gestational diabetes risk.
- Preterm Birth: Low Vitamin D status is associated with increased risk of preterm delivery, though the evidence is still evolving.
- Fetal Bone Development: Maternal Vitamin D status directly influences fetal calcium accretion and bone mineralization. Severe maternal deficiency can cause neonatal rickets and congenital craniotabes (soft skull bones).
- Immune Programming: Maternal Vitamin D status influences fetal immune system development, with deficiency associated with increased risk of asthma, allergies, and autoimmune diseases in the child.
- Brain Development: Vitamin D regulates neuronal differentiation, neurotrophic factor expression, and brain development during fetal life. Maternal deficiency is associated with altered neurocognitive outcomes in offspring.
- Doses Studied in Pregnancy: The IOM's RDA in pregnancy is 600 IU/day; some natural practitioners and researchers advocate 4,000–6,000 IU/day. In the Hollis et al. 2011 trial, 494 women at 12–16 weeks' gestation were randomized to 400, 2,000 or 4,000 IU/day; 4,000 IU/day was the most effective at achieving sufficiency in mothers and newborns, with no differences between groups on any safety measure. The 2024 Endocrine Society guideline states that the optimal doses for empiric supplementation remain unclear.
10. Respiratory Health
- Respiratory Infection Prevention: As detailed in the immune section, Vitamin D supplementation reduces the risk of acute respiratory tract infections, with the greatest benefit in deficient individuals.
- Asthma: Vitamin D deficiency is associated with increased asthma severity, more frequent exacerbations, reduced response to corticosteroids, and impaired lung function. A 2017 individual participant data meta-analysis of seven trials (955 participants) found that Vitamin D reduced the rate of asthma exacerbations requiring systemic corticosteroids (rate ratio 0.74).
- COPD: Low Vitamin D is common in chronic obstructive pulmonary disease and is associated with accelerated lung function decline, increased exacerbation frequency, and higher mortality.
- Lung Development: Vitamin D influences fetal and childhood lung development. Maternal deficiency is associated with reduced lung function and increased wheeze and asthma risk in offspring.
- Pneumonia: Low Vitamin D status is associated with increased pneumonia incidence and severity, consistent with its role in innate immune defense and cathelicidin production in the respiratory epithelium.
11. Thyroid Health
- Hashimoto's Thyroiditis: Vitamin D deficiency is highly prevalent among individuals with Hashimoto's — the most common cause of hypothyroidism. Low Vitamin D is associated with higher thyroid antibody levels (anti-TPO, anti-Tg), and supplementation has been shown to reduce antibody titers in some studies.
- Graves' Disease: Low Vitamin D is also associated with increased risk and severity of Graves' disease (autoimmune hyperthyroidism).
- Thyroid Cancer: Some epidemiological evidence links Vitamin D deficiency with increased thyroid cancer risk and more aggressive disease behavior.
- Immunomodulatory Mechanism: Vitamin D's promotion of regulatory T-cells and suppression of autoreactive immune responses is the proposed mechanism linking it to autoimmune thyroid disease. Autoimmune thyroid disease was one of the outcomes counted in the VITAL autoimmune analysis described in the Immune System section.
12. Gut Health
- Intestinal Barrier Function: In laboratory studies, calcitriol enhances the expression of tight junction proteins (claudins, occludin, ZO-1) in intestinal epithelial cells, strengthening the gut barrier and reducing intestinal permeability ("leaky gut").
- Inflammatory Bowel Disease (IBD): Vitamin D deficiency is extremely common in Crohn's disease and ulcerative colitis. Whether supplementation reduces intestinal inflammation or relapse has been studied in small trials; the evidence is limited. The latitude gradient of IBD incidence (higher in northern regions) is consistent with a role for Vitamin D.
- Microbiome Modulation: Early research suggests that Vitamin D status influences the composition and diversity of the gut microbiome.
- Celiac Disease: Individuals with celiac disease are at increased risk of Vitamin D deficiency due to malabsorption, and this deficiency contributes to the osteopenia and osteoporosis commonly seen in celiac patients.
- Colorectal Protection: Vitamin D's support of intestinal barrier integrity, immune regulation, and anti-inflammatory effects in the gut are proposed explanations for its observed association with lower colorectal cancer risk (see the Cancer section).
13. Skin Health
- Keratinocyte Differentiation: Calcitriol regulates the proliferation and differentiation of keratinocytes — the primary cells of the epidermis. This function is the basis for the use of Vitamin D analogues (calcipotriol, also called calcipotriene) as topical treatments for psoriasis.
- Psoriasis: Topical Vitamin D analogues are among the first-line treatments for plaque psoriasis, reducing keratinocyte hyperproliferation, modulating local immune responses, and promoting normal skin differentiation. Whether oral Vitamin D improves psoriasis is less clear.
- Atopic Dermatitis (Eczema): Vitamin D deficiency is associated with increased eczema severity. Supplementation may improve skin barrier function and reduce the antimicrobial peptide deficiency that predisposes atopic skin to infection.
- Vitiligo: Vitamin D's immunomodulatory effects and its role in melanocyte function make it relevant to vitiligo management, often used alongside UV phototherapy.
- Wound Healing: Vitamin D supports wound healing through its effects on cathelicidin production (antimicrobial defense), immune regulation, and keratinocyte proliferation.
- Skin Aging: Adequate Vitamin D supports skin health and may modulate photoaging processes, though direct sun exposure for Vitamin D synthesis must be balanced against UV-induced photodamage — a nuanced consideration in natural medicine.
14. Fertility and Reproductive Health
- Female Fertility: VDRs are expressed in the ovaries, uterus, and placenta. Vitamin D deficiency is associated with reduced fertility, impaired ovarian reserve, lower IVF success rates, and conditions such as polycystic ovary syndrome (PCOS) and endometriosis.
- PCOS: Vitamin D deficiency is highly prevalent among women with PCOS and is associated with worse metabolic profiles, insulin resistance, and anovulation. Supplementation has shown improvements in insulin sensitivity, menstrual regularity, and hormonal balance in some studies.
- Male Fertility: VDRs are expressed in testicular tissue, and Vitamin D influences spermatogenesis, sperm motility, capacitation, and acrosome reaction. Deficiency is associated with reduced sperm quality and fertility.
- IVF Outcomes: A 2018 meta-analysis of 11 cohort studies (2,700 women) found that women replete in Vitamin D were more likely than deficient or insufficient women to achieve clinical pregnancy (odds ratio 1.46) and live birth (odds ratio 1.33) after assisted reproduction, with no association with miscarriage. These are associations, not trial results.
- Pregnancy Outcomes: Vitamin D in pregnancy is covered in Section 9.
15. Sources of Vitamin D3
Sunlight — The Primary Natural Source
- Sun Exposure: How much Vitamin D3 the skin makes depends on the UV index, time of day, season, latitude, the area of skin exposed, and skin tone. Sun exposure over a large area of skin can produce more Vitamin D than typical foods supply.
- Skin Tone: Melanin in darker skin absorbs UV radiation, so darker skin needs longer sun exposure to produce the same amount of Vitamin D — which contributes to deficiency at higher latitudes.
- Latitude: In a classic 1988 study, winter sunlight in Boston (42.2°N) produced no previtamin D3 in skin from November through February, and in Edmonton (52°N) the ineffective period ran from October through March; further south (34°N and 18°N), sunlight still produced it in midwinter. This seasonal gap is often called the “Vitamin D winter.”
- Sunscreen: In laboratory experiments using artificial UV sources, sunscreen considerably reduced Vitamin D production. A 2019 systematic review, however, found little evidence that sunscreen lowers 25(OH)D in real-life use: randomized field trials (with SPF ~16 sunscreens) found no effect, and most observational studies found no association; the authors noted that very high-SPF sunscreens have not been tested in trials.
- Age: The concentration of 7-dehydrocholesterol in the skin decreases with age. In a 1985 study, skin from 77- and 82-year-olds produced less than half the previtamin D3 made by skin from 8- and 18-year-olds (a greater than twofold decrease).
- Glass: UVB radiation does not pass through glass. Indoor sun exposure through windows does not produce Vitamin D.
Dietary Sources
Vitamin D3 is found in very few natural foods — for most of human history, sunlight rather than diet supplied most of it.
- Cod Liver Oil: The traditional source — among the richest foods in Vitamin D3, and it also supplies Vitamin A and omega-3 fatty acids. Per-serving amounts from USDA data are listed on the Vitamin D3 Sources page.
- Fatty Fish: Salmon, mackerel, sardines, herring, and trout are among the richest food sources. A 2007 analysis found that farmed salmon contained about 25% of the Vitamin D of wild salmon, and that content varied widely even within a species.
- Egg Yolks: Supply smaller amounts; the egg's Vitamin D sits in the yolk.
- Beef Liver: Provides small amounts of Vitamin D3.
- UV-Exposed Mushrooms: Mushrooms exposed to UV light (sunlight or UV lamps) produce Vitamin D2 (ergocalciferol), not D3. A 2012 meta-analysis of trials found Vitamin D3 more effective than D2 at raising serum 25(OH)D.
- Lichen-Sourced Vitamin D3: A vegan source of Vitamin D3 (cholecalciferol), sold as supplements.
- Fortified Foods: Milk, some orange juice, cereals, and some plant milks are fortified with Vitamin D (usually D3 in the US, sometimes D2); amounts vary by product.
16. Recommended Daily Intake and Blood Levels
Official Recommendations — IOM 2011 Dietary Reference Intakes (IU/day)
- Infants (0–12 months): 400 IU (Adequate Intake); the American Academy of Pediatrics (2008) likewise lists a minimum of 400 IU/day for all infants, including exclusively breastfed infants
- Children and Adults (1–70 years): 600 IU
- Adults over 70: 800 IU
- Pregnant and Breastfeeding Women: 600 IU
- Tolerable Upper Intake Level (UL): 4,000 IU/day for ages 9 and older, lower for infants and young children. The IOM states that the UL is not a target intake; the risk of harm begins to increase once intakes surpass it.
The IOM set these RDAs from bone health, as the intakes that keep serum 25(OH)D at or above 20 ng/mL (50 nmol/L) in at least 97.5% of the population under minimal sun exposure. It judged the evidence for cancer, cardiovascular disease, diabetes and autoimmune disorders inconsistent and insufficient to set requirements.
Guideline Positions on Higher Intakes
- 2011 Endocrine Society guideline (Holick et al.): written for patients at risk of deficiency. It stated that adults may need at least 1,500–2,000 IU/day to keep 25(OH)D consistently above 30 ng/mL, suggested treating deficient adults with 50,000 IU once a week for 8 weeks (or 6,000 IU/day) followed by 1,500–2,000 IU/day, set a maintenance upper limit of 4,000 IU/day, said 10,000 IU/day may be needed to correct deficiency in adults, and suggested that obese children and adults be given at least two to three times more vitamin D for their age group.
- 2024 Endocrine Society guideline (Demay et al.): suggests empiric vitamin D for ages 1–18, adults over 75, pregnancy and high-risk prediabetes; suggests against empiric supplementation above the Dietary Reference Intakes to lower disease risk in healthy adults younger than 75; suggests daily rather than intermittent high-dose vitamin D for people over 50 who take it; and suggests against routine 25(OH)D testing in the general population, including people with obesity or dark complexion, finding no clear evidence defining an optimal 25(OH)D target for disease prevention.
Natural Medicine Perspective
Many natural medicine practitioners and integrative physicians consider the RDA of 600 IU too low for what they regard as optimal Vitamin D status. Intakes they commonly describe (practitioners’ figures, not guideline doses) include:
- Maintenance (adults): 2,000–5,000 IU/day of Vitamin D3
- Deficiency Repletion: 5,000–10,000 IU/day for 8–12 weeks, then maintenance dosing
- Pregnancy: 4,000–6,000 IU/day (citing the Hollis et al. trial, which tested up to 4,000 IU/day)
- Autoimmune Conditions: 5,000–10,000 IU/day under monitoring, targeting higher 25(OH)D levels (50–80 ng/mL)
- Obese Individuals: higher doses, in line with the 2011 Endocrine Society guideline’s two-to-three-times figure
Blood Level Cut-Points — 25(OH)D
Different bodies use different cut-points. To convert, 1 ng/mL = 2.5 nmol/L.
- Deficient: Below 20 ng/mL (50 nmol/L) in the 2011 Endocrine Society guideline — the range associated with rickets and osteomalacia. The IOM judged 20 ng/mL enough to meet the needs of at least 97.5% of people for bone health.
- Insufficient: 21–29 ng/mL in the 2011 Endocrine Society guideline; the IOM did not use this category.
- Sufficient: 30–100 ng/mL in the 2011 Endocrine Society guideline. The IOM found that levels above 30 ng/mL (75 nmol/L) were not consistently associated with greater benefit, and stated that levels above 50 ng/mL (125 nmol/L) should raise concerns about potential adverse effects.
- Practitioner target: Some natural medicine practitioners target 40–70 ng/mL (100–175 nmol/L); this range is not adopted by the guidelines cited here, and the 2024 Endocrine Society guideline found no clear evidence defining an optimal target.
- Upper limit: The 2011 Endocrine Society guideline set 100 ng/mL (250 nmol/L) as an upper limit to provide a safety margin against hypercalcemia.
- Toxicity concern: The same guideline stated that most studies suggest blood levels need to be above 150 ng/mL (375 nmol/L) before there is any concern about hypercalcemia.
17. Supplemental Forms
- Vitamin D3 (Cholecalciferol): The form most often used in natural medicine, identical to the form produced in the skin from sunlight. A 2012 meta-analysis of trials found D3 more effective than D2 at raising 25(OH)D; the difference was clear with bolus doses and was lost with daily dosing. Available from animal sources (lanolin from sheep's wool) and vegan sources (lichen).
- Vitamin D2 (Ergocalciferol): Derived from UV-irradiated yeast or fungi. Less effective than D3 at raising 25(OH)D levels in the 2012 meta-analysis. Still prescribed in some medical settings.
- Calcidiol (25-Hydroxyvitamin D3 / Calcifediol): The pre-hydroxylated form that is the circulating metabolite measured in blood tests. Because it bypasses the liver step, it raises 25(OH)D faster than cholecalciferol. It is available as a prescription medicine in some countries and as a supplement.
- Oil-Based Softgels vs. Dry Tablets: Vitamin D3 is fat-soluble and is absorbed better when taken with dietary fat. Oil-based softgels and liquid drops contain oil; dry tablets are usually taken with a meal containing fat.
- Liquid Drops: Sold in a range of concentrations and commonly used for infants and children.
- High-Dose Boluses: Weekly (50,000 IU), monthly, or annual high-dose regimens exist. In the 2017 respiratory-infection meta-analysis, protection was seen with daily or weekly dosing but not with bolus doses; the 2024 Endocrine Society guideline suggests daily rather than intermittent high doses for people over 50 who take vitamin D; and in a 2010 trial an annual 500,000 IU dose increased falls and fractures in older women.
18. Synergistic Nutrients — Proposed Partners
Vitamin D works alongside several other nutrients; natural practitioners place particular weight on these pairings, and the strength of the evidence differs for each.
- Vitamin K2 (Menaquinone): Described by natural practitioners as the most important partner for Vitamin D. The rationale: Vitamin D increases intestinal calcium absorption, while K2 activates osteocalcin (which binds calcium in bone) and matrix Gla protein (MGP) (which inhibits calcium deposition in arteries). On this reasoning, practitioners describe D3 and K2 as a necessary pairing and propose that Vitamin D without adequate K2 could contribute to arterial or soft-tissue calcification; trial evidence that the pairing changes clinical outcomes is limited.
- Magnesium: A 2018 review (Uwitonze and Razzaque) states that all the enzymes that metabolize Vitamin D seem to require magnesium as a cofactor in the liver and kidneys, so magnesium deficiency has been proposed to impair Vitamin D activation and the response to supplementation.
- Vitamin A (Retinol): Vitamins A and D share nuclear receptor partners (they both heterodimerize with RXR) and regulate overlapping sets of genes. They interact in immune function, and some researchers have proposed that the balance between A and D matters for gene expression. Cod liver oil has traditionally provided both vitamins in natural proportion.
- Calcium: Vitamin D's primary classical function is to enhance calcium absorption and maintain calcium homeostasis. In fracture trials, vitamin D given with calcium performed better than vitamin D alone (see Bone Health).
- Zinc: The VDR's DNA-binding domain is a zinc-finger structure, and zinc deficiency has been proposed to impair the cellular response to Vitamin D.
- Boron: This trace mineral influences Vitamin D metabolism and may enhance its effects on bone health and calcium utilization.
- Omega-3 Fatty Acids: Omega-3s and Vitamin D have synergistic anti-inflammatory, immunomodulatory, and neuroprotective effects. Fatty fish provides both naturally.
19. Populations at Higher Risk of Deficiency
- Individuals Living at High Latitudes: At higher latitudes, winter sunlight is too weak for cutaneous Vitamin D synthesis (see the Latitude entry above).
- Individuals with Dark Skin: Higher melanin content reduces Vitamin D synthesis, so dark-skinned individuals at higher latitudes are among the groups most often found deficient.
- Elderly Individuals: Reduced skin 7-dehydrocholesterol, decreased sun exposure, impaired renal hydroxylation, and lower dietary intake create a "perfect storm" of deficiency risk in the aged.
- Obese Individuals: Vitamin D is sequestered in adipose tissue, reducing its bioavailability. The 2011 Endocrine Society guideline suggested that obese children and adults be given at least two to three times more vitamin D for their age group.
- Indoor Workers: Office workers, shift workers, and individuals who spend most of their time indoors receive minimal UVB exposure regardless of latitude.
- Individuals Who Cover Their Skin: For cultural, religious, or sun-protection reasons, covered skin cannot synthesize Vitamin D.
- Breastfed Infants: Human breast milk contains little Vitamin D. The American Academy of Pediatrics (2008) recommends a minimum daily intake of 400 IU for all infants, including those exclusively breastfed, beginning soon after birth.
- Individuals with Malabsorptive Conditions: Celiac disease, Crohn's disease, cystic fibrosis, and other fat malabsorption conditions impair Vitamin D absorption from the gut.
- Post-Bariatric Surgery Patients: Gastric bypass in particular reduces Vitamin D absorption, and long-term supplementation is commonly used.
- Individuals with Liver or Kidney Disease: Impaired hepatic hydroxylation (liver disease) or renal hydroxylation (kidney disease) reduces the conversion of Vitamin D to its active forms.
- Individuals on Certain Medications: Anticonvulsants (phenytoin, phenobarbital), glucocorticoids, rifampin, cholestyramine, and antiretrovirals all accelerate Vitamin D catabolism or impair its metabolism.
- Vegans: Since almost all natural food sources of Vitamin D3 are animal-derived, vegans are at increased risk unless they get Vitamin D from fortified foods, lichen-sourced D3, or UV-exposed mushrooms (D2).
20. Signs of Deficiency
Vitamin D deficiency is often called the "silent epidemic" because it can persist for years without obvious symptoms before manifesting as serious disease. Features linked to deficiency span the musculoskeletal system (bone pain, proximal muscle weakness, fractures, rickets in children), the immune system (frequent respiratory infections, slow recovery, worsening autoimmunity), and the brain (depression, anxiety, cognitive fog, fatigue), along with slow wound healing and hair loss; several of these, such as infections and mood changes, are associations rather than established effects. For a full, patient-friendly guide to the symptoms, causes, and recovery, see Vitamin D Deficiency.
21. Toxicity and Safety
Vitamin D toxicity is rare but real. It does not come from sun exposure (the skin self-limits through photodegradation) — only from very high-dose supplementation sustained over time, which drives hypercalcemia (excess blood calcium) with nausea, excessive thirst and urination, confusion, kidney stones, and, in severe cases, kidney injury and heart-rhythm disturbances. People with sarcoidosis or other granulomatous diseases are more susceptible. For a full, patient-friendly guide to the symptoms, causes, and risks, see Vitamin D Toxicity.
22. Doses Described for Specific Uses
The doses below are those described by natural medicine practitioners or tested in trials, set beside what the trials and guidelines found. They are reported here as information; decisions about vitamin D doses belong with a clinician.
- General Use: Practitioners commonly describe 2,000–5,000 IU/day of D3 with K2 (100–200 mcg MK-7) and magnesium, targeting 25(OH)D of 40–60 ng/mL. For comparison, the IOM UL is 4,000 IU/day, and the 2024 Endocrine Society guideline suggests against empiric supplementation above the Dietary Reference Intakes for healthy adults younger than 75 and against routine 25(OH)D testing.
- Deficiency Repletion: The 2011 Endocrine Society guideline suggested 50,000 IU once a week for 8 weeks (or 6,000 IU/day) for deficient adults, followed by 1,500–2,000 IU/day; practitioners describe 5,000–10,000 IU/day for 8–12 weeks.
- Autoimmune Disease: Practitioners describe 5,000–10,000 IU/day under monitoring, often combined with omega-3, curcumin, and an anti-inflammatory diet. The trial result available is VITAL’s: 2,000 IU/day reduced confirmed autoimmune disease by 22%.
- Respiratory Infections: Practitioners describe 2,000–5,000 IU/day during cold and flu season, with short increases (10,000–20,000 IU/day for 3–5 days) at the onset of illness. The meta-analyses cited on this page associate protection with regular daily dosing (daily doses of 400–1,000 IU in the 2021 analysis) and found none with bolus doses (2017); they did not test short high-dose courses at the onset of illness.
- Osteoporosis and Fractures: Practitioners describe 2,000–5,000 IU/day D3 with K2, calcium from food, magnesium, and weight-bearing exercise. In trials, vitamin D with calcium modestly reduced fractures while vitamin D alone did not (see Bone Health).
- Pregnancy: Practitioners describe 4,000–6,000 IU/day D3 with K2 from preconception through lactation; the Hollis et al. trial found 4,000 IU/day safe and the most effective of the doses tested at achieving sufficiency.
- Depression and SAD: Practitioners describe 2,000–5,000 IU/day as part of a mood-support protocol with omega-3, B vitamins, and magnesium; the VITAL-DEP trial found that 2,000 IU/day did not prevent depression in adults aged 50 and over.
- Type 2 Diabetes Prevention: The D2d trial used 4,000 IU/day in adults with prediabetes (hazard ratio 0.88, not statistically significant); the 2023 three-trial meta-analysis found a 15% lower risk, and the 2024 Endocrine Society guideline suggests empiric vitamin D for high-risk prediabetes.
- PCOS: Practitioners describe 2,000–5,000 IU/day as adjunctive support for insulin sensitivity, hormonal balance, and ovulatory function; trial evidence is limited.
- Psoriasis: Topical calcipotriol is an established treatment; practitioners describe adding oral D3.
- Coimbra Protocol (Autoimmune): A high-dose regimen associated with the group of Brazilian physician Cicero Coimbra, combining very high daily vitamin D3 doses with a strict low-calcium diet, a daily fluid intake of at least 2.5 L, and regular laboratory monitoring. In a 2022 report of 319 patients with autoimmune diseases treated for up to 3.5 years, the mean dose was 35,291 IU per day and mean serum calcium and kidney-function values stayed within the normal range; this was an uncontrolled case series, and the report names hypercalcemia and impaired kidney function as the main concerns raised against the protocol. Such doses are far above the 4,000 IU/day UL.
Historical Medical Use & the Dosing Story (1926–1972)
Vitamin D has one of the most dramatic dosing histories in all of medicine — a story that swings from a genuine miracle cure to a near-forgotten danger and back to a modern, evidence-based middle ground. Understanding that arc helps make sense of the wildly different numbers patients still encounter online today, from the official 600 IU to claims that “everyone needs 10,000 IU.”
The Rickets Cure (1920s–1930s)
- A real, well-earned triumph. In the 1920s, rickets — the bone-softening disease that left children with bowed legs, widened wrists, and deformed chests — was epidemic in the smoky, sun-starved industrial cities of Europe and the northern United States. The discovery that both cod liver oil and ultraviolet light could prevent and cure it was one of the great nutritional victories of the era. By the early 1930s, “the antirachitic factor” had been chemically identified as vitamin D, and the routine fortification of milk that followed made childhood rickets rare across the developed world. This is honest history: vitamin D really did cure rickets, and it remains the textbook example of a vitamin deficiency disease conquered by a single nutrient.
- Why it worked. Vitamin D enables the gut to absorb calcium and phosphorus and lets the bone-building cells lay down hard mineral. Without it, even a calcium-rich diet cannot mineralize growing bone — which is why sunlight, cod liver oil, and later fortified milk all worked through the same final pathway. (See the Bone Health section above.)
The 1972 Megadose Era
- What online accounts attribute to an older medical text. Mid-century clinicians, impressed by vitamin D’s power over bone disease, experimented with very large doses for inflammatory and autoimmune conditions. Modern health videos cite an older (circa 1972) medical reference as using doses on the order of ~280,000 IU of vitamin D for certain autoimmune problems, as evidence that “doctors used to give enormous doses.” That reference could not be identified or checked for this page.
- Why that figure matters as a hazard. A dose of that size taken routinely is far above the 4,000 IU/day UL. Sustained intake at very high levels drives hypervitaminosis D, in which the body absorbs and mobilizes far too much calcium, producing hypercalcemia — nausea, excessive thirst and urination, confusion, kidney stones, kidney injury, soft-tissue and vascular calcification, and dangerous heart-rhythm disturbances. (The Toxicity and Safety section above details the mechanism.) Unlike sunlight, which the skin self-limits through photodegradation, swallowed vitamin D has no such brake.
- Today’s range of numbers. Current reference intakes are about 600 IU/day for most people (IOM 2011). A parallel camp of integrative practitioners argues that 600 IU is far too little and that most people need several thousand IU per day, with some claiming 6,000–10,000 IU/day. Readers today therefore meet very different figures: the large historical doses, a deliberately conservative RDA, and claims for 10,000 IU.
The Evidence-Based Middle Ground (Today)
Guideline bodies also differ on blood testing. Vitamin D status is measured by a blood test, 25-hydroxyvitamin D [25(OH)D], and the dose that raises it varies from person to person (body size, baseline level, skin tone, absorption, and obesity all change the response). The 2011 Endocrine Society guideline suggested measuring 25(OH)D in patients at risk of deficiency; the 2024 Endocrine Society guideline suggests against routine 25(OH)D testing in the general population, including people with obesity or dark complexion, because no trial evidence supports it. The reference figures are:
- RDA: 600 IU/day for most children and adults, 800 IU/day after age 70 (IOM 2011). The IOM set this from bone health, as the intake that keeps 25(OH)D at or above 20 ng/mL in at least 97.5% of people — not to reach the higher levels some studies associate with broader benefit.
- Tolerable Upper Intake Level: 4,000 IU/day for ages 9 and older. The IOM states that the UL is not a target intake and that the risk of harm begins to increase once intakes surpass it.
- Intakes to reach higher levels: the 2011 Endocrine Society guideline stated that adults may need at least 1,500–2,000 IU/day to keep 25(OH)D consistently above 30 ng/mL, while the IOM found that levels above 30 ng/mL were not consistently associated with greater benefit.
- On 10,000 IU/day: the 2011 Endocrine Society guideline described 10,000 IU/day as an amount that may be needed to correct deficiency in adults, not as a maintenance dose; the 2024 guideline suggests against empiric supplementation above the Dietary Reference Intakes for healthy adults younger than 75. (Practitioners’ higher protocols for specific conditions are described in Doses Described for Specific Uses above.)
Within that framework, the trials point to effects that are concentrated in correcting deficiency rather than in very high doses:
- Immunity: the 2017 meta-analysis found the largest reduction in respiratory infections in the most deficient people, with a smaller reduction in others, and the 2021 update found a small overall effect (see the Immune System section).
- Mood: the VITAL-DEP trial found no prevention of depression in adults not selected for deficiency; treatment trials in deficient patients with diagnosed depression are fewer and smaller (see Mental Health).
- Musculoskeletal & back pain: the diffuse bone and muscle pain of deficiency (osteomalacia) and proximal muscle weakness improve as 25(OH)D normalizes — this is repletion correcting a deficiency, not a painkiller effect of high doses.
- Pregnancy, infant skeleton & teeth: adequate maternal vitamin D supports fetal bone mineralization and tooth development and prevents neonatal rickets; a controlled trial found 4,000 IU/day safe and the most effective of the doses tested for reaching sufficiency in pregnancy (see Pregnancy and Fetal Development).
In short: the 1920s rickets cure was real; the very large doses described in online accounts of older texts are far above today’s upper limit; and current guidelines differ on routine testing and on intakes above the RDA.
Key Research Papers — History & Dosing
- Holick MF. Vitamin D Is Not as Toxic as Was Once Thought: A Historical and an Up-to-Date Perspective. Mayo Clinic Proceedings. 2015;90(5):561–564 — doi:10.1016/j.mayocp.2015.03.015
- Holick MF. Vitamin D Deficiency. New England Journal of Medicine. 2007;357(3):266–281 — doi:10.1056/NEJMra070553
- Holick MF, Binkley NC, Bischoff-Ferrari HA, et al. Evaluation, Treatment, and Prevention of Vitamin D Deficiency: an Endocrine Society Clinical Practice Guideline. The Journal of Clinical Endocrinology & Metabolism. 2011;96(7):1911–1930 — doi:10.1210/jc.2011-0385
- Hollis BW, Johnson D, Hulsey TC, Ebeling M, Wagner CL. Vitamin D supplementation during pregnancy: Double-blind, randomized clinical trial of safety and effectiveness. Journal of Bone and Mineral Research. 2011;26(10):2341–2357 — doi:10.1002/jbmr.463
Final Thoughts
Vitamin D3 is both a vitamin and the precursor of a hormone, calcitriol, which acts through receptors found in many tissues. Its role in bone mineralization and in preventing rickets and osteomalacia is established. The IOM’s 2011 committee found the evidence for cancer, cardiovascular disease, diabetes and autoimmune disorders inconsistent and insufficient to set requirements, and large trials since then have mostly found no reduction in cancer, cardiovascular events, fractures, falls or death in adults not selected for deficiency, alongside smaller benefits in some trials and meta-analyses for respiratory infections, autoimmune disease, cancer mortality and progression from prediabetes to diabetes. Natural medicine practitioners favor higher intakes and target levels than the official figures, while the 2024 Endocrine Society guideline suggests against supplementing above the reference intakes for healthy adults younger than 75 and against routine testing. Decisions about vitamin D doses and testing belong with a clinician.
Humans evolved making vitamin D in sunlit skin, and the receptor for its active form is found in cells throughout the body — which is why researchers continue to test what vitamin D does beyond bone.
Key Research Papers
- Ross AC, Manson JE, Abrams SA, et al. (2011). The 2011 report on dietary reference intakes for calcium and vitamin D from the Institute of Medicine: what clinicians need to know. J Clin Endocrinol Metab 96:53-8 — PubMed PMID: 21118827
- Holick MF, Binkley NC, Bischoff-Ferrari HA, et al. (2011). Evaluation, treatment, and prevention of vitamin D deficiency: an Endocrine Society clinical practice guideline. J Clin Endocrinol Metab 96:1911-30 — PubMed PMID: 21646368
- Demay MB, Pittas AG, Bikle DD, et al. (2024). Vitamin D for the Prevention of Disease: An Endocrine Society Clinical Practice Guideline. J Clin Endocrinol Metab 109:1907-1947 — PubMed PMID: 38828931
- Manson JE, Cook NR, Lee IM, et al. (2019). Vitamin D Supplements and Prevention of Cancer and Cardiovascular Disease. N Engl J Med 380:33-44 — PubMed PMID: 30415629
- Hahn J, Cook NR, Alexander EK, et al. (2022). Vitamin D and marine omega 3 fatty acid supplementation and incident autoimmune disease: VITAL randomized controlled trial. BMJ 376:e066452 — PubMed PMID: 35082139
- Neale RE, Baxter C, Romero BD, et al. (2022). The D-Health Trial: a randomised controlled trial of the effect of vitamin D on mortality. Lancet Diabetes Endocrinol 10:120-128 — PubMed PMID: 35026158
- Bischoff-Ferrari HA, Vellas B, Rizzoli R, et al. (2020). Effect of Vitamin D Supplementation, Omega-3 Fatty Acid Supplementation, or a Strength-Training Exercise Program on Clinical Outcomes in Older Adults: The DO-HEALTH Randomized Clinical Trial. JAMA 324:1855-1868 — PubMed PMID: 33170239
- Martineau AR, Jolliffe DA, Hooper RL, et al. (2017). Vitamin D supplementation to prevent acute respiratory tract infections: systematic review and meta-analysis of individual participant data. BMJ 356:i6583 — PubMed PMID: 28202713
- Jolliffe DA, Camargo CA Jr, Sluyter JD, et al. (2021). Vitamin D supplementation to prevent acute respiratory infections: a systematic review and meta-analysis of aggregate data from randomised controlled trials. Lancet Diabetes Endocrinol 9:276-292 — PubMed PMID: 33798465
- Pittas AG, Dawson-Hughes B, Sheehan P, et al. (2019). Vitamin D Supplementation and Prevention of Type 2 Diabetes. N Engl J Med 381:520-530 — PubMed PMID: 31173679
- Pittas AG, Kawahara T, Jorde R, et al. (2023). Vitamin D and Risk for Type 2 Diabetes in People With Prediabetes : A Systematic Review and Meta-analysis of Individual Participant Data From 3 Randomized Clinical Trials. Ann Intern Med 176:355-363 — PubMed PMID: 36745886
- Keum N, Lee DH, Greenwood DC, et al. (2019). Vitamin D supplementation and total cancer incidence and mortality: a meta-analysis of randomized controlled trials. Ann Oncol 30:733-743 — PubMed PMID: 30796437
- McCullough ML, Zoltick ES, Weinstein SJ, et al. (2019). Circulating Vitamin D and Colorectal Cancer Risk: An International Pooling Project of 17 Cohorts. J Natl Cancer Inst 111:158-169 — PubMed PMID: 29912394
- Bolland MJ, Grey A, Avenell A. (2018). Effects of vitamin D supplementation on musculoskeletal health: a systematic review, meta-analysis, and trial sequential analysis. Lancet Diabetes Endocrinol 6:847-858 — PubMed PMID: 30293909
- Yao P, Bennett D, Mafham M, et al. (2019). Vitamin D and Calcium for the Prevention of Fracture: A Systematic Review and Meta-analysis. JAMA Netw Open 2:e1917789 — PubMed PMID: 31860103
- DIPART (Vitamin D Individual Patient Analysis of Randomized Trials) Group. (2010). Patient level pooled analysis of 68 500 patients from seven major vitamin D fracture trials in US and Europe. BMJ 340:b5463 — PubMed PMID: 20068257
- LeBoff MS, Chou SH, Ratliff KA, et al. (2022). Supplemental Vitamin D and Incident Fractures in Midlife and Older Adults. N Engl J Med 387:299-309 — PubMed PMID: 35939577
- Sanders KM, Stuart AL, Williamson EJ, et al. (2010). Annual high-dose oral vitamin D and falls and fractures in older women: a randomized controlled trial. JAMA 303:1815-22 — PubMed PMID: 20460620
- Tripkovic L, Lambert H, Hart K, et al. (2012). Comparison of vitamin D2 and vitamin D3 supplementation in raising serum 25-hydroxyvitamin D status: a systematic review and meta-analysis. Am J Clin Nutr 95:1357-64 — PubMed PMID: 22552031
- Liu PT, Stenger S, Li H, et al. (2006). Toll-like receptor triggering of a vitamin D-mediated human antimicrobial response. Science 311:1770-3 — PubMed PMID: 16497887
- Ganmaa D, Uyanga B, Zhou X, et al. (2020). Vitamin D Supplements for Prevention of Tuberculosis Infection and Disease. N Engl J Med 383:359-368 — PubMed PMID: 32706534
- Jolliffe DA, Greenberg L, Hooper RL, et al. (2017). Vitamin D supplementation to prevent asthma exacerbations: a systematic review and meta-analysis of individual participant data. Lancet Respir Med 5:881-890 — PubMed PMID: 28986128
- Webb AR, Kline L, Holick MF. (1988). Influence of season and latitude on the cutaneous synthesis of vitamin D3: exposure to winter sunlight in Boston and Edmonton will not promote vitamin D3 synthesis in human skin. J Clin Endocrinol Metab 67:373-8 — PubMed PMID: 2839537
- MacLaughlin J, Holick MF. (1985). Aging decreases the capacity of human skin to produce vitamin D3. J Clin Invest 76:1536-8 — PubMed PMID: 2997282
- Neale RE, Khan SR, Lucas RM, et al. (2019). The effect of sunscreen on vitamin D: a review. Br J Dermatol 181:907-915 — PubMed PMID: 30945275
- Lu Z, Chen TC, Zhang A, et al. (2007). An evaluation of the vitamin D3 content in fish: Is the vitamin D content adequate to satisfy the dietary requirement for vitamin D? J Steroid Biochem Mol Biol 103:642-4 — PubMed PMID: 17267210
- Chu J, Gallos I, Tobias A, et al. (2018). Vitamin D and assisted reproductive treatment outcome: a systematic review and meta-analysis. Hum Reprod 33:65-80 — PubMed PMID: 29149263
- Uwitonze AM, Razzaque MS. (2018). Role of Magnesium in Vitamin D Activation and Function. J Am Osteopath Assoc 118:181-189 — PubMed PMID: 29480918
- Amon U, Yaguboglu R, Ennis M, et al. (2022). Safety Data in Patients with Autoimmune Diseases during Treatment with High Doses of Vitamin D3 According to the "Coimbra Protocol". Nutrients 14 — PubMed PMID: 35458137 (Uncontrolled case series.)
- Wagner CL, Greer FR. (2008). Prevention of rickets and vitamin D deficiency in infants, children, and adolescents. Pediatrics 122:1142-52 — PubMed PMID: 18977996
- Anglin RE, Samaan Z, Walter SD, et al. (2013). Vitamin D deficiency and depression in adults: systematic review and meta-analysis. Br J Psychiatry 202:100-7 — PubMed PMID: 23377209
- Gowda U, Mutowo MP, Smith BJ, et al. (2015). Vitamin D supplementation to reduce depression in adults: meta-analysis of randomized controlled trials. Nutrition 31:421-9 — PubMed PMID: 25701329
- Vellekkatt F, Menon V. (2019). Efficacy of vitamin D supplementation in major depression: A meta-analysis of randomized controlled trials. J Postgrad Med 65:74-80 — PubMed PMID: 29943744 (Note: its four pooled trials include the since-retracted Sepehrmanesh 2016 trial.)
- Sepehrmanesh Z, Kolahdooz F, Abedi F, et al. (2016). Vitamin D Supplementation Affects the Beck Depression Inventory, Insulin Resistance, and Biomarkers of Oxidative Stress in Patients with Major Depressive Disorder: A Randomized, Controlled Clinical Trial. J Nutr 146:243-8 — PubMed PMID: 26609167 — Retracted (retraction notice: PubMed PMID: 33974698)
- Okereke OI, Reynolds CF 3rd, Mischoulon D, et al. (2020). Effect of Long-term Vitamin D3 Supplementation vs Placebo on Risk of Depression or Clinically Relevant Depressive Symptoms and on Change in Mood Scores: A Randomized Clinical Trial. JAMA 324:471-480 — PubMed PMID: 32749491
- Patrick RP, Ames BN. (2014). Vitamin D hormone regulates serotonin synthesis. Part 1: relevance for autism. FASEB J 28:2398-413 — PubMed PMID: 24558199
PubMed Topic Searches
Connections
- Fluoride Chelation — part of the traditional fluorosis nutrition protocol
- UV Radiation — the synthesis pathway's other ledger: sun benefit vs sun damage
- All Vitamins
- Sunburn, Tanning & What UV Does to Your Skin — interactive animation
- How Your Skin Makes Vitamin D — interactive animation
- Bone Remodeling & Calcium Balance — interactive animation
- Vitamin D Deficiency — symptoms, causes, and recovery
- Vitamin D Toxicity — hypervitaminosis D symptoms, causes, and risks
- Vitamin K2 (Menaquinone) — the partner vitamin that directs the calcium D3 absorbs
- Calcium
- Calcium and Muscle Function — excitation-contraction coupling, cramps, tetany, and the calcium-magnesium balance for cardiac and skeletal muscle.
- Cancer
- Depression
- Diabetes
- Phosphorus
- Osteoporosis
- Vitamin D and Surgical Recovery
- Vitamin D3 and Bone Health
- Vitamin D3 and Immune System
- Vitamin D3 and Cancer Prevention
- Magnesium
- Psoriasis
- Vitamin D Test
- PCOS
- Cardiovascular Disease
- Insulin Resistance
- Celiac Disease
- Vitamin A
- Omega-3 Fatty Acids
- Conditions on this site that reference this page: Periodontitis (Gum Disease) · Dentistry & Oral Health · Alopecia · Basal Cell Carcinoma · Contact Dermatitis · Hidradenitis Suppurativa · Melanoma · Melasma
- Fat-Soluble Activators: Vitamins A, D and K2