⚠ Evidence warning: Clinical trials or other evidence do not support the claim that the VITAL autoimmune result has influenced clinical practice guidelines and public health recommendations. This page keeps it as a report of what people, websites or other media say.
Vitamin D3 and Immune System Regulation
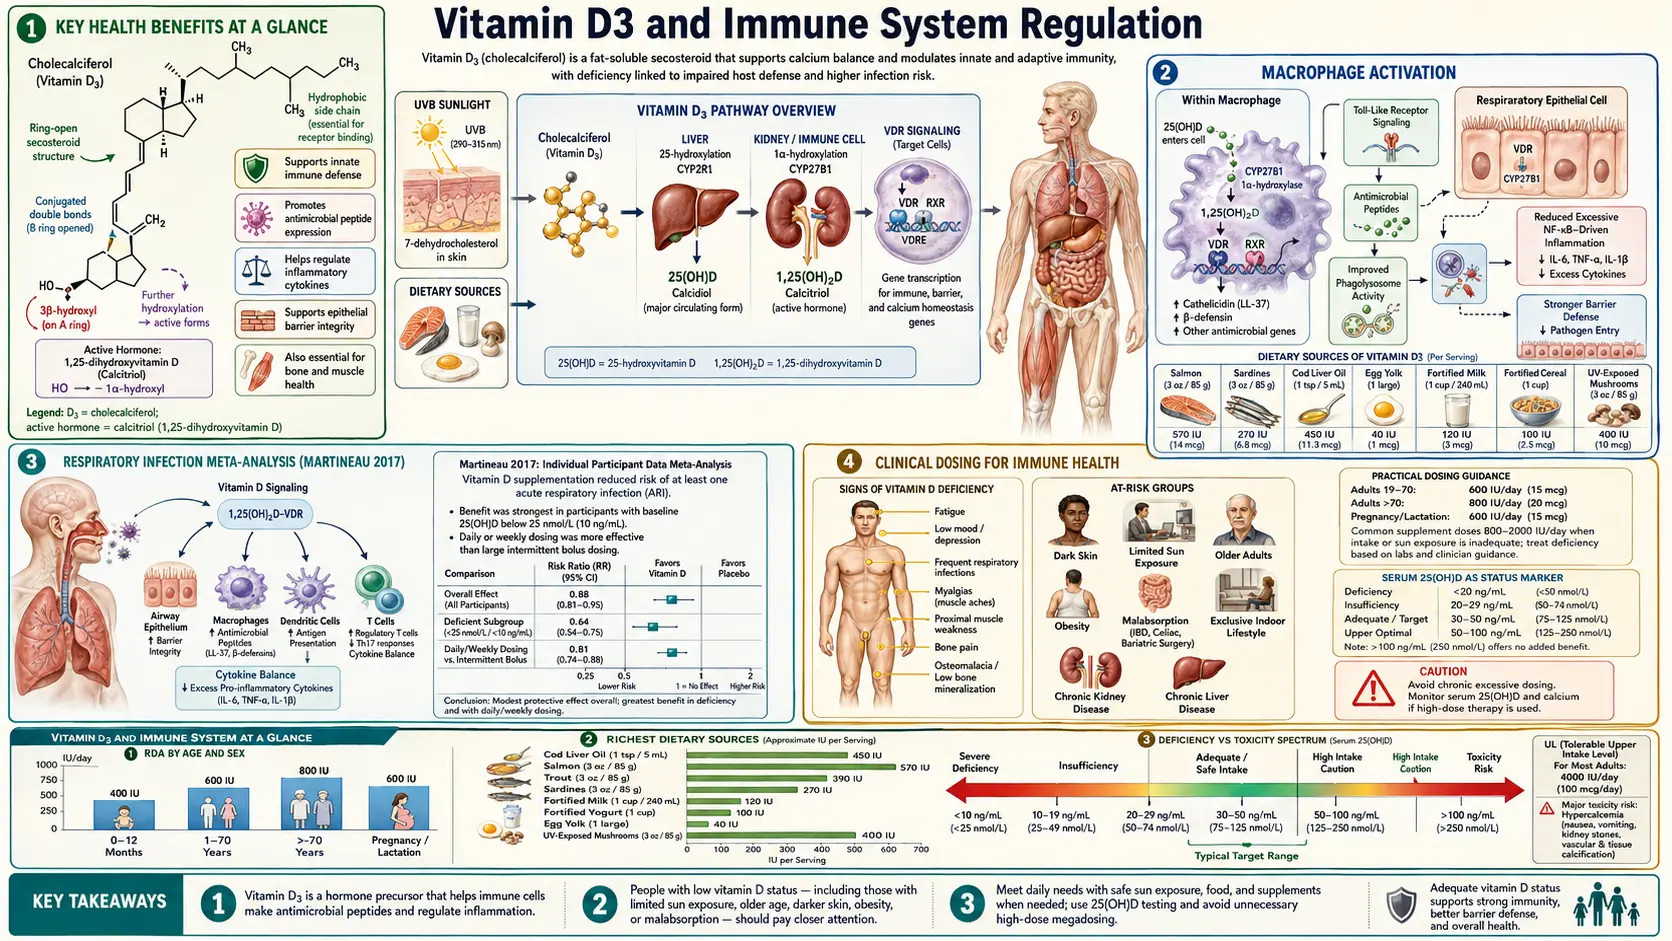
The discovery that virtually all immune cells express the vitamin D receptor (VDR) and that many possess the enzymatic machinery to convert 25(OH)D to active calcitriol locally has fundamentally changed our understanding of vitamin D3. Far beyond its classical role in calcium metabolism, vitamin D3 functions as a powerful immunomodulator, enhancing innate antimicrobial defenses while simultaneously regulating adaptive immune responses to prevent autoimmunity. The 2017 Martineau individual-participant-data meta-analysis in BMJ, pooling 25 randomized trials and 11,321 participants, found that vitamin D supplementation reduced acute respiratory infection risk by 12% overall — with a 70% reduction in participants starting below 10 ng/mL who took it daily or weekly. That was not the last word: the same research group's 2025 update, pooling 40 trials and 61,589 participants, found a similar but no longer statistically significant effect. The 2022 VITAL autoimmune substudy showed that 2,000 international units (IU)/day of D3 reduced confirmed autoimmune disease incidence by 22% in older adults, although two years after the trial ended that protection had faded.
Table of Contents
- Key Health Benefits at a Glance
- Vitamin D Receptor (VDR) in Immune Cells
- Cathelicidin (LL-37) Induction
- Defensin Production
- Macrophage Activation
- Th1/Th2/Th17/Treg Balance
- Autoimmune Disease Prevention
- VITAL Study: Autoimmune Disease Results
- Respiratory Infection Meta-Analysis (Martineau 2017)
- Tuberculosis Connection
- Cancer Immunosurveillance
- Latitude Gradient and Seasonal Immunity
- Clinical Dosing for Immune Health
- Key Research Papers
- Connections
- Featured Videos
Key Health Benefits at a Glance
The following is a high-level summary of the evidence-backed immune benefits of adequate vitamin D3 status. Each is explored in more depth below, and the supporting studies are linked in the Key Research Papers section.
- Cuts respiratory infections – Martineau et al. (2017, BMJ) pooled 25 randomized controlled trials (RCTs) of 11,321 participants and found a 12% reduction in acute respiratory infections overall, rising to 70% in those starting below 10 ng/mL; a 2025 update of 40 trials (61,589 participants) found a similar estimate that was no longer statistically significant.
- Reduces autoimmune disease incidence – The VITAL autoimmune substudy showed a 22% reduction in incident autoimmune disease (rheumatoid arthritis (RA), psoriasis, polymyalgia rheumatica, autoimmune thyroid, inflammatory bowel disease (IBD)) over 5 years with 2,000 international units/day; two years after the trial ended, the effect had faded.
- Induces the antimicrobial peptide cathelicidin – The CAMP gene carries a vitamin D response element; adequate 25(OH)D is required for macrophages to manufacture LL-37, the broad-spectrum peptide that kills bacteria, fungi, and enveloped viruses.
- Promotes regulatory T cells – Calcitriol expands FoxP3+ Tregs and tolerogenic dendritic cells, suppressing the Th17 responses implicated in multiple sclerosis (MS), rheumatoid arthritis, psoriasis, and inflammatory bowel disease.
- Protects pancreatic beta cells – Finnish birth cohort data (an observational study) link regular vitamin D supplementation in infancy with a much lower type 1 diabetes risk over about 30 years, and 2,000 international units/day with a 78% lower risk than smaller regular doses.
- Lowers multiple sclerosis risk along a latitude gradient – U.S. military data show a 62% lower multiple sclerosis risk in white service members with 25(OH)D above about 40 ng/mL compared to below about 25 ng/mL; no significant link was found in black and Hispanic service members.
- Enhances macrophage autophagy – Vitamin D-sufficient macrophages can clear intracellular M. tuberculosis via cathelicidin-driven autophagy, linking the pre-antibiotic heliotherapy era to modern molecular immunology.
- Balances inflammation – Calcitriol suppresses tumor necrosis factor-alpha, interleukin-6 (IL-6), and interleukin-1-beta while upregulating interleukin-10 (IL-10), promoting pathogen clearance without excessive tissue damage.
Vitamin D Receptor (VDR) in Immune Cells
- Widespread Expression – The VDR is expressed in monocytes, macrophages, dendritic cells, neutrophils, natural killer cells, and both T and B lymphocytes. This ubiquitous presence indicates that vitamin D signaling is integral to immune function across both the innate and adaptive arms.
- 1-Alpha-Hydroxylase (CYP27B1) – Immune cells, particularly macrophages and dendritic cells, express CYP27B1, the enzyme that converts circulating 25(OH)D to active 1,25(OH)2D (calcitriol). Unlike renal CYP27B1, which is regulated by parathyroid hormone (PTH) and calcium, immune cell CYP27B1 is regulated by immune signals such as toll-like receptor (TLR) activation and interferon-gamma. This allows immune cells to produce calcitriol locally in response to infection, independently of systemic calcium homeostasis.
- Autocrine and Paracrine Signaling – The locally produced calcitriol acts in an autocrine manner (on the producing cell) and paracrine manner (on neighboring immune cells) to modulate immune responses. This localized production depends entirely on the availability of the substrate 25(OH)D, directly linking circulating vitamin D status to immune competence.
- Genomic Effects – Once calcitriol binds the VDR, the receptor forms a heterodimer with the retinoid X receptor (RXR) and binds to vitamin D response elements (VDREs) in the promoter regions of target genes. In immune cells, calcitriol-VDR signaling regulates the expression of over 200 genes involved in antimicrobial defense, inflammation, and immune tolerance.
Cathelicidin (LL-37) Induction
- Discovery – The landmark 2006 study by Liu et al. demonstrated that activation of TLR2/1 on human macrophages by mycobacterial lipopeptides upregulates CYP27B1 and VDR, leading to local calcitriol production, which in turn induces the antimicrobial peptide cathelicidin (LL-37). This elegant mechanism directly linked vitamin D status to the innate ability to kill intracellular pathogens.
- Antimicrobial Properties – LL-37 is a 37-amino acid peptide with broad-spectrum antimicrobial activity. It kills bacteria by disrupting their cell membranes through electrostatic interactions with negatively charged lipid bilayers. LL-37 is also active against fungi, enveloped viruses (including influenza A and respiratory syncytial virus), and mycobacteria (including M. tuberculosis).
- Vitamin D Dependence – The cathelicidin gene (CAMP) contains a vitamin D response element in its promoter, making its expression directly dependent on VDR activation. Serum from vitamin D-deficient individuals fails to support cathelicidin induction in macrophages in vitro, while serum from vitamin D-sufficient individuals supports robust LL-37 production. This is one of the clearest demonstrations of how vitamin D deficiency impairs innate immunity.
- Beyond Direct Killing – LL-37 also functions as a chemoattractant, recruiting neutrophils, monocytes, and T cells to sites of infection. It modulates TLR signaling, promotes autophagy (an intracellular pathogen-clearing mechanism), and neutralizes bacterial endotoxin (lipopolysaccharide), reducing the risk of septic shock.
Defensin Production
- Beta-Defensins – Vitamin D induces the expression of beta-defensin 2 (DEFB4) and beta-defensin 4 in epithelial cells of the respiratory tract, skin, and gastrointestinal tract. These antimicrobial peptides provide a chemical barrier at mucosal surfaces, killing pathogens before they can establish infection.
- Barrier Defense – The induction of defensins by vitamin D strengthens the first line of defense at epithelial surfaces, which are the primary entry points for respiratory, gastrointestinal, and urogenital pathogens. This barrier-enhancing function helps explain the epidemiological association between vitamin D deficiency and increased susceptibility to mucosal infections.
Macrophage Activation
- Enhanced Phagocytosis – Calcitriol promotes macrophage differentiation from monocyte precursors and enhances phagocytic activity. Vitamin D-stimulated macrophages show increased expression of pattern recognition receptors and improved capacity to engulf and process pathogens.
- Autophagy Induction – Vitamin D promotes autophagy in macrophages through induction of the autophagy gene BECN1 (beclin-1) and cathelicidin-mediated activation of the autophagy machinery. Autophagy is a critical mechanism for killing intracellular pathogens such as M. tuberculosis that survive within phagosomes by preventing phagolysosomal fusion.
- Anti-Inflammatory Shift – While vitamin D enhances microbial killing, it simultaneously promotes an anti-inflammatory macrophage phenotype by suppressing pro-inflammatory cytokines (tumor necrosis factor-alpha, interleukin-6, interleukin-1-beta) and upregulating anti-inflammatory cytokines (interleukin-10). This balanced response enhances pathogen clearance while limiting collateral tissue damage.
Th1/Th2/Th17/Treg Balance
Vitamin D3 exerts profound effects on the differentiation and function of CD4+ T helper cell subsets, shifting the balance toward immune tolerance.
- Th1 Suppression – Calcitriol inhibits the differentiation and cytokine production of Th1 cells, which produce interferon-gamma and drive cell-mediated immunity. While Th1 responses are essential for intracellular pathogen defense, excessive Th1 activity underlies many organ-specific autoimmune diseases. Vitamin D moderates Th1 responses without eliminating them.
- Th2 Modulation – The effect of vitamin D on Th2 cells (which produce IL-4, IL-5, IL-13 and drive humoral immunity and allergic responses) is more nuanced. Some studies suggest vitamin D mildly promotes Th2 responses, potentially contributing to allergic sensitization in early life when given in excess, though this remains controversial.
- Th17 Suppression – Calcitriol strongly suppresses the differentiation of Th17 cells, which produce IL-17 and IL-22 and are major drivers of inflammatory and autoimmune pathology. Th17 cells are implicated in multiple sclerosis, rheumatoid arthritis, psoriasis, and inflammatory bowel disease. The suppression of Th17 differentiation is one of the most therapeutically relevant immune effects of vitamin D.
- Regulatory T Cell (Treg) Promotion – Vitamin D promotes the differentiation and function of FoxP3+ regulatory T cells, which suppress excessive immune responses and maintain self-tolerance. Tregs are critical for preventing autoimmunity, and their enhancement by vitamin D is considered a key mechanism underlying its protective effect against autoimmune diseases.
- Dendritic Cell Tolerogenesis – Vitamin D promotes a tolerogenic dendritic cell phenotype characterized by reduced expression of MHC class II molecules and co-stimulatory molecules (CD80, CD86), decreased IL-12 production, and increased interleukin-10 secretion. These tolerogenic dendritic cells preferentially induce Treg differentiation rather than effector T cell activation.
Autoimmune Disease Prevention
Epidemiological, genetic, and clinical evidence strongly links vitamin D status to autoimmune disease risk.
- Multiple Sclerosis (MS) – multiple sclerosis prevalence follows a striking latitude gradient, increasing with distance from the equator. Higher 25(OH)D levels are associated with reduced multiple sclerosis risk in prospective studies. Among white U.S. military personnel, those with 25(OH)D levels above about 40 ng/mL (99.1 nmol/L) had a 62 percent lower risk of developing multiple sclerosis compared to those with levels below about 25 ng/mL (63.3 nmol/L) (odds ratio 0.38). Among black and Hispanic personnel, who had lower vitamin D levels, the study found no significant association. Vitamin D supplementation may also reduce relapse rates in established multiple sclerosis, though evidence from randomized trials remains limited.
- Type 1 Diabetes (T1D) – A Finnish birth cohort study of 10,366 children born in 1966 (81 of whom developed T1D by the end of 1997) found that children given vitamin D regularly in the first year of life had an 88 percent lower rate of T1D than children given none (rate ratio 0.12), and that those who regularly took the then-recommended 2,000 international units daily had a 78 percent lower rate than those who regularly took less (rate ratio 0.22). The study was observational, so it shows an association rather than proof of cause. Meta-analyses confirm a consistent inverse association between vitamin D supplementation in infancy and T1D risk. Mechanistically, vitamin D protects pancreatic beta cells from autoimmune destruction by suppressing Th1/Th17 responses and promoting Tregs.
- Rheumatoid Arthritis (RA) – Low vitamin D levels are associated with increased rheumatoid arthritis risk and disease activity in observational studies. The Iowa Women's Health Study found that higher vitamin D intake was associated with a reduced risk of rheumatoid arthritis. Vitamin D supplementation may reduce disease activity in some rheumatoid arthritis patients, though evidence is inconsistent.
- Inflammatory Bowel Disease (IBD) – Both Crohn's disease and ulcerative colitis show latitude-dependent prevalence patterns and are associated with low vitamin D levels. Vitamin D deficiency is both a consequence (due to malabsorption and reduced sun exposure) and a potential contributor to inflammatory bowel disease pathogenesis through effects on intestinal barrier function and mucosal immunity.
VITAL Study: Autoimmune Disease Results
- Study Design – The VITAL study was a large randomized, double-blind, placebo-controlled trial of 25,871 U.S. adults (men aged 50 and older, women aged 55 and older) receiving 2,000 international units of vitamin D3 daily, 1 gram of omega-3 fatty acids daily, both, or placebo, with a median follow-up of 5.3 years.
- Primary Autoimmune Finding – The vitamin D arm showed a 22 percent reduction in confirmed autoimmune disease incidence (hazard ratio 0.78, 95% confidence interval 0.61 to 0.99, P = 0.05): 123 people in the vitamin D group and 155 in the placebo group developed a confirmed autoimmune disease over a median 5.3 years, in participants whose mean age was 67. This represented the first large randomized trial evidence that vitamin D supplementation can prevent autoimmune diseases.
- Diseases Included – The autoimmune endpoint included rheumatoid arthritis, polymyalgia rheumatica, autoimmune thyroid disease, psoriasis, and inflammatory bowel disease, among others. The effect appeared to strengthen over time, with greater risk reduction in years 3 through 5 compared to the first two years.
- Clinical Significance – The finding drew wide attention because it suggested that a simple, inexpensive intervention (2,000 international units vitamin D3 daily) could reduce autoimmune disease in older adults. The result has influenced clinical practice guidelines and public health recommendations. Later evidence tempered it. When 65 newly confirmed cases that had begun during the trial were added, the in-trial result became hazard ratio 0.85 (95% confidence interval 0.70 to 1.04), no longer statistically significant. The 2024 Endocrine Society guideline suggests against vitamin D above the Dietary Reference Intakes to lower disease risk in healthy adults younger than 75.
- After the Trial Ended – In a two-year follow-up of 21,592 VITAL participants, the protection from 2,000 international units/day of vitamin D had faded (hazard ratio 0.98 at 7 years; 255 cases in the vitamin D group against 259 on placebo). The omega-3 fatty acid arm (1,000 mg/day) kept a modest effect (hazard ratio 0.83).
Respiratory Infection Meta-Analysis (Martineau 2017)
- Study Overview – The individual participant data meta-analysis by Martineau et al., published in the BMJ in 2017, analyzed 25 randomized controlled trials including 11,321 participants aged 0 to 95 years. This rigorous methodology (using individual-level data rather than study-level summaries) provided the strongest available evidence on vitamin D and respiratory infections.
- Overall Results – Vitamin D supplementation reduced the risk of acute respiratory tract infections by 12 percent overall (adjusted odds ratio 0.88, 95% confidence interval (CI) 0.81 to 0.96). The benefit was seen across all age groups.
- Subgroup with Greatest Benefit – The most striking finding was in participants with baseline 25(OH)D levels below 10 ng/mL (25 nmol/L), who experienced a 70 percent reduction in respiratory infection risk with daily or weekly supplementation (adjusted odds ratio (OR) 0.30, 95% confidence interval 0.17 to 0.53). This suggests that correcting frank deficiency has the most dramatic protective effect.
- Dosing Frequency – Daily or weekly dosing was protective, while intermittent bolus dosing (monthly or less frequently) showed no significant benefit. This finding is consistent with the hypothesis that maintaining stable circulating 25(OH)D levels is important for continuous immune readiness.
- The 2025 Update – The same research group updated the analysis in 2025 with 40 trials and 61,589 participants. Vitamin D against placebo no longer had a statistically significant effect on acute respiratory infection (odds ratio 0.94, 95% confidence interval 0.88 to 1.00, P = 0.057), and the effect did not differ by age, starting vitamin D level, dose size or daily versus bolus dosing. Vitamin D did not change the share of people with serious side effects. The authors concluded that the confidence interval "now includes 1·00, indicating no statistically significant protection."
Tuberculosis Connection
- Historical Context – Before the antibiotic era, tuberculosis was treated with sunlight therapy (heliotherapy) and cod liver oil, both of which increase vitamin D levels. The Nobel Prize-winning use of ultraviolet (UV) light therapy for lupus vulgaris (cutaneous tuberculosis, TB) by Niels Finsen in 1903 likely worked in part through vitamin D-mediated cathelicidin induction.
- Mechanistic Link – The TLR2/1-mediated vitamin D-cathelicidin pathway was discovered specifically in the context of macrophage defense against M. tuberculosis. Vitamin D-sufficient macrophages can kill intracellular M. tuberculosis through cathelicidin-mediated autophagy; vitamin D-deficient macrophages cannot.
- Epidemiological Evidence – Vitamin D deficiency is a consistent risk factor for tuberculosis in observational studies, and tuberculosis patients typically have lower 25(OH)D levels than matched controls. Immigrants from equatorial countries to northern latitudes show increased tuberculosis susceptibility as their vitamin D levels decline.
- Clinical Trials – Adjunctive vitamin D supplementation in tuberculosis treatment has shown mixed results in randomized trials. In a 2011 London trial by Martineau et al., 146 adults with pulmonary tuberculosis received four doses of 2.5 mg vitamin D3 or placebo during the first phase of standard treatment. Overall, vitamin D did not significantly speed the clearing of tuberculosis from the sputum (median 36.0 against 43.5 days; adjusted hazard ratio 1.39, 95% confidence interval 0.90 to 2.16, P = 0.14). It did speed clearance in patients with the tt genotype of the TaqI VDR polymorphism (adjusted hazard ratio 8.09), suggesting pharmacogenomic factors influence treatment response.
Cancer Immunosurveillance
- VDR Expression in Immune and Epithelial Cells – The vitamin D receptor is expressed in nearly every cell of the immune system as well as in colonic, breast, and prostatic epithelium. Calcitriol signaling through VDR promotes cell-cycle arrest (upregulation of p21 and p27), differentiation, and apoptosis in premalignant cells, while simultaneously supporting the cytotoxic activity of natural killer cells and CD8+ T lymphocytes that eliminate transformed cells.
- Colorectal Cancer – Prospective cohort studies and meta-analyses of observational data consistently show an inverse association between circulating 25(OH)D and colorectal cancer incidence. Higher vitamin D status is also associated with improved survival after colorectal cancer diagnosis. Proposed mechanisms include Wnt/beta-catenin pathway suppression, enhanced mucosal immunity, and modulation of the colonic microbiome.
- VITAL Cancer Endpoints – The VITAL trial did not find a significant reduction in overall cancer incidence with 2,000 international units daily vitamin D3 over 5 years, but post-hoc analyses suggested reductions in cancer mortality and in advanced (metastatic or fatal) cancer, particularly among participants with a normal body mass index. These findings support the hypothesis that vitamin D primarily affects cancer progression rather than initiation.
- Clinical Implications – While vitamin D supplementation is not promoted as a cancer prevention strategy in isolation, maintaining 25(OH)D levels in the sufficient range (30 to 50 ng/mL) is consistent with both immune competence and a lower observed burden of several cancers in population studies.
Latitude Gradient and Seasonal Immunity
- Solar ultraviolet B (UVB) and Vitamin D Synthesis – Cutaneous vitamin D3 production requires ultraviolet B radiation (wavelength 290 to 315 nm). At latitudes above approximately 35 degrees North (or South), ultraviolet B intensity is insufficient for vitamin D synthesis during winter months. In Boston (42 degrees North), there is essentially no cutaneous vitamin D production from November through February. In northern Scandinavia, the "vitamin D winter" extends from October through March.
- Seasonal Infection Patterns – The winter peak in respiratory infections (influenza, respiratory syncytial virus (RSV), common cold) coincides with the nadir of population vitamin D levels. While indoor crowding and low humidity also contribute, the seasonal decline in vitamin D-dependent immune defenses (particularly cathelicidin and defensin production) may be a significant factor in seasonal infection susceptibility.
- Latitude and Autoimmunity – Multiple sclerosis, type 1 diabetes, and inflammatory bowel disease all show increasing prevalence with increasing latitude, mirroring the gradient of declining ultraviolet B exposure and vitamin D synthesis. This pattern, observed across multiple continents and ethnic groups, is one of the strongest ecological arguments for a causal role of vitamin D in autoimmune disease prevention.
Clinical Dosing for Immune Health
- Minimum Effective Level – Many practitioners hold that most immune benefits of vitamin D require 25(OH)D levels of at least 30 ng/mL (75 nmol/L). The 2017 Martineau meta-analysis found the largest benefit in people starting below 10 ng/mL, although its 2025 update found no difference by starting level. The 2024 Endocrine Society guideline found "no clear evidence defining the optimal target level of 25(OH)D required for disease prevention."
- Target Range – Many immunologists and functional medicine practitioners recommend targeting 25(OH)D levels of 40 to 60 ng/mL (100 to 150 nmol/L) for optimal immune function, based on the levels at which cathelicidin induction and immune cell function are maximized in laboratory studies. This is a practitioner view; no trial has shown that this range prevents disease.
- Daily Dosing – Practitioners who aim for levels of 40 to 60 ng/mL report that most adults need 2,000 to 5,000 international units of vitamin D3 daily to reach them, depending on baseline levels, body weight, skin pigmentation, sun exposure, and genetic factors affecting vitamin D metabolism.
- Loading Dose for Deficiency – For individuals with documented deficiency (below 20 ng/mL), a loading regimen of 5,000 to 10,000 international units daily for 8 to 12 weeks, followed by a maintenance dose, is described as restoring levels quickly. Weekly doses of 50,000 international units for 8 weeks are an alternative approach commonly used in clinical practice.
- Cofactors – Optimal vitamin D metabolism requires adequate magnesium (a cofactor for both 25-hydroxylase and 1-alpha-hydroxylase), vitamin K2 (which works synergistically with vitamin D to direct calcium to bones rather than soft tissues), and adequate vitamin A to prevent VDR competition. Practitioners who build comprehensive supplementation plans commonly include these cofactors.
- Monitoring – Practitioners who adjust doses commonly use regular 25(OH)D testing (every 3 to 6 months during dose adjustment, annually once stable) to track both deficiency and excess, particularly in obese individuals, those with malabsorption, and those taking medications that affect vitamin D metabolism (anticonvulsants, glucocorticoids, antiretrovirals). The 2024 Endocrine Society guideline, by contrast, "suggests against routine 25(OH)D testing" in the general populations it considered, including people with obesity or dark skin, because no trial evidence supported it.
The 2024 Endocrine Society clinical practice guideline on vitamin D for preventing disease suggests extra ("empiric") vitamin D for children and teenagers aged 1 to 18, adults over 75, pregnant people, and people with high-risk prediabetes. For healthy adults younger than 75 it suggests against vitamin D above the Dietary Reference Intakes to lower disease risk, and against routine blood testing, because no trial has defined an optimal 25(OH)D target. It found the best doses unclear, and for people over 50 who take vitamin D it suggests daily doses rather than occasional high doses. The guideline does not apply to people with an established medical reason for vitamin D treatment or testing.
This content is provided for informational purposes only and does not constitute medical advice. In granulomatous diseases (such as sarcoidosis and tuberculosis) and some lymphomas, immune cells make active vitamin D outside the kidney's control, as described above, which can raise blood calcium; hyperparathyroidism and chronic kidney disease also change how the body handles vitamin D and calcium. The Institute of Medicine's tolerable upper intake level for adults is 4,000 international units a day.
Key Research Papers
The following are landmark and frequently cited research papers underpinning the claims on this page. Links resolve to the publisher DOI or PubMed record.
Foundational Reviews
- Holick MF. Vitamin D deficiency. New England Journal of Medicine. 2007;357(3):266-281. — doi:10.1056/NEJMra070553
- Bikle DD. Vitamin D metabolism, mechanism of action, and clinical applications. Chemistry & Biology. 2014;21(3):319-329. — doi:10.1016/j.chembiol.2013.12.016
Respiratory Infection
- Martineau AR, Jolliffe DA, Hooper RL, et al. Vitamin D supplementation to prevent acute respiratory tract infections: systematic review and meta-analysis of individual participant data. BMJ. 2017;356:i6583. — doi:10.1136/bmj.i6583
- Liu PT, Stenger S, Li H, Wenzel L, Tan BH, et al. Toll-like receptor triggering of a vitamin D-mediated human antimicrobial response. Science. 2006;311(5768):1770-1773. doi:10.1126/science.1123933 — PubMed PMID: 16497887
- Jolliffe DA, Camargo CA Jr, Sluyter JD, et al. Vitamin D supplementation to prevent acute respiratory infections: systematic review and meta-analysis of stratified aggregate data. Lancet Diabetes & Endocrinology. 2025;13(4):307-320. doi:10.1016/S2213-8587(24)00348-6 — PubMed PMID: 39993397
- Martineau AR, Timms PM, Bothamley GH, et al. High-dose vitamin D(3) during intensive-phase antimicrobial treatment of pulmonary tuberculosis: a double-blind randomised controlled trial. Lancet. 2011;377(9761):242-250. doi:10.1016/S0140-6736(10)61889-2 — PubMed PMID: 21215445
Autoimmune Disease
- Hahn J, Cook NR, Alexander EK, et al. Vitamin D and marine omega 3 fatty acid supplementation and incident autoimmune disease: VITAL randomized controlled trial. BMJ. 2022;376:e066452. doi:10.1136/bmj-2021-066452 — PubMed PMID: 35082139
- Munger KL, Levin LI, Hollis BW, Howard NS, Ascherio A. Serum 25-hydroxyvitamin D levels and risk of multiple sclerosis. JAMA. 2006;296(23):2832-2838. doi:10.1001/jama.296.23.2832 — PubMed PMID: 17179460
- Hyppönen E, Läärä E, Reunanen A, Järvelin MR, Virtanen SM. Intake of vitamin D and risk of type 1 diabetes: a birth-cohort study. Lancet. 2001;358(9292):1500-1503. doi:10.1016/S0140-6736(01)06580-1 — PubMed PMID: 11705562
- Costenbader KH, Cook NR, Lee IM, et al. Vitamin D and Marine n-3 Fatty Acids for Autoimmune Disease Prevention: Outcomes Two Years After Completion of a Double-Blind, Placebo-Controlled Trial. Arthritis & Rheumatology. 2024;76(6):973-983. doi:10.1002/art.42811 — PubMed PMID: 38272846
Overall Mortality and Broader Outcomes
- Chowdhury R, Kunutsor S, Vitezova A, et al. Vitamin D and risk of cause specific death: systematic review and meta-analysis. BMJ. 2014;348:g1903. — doi:10.1136/bmj.g1903
- Manson JE, Cook NR, Lee IM, et al. Vitamin D supplements and prevention of cancer and cardiovascular disease (VITAL). New England Journal of Medicine. 2019;380(1):33-44. — doi:10.1056/NEJMoa1809944
- Demay MB, Pittas AG, Bikle DD, et al. Vitamin D for the Prevention of Disease: An Endocrine Society Clinical Practice Guideline. Journal of Clinical Endocrinology & Metabolism. 2024;109(8):1907-1947. doi:10.1210/clinem/dgae290 — PubMed PMID: 38828931