Artificial Sweeteners: Research Findings and Regulatory Status

Table of Contents
- A Brief History of Artificial Sweeteners
- The Six FDA-Approved High-Intensity Sweeteners
- How Sweeteners Activate Sweet Taste Receptors
- Gut Microbiome Findings
- Diet Drinks and Weight Gain in Observational Studies
- Glucose and Insulin Responses
- Cancer Findings and Regulatory Responses
- Neurological Findings
- Cardiovascular Findings
- Appetite and Brain Reward Studies
- Plant-Derived Sweeteners and Sugar Alcohols
- Calories and Biological Activity
- Regulatory History and Criticism
- Summary
- Key Research Papers
- Connections
- Featured Videos
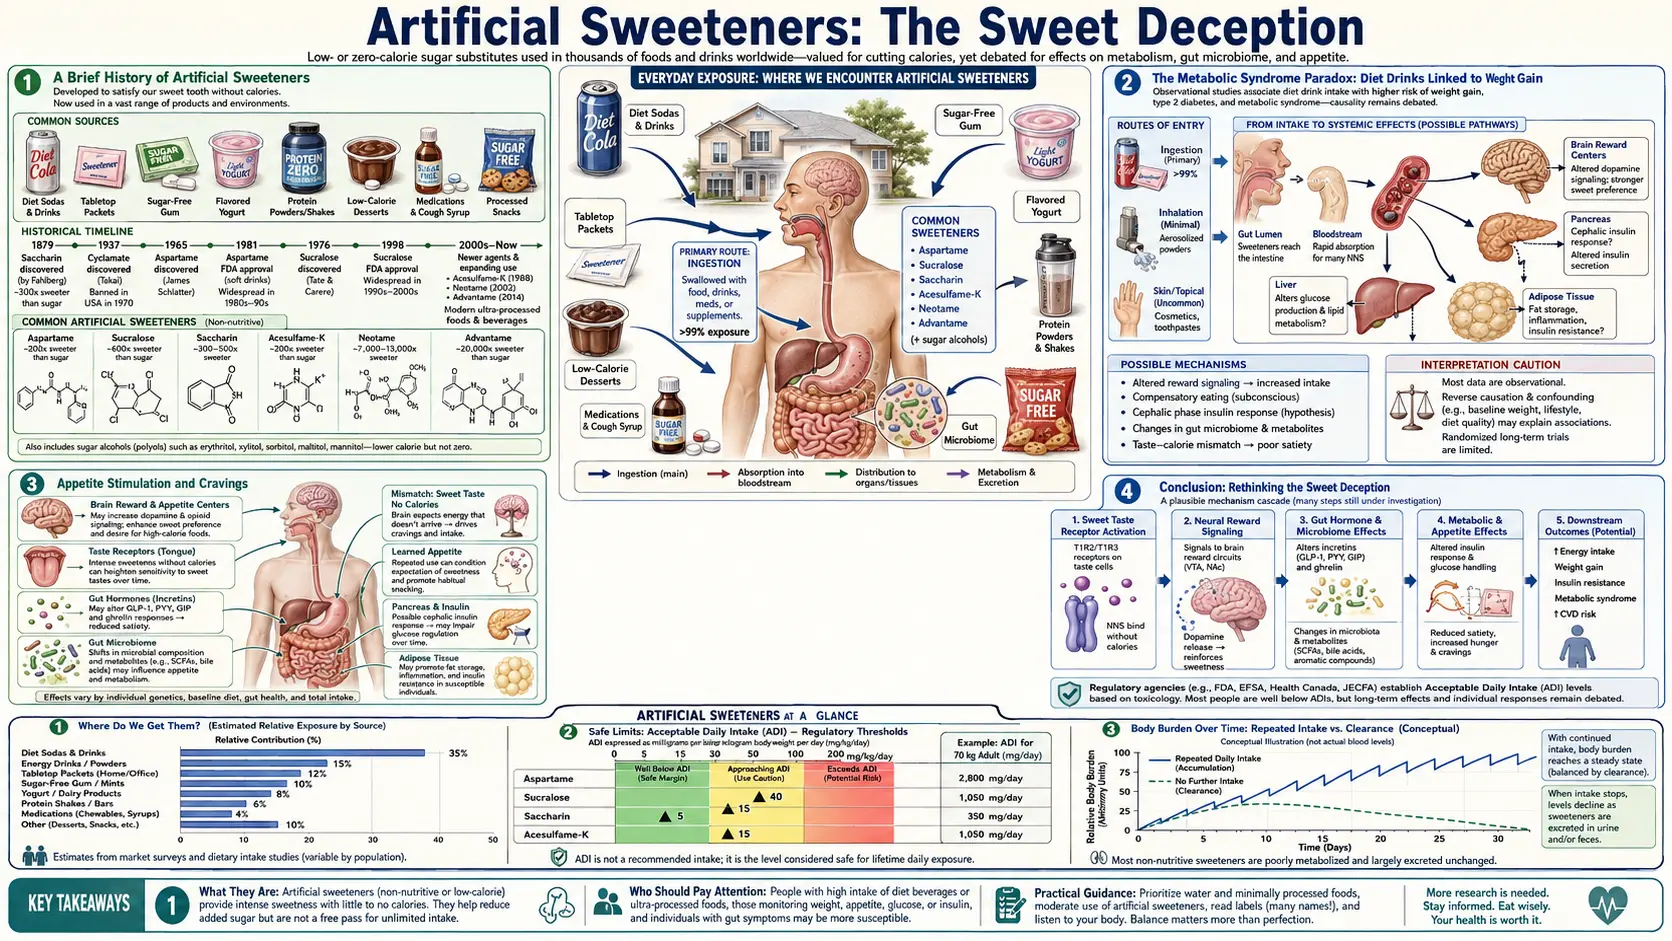
Artificial sweeteners are high-intensity sugar substitutes that provide sweetness with few or no calories. They are used in diet and “zero” drinks, sugar-free gum, yogurts, baked goods, tabletop sweeteners and some medicines. Regulators in the United States and Europe, and the Joint FAO/WHO Expert Committee on Food Additives (JECFA), consider the approved sweeteners safe at intakes within their acceptable daily intakes (ADIs). Research over the past two decades has reported effects on gut bacteria and glucose responses, associations with weight gain, cancer and cardiovascular disease in observational studies, and cancer findings in some animal studies; many of these findings come from animal, cell or observational studies, and several are disputed. In 2023 the International Agency for Research on Cancer (IARC) classified aspartame as possibly carcinogenic to humans, and the World Health Organization (WHO) issued a conditional recommendation against using non-sugar sweeteners for weight control. This page sets out what the studies and agencies reported; the aspartame, sucralose and acesulfame potassium pages cover each sweetener in more detail.
A Brief History of Artificial Sweeteners
By the usual accounts, the main synthetic sweeteners were found by accident. Saccharin was discovered in 1879 by Constantin Fahlberg, working at Johns Hopkins University on coal-tar derivatives. Cyclamate followed in 1937, aspartame in 1965 (found by a chemist working on an anti-ulcer drug) and sucralose in 1976 (during work on chlorinated sugar compounds). None of these compounds was developed as a food; each was found to taste sweet and was then put through the food-additive approval process.
The Six FDA-Approved High-Intensity Sweeteners
The US Food and Drug Administration (FDA) has approved six high-intensity sweeteners as food additives. The figures below are those given on the FDA’s sweeteners page. Two plant-derived sweeteners, high-purity steviol glycosides and monk fruit extracts, reach the US market instead through GRAS (generally recognized as safe) notices to which the FDA has raised no questions.
- Aspartame — About 200 times sweeter than sugar. First approved in 1974; after objections and a public board of inquiry, the FDA approved it for dry foods in 1981 and as a general-purpose sweetener in 1996. It is the methyl ester of a dipeptide of two amino acids, aspartic acid and phenylalanine, and releases methanol when digested. Because it supplies phenylalanine, US labels must carry the statement “PHENYLKETONURICS: CONTAINS PHENYLALANINE” (21 CFR 172.804). The FDA ADI is 50 mg/kg body weight per day. IARC classified it as “possibly carcinogenic to humans” (Group 2B) in July 2023; JECFA kept its ADI of 40 mg/kg.
- Sucralose — About 600 times sweeter than sugar; approved in 1998 for 15 food categories and in 1999 as a general-purpose sweetener; FDA ADI 5 mg/kg. Three hydroxyl groups on sucrose are replaced with chlorine atoms. Most of an oral dose is excreted unchanged, but studies have reported effects on gut bacteria and glucose responses, chlorinated breakdown products when it is heated, and genotoxicity of a related manufacturing impurity, sucralose-6-acetate, in cell assays; these are covered on the sucralose page.
- Saccharin — 200 to 700 times sweeter than sugar; FDA ADI 15 mg/kg. In the early 1970s saccharin was linked to bladder cancer in laboratory rats, and Congress required a warning label. In 2000 the US National Toxicology Program removed saccharin from its list of potential carcinogens, and the warning label is no longer required.
- Acesulfame Potassium (Ace-K) — About 200 times sweeter than sugar; approved in 1988 for specific uses and in 2003 as a general-purpose sweetener; FDA ADI 15 mg/kg. It is often blended with other sweeteners. It is manufactured using dichloromethane (methylene chloride) as a solvent; in its 2025 re-evaluation the European Food Safety Authority (EFSA) reported dichloromethane in tested samples as below the 1 ppm limit of detection and considered residual solvent unlikely. A US consumer advocacy group objected to its approval in 1988 and 1995, arguing that its long-term cancer studies were inadequate; the FDA denied those objections.
- Neotame — Approved in 2002; approximately 7,000 to 13,000 times sweeter than sugar; FDA ADI 0.3 mg/kg. It is a derivative of aspartame. Its US regulation (21 CFR 172.829) contains no phenylketonuria label statement.
- Advantame — Approved in 2014; approximately 20,000 times sweeter than sugar, the highest figure among the six; FDA ADI 32.8 mg/kg. It is also an aspartame derivative, and its regulation (21 CFR 172.803) likewise contains no phenylketonuria label statement.
How Sweeteners Activate Sweet Taste Receptors
Sweet taste is detected by the T1R2/T1R3 receptor, which recognizes chemically diverse compounds perceived as sweet, natural sugars and sweeteners alike. High-intensity sweeteners activate this receptor at very low concentrations, which is why they taste many times sweeter than sugar, while supplying few or no calories.
A 2014 review reports that a functional sweet taste receptor has also been found outside the mouth, in the gut, pancreas, bladder, brain, bone and fat tissue, and that in the gut it has been suggested to take part in glucose sensing, the release of some satiety hormones and glucose homeostasis (Laffitte et al., 2014). One hypothesis, tested in rats by Swithers and Davidson (2008), is that sweet taste without calories weakens the body’s learned link between sweetness and energy; this is discussed with the observational studies below.
Gut Microbiome Findings
Suez et al. (2014, Nature), at the Weizmann Institute of Science, reported that in mice, commonly used non-caloric sweetener formulations (saccharin, sucralose and aspartame) drove glucose intolerance through changes in the gut microbiota. The effect was abolished by antibiotics and transferred to germ-free mice by faecal transplant, and the abstract reports similar changes in gut bacteria and glucose intolerance in healthy human subjects. The abstract does not break the human results down by sweetener.
The same group then ran a randomized controlled trial (Suez et al., 2022, Cell) in 120 healthy adults given saccharin, sucralose, aspartame or stevia sachets for two weeks, at doses below the ADI. Each sweetener altered the stool and oral microbiome and the plasma metabolome; saccharin and sucralose significantly impaired glycemic responses. The authors describe the effects as person-specific and call for assessment of their clinical implications.
Diet Drinks and Weight Gain in Observational Studies
Several prospective cohort studies have found that people who drank more artificially sweetened beverages gained more weight or developed more metabolic disease:
- Weight gain — In the San Antonio Heart Study, 3,682 adults were re-examined 7–8 years after baseline. Consuming more than 21 artificially sweetened beverages a week, compared with none, was associated with almost double the risk of becoming overweight or obese among people of normal weight at baseline (Fowler et al., 2008).
- Metabolic syndrome and type 2 diabetes — In the Multi-Ethnic Study of Atherosclerosis (MESA), drinking diet soda at least daily was associated with a 36% greater relative risk of incident metabolic syndrome and a 67% greater relative risk of incident type 2 diabetes compared with not drinking it (Nettleton et al., 2009, Diabetes Care). The authors note that observational data cannot establish causality.
- Waist circumference — In the San Antonio Longitudinal Study of Aging, 749 adults aged 65 and older were followed for a total of about 9.4 years. The adjusted increase in waist circumference per follow-up interval among diet soda users was almost triple that of non-users (Fowler et al., 2015).
- Soft drinks and metabolic syndrome — In the Framingham Heart Study, middle-aged adults who drank one or more soft drinks a day had higher odds of developing metabolic syndrome over about four years (odds ratio 1.44) than those who drank less than one (Dhingra et al., 2007). The abstract reports soft drinks as a single category and does not report type 2 diabetes.
Associations of this kind may reflect reverse causation: people who are already gaining weight or at metabolic risk may be the ones who switch to diet drinks. Animal experiments have tested a direct mechanism. In rats, Swithers and Davidson (2008) found that experience with a sweet taste that did not predict calories (saccharin) led to increased caloric intake, body weight and adiposity and blunted thermic responses to sweet-tasting diets. WHO’s 2023 guideline rated the evidence on non-sugar sweeteners and disease outcomes as low certainty, because the associations might be confounded by the baseline characteristics of study participants.
Glucose and Insulin Responses
Sweeteners supply little or no glucose, but several studies have reported effects on glucose and insulin responses under specific conditions:
- Sucralose before a glucose drink — Pepino et al. (2013) gave 17 obese adults who did not normally use such sweeteners a sucralose drink 10 minutes before a glucose load. Compared with water, sucralose produced a 20 ± 8% greater incremental insulin response. The study tested sucralose together with glucose, not sucralose alone.
- Sucralose with a carbohydrate — Dalenberg et al. (2020, Cell Metabolism) found that seven sucralose-sweetened drinks consumed with, but not without, a carbohydrate over 10 days decreased insulin sensitivity in healthy adults, and that the decrease correlated with reduced brain responses to sweet taste.
- Acesulfame potassium in rats — Acesulfame potassium increased insulin release from isolated rat pancreatic islets in a dose- and glucose-dependent way (Liang et al., 1987, in vitro), and an intravenous injection of 150 mg/kg raised plasma insulin in anaesthetized rats without changing blood glucose (Liang et al., 1987, in vivo). These were animal and laboratory experiments.
- Aspartame — In a 1987 crossover trial of 40 people who reported headaches after aspartame, a 30 mg/kg challenge produced no treatment-related changes in plasma insulin or glucagon (Schiffman et al., 1987).
Whether these short-term effects lead to insulin resistance or type 2 diabetes over time has not been shown in trials.
Cancer Findings and Regulatory Responses
In July 2023, IARC classified aspartame as “possibly carcinogenic to humans” (Group 2B) on the basis of limited evidence for cancer in humans, specifically for hepatocellular carcinoma (a type of liver cancer), with limited evidence in experimental animals and limited mechanistic evidence (Riboli et al., 2023). In the same month JECFA kept its ADI for aspartame at 0–40 mg/kg body weight, and the FDA stated that it disagrees with IARC’s conclusion.
The Ramazzini Institute in Italy reported lifetime feeding studies in which aspartame increased lymphomas and leukaemias in rats, at doses down to 20 mg/kg body weight a day (Soffritti et al., 2006), and EFSA concluded after each of its reviews of these studies that there was no reason to revise the ADI; the details are on the aspartame page. Saccharin was linked to bladder cancer in rats in the 1970s and was removed from the US list of potential carcinogens in 2000. For sucralose, a manufacturing intermediate and impurity, sucralose-6-acetate, was genotoxic in two cell-based assays (Schiffman et al., 2023); EFSA’s 2026 re-evaluation found no safety concern for genotoxicity of sucralose, its impurities and its degradation products.
In the French NutriNet-Santé cohort of 102,865 adults followed for a median of 7.8 years, higher consumers of artificial sweeteners had a higher risk of overall cancer than non-consumers (hazard ratio 1.13), particularly for aspartame (1.15) and acesulfame potassium (1.13), with higher risks also observed for breast cancer and obesity-related cancers (Debras et al., 2022, PLOS Medicine). The authors list potential selection bias, residual confounding and reverse causality among the study’s limitations.
Neurological Findings
Most of the neurological research concerns aspartame, and the results differ between studies:
- Headaches — In a randomized, double-blind crossover trial of people who reported headaches after aspartame, participants reported headaches on 33% of days on aspartame (about 30 mg/kg a day) and 24% on placebo, with no difference in the length or intensity of headaches (Van den Eeden et al., 1994). An earlier double-blind trial in 40 similar subjects found aspartame no more likely than placebo to produce headache (Schiffman et al., 1987).
- Seizures — In mice, aspartame pretreatment increased seizures induced by convulsant drugs, an effect reproduced by phenylalanine (Pinto and Maher, 1988). Controlled trials in children with epilepsy (Shaywitz et al., 1994) and in people who reported aspartame-related seizures (Rowan et al., 1995) found no seizures provoked by aspartame.
- Mood and cognition — Healthy adults on a high-aspartame diet (25 mg/kg a day) for 8 days had more irritable mood and more depression and performed worse on spatial orientation tests than on a low-aspartame diet (10 mg/kg a day); working memory was unaffected (Lindseth et al., 2014).
- Aspartic acid and methanol — Aspartame is broken down into phenylalanine, aspartic acid and methanol, which the body converts to formaldehyde and formic acid. EFSA’s 2013 re-evaluation concluded that these breakdown products are also naturally present in other foods, that methanol from aspartame is a small portion of total methanol exposure, and that aspartame does not harm the brain or nervous system at current intakes.
Cardiovascular Findings
In the NutriNet-Santé cohort of 103,388 participants, total artificial sweetener intake was associated with a higher risk of cardiovascular disease (hazard ratio 1.09) and particularly of cerebrovascular disease (1.18). Aspartame intake was associated with cerebrovascular events (1.17), and acesulfame potassium (1.40) and sucralose (1.31) with coronary heart disease (Debras et al., 2022, BMJ). The authors describe the findings as suggesting a potential direct association.
In the Nurses’ Health Study and the Health Professionals Follow-up Study (118,363 adults), artificially sweetened beverages were associated with total and cardiovascular mortality only in the highest intake category (two or more a day), and only among women; the authors state that this finding requires further confirmation (Malik et al., 2019). Sugar-sweetened beverages showed a graded association with mortality in the same study.
Appetite and Brain Reward Studies
In a functional MRI study of 12 healthy women, sucrose and sucralose both activated primary taste pathways, but sucrose produced a stronger response in several brain regions, and only sucrose engaged dopaminergic midbrain areas in relation to how pleasant it tasted (Frank et al., 2008). The authors suggest that this could affect how well artificial sweeteners substitute for sugar.
In fruit flies, a sucralose-supplemented diet produced a sustained increase in food and calories consumed, along with hyperactivity, insomnia and glucose intolerance, effects reversed when sucralose was removed; the researchers traced the response to a neuronal starvation pathway and reported that a sweet/energy-imbalanced diet also increased food intake in mammals through an NPY-dependent mechanism (Wang et al., 2016). These are animal studies.
Plant-Derived Sweeteners and Sugar Alcohols
Several other sweeteners are used as sugar substitutes. They have their own research findings:
- Stevia — High-purity steviol glycosides from the leaves of Stevia rebaudiana, 200 to 400 times sweeter than sugar according to the FDA. In the 2022 Weizmann Institute trial (Suez et al.), stevia also altered the stool and oral microbiome, although it was not one of the two sweeteners that significantly impaired glycemic responses.
- Monk fruit (luo han guo) — Extracts of Siraitia grosvenorii, sweetened by mogrosides; 100 to 250 times sweeter than sugar according to the FDA. Long-term human research on it is limited.
- Erythritol — A sugar alcohol. In a 2023 Nature Medicine study, higher circulating erythritol was associated with incident major adverse cardiovascular events in US and European cohorts of people undergoing cardiac evaluation; erythritol enhanced platelet reactivity in vitro and thrombosis formation in animal experiments, and in 8 healthy volunteers erythritol ingestion raised plasma levels above the thresholds associated with heightened platelet reactivity. The authors call for studies of its long-term safety (Witkowski et al., 2023).
- Allulose — A rare sugar found in small amounts in some foods. The FDA allows a factor of 0.4 calories per gram for allulose on nutrition labels and excludes it from “Total Sugars” and “Added Sugars”. Long-term human studies are limited.
WHO’s 2023 guideline on non-sugar sweeteners covers stevia and other naturally occurring non-nutritive sweeteners, but not low-calorie sugars or sugar alcohols such as erythritol.
Calories and Biological Activity
Sweeteners are often discussed only in terms of calories. The studies above show that some of them also interact with sweet taste receptors in and beyond the mouth, alter gut bacteria in some experiments and affect glucose and insulin responses under specific conditions. These findings concern biological activity; whether they cause harm in people at usual intakes is what the agencies and the observational studies disagree about.
On 15 May 2023 WHO issued a guideline making a conditional recommendation against using non-sugar sweeteners for weight control or to reduce the risk of noncommunicable diseases. It states that they do not confer any long-term benefit in reducing body fat in adults or children, and that its evidence review suggested potential undesirable effects from long-term use, such as an increased risk of type 2 diabetes, cardiovascular diseases and mortality in adults. The recommendation is conditional because the certainty of the evidence is low; it does not apply to people with pre-existing diabetes, and WHO notes that it is not a toxicological safety assessment.
Regulatory History and Criticism
Aspartame’s US approval was contested for several years. A 2019 review of the documentary record (Millstone and Dawson) describes how the FDA’s 1974 approval was held up by objections and by questions about how the developer’s toxicology studies had been conducted; a public board of inquiry recommended in 1980 that aspartame not be approved pending further study of brain tumours, and the FDA Commissioner approved it for dry foods in 1981, against that advice. The same review argues that EFSA’s 2013 re-evaluation judged every one of 73 studies indicating possible harm unreliable, while judging most studies indicating no harm reliable. EFSA concluded in 2013 that aspartame is safe at current intakes.
For acesulfame potassium, a consumer advocacy group objected in 1988 and again in 1995 that the long-term rodent studies were inadequate to show the sweetener does not cause cancer. The FDA denied the objections; its 1998 response states that it had judged the first rat study inadequate, and that a second rat study together with a mouse study showed no association with cancer.
Industry funding has also been studied. A systematic review of reviews on artificially sweetened beverages and weight found that reviews sponsored by the artificial sweetener industry were more likely to report favourable results and conclusions, and that reviews by authors with financial conflicts of interest with the food industry were more likely to have favourable conclusions (Mandrioli et al., 2016).
Summary
Regulators conclude that the approved sweeteners are safe within their ADIs; EFSA’s recent re-evaluations kept the sucralose ADI and raised the acesulfame potassium ADI. Independent research has reported effects on gut bacteria and glucose responses, associations with weight gain, metabolic disease, cancer and cardiovascular disease in cohort studies, and cancer findings in some rodent studies. Much of that evidence is observational or from animals and cells, several findings have been contested, and WHO rates the evidence on disease outcomes as low certainty. Questions about sweeteners and an individual’s health belong with a clinician.
Related Pages
Key Research Papers
The papers and regulatory documents behind the statements on this page. Links resolve to PubMed records, publisher DOIs, or the originating regulatory body.
Gut Microbiome, Glucose and Insulin
- Suez J, Korem T, Zeevi D, et al. Artificial sweeteners induce glucose intolerance by altering the gut microbiota. Nature. 2014;514:181-186. — doi:10.1038/nature13793
- Suez J, Cohen Y, Valdés-Mas R, et al. Personalized microbiome-driven effects of non-nutritive sweeteners on human glucose tolerance. Cell. 2022;185(18):3307-3328.e19. — PubMed PMID: 35987213
- Pepino MY, Tiemann CD, Patterson BW, Wice BM, Klein S. Sucralose affects glycemic and hormonal responses to an oral glucose load. Diabetes Care. 2013;36(9):2530-2535. — PubMed PMID: 23633524
- Dalenberg JR, Patel BP, Denis R, et al. Short-term consumption of sucralose with, but not without, carbohydrate impairs neural and metabolic sensitivity to sugar in humans. Cell Metab. 2020;31(3):493-502.e7. — PubMed PMID: 32130881
- Liang Y, Maier V, Steinbach G, Lalić L, Pfeiffer EF. The effect of artificial sweetener on insulin secretion. II. Stimulation of insulin release from isolated rat islets by Acesulfame K (in vitro experiments). Horm Metab Res. 1987;19(7):285-289. — PubMed PMID: 2887503
- Liang Y, Steinbach G, Maier V, Pfeiffer EF. The effect of artificial sweetener on insulin secretion. 1. The effect of acesulfame K on insulin secretion in the rat (studies in vivo). Horm Metab Res. 1987;19(6):233-238. — PubMed PMID: 2887500
- Laffitte A, Neiers F, Briand L. Functional roles of the sweet taste receptor in oral and extraoral tissues. Curr Opin Clin Nutr Metab Care. 2014;17(4):379-385. — PubMed PMID: 24763065
Weight, Metabolic Disease and Mortality
- Fowler SP, Williams K, Resendez RG, Hunt KJ, Hazuda HP, Stern MP. Fueling the obesity epidemic? Artificially sweetened beverage use and long-term weight gain. Obesity (Silver Spring). 2008;16(8):1894-1900. — PubMed PMID: 18535548
- Nettleton JA, Lutsey PL, Wang Y, Lima JA, Michos ED, Jacobs DR Jr. Diet soda intake and risk of incident metabolic syndrome and type 2 diabetes in the Multi-Ethnic Study of Atherosclerosis (MESA). Diabetes Care. 2009;32(4):688-694. — PubMed PMID: 19151203
- Fowler SP, Williams K, Hazuda HP. Diet soda intake is associated with long-term increases in waist circumference in a biethnic cohort of older adults: the San Antonio Longitudinal Study of Aging. J Am Geriatr Soc. 2015;63(4):708-715. — PubMed PMID: 25780952
- Dhingra R, Sullivan L, Jacques PF, et al. Soft drink consumption and risk of developing cardiometabolic risk factors and the metabolic syndrome in middle-aged adults in the community. Circulation. 2007;116(5):480-488. — PubMed PMID: 17646581
- Swithers SE, Davidson TL. A role for sweet taste: calorie predictive relations in energy regulation by rats. Behav Neurosci. 2008;122(1):161-173. — PubMed PMID: 18298259
- Malik VS, Li Y, Pan A, et al. Long-term consumption of sugar-sweetened and artificially sweetened beverages and risk of mortality in US adults. Circulation. 2019;139(18):2113-2125. — PubMed PMID: 30882235
- Debras C, Chazelas E, Sellem L, et al. Artificial sweeteners and risk of cardiovascular diseases: results from the prospective NutriNet-Santé cohort. BMJ. 2022;378:e071204. — PubMed PMID: 36638072
Cancer
- Riboli E, Beland FA, Lachenmeier DW, et al. Carcinogenicity of aspartame, methyleugenol, and isoeugenol. Lancet Oncol. 2023;24(8):848-850. — PubMed PMID: 37454664
- Soffritti M, Belpoggi F, Degli Esposti D, et al. First experimental demonstration of the multipotential carcinogenic effects of aspartame administered in the feed to Sprague-Dawley rats. Environ Health Perspect. 2006;114(3):379-385. — PubMed PMID: 16507461
- Debras C, Chazelas E, Srour B, et al. Artificial sweeteners and cancer risk: results from the NutriNet-Santé population-based cohort study. PLoS Med. 2022;19(3):e1003950. — PubMed PMID: 35324894
- Schiffman SS, Scholl EH, Furey TS, Nagle HT. Toxicological and pharmacokinetic properties of sucralose-6-acetate and its parent sucralose: in vitro screening assays. J Toxicol Environ Health B Crit Rev. 2023;26(6):307-341. — PubMed PMID: 37246822
Neurological Effects
- Van den Eeden SK, Koepsell TD, Longstreth WT Jr, et al. Aspartame ingestion and headaches: a randomized crossover trial. Neurology. 1994;44(10):1787-1793. — PubMed PMID: 7936222
- Schiffman SS, Buckley CE 3rd, Sampson HA, et al. Aspartame and susceptibility to headache. N Engl J Med. 1987;317(19):1181-1185. — PubMed PMID: 3657889
- Pinto JM, Maher TJ. Administration of aspartame potentiates pentylenetetrazole- and fluorothyl-induced seizures in mice. Neuropharmacology. 1988;27(1):51-55. — PubMed PMID: 3352866
- Shaywitz BA, Anderson GM, Novotny EJ, et al. Aspartame has no effect on seizures or epileptiform discharges in epileptic children. Ann Neurol. 1994;35(1):98-103. — PubMed PMID: 7506878
- Rowan AJ, Shaywitz BA, Tuchman L, et al. Aspartame and seizure susceptibility: results of a clinical study in reportedly sensitive individuals. Epilepsia. 1995;36(3):270-275. — PubMed PMID: 7614911
- Lindseth GN, Coolahan SE, Petros TV, Lindseth PD. Neurobehavioral effects of aspartame consumption. Res Nurs Health. 2014;37(3):185-193. — PubMed PMID: 24700203
Appetite, Brain Reward and Other Sweeteners
- Frank GK, Oberndorfer TA, Simmons AN, et al. Sucrose activates human taste pathways differently from artificial sweetener. Neuroimage. 2008;39(4):1559-1569. — PubMed PMID: 18096409
- Wang QP, Lin YQ, Zhang L, et al. Sucralose promotes food intake through NPY and a neuronal fasting response. Cell Metab. 2016;24(1):75-90. — PubMed PMID: 27411010
- Witkowski M, Nemet I, Alamri H, et al. The artificial sweetener erythritol and cardiovascular event risk. Nat Med. 2023;29(3):710-718. — PubMed PMID: 36849732
Regulation and Research Funding
- Millstone EP, Dawson E. EFSA’s toxicological assessment of aspartame: was it even-handedly trying to identify possible unreliable positives and unreliable negatives? Arch Public Health. 2019;77:34. — PubMed PMID: 31338189
- Mandrioli D, Kearns CE, Bero LA. Relationship between research outcomes and risk of bias, study sponsorship, and author financial conflicts of interest in reviews of the effects of artificially sweetened beverages on weight outcomes: a systematic review of reviews. PLoS One. 2016;11(9):e0162198. — PubMed PMID: 27606602
- EFSA Panel on Food Additives and Flavourings (FAF). Re-evaluation of acesulfame K (E 950) as food additive. EFSA J. 2025;23(4):e9317. — PubMed PMID: 40309404
- US Food and Drug Administration. Food additives permitted for direct addition to food for human consumption; acesulfame potassium. Final rule; response to objection. Federal Register. 1998;63(128):36362-36365. — govinfo 98-17701
Regulatory and Authoritative Resources
- FDA — Aspartame and Other Sweeteners in Food.
- World Health Organization. Aspartame hazard and risk assessment results released. News release, 14 July 2023. — WHO news release
- World Health Organization. Use of non-sugar sweeteners: WHO guideline. Geneva: WHO; 15 May 2023. — WHO publication 9789240073616
- European Food Safety Authority. EFSA completes full risk assessment on aspartame and concludes it is safe at current levels of exposure. News release, 10 December 2013. — EFSA news release
- US Food and Drug Administration. Guidance for industry: the declaration of allulose and calories from allulose on Nutrition and Supplement Facts labels. — FDA guidance
Connections
Featured Videos