⚠ Evidence warning: Clinical trials or other evidence do not support the claims that graded motor imagery and mirror therapy work better than almost anything else and that roughly 70% of patients substantially recover within the first year while the remaining 20-30% develop persistent or progressive disease. This page keeps it as a report of what people, websites or other media say.
Complex Regional Pain Syndrome (CRPS / RSD)
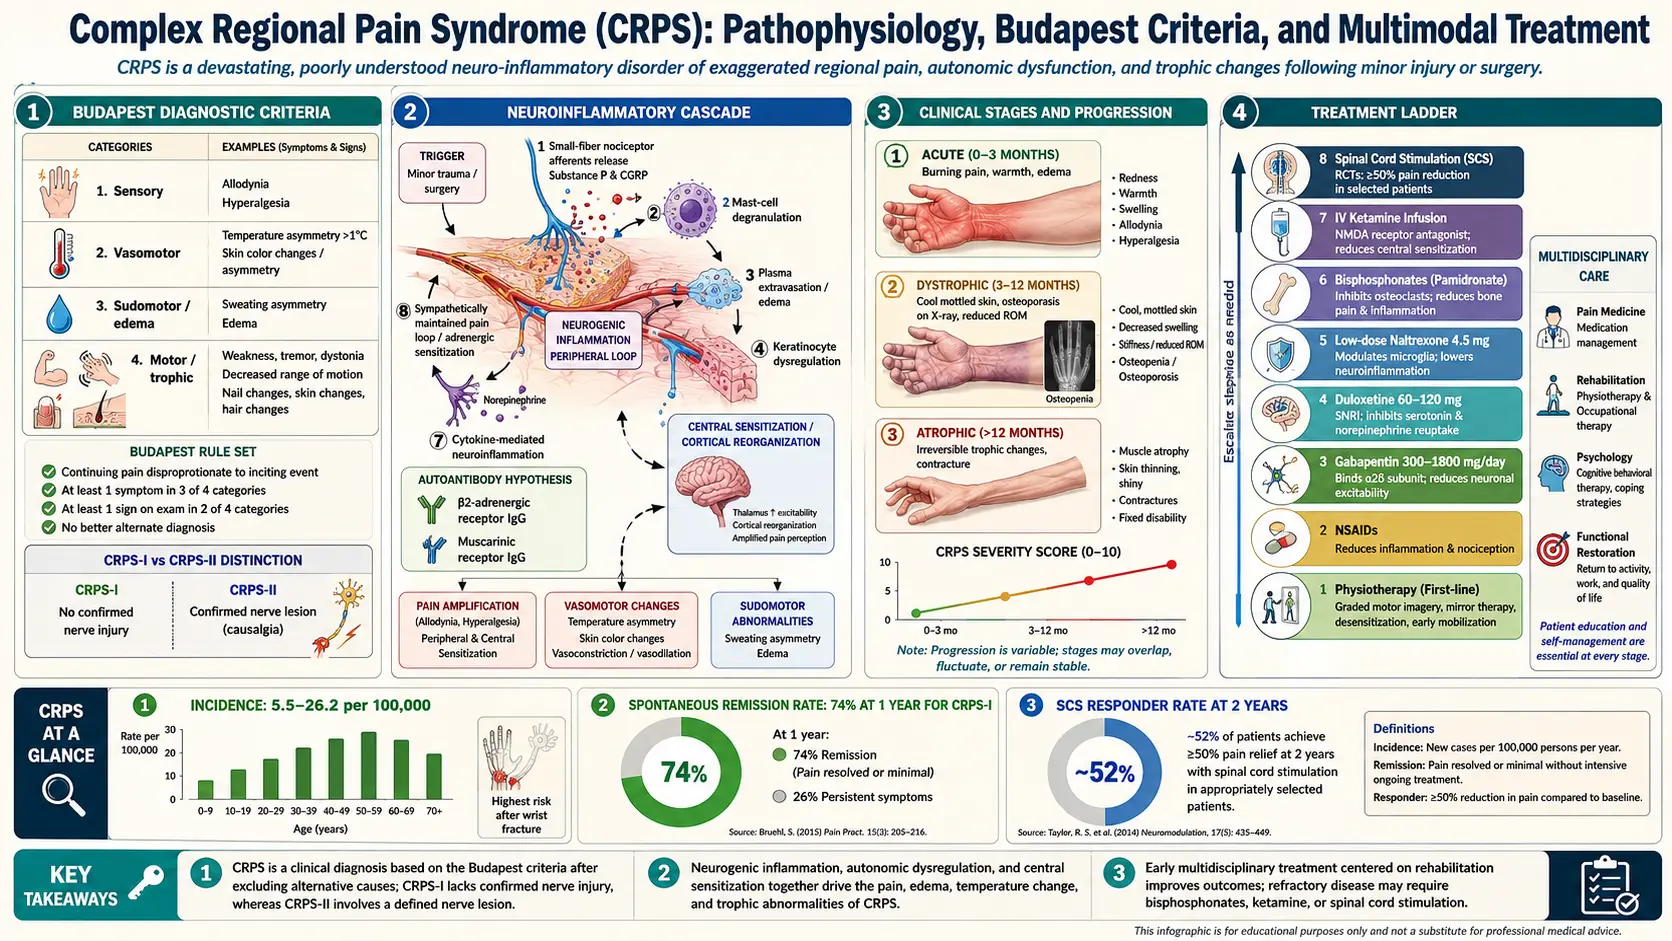
Table of Contents
- What CRPS Is
- Type I vs Type II
- Typical Triggers
- Budapest Diagnostic Criteria
- Pathophysiology — What Goes Wrong
- Stages and Natural History
- Early Mobilization — First-Line Treatment
- Graded Motor Imagery and Mirror Therapy
- Medications Used for CRPS
- Bisphosphonates (Pamidronate, Neridronate)
- Ketamine Infusions
- Sympathetic Nerve Blocks
- Spinal Cord and Dorsal Root Ganglion Stimulation
- Refractory CRPS — When Nothing Works
- Vitamin C Prophylaxis for Distal Radius Fracture
- Living With CRPS
- Key Research Papers
- Connections
- Featured Videos
What CRPS Is
Complex Regional Pain Syndrome (CRPS) — still called Reflex Sympathetic Dystrophy (RSD) in older charts and among long-time patients — is a chronic pain disorder that usually starts in a single limb after a relatively minor injury. The defining feature is a mismatch between the injury and the response: a wrist fracture that should heal in eight weeks instead triggers burning pain, swelling, color and temperature changes, sweating, hair and nail changes, and eventually weakness and stiffness that persist for months or years.
CRPS is uncommon but not rare. The best epidemiology, from a Dutch population study, puts the incidence at about 26 cases per 100,000 person-years, with women affected roughly three times more often than men. The upper limb is involved about twice as often as the lower limb. Most cases follow a fracture, sprain, surgery, or crush injury — but roughly 10% have no identifiable trigger at all.
Two points run through the rest of this article: outcomes are described as better the earlier CRPS is treated, and active movement is the treatment CRPS care puts first, ahead of rest, immobilization, or opioids. The sections below explain why.
Type I vs Type II
CRPS is split into two subtypes by whether a nerve injury can be identified:
- CRPS Type I (formerly RSD). No demonstrable nerve injury. The inciting event is tissue damage — a fracture, a sprain, a bruise, a surgery — without a named nerve having been cut or compressed. About 90% of CRPS cases are Type I.
- CRPS Type II (formerly causalgia). A specific peripheral nerve injury can be identified — for example, a severed median nerve during carpal tunnel release, or a traction injury to the brachial plexus. The pain and autonomic changes behave the same way clinically; the only difference is the identifiable nerve lesion.
The distinction matters for insurance coding and for surgical planning (Type II occasionally responds to nerve repair) but not for most day-to-day treatment. Both subtypes are managed the same way: early mobilization, graded sensory and motor rehabilitation, and a stepwise ladder of medications and procedures.
Typical Triggers
CRPS almost always follows something. The most common triggers, in rough order:
- Distal radius (wrist) fracture — the single most studied trigger, and the setting where vitamin C prophylaxis has been tested (see below). Roughly 3–7% of wrist fractures develop CRPS.
- Foot and ankle sprains or fractures, including lateral ankle sprains that seemed trivial at the time.
- Elective surgery on a limb — carpal tunnel release, trigger finger release, ankle arthroscopy, knee replacement, bunion correction.
- Crush injuries and soft-tissue trauma without fracture.
- Prolonged immobilization — casting or splinting for longer than necessary appears to increase risk in susceptible people.
- Stroke, myocardial infarction, or spinal cord injury — "shoulder-hand syndrome" is a CRPS-like presentation after stroke.
- No identifiable trigger in roughly 10% of cases.
The size of the trigger does not predict the size of the response. A sprained ankle can produce severe, treatment-resistant CRPS; a shattered tibia often heals without any CRPS at all. Something about the individual nervous system — genetics, prior central sensitization, inflammation profile, psychological state at the time of injury — tips the balance.
Budapest Diagnostic Criteria
CRPS has no blood test and no imaging finding that confirms it. Diagnosis is clinical, using the Budapest Criteria, published as proposed criteria by Harden and colleagues in 2007 and tested in a 2010 validation study against the older criteria of the International Association for the Study of Pain (IASP). To meet criteria, a patient must have:
- Continuing pain that is disproportionate to any inciting event.
- At least one symptom reported by the patient in three of four categories:
- Sensory: hyperesthesia (painfully heightened sensation) or allodynia (pain from a non-painful touch, like a bedsheet or a breeze).
- Vasomotor: temperature asymmetry, skin color changes, or color asymmetry between the two limbs.
- Sudomotor / edema: swelling, sweating changes, or sweating asymmetry.
- Motor / trophic: decreased range of motion, weakness, tremor, dystonia, or trophic changes (skin, hair, or nails looking abnormal).
- At least one sign observed by the clinician at the time of evaluation in two or more of the same four categories.
- No other diagnosis better explains the signs and symptoms.
The Budapest Criteria are strict on purpose. In the 2010 validation study (113 people with CRPS type I and 47 with other nerve pain), the older 1994 IASP criteria picked up every CRPS case (sensitivity 1.00) but correctly ruled out only 41% of the people who did not have CRPS (specificity 0.41), a weakness that can lead to overdiagnosis. The Budapest clinical criteria kept sensitivity at 0.99 and raised specificity to 0.68. For research, an even stricter "research Budapest" version requires symptoms in all four categories and signs in two or more; in the 2010 study this research version reached a specificity of 0.79.
Two later updates matter. In 2021 an international group published the Valencia consensus, an adaptation of the IASP CRPS diagnostic criteria. A 2024 review in The Lancet Neurology reports that better understanding of the mechanisms has led to CRPS being classified as a chronic primary pain disorder, that its subtypes have been updated, and that the procedures for diagnosis have been clarified; it also notes that effective treatment of CRPS remains a challenge.
A few practical notes. First, the signs — especially temperature and color changes — can wax and wane, and a single normal exam at the orthopedist's office does not rule out CRPS; photos taken during a flare can show changes that are absent on the day of an exam. Second, triple-phase bone scintigraphy can support the diagnosis in early CRPS by showing periarticular uptake, but a normal scan does not exclude it. Third, sympathetic nerve blocks (discussed below) are a treatment, not a diagnostic test — response or non-response does not confirm or rule out CRPS.
Pathophysiology — What Goes Wrong
CRPS is the clearest clinical example in medicine of a nervous system that has learned pain and cannot unlearn it. Five overlapping mechanisms drive the syndrome:
Peripheral sensitization and neurogenic inflammation
After the inciting injury, C-fibers in the affected limb become hyperexcitable. They release substance P, calcitonin gene-related peptide (CGRP), and other neuropeptides into the local tissue, causing vasodilation, plasma extravasation, and swelling — the warm, red, puffy early-stage limb. This is called neurogenic inflammation, and it is why nonsteroidal anti-inflammatory drugs (NSAIDs) and ice usually do little.
Small-fiber nerve loss
Skin biopsies from CRPS limbs show a measurable reduction in small-fiber nerve density compared with the unaffected limb — a partial small-fiber neuropathy confined to the region of pain. This explains the mixed picture of numbness plus hypersensitivity: the large fibers still work, but the small fibers that carry temperature and pain are damaged and misfiring.
Central sensitization
Repeated input from the inflamed limb rewires the spinal cord dorsal horn. N-methyl-D-aspartate (NMDA) receptors become hyperactive, gamma-aminobutyric acid-mediated inhibition weakens, and non-painful inputs (light touch, normal joint movement) start being interpreted as pain. This is the same central sensitization process that drives fibromyalgia, nociplastic pain, and chronic low back pain — which is why ketamine (a N-methyl-D-aspartate antagonist) and gabapentinoids (which dampen excitatory signaling) sometimes help.
Immune dysregulation
CRPS patients have elevated circulating pro-inflammatory cytokines (tumor necrosis factor-alpha, interleukin-1, interleukin-6) and, in many cases, autoantibodies against autonomic nervous system targets such as the beta-2 adrenergic receptor and the muscarinic-2 receptor. These antibodies can cause vasomotor and sudomotor dysfunction when passively transferred to animals. The implication is that at least a subset of CRPS is a low-grade autoimmune disorder — which is why intravenous immunoglobulin (IVIG) and plasmapheresis have been tried. Results have been modest and inconsistent, and the largest IVIG trial (LIPS, 2017) found low-dose IVIG no better than placebo (see Refractory CRPS below).
Cortical reorganization
Functional magnetic resonance imaging (MRI) studies show that the cortical map of the affected limb shrinks in the primary somatosensory cortex, and the brain's representation of the limb becomes distorted. Patients often describe the affected hand or foot as feeling "not mine," swollen when it isn't, or misshapen. Graded motor imagery and mirror therapy are designed specifically to reverse this cortical remapping — and they work better than almost anything else we have; the trials of these methods are described below.
Stages and Natural History
Older textbooks describe three sequential stages (warm, dystrophic, atrophic). Modern research has shown the staged model is misleading — CRPS does not march predictably through phases, and many patients cycle between "warm" and "cold" presentations without ever entering a truly atrophic stage. What is more useful:
- Warm CRPS: red, hot, swollen, usually within the first 6–12 months. Most responsive to treatment.
- Cold CRPS: cool, bluish or mottled, often drier. Associated with longer duration, more central sensitization, and worse prognosis.
Prognosis varies widely, and long-lasting problems are more common than older figures suggested. In population-based cohorts, roughly 70% of patients have substantial recovery within the first year with appropriate treatment. The remaining 20–30% develop persistent or progressive disease. A 2022 systematic review of 22 studies of people whose CRPS had lasted 12 months or more found that pain and reduced movement or strength were still present in 51–89% of them at 12 months or later. On average, grip strength was 25–66% lower and range of motion 20–25% lower; 30–40% had not returned to work, and a further 27–35% went back only with changes to their workplace (the authors rate the quality of the work data as poor). Pain specialists describe delayed diagnosis and delayed mobilization as strong predictors of a poor outcome: weeks lost to casting a painful limb or to opioid-only management add up to months of rehabilitation later.
Early Mobilization — First-Line Treatment
The core of CRPS rehabilitation, as therapists describe it, is moving the limb, gently, early, and daily, even when it hurts. Immobilization, guarding, and "resting until the pain settles" are described as making CRPS worse. Movement — graded, paced, guided by a physical or occupational therapist familiar with CRPS — is described as what retrains the nervous system.
Early-stage programs typically include:
- Desensitization: systematic exposure to textures (silk, cotton, terrycloth, corduroy) for a few minutes several times a day, starting with whatever the skin tolerates and progressing over weeks.
- Active range-of-motion within the pain-tolerable range, every day, multiple times a day. Passive stretching by a therapist is kept minimal early on — patient-driven movement teaches the brain that the limb is safe to use.
- Weight-bearing (for leg CRPS) in a graded way: standing, then stepping, then walking, with a walker or crutch if needed. Staying non–weight-bearing past the orthopedic healing point is described as harmful.
- Edema management with elevation, compression garments, and contrast baths (alternating warm and cool water).
- Pacing — doing a little, consistently, rather than pushing through a 30-minute session and crashing for three days.
If the pain is severe enough that no movement is possible at all, the first job of medical treatment (nerve blocks, ketamine, medications) is to open a window so physical therapy can happen. In this approach the drugs and procedures do not cure CRPS: movement, repeated many thousands of times, is what drives recovery, and the drugs make the movement possible.
Graded Motor Imagery and Mirror Therapy
Graded Motor Imagery (GMI) is a three-stage cognitive rehabilitation program developed specifically for CRPS and phantom limb pain. Randomized controlled trials by Moseley and colleagues show clinically meaningful reductions in pain and disability. The three stages:
- Left/right discrimination. The patient looks at photographs of hands or feet and decides, as quickly as possible, whether each image shows a left or a right. In CRPS, this ability is measurably slower on the affected side. Practicing reboots the brain's internal model of the limb.
- Motor imagery. The patient imagines performing movements with the affected limb — without actually moving it. Imagined movement activates the same motor cortex regions as real movement, without provoking peripheral pain.
- Mirror therapy. The patient places a mirror vertically along the body's midline, reflecting the unaffected limb so that it appears to be in the position of the affected limb. Watching the reflection move convinces the brain that the painful limb is moving normally — and cortical pain signaling often drops within minutes.
GMI costs almost nothing, has no side effects, and can be done at home. A left/right limb-recognition app is widely used for the left/right discrimination stage. A cheap flat mirror works for stage three. Patients typically spend 10–15 minutes at each session, several times a day, progressing through the stages over weeks to months. Some therapists are trained in GMI; where none is available, the protocol is described in the published literature.
Medications Used for CRPS
No drug is specifically U.S. Food and Drug Administration-approved for CRPS. The evidence base is built on small trials, case series, and extrapolation from other neuropathic pain syndromes. Medicines commonly used first:
- Gabapentin (typically titrated to 1800–3600 mg/day in divided doses) or pregabalin (150–600 mg/day). Dampens central sensitization. See the gabapentinoid article.
- Amitriptyline (10–75 mg at bedtime) or duloxetine (30–60 mg/day). Tricyclics and serotonin-norepinephrine reuptake inhibitors (SNRIs) have the best neuropathic-pain evidence overall.
- Low-dose naltrexone (1.5–4.5 mg at bedtime) for the glial-modulation and nociplastic component. Case series only, but cheap and benign.
- Topical lidocaine 5% patches or capsaicin 8% patches for focal allodynia.
- Some clinicians use a prednisone taper in the first weeks (for example, 30 mg/day tapering over 2–4 weeks) with the aim of reducing the early neurogenic-inflammatory component in warm CRPS.
Pain specialists generally regard opioids as a poor long-term treatment for CRPS. They do not reverse central sensitization, they are described as blunting motivation for rehabilitation, and they can worsen the syndrome through opioid-induced hyperalgesia. Short courses around surgery or during severe flares are the usual exception in that view; months-long daily opioid use is not. See the opioid article for more detail.
Bisphosphonates (Pamidronate, Neridronate)
Bisphosphonates — drugs normally used for osteoporosis — have the strongest randomized evidence of any medication for early CRPS. The landmark trial, published by Varenna and colleagues in 2013, gave neridronate 100 mg intravenous (IV) on days 1, 4, 7, and 10 (four infusions over 10 days) or placebo to 82 patients with early (acute) CRPS type I of the hand or foot. Pain scores fell by 46.5 mm with neridronate versus 22.6 mm with placebo on a visual analogue scale (P<0.0001). When the placebo group was later given neridronate, they improved in the same way, and a year later none of the patients reported CRPS symptoms.
Neridronate is not available in the United States but is used routinely for CRPS in Italy and parts of Europe. The closest U.S. equivalent is intravenous pamidronate (typical regimens: 60 mg intravenous over 2–4 hours, with a second dose often given at 4–8 weeks) or oral alendronate (40 mg/day for 8 weeks in one small trial). Side effects include an acute-phase reaction (fever, flu-like symptoms, bone pain) in the first 48 hours after infusion, occasional eye inflammation, and, rarely with extended use, osteonecrosis of the jaw and atypical femoral fractures.
Practical points. Bisphosphonates work best when started within the first year of symptoms — they mainly affect the warm, bone-edema-predominant phase. A dental exam before treatment is standard practice, and calcium and vitamin D levels are usually checked and corrected first. Insurance coverage for bisphosphonates in CRPS is off-label in the U.S.; documentation of a Budapest-criteria diagnosis and of failed first-line therapy helps with prior authorization.
Ketamine Infusions
Ketamine is a N-methyl-D-aspartate receptor antagonist that, at sub-anesthetic doses, can interrupt central sensitization. Two delivery models exist:
- Outpatient low-dose infusions: 0.25–0.5 mg/kg/hour for 4 hours a day, repeated for 5–10 consecutive weekdays. This is the most common U.S. protocol. Roughly half of CRPS patients report meaningful pain reduction; the effect typically lasts weeks to a few months before boosters are needed.
- Inpatient high-dose / coma-dose protocols (Germany, Mexico): continuous infusion at anesthetic doses for several days. Dramatic responses have been reported, but serious risks — hepatotoxicity, dissociative and psychiatric effects, infection — make this a last-resort option. U.S. insurers do not cover it.
Side effects at the low-dose outpatient level are usually manageable: dissociation and "K-hole" sensations during infusion, nausea, transient blood-pressure elevation. A trained anesthesiologist or pain physician monitors vital signs and offers a benzodiazepine if dysphoria becomes intolerable. Cost in the U.S. typically runs $500–$1,500 per infusion and is poorly covered by insurance; patients describe asking the clinic for a superbill (an itemized receipt) and filing an insurance appeal. Response is most likely in patients with strong central-sensitization features (widespread allodynia, hyperalgesia, bilateral spread).
Sympathetic Nerve Blocks
The sympathetic nervous system is entangled with CRPS — the older name "reflex sympathetic dystrophy" reflects the hypothesis that sympathetic efferents drive the pain. The hypothesis turned out to be partly right: some patients have sympathetically maintained pain, where blocking the sympathetic chain dramatically relieves symptoms; others have sympathetically independent pain, where blocks do nothing. There is no reliable way to predict in advance which type a patient has — the answer comes only from trying a block.
- Stellate ganglion block (upper limb CRPS): local anesthetic injected around the stellate ganglion at C6–C7. Done under fluoroscopy or ultrasound. If the first block produces clear pain relief and the characteristic Horner's sign (drooping eyelid, small pupil), a series of 3–6 blocks over several weeks is commonly pursued.
- Lumbar sympathetic block (lower limb CRPS): local anesthetic injected around the L2–L4 sympathetic chain. Same principle, same decision algorithm.
Blocks are low-risk, outpatient, and diagnostic as well as therapeutic — a positive response signals a treatable sympathetic component. Blocks are not a long-term monotherapy. They work best as a window that lets the patient participate in aggressive physical therapy for the days or weeks after each injection. If the first two well-placed blocks do nothing, further blocks are unlikely to help, and the pain is sympathetically independent. See the interventional pain article for the broader landscape.
Spinal Cord and Dorsal Root Ganglion Stimulation
For CRPS that persists despite conservative and medical treatment, neuromodulation is one of the better-evidenced options in chronic pain medicine.
Spinal cord stimulation (SCS) places electrodes in the epidural space over the dorsal columns, connected to an implanted pulse generator. The device delivers electrical pulses that modulate pain signaling. Older "tonic" SCS created a tingling (paresthesia) over the painful area; newer "high-frequency" (10 kHz) and "burst" modes provide relief without paresthesia. The landmark randomized controlled trial (RCT) by Kemler et al. in NEJM 2000 found pain relief for CRPS patients who had failed conservative care. The same trial's five-year follow-up (2008; 36 patients given stimulation plus physical therapy, 18 physical therapy alone) found that the advantage faded: at 5 years, stimulation plus physical therapy gave results similar to physical therapy alone for pain relief and every other measure. Even so, 95% of the patients with an implant said they would repeat the treatment for the same result.
Dorsal root ganglion (DRG) stimulation targets the sensory cell bodies in the DRG rather than the dorsal columns. The ACCURATE trial showed DRG stimulation superior to conventional SCS for CRPS of the lower limb, particularly for focal pain in the foot. For upper-limb CRPS, both are used.
Both are done in two stages: a 5–7 day trial with percutaneous leads and an external generator, followed by permanent implantation only if the trial produces at least 50% pain relief. Complications include lead migration, infection (roughly 2–5%), and, rarely, neurological injury. Insurance coverage in the U.S. is generally good once conservative care has been documented to fail. Average total cost (trial plus implant) runs $40,000–$80,000 and is typically covered by commercial plans and Medicare.
Refractory CRPS — When Nothing Works
Roughly one in ten CRPS patients progresses to severe, treatment-resistant disease with dystonia, contracture, or spread to other limbs. Options at this point are limited and experimental, and are mostly offered at dedicated CRPS centers:
- Intrathecal drug delivery (baclofen for dystonia; ziconotide or opioid for pain).
- IVIG — two small trials suggested low-dose IVIG might improve symptoms, but the largest trial (LIPS, 2017; 111 people in the United Kingdom with moderate or severe CRPS for 1–5 years) found that low-dose IVIG (0.5 g/kg on days 1 and 22) did not lower pain more than placebo over 6 weeks: average pain was 7.2 out of 10 with IVIG and 6.9 with placebo. The results do not apply to full-dose treatment (for example 2 g/kg) or to people who have had CRPS for under 1 year or over 5 years.
- Plasmapheresis — case series only.
- Scrambler therapy — a scrambler therapy device is a surface electrical stimulator that provides non-pain signals to the affected dermatomes. Mixed evidence; low risk.
- Intensive multidisciplinary inpatient rehabilitation — 3–4 weeks of combined physical therapy, occupational therapy, psychology, and medication management. Practitioners describe it as the most effective option for severe long-duration CRPS; it is also the hardest to get insurance to cover.
- Amputation — historically a dead end (pain recurs in the stump or phantom limb in the majority). Considered only for non-functional, infected, or contracted limbs and with realistic expectations.
Psychological care is part of standard treatment at this stage — not because CRPS is psychological, but because living with severe refractory pain erodes mood, sleep, and relationships, and treating those makes the pain more tolerable. Cognitive behavioral therapy, acceptance and commitment therapy, and pain reprocessing therapy all have roles.
Vitamin C Prophylaxis for Distal Radius Fracture
This is the main prevention evidence in CRPS, and it is not settled. In 1999, Zollinger and colleagues published a randomized controlled trial in The Lancet in which people with a wrist fracture took 500 mg of vitamin C daily for 50 days or placebo: CRPS developed in 7% of wrists (4 of 54) with vitamin C and 22% (14 of 65) with placebo. A larger follow-up trial in 2007 (416 patients) found CRPS in 2.4% of all the vitamin C groups combined versus 10.1% with placebo; by dose it was 4.2% at 200 mg, 1.8% at 500 mg and 1.7% at 1,500 mg a day, so the higher dose added no further benefit. All the affected patients in that trial were older women.
The American Academy of Orthopaedic Surgeons' 2010 guideline on distal radius fractures gave a moderate-strength recommendation for vitamin C to prevent disproportionate pain. Surveys later found that 11% of hand surgeons (2013) and 20% of orthopedic trauma surgeons (2018) routinely prescribed it. Vitamin C is cheap (a bottle of 500 mg tablets costs a few dollars), well tolerated, and has almost no downside other than occasional loose stools or the theoretical concern about kidney stones in stone-formers.
What is not settled. A 2014 double-blind trial of 336 adults with a distal radius fracture, given 500 mg of vitamin C or placebo daily for 50 days, found no difference at one year in function, the rate of CRPS or bone healing. Meta-analyses disagree: a 2022 analysis of 8 studies found fewer CRPS cases with vitamin C after wrist, foot and ankle surgery (odds ratio 0.33), while a 2024 analysis of 8 studies found a favourable effect whose pooled result was not statistically significant, and detected publication bias.
The evidence for vitamin C prophylaxis in other fractures (ankle, hip, foot) is less consistent, but the intervention is cheap enough that some orthopedists prescribe it after any significant extremity fracture. For people having limb surgery who have a CRPS history — or a family member with CRPS — the measures discussed in this setting are vitamin C, regional anesthesia instead of general, and shorter rather than longer immobilization.
Living With CRPS
A few things patients consistently report helping, beyond the formal medical pathway:
- Sleep first. Poor sleep amplifies central sensitization more reliably than almost any other variable. See sleep, exercise and lifestyle.
- Clothing and bedding. Soft, seamless fabrics. A bed cradle to keep blankets off a hypersensitive foot. A silk glove sleeve for the hand.
- Heat and cold strategically. Many patients find warmth helps cold CRPS and cool compresses help warm CRPS, and describe testing each in a small way first.
- A pacing diary. Patients log activity and pain for two weeks to find the level of movement that does not trigger a two-day flare, use that as their baseline, and increase it by about 10% every one to two weeks.
- Community. The Reflex Sympathetic Dystrophy Syndrome Association (RSDSA, a patient charity) and online CRPS patient communities are used by patients to find CRPS-literate physicians and physical therapists in their area.
- Disability and insurance planning. CRPS is recognized by the Social Security Administration (SSR 03-2p). People whose work is limited by the syndrome describe early documentation as important — including photographs of color and swelling changes, physical therapy notes showing objective progress or plateaus, and a rheumatology or pain-medicine provider willing to write a detailed functional statement.
Key Research Papers
- Harden RN, et al. Proposed new diagnostic criteria for complex regional pain syndrome. Pain Med. 2007. PubMed PMID: 17610454 (The Budapest Criteria.)
- Harden NR, et al. Validation of proposed diagnostic criteria (the "Budapest Criteria") for Complex Regional Pain Syndrome. Pain. 2010. PubMed PMID: 20493633
- Goebel A, et al. The Valencia consensus-based adaptation of the IASP complex regional pain syndrome diagnostic criteria. Pain. 2021. PubMed PMID: 33729210
- Ferraro MC, et al. Complex regional pain syndrome: advances in epidemiology, pathophysiology, diagnosis, and treatment. Lancet Neurol. 2024. PubMed PMID: 38631768
- Johnson S, et al. Complex regional pain syndrome what is the outcome? - a systematic review of the course and impact of CRPS at 12 months from symptom onset and beyond. Eur J Pain. 2022. PubMed PMID: 35435302
- Varenna M, et al. Treatment of complex regional pain syndrome type I with neridronate: a randomized, double-blind, placebo-controlled study. Rheumatology. 2013. — doi:10.1093/rheumatology/kes312
- Zollinger PE, et al. Effect of vitamin C on frequency of reflex sympathetic dystrophy in wrist fractures: a randomised trial. Lancet. 1999. — doi:10.1016/S0140-6736(99)03059-7
- Zollinger PE, et al. Can vitamin C prevent complex regional pain syndrome in patients with wrist fractures? A randomized, controlled, multicenter dose-response study. J Bone Joint Surg Am. 2007. — doi:10.2106/jbjs.f.01147
- Ekrol I, et al. The influence of vitamin C on the outcome of distal radial fractures: a double-blind, randomized controlled trial. J Bone Joint Surg Am. 2014. PubMed PMID: 25187584
- Seth I, et al. Effect of Perioperative Vitamin C on the Incidence of Complex Regional Pain Syndrome: A Systematic Review and Meta-Analysis. J Foot Ankle Surg. 2022. PubMed PMID: 34961681
- Ranjbar Moghaddam M, et al. Efficacy of vitamin C supplementation in preventing and treating complex regional pain syndrome type I (CRPS-I) in Orthopedic patients: A systematic review and meta-analysis. Int J Orthop Trauma Nurs. 2024. PubMed PMID: 39447383
- Lichtman DM, et al. Treatment of distal radius fractures. J Am Acad Orthop Surg. 2010. PubMed PMID: 20190108
- Matzon JL, et al. Adherence to the AAOS upper-extremity clinical practice guidelines. Orthopedics. 2013. PubMed PMID: 24200445
- Okoroafor UC, Cannada LK. Do Orthopedic Trauma Surgeons Adhere to AAOS Guidelines when Treating Distal Radius Fractures? Iowa Orthop J. 2018. PubMed PMID: 30104925
- Kemler MA, et al. Spinal cord stimulation in patients with chronic reflex sympathetic dystrophy. N Engl J Med. 2000. — doi:10.1056/NEJM200008313430904
- Kemler MA, et al. Effect of spinal cord stimulation for chronic complex regional pain syndrome Type I: five-year final follow-up of patients in a randomized controlled trial. J Neurosurg. 2008. PubMed PMID: 18240925
- Goebel A, et al. Low-Dose Intravenous Immunoglobulin Treatment for Long-Standing Complex Regional Pain Syndrome: A Randomized Trial. Ann Intern Med. 2017. PubMed PMID: 28973211
- Deer TR, et al. Dorsal root ganglion stimulation yielded higher treatment success rate for complex regional pain syndrome and causalgia: the ACCURATE randomized comparative trial. Pain. 2017. — doi:10.1097/j.pain.0000000000000814
- Moseley GL. Graded motor imagery for pathologic pain: a randomized controlled trial. Neurology. 2006. — doi:10.1212/01.wnl.0000249112.56935.32
- Sigtermans MJ, et al. Ketamine produces effective and long-term pain relief in patients with complex regional pain syndrome type 1. Pain. 2009. — doi:10.1016/j.pain.2009.06.023
PubMed Topic Searches
For further reading, the following PubMed topic searches return current peer-reviewed work on CRPS diagnosis, pathophysiology, and management:
- PubMed: Budapest criteria and CRPS diagnosis
- PubMed: CRPS pathophysiology and mechanisms
- PubMed: Graded motor imagery and mirror therapy for CRPS
- PubMed: Bisphosphonates for CRPS (neridronate, pamidronate)
- PubMed: Ketamine infusion for CRPS
- PubMed: Sympathetic blocks (stellate, lumbar) for CRPS
- PubMed: Spinal cord and dorsal root ganglion stimulation for CRPS
- PubMed: Vitamin C prophylaxis for CRPS after wrist fracture
Connections
- Pain & Allergy
- Interventional Pain
- Complex Regional Pain Syndrome (CRPS): the short overview — a briefer introduction to the same condition, filed directly under Pain & Allergy, with sections on low-dose naltrexone and natural approaches that this deep dive does not cover.
- Fibromyalgia
- Central Sensitization and Nociplastic Pain
- Non-Opioid Medications
- Pain Reprocessing Therapy
- Sleep and Lifestyle for Chronic Pain
- Opioids for Chronic Pain
- Chronic Low Back Pain
- Vitamin C
- Chronic Pain Overview
- Pain Mechanisms
- Peripheral Neuropathy
- Arthritis
- Depression
- Chronic Fatigue Syndrome
- Low-Dose Naltrexone for Fibromyalgia
- Low Dose Naltrexone