⚠ Evidence warning: Clinical trials or other evidence do not support the claims that graded exercise has the strongest evidence base of any non-drug treatment for fibromyalgia, that moderate-intensity aerobic training improves pain, that aquatic training has lower drop-out rates than land-based training, and that passive stretching alone has shown no meaningful benefit. This page keeps it as a report of what people, websites or other media say.
Exercise Pacing and Graded Movement for Fibromyalgia
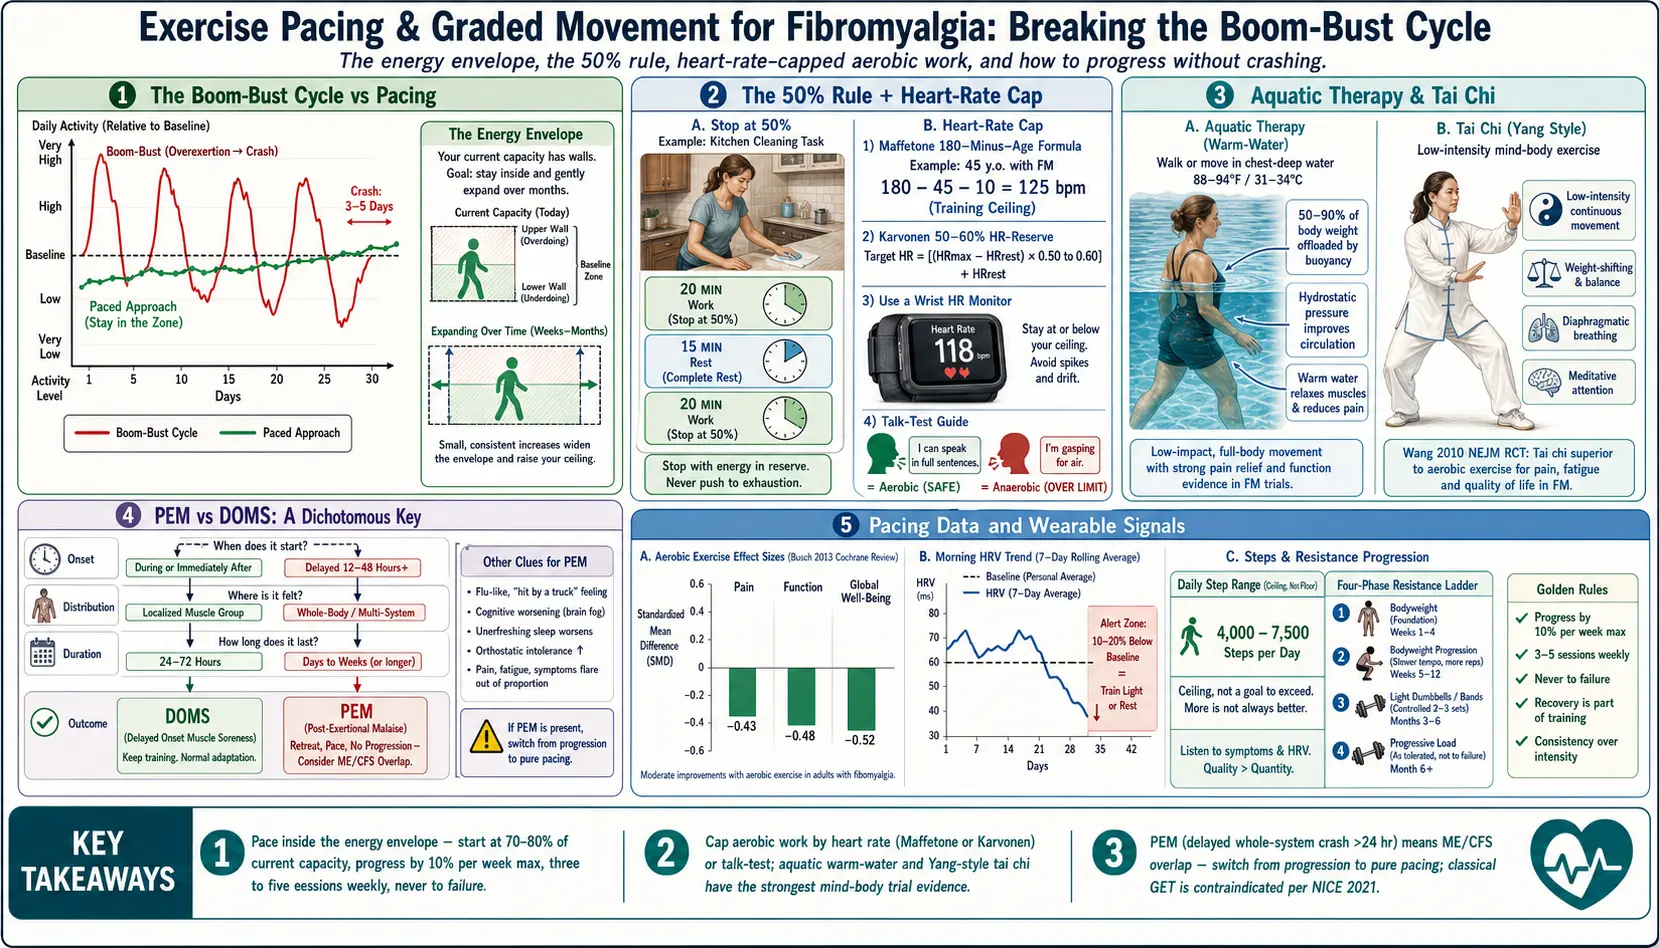
Table of Contents
- Why “Push Through the Pain” Backfires: The Boom-Bust Cycle
- The Pacing Envelope Concept
- Activity-Rest Balancing: The 50% Rule
- How Graded Exercise Therapy (GET) Is Set Up for Fibromyalgia
- How Fibromyalgia GET Differs from the Discredited PACE Protocol
- Heart-Rate-Capped Aerobic Work
- Aquatic Therapy: Warm Water Changes the Math
- Resistance Training That Starts Unloaded
- Tai Chi, Yoga, and Qigong
- Distinguishing Post-Exertional Malaise from Normal Soreness
- Using a Wearable to Track Load
- Example Weekly Templates From Pacing Programs
- Pitfalls Pacing Programs Describe
- Key Research Papers
- Connections
- Featured Videos
Why “Push Through the Pain” Backfires: The Boom-Bust Cycle
Almost everyone with fibromyalgia has lived this pattern: a good day arrives, the person feels close to normal and burns through a week’s worth of delayed chores in six hours — laundry, yard work, a long walk with a friend, maybe dinner out. The next morning they cannot get out of bed. Pain is everywhere, the fog is thick, sleep didn’t restore anything, and the crash lasts two, three, sometimes five days. By the time they recover, they are deconditioned again, and the cycle repeats.
This is the boom-bust cycle, which pacing practitioners describe as the most damaging pattern in fibromyalgia self-management. In their account every crash costs more than it gained: the total work completed over a month is lower than with even pacing, because so many days are spent below baseline recovering from the peaks. They also describe repeated crashes as sensitizing the central nervous system further — meaning pain, fatigue, and fog all get more reactive over time (see central sensitization explained).
The approach these programs describe is not doing less but doing the same or slightly more, spread evenly, every day. The jargon word for this is pacing, and it is the foundation everything else in this article sits on.
The Pacing Envelope Concept
Pacing programs picture daily capacity as a rectangle with walls a person can feel but not see. Activity inside the rectangle — the “energy envelope” costs nothing extra. Activity outside it triggers a crash 24–72 hours later. The aim of pacing, as these programs describe it, is to find where those walls are and stay comfortably inside them while slowly, deliberately pushing them outward over months.
To find the envelope, pacing programs track two numbers for two weeks:
- Morning energy rating on a 0–10 scale (0 = can’t get out of bed, 10 = best day of your life).
- Activity completed — steps walked, minutes of exercise, hours of household work, hours of focused mental work.
After two weeks, the daily activity level at which the next-morning rating stays stable or rises is taken as the top of the envelope. These programs start a training plan at 70–80% of that number rather than 100%, because training at the absolute edge is fragile — any poor night of sleep, minor illness, or life stress pushes a person over.
Activity-Rest Balancing: The 50% Rule
A practical rule used by occupational therapists who treat fibromyalgia and myalgic encephalomyelitis/chronic fatigue syndrome (ME/CFS): stopping at 50% of what a person thinks they can do, then resting, then doing the next 50% block, then resting again.
Example: cleaning the kitchen is estimated at 40 minutes of continuous work. Under the 50% rule, the person works for 20 minutes, sits down for 15, then finishes the remaining 20 minutes. Total clock time is 55 minutes instead of 40; practitioners describe the cost to the nervous system as half, and the task ends with capacity to spare, which is the whole point.
The rest intervals are not necessarily spent lying down. They are deliberate low-demand intervals — sitting with tea, listening to music, legs up against a wall, slow breathing. These practitioners exclude scrolling a phone from rest, because it keeps cognitive load high.
How Graded Exercise Therapy (GET) Is Set Up for Fibromyalgia
Graded Exercise Therapy is the gradual, measured increase of activity over weeks and months. For fibromyalgia specifically, done correctly, it has the strongest evidence base of any non-drug intervention. The 2007 Cochrane review led by Busch and colleagues (DOI 10.1002/14651858.CD003786.pub2) included 34 studies (2,276 people) of several kinds of exercise in fibromyalgia. It found moderate-quality evidence that aerobic exercise at recommended intensity improves global well-being and physical function; the effect on pain was uncertain, because its confidence range included no effect (standardized mean difference 0.94, 95% confidence interval −0.15 to 2.03). Moderate-intensity aerobic training improves pain, function, and global well-being, with effect sizes small to moderate but consistent.
Exercise also has the strongest guideline backing of any fibromyalgia treatment. The revised European League Against Rheumatism (EULAR) recommendations (Annals of the Rheumatic Diseases, 2017), written by a panel from 12 countries from 107 systematic reviews and meta-analyses, rated exercise as the only “strong for” therapy. The further options the panel listed — psychological therapies, drug treatment and multimodal rehabilitation — were all rated “weak for”, and the panel described the size of effect for most treatments as relatively modest.
The progression that pacing and graded-exercise programs describe (these rules come from practice, not from a cited trial):
- A very low start. Someone who can currently walk five minutes before a symptom flare starts at two minutes — not five, not ten.
- Increases of no more than 10% per week. Two minutes becomes 2:12 the next week, 2:25 the week after. If the next morning’s symptom rating drops, the current level is held an extra week before progressing.
- Three to five sessions per week, not daily; these programs treat recovery days as being as important as training days.
- Intensity capped at a level where a full-sentence conversation is still possible. Needing a breath mid-sentence is taken as a sign of being above threshold, with symptoms likely the next day.
- A flare is expected in the first two to six weeks. Then the body adapts, and the same workload starts feeling easier. If it has not adapted by week six, these programs take the starting dose as too high, cut it by 50% and restart.
How Fibromyalgia GET Differs from the Discredited PACE Protocol
Anyone who has read about myalgic encephalomyelitis/chronic fatigue syndrome in the last decade has seen the backlash against Graded Exercise Therapy. The UK’s 2011 PACE trial was the most influential study to promote GET and Cognitive Behavioral Therapy for myalgic encephalomyelitis/chronic fatigue syndrome. After a decade of patient advocacy and reanalysis, the trial’s protocol changes, outcome-measure switching, and modest effect sizes led the UK’s National Institute for Health and Care Excellence (UK National Institute for Health and Care Excellence, NICE) to remove GET as a recommended treatment for myalgic encephalomyelitis/chronic fatigue syndrome in 2021.
This matters because some fibromyalgia patients — particularly those with heavy post-exertional malaise — have a myalgic encephalomyelitis/chronic fatigue syndrome-dominant phenotype in which any prescribed activity escalation makes them worse permanently. For those patients, classical GET is reported to be harmful.
The key differences between fibromyalgia GET and the discredited ME/CFS PACE approach:
- Fibromyalgia GET is patient-led and symptom-contingent. Progression does not follow a fixed schedule when symptoms worsen — the level is held or reduced. PACE progressed participants on a pre-set calendar regardless of crashes.
- Fibromyalgia GET caps intensity by heart rate or talk-test, not by time-at-effort.
- For patients with clear PEM (post-exertional malaise), the protocol becomes pacing without progression. The goal shifts from improvement to stability.
A full-system crash (not soreness) lasting more than 24 hours after a gentle activity session is the pattern covered in the fibromyalgia and myalgic encephalomyelitis/chronic fatigue syndrome overlap article.
Heart-Rate-Capped Aerobic Work
Pacing programs keep exercise below the danger zone by capping heart rate. The aim is to stay aerobic — meaning the mitochondria have enough oxygen to make energy cleanly — rather than cross into anaerobic metabolism, which dumps lactate, spikes sympathetic drive, and which these programs describe as the dose most likely to trigger next-day flares.
Two formulas practitioners use:
- Maffetone 180-minus-age (conservative). 180 minus age; for people with a chronic illness or who have been sedentary, the method subtracts another 5–10. For a 45-year-old with fibromyalgia: 180 − 45 − 10 = 125 bpm ceiling, used as the upper limit for steady-state cardio.
- Karvonen heart-rate-reserve method, 50–60% zone. Target HR = resting HR + (0.50 to 0.60) × (220 − age − resting HR). For a 45-year-old with resting HR 70: target = 70 + 0.55 × (220 − 45 − 70) = 70 + 58 = 128 bpm.
Both formulas land in roughly the same window. In practice a heart-rate monitor on the wrist or chest shows when the number passes the cap, and the pace is slowed. Many people are surprised at how easy the pace is at first — a stroll, not a brisk walk; practitioners describe the adaptation as coming from consistency, not intensity.
The talk test is the backup without a monitor: the pace is set so that a full sentence can be spoken without gasping, and managing only short phrases means the intensity is above the cap.
Aquatic Therapy: Warm Water Changes the Math
Many people with fibromyalgia report that water-based exercise is the only form they can do without triggering flares. The reasons are mechanical and neurological:
- Buoyancy offloads 50–90% of body weight depending on water depth. Joint-loading pain drops to near-zero.
- Hydrostatic pressure improves circulation and reduces the orthostatic component that many fibromyalgia patients also carry.
- Warm water (88–94°F / 31–34°C) reduces muscle guarding and central pain sensitization by competing for the same sensory pathways that transmit pain.
- Resistance is proportional to effort — the faster the movement, the more resistance. Accidental overload at a slow pace is unlikely.
The 2014 Cochrane review on aquatic exercise for fibromyalgia led by Bidonde and colleagues (16 studies, 881 people) concluded that aquatic training produces improvements in pain, stiffness, and multidimensional function, with evidence quality ranging from low to moderate. Compared with no exercise, pain improved by about 7 points and stiffness by about 18 points on a 100-point scale; of the main outcomes, only stiffness and muscle strength passed the review’s 15% threshold for a clinically relevant change. Compared with land-based exercise there were no significant differences in function, pain or stiffness, except that land-based training was better for muscle strength. Withdrawals were similar in the aquatic and control groups and in the aquatic and land groups, and no serious adverse effects were reported. The effect size is similar to land-based aerobic training, but drop-out rates are lower because tolerability is higher.
Practical notes from warm-water programs: they use pools kept at 88°F or warmer and describe standard lap pools at 78–82°F as cool enough to tighten muscles. Community pools and gyms, hospital rehab pools, and arthritis-charity aquatic programs often run warm-water sessions. Beginner sessions in these programs run about 20 minutes twice a week, alternating walking in chest-deep water with gentle arm sweeps. Leg-only kickboard work is left until later, because the floating horizontal position can spike neck and shoulder tension.
Resistance Training That Starts Unloaded
Muscle mass matters for fibromyalgia outcomes. Stronger muscles are less reactive to the same load, sleep quality tends to improve, and metabolic health — glucose regulation, bone density, mitochondrial function — all respond to resistance training in ways aerobic work alone cannot match. Fibromyalgia exercise practitioners describe the standard gym approach (“start with the bar, add weight each session”) as too aggressive.
A progression these practitioners use for fibromyalgia:
- Phase 1 — Bodyweight or less, weeks 1–4. Wall push-ups, sit-to-stand from a chair, supine hip bridges, standing heel raises. Five to eight reps per set. One set per exercise. Twice per week.
- Phase 2 — Full bodyweight, weeks 5–10. Push-ups on knees, bodyweight squats to a chair, glute bridges with a pause, assisted lunges holding a counter. Two sets. Still twice per week.
- Phase 3 — Light external load, month 3 onward. Dumbbells in the 2–8 lb range, resistance bands, suspension trainers. Two to three sets of 8–12 reps.
- Phase 4 — Progressive loading, month 6+. Begun only after the prior phases have been symptom-stable for at least four weeks.
Two rules in these programs override everything else. First, each set ends two reps before failure; practitioners describe training to failure as spiking post-exertional symptoms out of proportion to the benefit. Second, load and volume are not raised in the same week: when the weight on squats goes up, no set is added. One variable changes, the body is given two weeks to adapt, then the next one changes.
Tai Chi, Yoga, and Qigong
The strongest single trial of non-aerobic movement for fibromyalgia was Wang and colleagues’ 2010 randomized controlled trial in the New England Journal of Medicine (DOI 10.1056/NEJMoa0912611). Sixty-six patients were randomized to twice-weekly Yang-style tai chi for 12 weeks versus a wellness-and-stretching control. The tai chi group improved significantly on the Fibromyalgia Impact Questionnaire, sleep, and depression scores, with benefits sustained at 24 weeks. On the questionnaire (0 to 100, higher is worse), scores fell from 62.9 to 35.1 in the tai chi group and from 68.0 to 58.6 in the control group — a difference of 18.4 points. A 2018 follow-up trial by the same group (BMJ 2018, DOI 10.1136/bmj.k851) in 226 adults followed for 52 weeks showed tai chi was at least as effective as aerobic exercise: the combined tai chi groups improved more than the aerobic exercise group on the revised questionnaire at 24 weeks (a difference of 5.5 points, 95% confidence interval 0.6 to 10.4), and 24 weeks of tai chi did better than 12 weeks.
Researchers and teachers explain tai chi’s effect in fibromyalgia by several active ingredients that are individually helpful and synergistic:
- Low-intensity continuous movement (aerobic exposure below any flare threshold).
- Weight-shifting balance training (proprioceptive recalibration for a sensitized nervous system).
- Diaphragmatic breathing (parasympathetic activation, vagal tone improvement).
- Meditative attention (reduces catastrophizing, a known amplifier of central pain).
- Social and teacher-led structure (improves adherence, a bigger driver of benefit than the movement itself in many trials).
Yoga — particularly gentle, restorative, or Iyengar styles with heavy prop use — has a smaller but positive evidence base. Practitioners describe hot yoga as pushing many fibromyalgia patients into crash territory (the heat plus the intensity), and vinyasa-style flows as hard to tolerate when sleep is already non-restorative. Qigong is essentially tai chi stripped of the martial forms and focused on breath-led movement; the trial data is smaller but directionally similar.
Distinguishing Post-Exertional Malaise from Normal Soreness
Pacing programs call this the most important diagnostic skill a person with fibromyalgia can develop. The two phenomena look similar at first — both involve “feeling bad after exercise” but they respond to opposite strategies.
Normal post-exercise soreness (DOMS):
- Localized to the muscles that were worked.
- Peaks 24–48 hours after the session and resolves by 72 hours.
- Feels mechanical — tender-to-press, sore on stretch, better with gentle movement.
- Mental clarity, sleep, and appetite are unchanged.
- Usual response in pacing programs: training continues, with fluids and perhaps a lighter session.
Post-exertional malaise (PEM):
- Whole-system crash — muscle, joint, cognitive fog, orthostatic intolerance, sleep disruption, sometimes sore throat or swollen lymph nodes.
- Typically delayed 12–48 hours, lasts 2–7 days or longer.
- Disproportionate to the trigger (“I only walked to the mailbox”).
- Rest does not quickly resolve it the way it resolves soreness.
- Usual response in pacing programs: activity drops back from the level that triggered it, pacing stays more conservative for weeks, and progression waits until symptoms are fully stable.
Consistent PEM after sessions a protocol considers “gentle” points to a myalgic encephalomyelitis/chronic fatigue syndrome-dominant phenotype. Classical GET is the approach NICE removed for that condition in 2021 (see above); pacing programs use pure pacing without progression — plus treatment of any co-occurring orthostatic intolerance, dysautonomia, or sleep disorder — as the first step. See the myalgic encephalomyelitis/chronic fatigue syndrome overlap article.
Using a Wearable to Track Load
Consumer wearables have quietly become one of the most useful tools in fibromyalgia self-management. The key metrics:
- Heart-rate variability (HRV). Pacing practitioners treat a morning HRV reading 10–20% below a person’s own baseline as the best objective signal of under-recovery, and the day’s training is made lighter or replaced by rest. The recovery and readiness scores on wearable heart-rate and activity trackers all derive from the same underlying autonomic signal.
- Resting heart rate trend. A resting HR 7–10 bpm above a person’s own baseline for two days in a row is used as a flare-warning signal, and activity is reduced.
- Sleep staging. Consumer estimates of deep and REM sleep are approximate, but trends over weeks are useful. Non-restorative sleep is a fibromyalgia hallmark — see the sleep article.
- Daily step count. Used as a ceiling, not a floor. Pacing practitioners describe 4,000–7,500 steps as a sustainable daily range for many fibromyalgia patients, and chasing 10,000 as a boom-bust trap.
Which device is used matters less than wearing it consistently for at least six weeks to establish personal baselines; the absolute number on any given day says little, and the deviation from baseline is the signal these programs act on.
Example Weekly Templates From Pacing Programs
Two example weeks of the kind pacing programs use for different starting points; these programs shorten the durations freely when they still feel like too much.
Template A — Mild-to-moderate fibromyalgia, can tolerate a 15-minute walk without next-day flare:
- Monday: 20 minutes walking, heart-rate capped. Five minutes of gentle stretching.
- Tuesday: Phase-appropriate resistance circuit, 20–25 minutes total including rests.
- Wednesday: Rest or 15 minutes of tai chi / restorative yoga.
- Thursday: 20–25 minutes warm-water walking or aquatic class.
- Friday: Resistance circuit repeat.
- Saturday: 25-minute walk OR tai chi class. Not both.
- Sunday: Full rest. Gentle stretching only.
Template B — Severe fibromyalgia or PEM-dominant phenotype:
- Monday: 5 minutes seated leg raises + ankle circles. 5 minutes diaphragmatic breathing.
- Tuesday: Rest.
- Wednesday: 10 minutes warm-water walking in chest-deep pool, slow pace, no arm work.
- Thursday: Rest.
- Friday: 5–7 minutes supine mobility work — hip bridges, knee-to-chest, cat-cow on hands and knees if tolerated.
- Saturday: Rest.
- Sunday: 10 minutes tai chi video, seated modifications.
In these programs Template B is held for at least four weeks before any increase is considered, and progression starts only when morning symptom ratings are stable or rising for 14 consecutive days.
Pitfalls Pacing Programs Describe
- Progressing by feel on good days. Pacing programs treat a good day as no reason to jump two phases; the plan made on an average day stays in place.
- Skipping rest weeks. Every four to six weeks, these programs hold volume and intensity flat for seven days — not absolute rest, just no progression — to consolidate adaptation.
- Treating stretching as exercise. Stretching feels good, but a 2019 Cochrane review of 12 trials (743 people) found that, compared with aerobic training, it is uncertain whether flexibility exercise improves quality of life, pain, fatigue, stiffness or physical function, because the certainty of the evidence is very low. Passive stretching alone has not shown meaningful benefit in fibromyalgia trials. Pacing programs treat it as an adjunct, not a substitute for aerobic + resistance + mind-body work.
- Chasing morning workouts when sleep is broken. With non-restorative sleep, practitioners describe the first two hours after waking as often the worst window for training, and mid-morning or early afternoon as tending to work better.
- Ignoring stress load. Pacing programs describe a hard week at work, a family conflict, or grief as drawing from the same envelope as physical activity, and scale back the training plan during life stress — see the stress management article.
Key Research Papers
- Busch AJ, Barber KA, Overend TJ, Peloso PM, Schachter CL. Exercise for treating fibromyalgia syndrome. Cochrane Database of Systematic Reviews. 2007;(4):CD003786. — PubMed PMID: 17943797
- Wang C, Schmid CH, Rones R, Kalish R, Yinh J, Goldenberg DL, Lee Y, McAlindon T. A randomized trial of tai chi for fibromyalgia. N Engl J Med. 2010;363(8):743–754. — PubMed PMID: 20818876
- Bidonde J, Busch AJ, Webber SC, Schachter CL, Danyliw A, Overend TJ, Richards RS, Rader T. Aquatic exercise training for fibromyalgia. Cochrane Database of Systematic Reviews. 2014;(10):CD011336. — PubMed PMID: 25350761
- Wang C, Schmid CH, Fielding RA, Harvey WF, Reid KF, Price LL, Driban JB, Kalish R, Rones R, McAlindon T. Effect of tai chi versus aerobic exercise for fibromyalgia: comparative effectiveness randomized controlled trial. BMJ. 2018;360:k851. — PubMed PMID: 29563100
- Bidonde J, et al. Aerobic exercise training for adults with fibromyalgia. Cochrane Database of Systematic Reviews. 2017. — doi:10.1002/14651858.cd012700
- Macfarlane GJ, Kronisch C, Dean LE, Atzeni F, Häuser W, Fluß E, Choy E, Kosek E, Amris K, Branco J, Dincer F, Leino-Arjas P, Longley K, McCarthy GM, Makri S, Perrot S, Sarzi-Puttini P, Taylor A, Jones GT. EULAR revised recommendations for the management of fibromyalgia. Ann Rheum Dis. 2017;76(2):318–328. — PubMed PMID: 27377815
- Kim SY, Busch AJ, Overend TJ, Schachter CL, van der Spuy I, Boden C, Góes SM, Foulds HJ, Bidonde J. Flexibility exercise training for adults with fibromyalgia. Cochrane Database of Systematic Reviews. 2019;9(9):CD013419. — PubMed PMID: 31476271
PubMed Topic Searches
For further reading, the following PubMed topic searches return current peer-reviewed work on exercise, pacing, and movement therapies in fibromyalgia:
- PubMed: Fibromyalgia and graded exercise therapy
- PubMed: Fibromyalgia pacing and the energy envelope
- PubMed: Fibromyalgia and aquatic exercise
- PubMed: Fibromyalgia and resistance training
- PubMed: Fibromyalgia and tai chi
- PubMed: Fibromyalgia and yoga
- PubMed: Post-exertional malaise in fibromyalgia
- PubMed: Heart-rate variability in fibromyalgia
- PubMed: The PACE trial and ME/CFS graded exercise controversy
Connections
- Orthopedics
- Fibromyalgia and Myalgic Encephalomyelitis/Chronic Fatigue Syndrome Overlap
- Central Sensitization Explained
- Stress Management
- Sleep and Non-Restorative Sleep
- Fibromyalgia Overview
- Arthritis
- Low-Dose Naltrexone for Fibromyalgia
- Nutrient Gaps in Fibromyalgia
- ACR 2016 Diagnostic Criteria
- Small-Fiber Neuropathy Overlap
- Postural Orthostatic Tachycardia Syndrome Compression and Exercise Program
- Chronic Pain
- Chronic Fatigue Syndrome
- Ankylosing Spondylitis
- Postural Orthostatic Tachycardia Syndrome
- Mast Cell Activation Syndrome
- Low-Dose Naltrexone
- Exercise and PT Protocol