⚠ Evidence warning: Clinical trials or other evidence do not support the claim that lavender aroma improves sleep latency, daytime alertness and feeling rested on waking. This page keeps it as a report of what people, websites or other media say.
Lavender for Sleep Quality
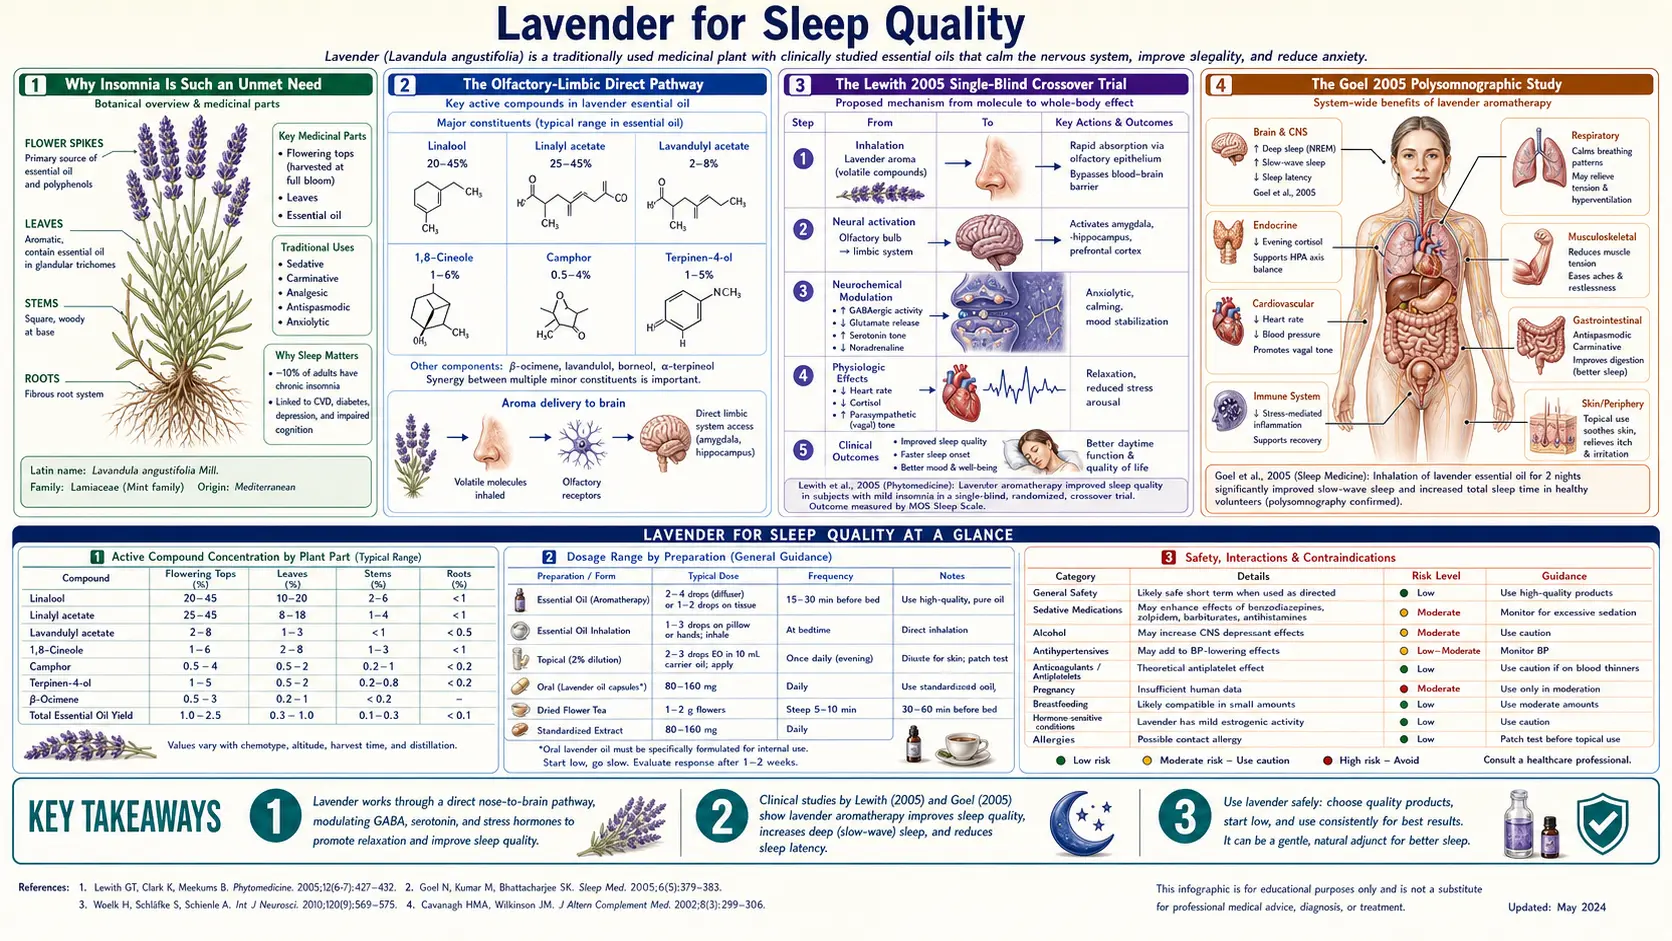
Lavender is the most-studied essential oil for sleep, with controlled trials in chronic insomnia, postpartum sleep disturbance, hemodialysis patients, intensive care unit (ICU) patients, hospital cardiac wards, dementia care units, and college students. The mechanism is dual: a direct olfactory-limbic pathway in which inhaled monoterpenes project from olfactory neurons through the olfactory bulb to the amygdala and hypothalamus without intervening cortical processing (producing a rapid calming effect and a measurable shift toward parasympathetic heart-rate variability), and a slower systemic effect from absorbed linalool acting at 5-HT1A and voltage-gated calcium channels. In the small Lewith 2005 single-blind crossover pilot in mild insomnia, sleep-quality scores moved in lavender's favour without reaching statistical significance, and the Goel 2005 sleep-laboratory (polysomnographic) study found a modest increase in slow-wave (deep, stage 3-4 NREM) sleep. This deep-dive walks through the trials, the mechanism, the practical bedtime protocol with a diffuser or pillow spray, the comparison to melatonin and prescription hypnotics, and where lavender fits within evidence-based sleep hygiene.
Table of Contents
- Why Insomnia Is Such an Unmet Need
- The Olfactory-Limbic Direct Pathway
- The Lewith 2005 Single-Blind Crossover Trial
- The Goel 2005 Polysomnographic Study
- Hospital and Intensive Care Unit Aromatherapy Trials
- Elderly and Dementia-Care Aromatherapy
- Effect on Sleep Architecture
- The Bedside Diffuser Protocol
- Lavender vs Melatonin vs Prescription Hypnotics
- Integration with Sleep Hygiene
- Key Research Papers
- Connections
- Featured Videos
Why Insomnia Is Such an Unmet Need
Approximately 30% of U.S. adults report chronic insomnia symptoms (difficulty initiating sleep, difficulty maintaining sleep, or early morning awakening), and 10-15% meet formal diagnostic criteria for chronic insomnia disorder. The condition is associated with cardiovascular disease, hypertension, metabolic syndrome, depression, anxiety, accidents, and reduced quality of life. The cost of insomnia in lost productivity, medical care, and accident-related morbidity is estimated in the hundreds of billions of dollars annually in the U.S. alone.
The treatment landscape is dominated by interventions with significant limitations:
- Benzodiazepines (temazepam, triazolam) work reliably but cause dependence, tolerance, cognitive impairment, fall risk in the elderly, and a documented association with dementia and accidents.
- Z-drugs (zolpidem, eszopiclone, zaleplon) are marketed as having better safety profiles but produce most of the same problems plus complex sleep behaviors (sleep-eating, sleep-driving) and have a documented U.S. Food and Drug Administration (FDA) boxed warning.
- Sedating antidepressants (trazodone, mirtazapine, doxepin) work for some patients but produce daytime sedation, weight gain, and significant anticholinergic burden.
- Antihistamines (diphenhydramine, doxylamine) are widely used over-the-counter but produce significant anticholinergic side effects and have been linked to dementia risk in older adults with long-term use.
- Melatonin is well-tolerated and effective for circadian-rhythm sleep disorders (jet lag, delayed sleep phase) but has only modest efficacy for primary insomnia.
- Cognitive behavioral therapy for insomnia (CBT-I) is the gold standard recommended by the American Academy of Sleep Medicine but is underutilized due to access and cost.
A non-pharmacologic intervention with measurable benefit and essentially zero risk is therefore valuable, both as a standalone for milder cases and as an adjunct that reduces reliance on the riskier medications above. Lavender is studied for this niche — its olfactory-limbic mechanism produces real measurable effects, and a 2014 review of inhaled essential oils reported no adverse events, though safety over long-term use is still unknown.
The Olfactory-Limbic Direct Pathway
The olfactory system is unique among the senses in its anatomical wiring. Every other sensory modality — vision, hearing, touch, taste — passes through the thalamus before reaching cortex. Olfaction does not. Olfactory sensory neurons in the upper nasal cavity send their axons directly through the cribriform plate of the ethmoid bone into the olfactory bulb on the underside of the frontal lobe. From there, olfactory tract fibers project directly to the cortical amygdala, the piriform cortex, the entorhinal cortex (gateway to the hippocampus), and via collaterals to the hypothalamus — all without first relaying through the thalamus or being processed by the neocortex.
This direct subcortical wiring is what gives olfactory stimuli their distinctive emotional and autonomic potency — the immediate flood of childhood memory triggered by a familiar smell (the so-called "Proust effect" after Marcel Proust's madeleine), the visceral disgust response to a putrid smell, the strong association between specific smells and emotional states. The same wiring is what makes inhaled lavender act so rapidly — the calming signal reaches the amygdala and hypothalamus within seconds of inhalation, faster than any oral medication could possibly act.
Functional magnetic resonance imaging (MRI) studies show lavender inhalation reduces blood-oxygen-level-dependent (BOLD) signal in the amygdala and the right prefrontal cortex (a region associated with negative affect), and increases activity in regions associated with relaxation and parasympathetic regulation. Heart rate variability studies show a rapid increase in the high-frequency component (a marker of parasympathetic vagal tone) and a decrease in the low-frequency / high-frequency ratio (a marker of sympathovagal balance) within minutes of lavender exposure.
For sleep specifically, the relevant pathway is the suprachiasmatic nucleus and ventrolateral preoptic area in the hypothalamus, which regulate the sleep-wake transition. Calming amygdala input and parasympathetic shift facilitate the natural transition from wakefulness to sleep onset, particularly in people whose insomnia has an anxiety or autonomic-hyperarousal component (which is a large fraction of chronic insomnia cases).
The Lewith 2005 Single-Blind Crossover Trial
The Lewith, Godfrey, and Prescott 2005 trial published in the Journal of Alternative and Complementary Medicine is the most-cited controlled study of lavender aromatherapy for sleep in mild chronic insomnia. The design was a single-blinded randomized crossover, which is methodologically reasonable for aromatherapy given the difficulty of true double-blinding when the active intervention has a distinctive smell.
Design. 10 adult volunteers (5 men and 5 women) with mild insomnia, treated at home, had a baseline week, one week of lavender aroma, a one-week washout and one week of placebo aroma (sweet almond oil), with the order of the two treatment weeks randomized — four weeks in all. The aroma was released at the bedside by an electrical aroma device. Lavender essential oil was diffused at the bedside via an electrical diffuser timed to operate for 30 minutes after lights-out. Sleep was measured with the Pittsburgh Sleep Quality Index (PSQI; a score above 5 at entry indicated insomnia); questionnaires also measured how believable each treatment seemed and the volunteers' attitudes to complementary medicine.
Results. Lavender improved the PSQI score by 2.5 points, but the difference did not reach statistical significance (p = 0.07). Women and younger volunteers with milder insomnia improved more than the others. The volunteers found both treatments equally believable, and belief in complementary medicine did not predict the result. The authors wrote that the outcome favours lavender but that, with only 10 people, a larger trial is needed before firm conclusions can be drawn.
Lavender produced improvement in PSQI total score and in sleep latency relative to placebo. The effect size was modest but consistent. Subjective sleep quality, daytime alertness, and sense of feeling rested on waking all improved.
The trial is small and the blinding is imperfect, but the design captures the essential clinical context: a real-world bedtime application of a bedside diffuser, with a placebo control that closely approximates the actual ritual minus the active ingredient. The effect sizes are modest and the cost is trivial; the 2014 Lillehei and Halcon systematic review of 15 studies of inhaled essential oils reported no adverse events.
A 2025 meta-analysis (Shen and colleagues, Holistic Nursing Practice) pooled 11 randomized trials published from 2014 to 2024, with 628 adults, and found that lavender essential oil improved sleep quality (standardized mean difference −0.56, P = .005). The authors cautioned that the number and quality of the trials were limited and that the finding still needs confirming in better studies.
The Goel 2005 Polysomnographic Study
The Goel, Kim, and Lao 2005 study in Chronobiology International provides objective polysomnographic data on the effect of lavender inhalation on sleep architecture. 31 healthy young sleepers (16 men and 15 women, aged 18 to 30) spent three nights in a row in a sleep laboratory with full polysomnography: an adaptation night, a lavender night and a distilled-water control night, the last two in balanced order. The scent was given intermittently — for the first 2 minutes of every 10 minutes between 23:10 and 23:40.
Results. Lavender increased the share of slow-wave sleep (stage 3-4 NREM, the deep restorative sleep stage) in both men and women, and all the volunteers reported more vigor the morning after the lavender night. In women, lavender also increased stage 2 (light) sleep and decreased REM (dreaming) sleep and the time spent awake after first falling asleep; in men these effects went the opposite way. The authors described lavender as a mild sedative. Each volunteer had a single lavender night, so the study shows nothing about nightly use over weeks. The shift toward more slow-wave sleep matters because slow-wave sleep is the most restorative sleep stage and is selectively reduced in aging, depression, and chronic stress.
The increase in slow-wave sleep is particularly notable because most pharmacologic sleep aids (benzodiazepines, Z-drugs) actually suppress slow-wave sleep while increasing lighter stage 2 sleep — producing the paradox where polysomnography looks worse despite subjective improvement. In the Goel 2005 data lavender increased deep restorative sleep in both sexes, while light (stage 2) sleep rose in women and fell in men.
Hospital and Intensive Care Unit Aromatherapy Trials
Lavender aromatherapy has been extensively studied in hospital sleep environments, where ambient noise, light, frequent monitoring, anxiety, and medication side effects make sleep notoriously poor. The hospital trials are particularly interesting because they are conducted in real clinical settings with measurable outcomes and substantial samples.
Cardiac care unit. In a randomized trial of 60 coronary intensive care patients (Karadag 2017), 15 days of inhaled 2% lavender essential oil improved sleep-quality (PSQI) and anxiety scores compared with no lavender. In a 50-patient pilot in an intermediate care unit (Lytle 2014), the mean sleep score was higher with lavender (48.25 vs 40.10) but the difference was not statistically significant; blood pressure was lower between midnight and 4 am (P = .03), though the overall change in blood pressure did not differ significantly between the groups (P = .12). Patients post-myocardial infarction or post-cardiac surgery have particularly disturbed sleep, and the lavender intervention is well-suited because it requires no patient cooperation, no swallowing, no intravenous (IV) access, and no monitoring.
Intensive care unit and mechanical ventilation. Critical care patients have notoriously poor sleep with high rates of delirium. Studies of lavender aromatherapy or massage in mechanically ventilated intensive care unit patients have shown reduced sedative requirements, improved sleep architecture on polysomnography, and trends toward reduced intensive care unit delirium incidence. This is potentially important because intensive care unit delirium is associated with long-term cognitive impairment, and reducing sedative use is a goal of modern intensive care unit practice (the ABCDEF bundle).
Hemodialysis units. Patients on chronic hemodialysis have a sleep-disorder prevalence approaching 80%. Trials of lavender aromatherapy in hemodialysis units have shown improvements in Pittsburgh Sleep Quality Index scores and reduced anxiety during dialysis sessions.
Postpartum wards. The postpartum period is associated with severe sleep disturbance from infant care plus the hormonal disruption of late pregnancy. Trials of lavender aromatherapy for postpartum women have shown improvements in maternal sleep quality and reductions in postpartum blues and fatigue scores. In a randomized trial of 141 pregnant women with poor sleep (Effati-Daryani 2018), a lavender cream rubbed into the skin, with or without a footbath, lowered PSQI scores compared with a placebo cream both in pregnancy and after the birth; fatigue improved only at the 6th week after the birth.
Oncology wards. Cancer patients have high rates of sleep disturbance from disease, treatment side effects, anxiety, and pain. Lavender aromatherapy and lavender-infused massage have both shown sleep-quality improvements in randomized trials in oncology populations.
The common thread across these hospital studies is that lavender is well-tolerated, produces modest but measurable sleep benefits, had no adverse events reported across the 15 studies of the 2014 Lillehei and Halcon review, and integrates easily with whatever conventional care the patient is receiving without significant drug interactions.
Elderly and Dementia-Care Aromatherapy
The elderly population is particularly vulnerable to the harms of conventional sleep aids — benzodiazepines and Z-drugs increase fall risk and fracture risk, anticholinergic sleep aids accelerate cognitive decline, and antipsychotics used off-label for sleep agitation in dementia patients have a documented increased mortality risk (U.S. Food and Drug Administration boxed warning). The case for non-pharmacologic alternatives is therefore strongest in older adults.
Lavender aromatherapy has been studied in nursing home and dementia-care unit populations with consistent positive results for sleep quality, reduced nighttime agitation, and reduced PRN psychotropic medication use. The intervention is particularly well-suited to dementia care because it requires no patient cooperation or comprehension — the diffuser runs in the room and the patient simply breathes the ambient air. Several British and Japanese nursing homes have adopted lavender aromatherapy as routine evening practice as part of falls-prevention and agitation-reduction programs.
A 2025 systematic review and meta-analysis (Ostovar and colleagues, Experimental Gerontology) found 10 clinical trials of lavender in adults over 60 with sleep problems; 9 of the 10 reported a significant improvement. All of them used inhaled lavender, and 7 measured sleep with the Pittsburgh Sleep Quality Index. The pooled sleep-quality score improved (standardized mean difference −1.20), but results varied widely between trials, and the authors called the evidence preliminary, with effectiveness and safety over long-term use still unknown.
The Henley 2007 concern about prepubertal gynecomastia from chronic lavender exposure comes from case reports in children, not adult and elderly populations — the mechanism (if real) is hypothesized to involve weak estrogenic / antiandrogenic activity of certain monoterpenes during pre-pubertal hormonal development. In older adults, the review above leaves safety over long-term use unknown.
Effect on Sleep Architecture
Normal sleep cycles through five stages in approximately 90-minute cycles across the night:
- Stage 1 NREM — the brief transition from wakefulness to sleep, characterized by theta waves and easy arousability
- Stage 2 NREM — the majority of sleep time in healthy adults, characterized by sleep spindles and K-complexes
- Stage 3-4 NREM (slow-wave sleep) — the deepest, most restorative sleep, characterized by delta waves; concentrated in the first half of the night; associated with growth hormone release, immune system regulation, glymphatic clearance of beta-amyloid and other metabolic waste
- REM sleep — the dreaming stage, characterized by rapid eye movements, muscle atonia, and electroencephalogram (EEG) patterns similar to wakefulness; concentrated in the second half of the night; critical for memory consolidation and emotional regulation
Pharmacologic sleep aids have characteristically problematic effects on this architecture. Benzodiazepines and Z-drugs increase stage 2 sleep at the expense of slow-wave sleep and REM sleep — the patient sleeps but the sleep is less restorative than natural sleep. Antidepressants (including trazodone and mirtazapine) suppress REM sleep. Antihistamines blunt slow-wave sleep.
Lavender, in the Goel 2005 polysomnographic data, does the opposite: it modestly increased slow-wave sleep in both men and women, while REM sleep fell in women and rose in men. This is consistent with the olfactory-limbic mechanism — the authors called lavender a mild sedative rather than a sedative-hypnotic in the conventional sense; it produces a calming effect that facilitates natural sleep onset.
The Bedside Diffuser Protocol
The bedtime protocol as aromatherapy practitioners commonly describe it:
- Equipment — an ultrasonic diffuser (uses water and ultrasonic vibration to mist essential oil into ambient air) or a nebulizing diffuser (no water, more intense diffusion). Ultrasonic is more common and adequate for sleep applications.
- Oil quality — pure Lavandula angustifolia essential oil, GC/MS-certified, ideally indicating linalool 30-40% and linalyl acetate 30-40%. Lavandin (Lavandula x intermedia) has a higher camphor content and a more medicinal smell. Synthetic "lavender fragrance" lacks the active monoterpenes entirely.
- Dose — 3-5 drops of essential oil in the diffuser reservoir. This is sufficient to produce a clearly detectable but not overwhelming scent in a bedroom-sized space.
- Timing — the diffuser is usually started 30 minutes before lights-out and run for 30-60 minutes. Many ultrasonic diffusers have a timer. Continuous all-night diffusion is not necessary and may be too intense for some users; the brain habituates to a continuous odor within minutes anyway.
- Pillow spray alternative — for those without a diffuser, a 1-2% lavender essential oil hydrosol or pillow spray applied to the pillowcase 10-15 minutes before bed provides a similar olfactory dose with less equipment.
- Roll-on / inhaler alternative — for travel or for use without disturbing a partner who dislikes the scent, a lavender roll-on (1-2% dilution in jojoba) applied to the wrists or temples, or a personal aromatherapy inhaler held under the nose for 30 seconds, provides a localized olfactory dose.
- Consistency — the strongest evidence comes from nightly use as a sleep ritual. The ritual itself (consistent timing, consistent context) is a behavioral cue that the brain uses to initiate the sleep-onset cascade — the aromatherapy is both an olfactory pharmacologic intervention and a behavioral conditioning cue.
Lavender vs Melatonin vs Prescription Hypnotics
How the main options for sleep improvement compare:
- Lavender aromatherapy — no adverse events reported in the reviewed inhalation studies, modest effect on sleep quality and slow-wave sleep, best suited to insomnia with an anxiety or autonomic-hyperarousal component, requires bedtime ritual, cost effectively zero
- Oral lavender oil capsule 80 mg — effective for both anxiety and sleep when anxiety is the driver of insomnia (Kasper 2015 trial specifically addressed restlessness and disturbed sleep), takes 2-4 weeks to reach effect, well-tolerated. A re-analysis of a 10-week, 212-patient placebo-controlled trial of 80 mg a day (Seifritz 2019) found that the capsule improved both anxiety (Hamilton Anxiety Scale, p < 0.001) and sleep (PSQI, p = 0.002), and that 98.4% of the sleep improvement was explained by the drop in anxiety, with no appreciable direct effect on sleep — the oil improved sleep by calming anxiety rather than by sedation
- Melatonin 0.3-3 mg — well-tolerated, most effective for circadian-rhythm disorders (jet lag, delayed sleep phase, shift work) rather than primary insomnia, the surprisingly modest evidence base for primary insomnia is often overstated in popular media. Lower doses (0.3-1 mg) appear as effective as higher doses for sleep induction in most studies
- Magnesium glycinate 400-600 mg — modest effect on sleep quality particularly in patients with documented or likely magnesium insufficiency (poor diet, alcohol use, diuretic use, proton pump inhibitor (PPI) use). See Magnesium
- Glycine 3 g at bedtime — lowers core body temperature (a sleep-onset trigger), modest effect on subjective sleep quality and morning alertness
- L-theanine 200-400 mg — mild relaxation, alpha-EEG promoting, works well in combination with other gentle agents
- Apigenin / chamomile — binds benzodiazepine site of gamma-aminobutyric acid-A receptor; gentle sedation; long history of safe use
- Z-drugs (zolpidem, eszopiclone) — effective but with significant side-effect and dependence concerns; intended for short-term use only
- Trazodone 25-100 mg off-label — commonly prescribed, works well, but produces morning grogginess and orthostatic hypotension
- Low-dose doxepin 3-6 mg — U.S. Food and Drug Administration-approved low-dose H1-antagonist for sleep maintenance; effective but with anticholinergic concerns at higher doses
- Cognitive behavioral therapy for insomnia — the gold standard; effect sizes comparable to or larger than pharmacotherapy with durable benefit beyond the treatment period; often delivered by digital health apps or therapist; the American Academy of Sleep Medicine (AASM) guideline recommends it for chronic insomnia
In the stepwise approach many practitioners describe for mild-to-moderate insomnia, sleep hygiene, lavender aromatherapy and magnesium glycinate come first, melatonin is added when there is a clear circadian component, and cognitive behavioral therapy for insomnia is added if the insomnia persists past 4-6 weeks of these simpler measures. In that approach, prescription hypnotics, with the risks listed above, are kept for cases where the simpler measures fail or for short-term use during an acute crisis.
Integration with Sleep Hygiene
Lavender aromatherapy works synergistically with the evidence-based sleep-hygiene practices on our Sleep Hygiene page:
- Consistent sleep and wake times — the body's circadian system is reinforced by consistency; weekend "social jetlag" undermines it. The bedtime diffuser ritual reinforces the consistent bedtime cue.
- Bedroom temperature 65-68°F (18-20°C) — the body must lower its core temperature by approximately 1°C to initiate sleep; an over-warm bedroom prevents this.
- Dark bedroom — even moderate light suppresses melatonin secretion; blackout curtains and removal of LED indicators from electronics matter.
- No screens for 60 minutes before bed — blue-spectrum light from screens suppresses melatonin; if screens are unavoidable, blue-light-blocking glasses or device night modes help.
- Caffeine cutoff 8 hours before bed — caffeine's half-life is 5-6 hours; an afternoon coffee is still measurably affecting adenosine receptor signaling at bedtime.
- Alcohol — modest amounts, not late — alcohol initially sedates but disrupts sleep architecture in the second half of the night and causes early awakening as it metabolizes.
- Exercise during the day, not within 3 hours of bed — regular exercise dramatically improves sleep but immediate pre-sleep exercise raises core temperature and alertness.
- Daytime light exposure — 30 minutes of bright morning light synchronizes the circadian clock and improves nighttime sleep quality.
- Bedroom for sleep and sex only — the bed becomes associated with the activities done in it; working or watching TV in bed conditions the brain to alertness rather than sleep when in that location.
- Getting up after 20 minutes awake in bed — staying in bed awake conditions the bed as a place of frustration. The stimulus-control method has the person get up, do a quiet activity in dim light, and return to bed when sleepy.
The lavender ritual reinforces the bedroom-as-sleep-cue conditioning, calms the autonomic system to facilitate sleep onset, and produces a modest direct improvement in sleep architecture. It is best thought of as one component of a broader sleep-promotion approach rather than a stand-alone solution for severe insomnia.
Key Research Papers
- Lewith GT, Godfrey AD, Prescott P (2005). A single-blinded, randomized pilot study evaluating the aroma of Lavandula angustifolia as a treatment for mild insomnia. Journal of Alternative and Complementary Medicine. — PubMed PMID: 16131287
- Goel N, Kim H, Lao RP (2005). An olfactory stimulus modifies nighttime sleep in young men and women. Chronobiology International. — PubMed PMID: 16298774
- Kasper S, Anghelescu I, Dienel A (2015). Efficacy of orally administered Silexan in patients with anxiety-related restlessness and disturbed sleep. European Neuropsychopharmacology. — PubMed PMID: 26293583
- Lytle J, Mwatha C, Davis KK (2014). Effect of lavender aromatherapy on vital signs and perceived quality of sleep in the intermediate care unit. American Journal of Critical Care. — PubMed PMID: 24382614
- Karadag E et al. (2017). Effect of aromatherapy on sleep quality and anxiety of patients. Nursing in Critical Care. — PubMed PMID: 26211735
- Effati-Daryani F, Mohammad-Alizadeh-Charandabi S, Mirghafourvand M, Taghizadeh M, Bekhradi R, Zarei S (2018). Effect of Lavender cream with or without footbath on sleep quality and fatigue in pregnancy and postpartum: a randomized controlled trial. Women & Health. — PubMed PMID: 29787355
- Muz G, Tasci S (2017). Effect of aromatherapy via inhalation on sleep quality and fatigue in hemodialysis patients. Applied Nursing Research. — PubMed PMID: 28985917
- Lillehei AS, Halcon LL (2014). A systematic review of the effect of inhaled essential oils on sleep. Journal of Alternative and Complementary Medicine. — PubMed PMID: 24720812
- Lee IS, Lee GJ (2006). [Effects of lavender aromatherapy on insomnia and depression in women college students]. Taehan Kanho Hakhoe Chi. — PubMed PMID: 16520572
- Velasco-Rodríguez R et al. (2019). The effect of aromatherapy with lavender (Lavandula angustifolia) on serum melatonin levels. Complementary Therapies in Medicine. — PubMed PMID: 31780012
- Field T et al. (2008). Lavender bath oil reduces stress and crying and enhances sleep in very young infants. Early Human Development. — PubMed PMID: 18053656
- Shen H, Zhang LJ, Zhu WY (2026). The Sleep-Enhancing Effect of Lavender Essential Oil in Adults: A Systematic Review and Meta-Analysis. Holistic Nursing Practice. — PubMed PMID: 40600743
- Ostovar M, Khademizadeh MH, Namjoyan F, Kazemi A, Vakili S, Mosavat SH, Mohit M, Hashempur MH (2025). A systematic review and meta-analysis of clinical trials on lavender for sleep disorders in older adults. Experimental Gerontology. — PubMed PMID: 41057090
- Seifritz E, Schlafke S, Holsboer-Trachsler E (2019). Beneficial effects of Silexan on sleep are mediated by its anxiolytic effect. Journal of Psychiatric Research. — PubMed PMID: 31121394
PubMed Topic Searches
Connections
- All Herbs
- Lavender Overview
- Lavender Benefits Hub
- Lavender for Anxiety & Stress
- Lavender for Headache & Migraine
- Lavender for Skin Healing & Burns
- Sleep Hygiene
- Stress Management
- Chamomile
- Passionflower
- Lemon Balm
- Valerian
- Magnesium Glycinate
- Glycine
- Anxiety
- Depression
- Aromatherapy — the delivery method behind every trial on this page, including the bedside diffuser protocol and the hospital and dementia-care studies.
- Covered in depth on its own page: Insomnia
- History