⚠ Evidence warning: Clinical trials or other evidence do not support the claim that a lavender roll-on or inhaler works as a rescue for acute panic. This page keeps it as a report of what people, websites or other media say.
Lavender for Anxiety and Stress
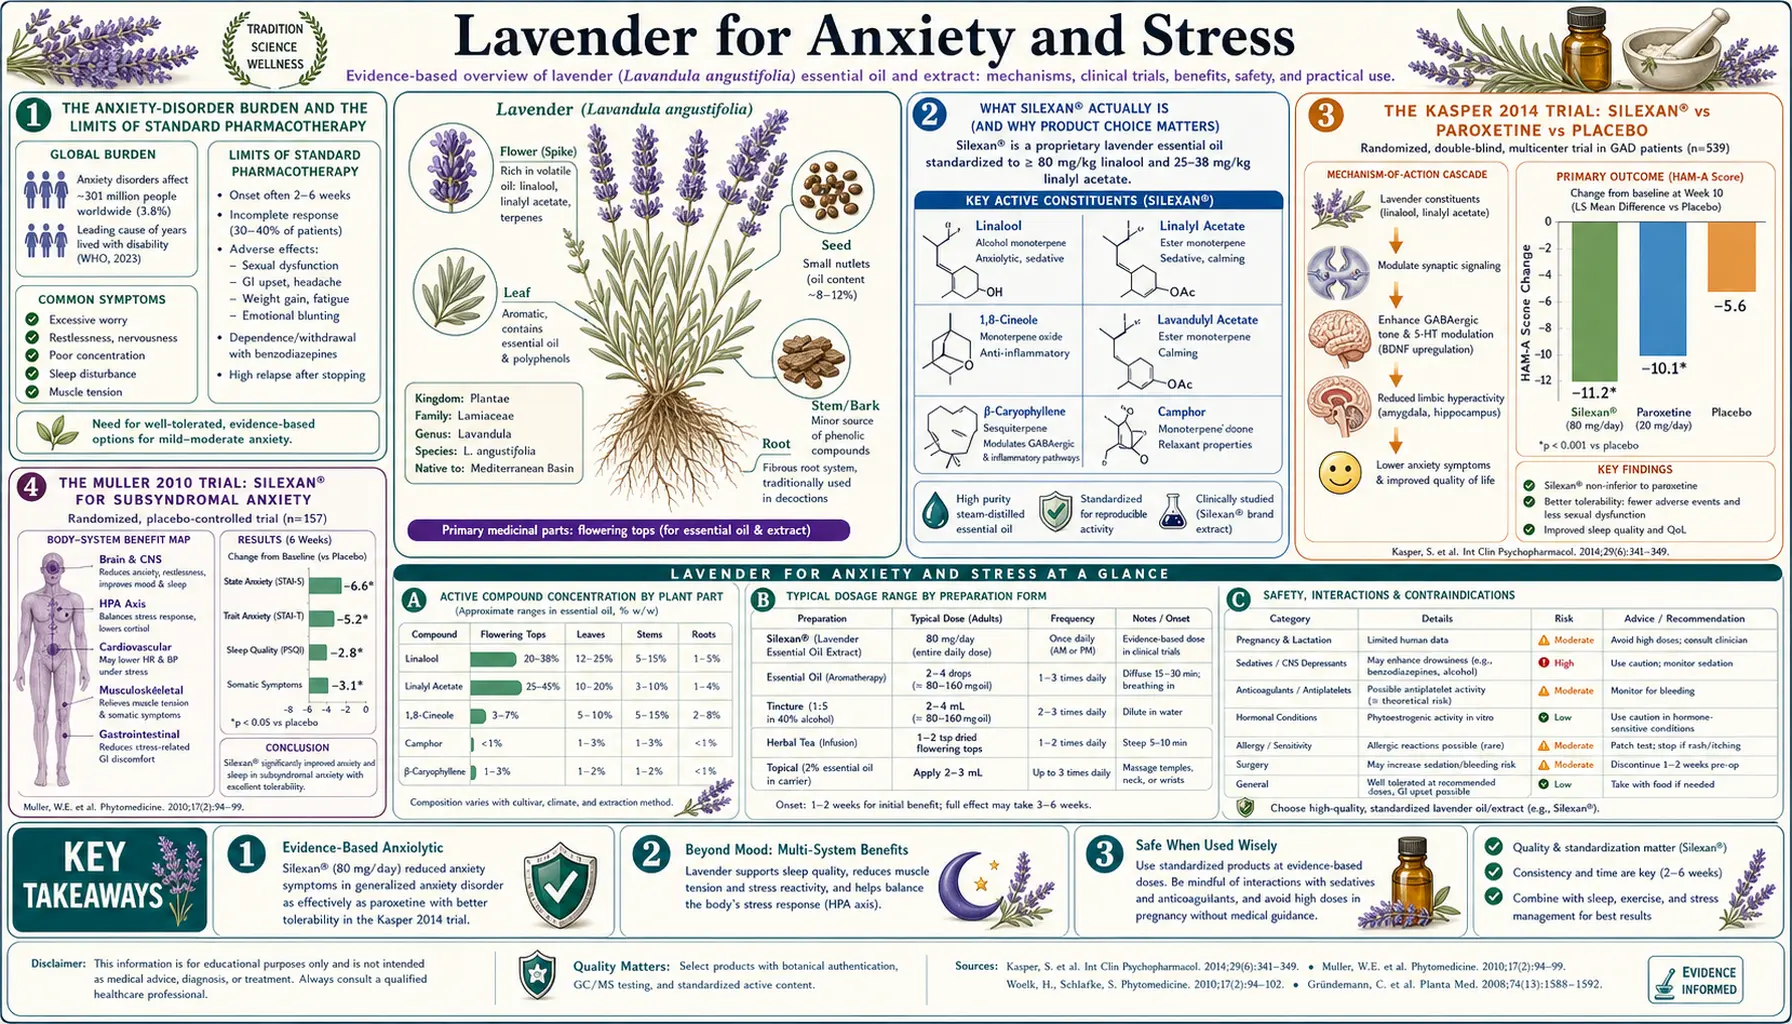
Of every herbal anxiolytic studied in modern controlled trials, the standardized oral lavender oil preparation (80 mg/day) has the most replicated efficacy data — including two head-to-head trials against pharmaceutical comparators (paroxetine in the Kasper 2014 trial, lorazepam in the Woelk 2010 trial) showing comparable anxiolytic effect without the sedation, dependence, withdrawal, or sexual dysfunction that limit those drugs. Laboratory work shows the oil inhibits voltage-gated calcium channels, with some similarities to pregabalin. An effect on the serotonin 5-HT1A receptor has also been reported, but a 2025 review by trial authors states that the exact way it acts on the serotonin system remains unclear. Selective serotonin reuptake inhibitors (SSRIs) are the usual comparison. This page walks through the trials, the mechanism, the dosing used in trials, the safety profile, and where the oral preparation and lavender aromatherapy fit within an integrative approach to subsyndromal anxiety, generalized anxiety disorder, and acute situational stress.
Table of Contents
- The Anxiety-Disorder Burden and the Limits of Standard Pharmacotherapy
- What the Oral Lavender Oil Preparation Actually Is (and Why Product Choice Matters)
- The Kasper 2014 Trial: Oral Lavender Oil vs Paroxetine vs Placebo
- The Kasper 2010 Trial: Oral Lavender Oil for Subsyndromal Anxiety
- The Woelk 2010 Trial: Oral Lavender Oil vs Lorazepam
- Mechanism: Serotonin 5-HT1A Receptor Effects Remain Unclear
- Mechanism: Voltage-Gated Calcium Channel Inhibition
- Mechanism: Olfactory-Limbic Pathway (Inhalational Route)
- Dosing Used in Studies and Time to Effect
- Safety Profile: What the Oral Lavender Oil Preparation Does Not Do
- Lavender Capsules and Depression
- What Practitioners Combine in Integrative Anxiety Care
- Key Research Papers
- Connections
- Featured Videos
The Anxiety-Disorder Burden and the Limits of Standard Pharmacotherapy
Anxiety disorders are the most common class of psychiatric illness, affecting approximately 31% of U.S. adults over the lifetime and 19% in any given year per the National Comorbidity Survey Replication. The standard pharmacologic interventions — selective serotonin reuptake inhibitors (escitalopram, sertraline, paroxetine), serotonin-norepinephrine reuptake inhibitors (venlafaxine, duloxetine), benzodiazepines (alprazolam, lorazepam, clonazepam), the 5-HT1A partial agonist buspirone, and the calcium-channel-binding pregabalin — are all effective in controlled trials but each has substantial limitations:
- Selective serotonin reuptake inhibitors and serotonin-norepinephrine reuptake inhibitors (SNRIs) take 2-4 weeks to reach efficacy, frequently worsen anxiety in the first 1-2 weeks, cause sexual dysfunction in 40-60% of users, and produce a documented discontinuation syndrome on cessation that can persist for weeks.
- Benzodiazepines act rapidly and reliably but carry tolerance, physiologic dependence, severe withdrawal (including seizure risk), driving impairment, fall risk in the elderly, a U.S. Food and Drug Administration (FDA) boxed warning covering risks with opioids, abuse, misuse and addiction, and dependence and withdrawal reactions, and a still-debated but consistent signal for accelerated cognitive decline and dementia in long-term users.
- Buspirone is non-sedating and non-dependence-producing but is generally considered less potent and has a slow onset.
- Pregabalin is effective but is controlled in the U.K. and several other jurisdictions due to abuse potential and produces sedation and weight gain.
Subsyndromal anxiety — symptoms that cause distress but do not meet full diagnostic criteria for generalized anxiety disorder (GAD) — is even more common and is often poorly served by standard pharmacotherapy, which generally requires a formal diagnosis to justify the risk-benefit ratio. The clinical opening for an effective, well-tolerated, non-dependence-producing botanical with a good safety profile and rapid onset is therefore very large — and standardized oral lavender oil is the botanical most tested for that gap.
What the Oral Lavender Oil Preparation Actually Is (and Why Product Choice Matters)
The oral lavender oil preparation is a specific patented preparation of Lavandula angustifolia essential oil, made by one manufacturer in Germany. The active drug substance is a steam-distilled essential oil from cultivated L. angustifolia flowers with a tightly controlled chromatographic profile: linalool 36.8%, linalyl acetate 34.2%, with cineole, camphor, beta-caryophyllene, and other minor monoterpenes at fixed ratios. The standard dose is one soft-gel capsule of 80 mg taken orally once daily; some trials have used 160 mg (two capsules).
This standardization matters because virtually all of the positive clinical trial data refers to this one preparation, not to lavender essential oil in general. A bottle of lavender essential oil from a health-food store has a different chemotype (concentration of active compounds varies by plant genetics, growing conditions, altitude, and distillation), a different manufacturing process, no oral safety testing, and no pharmacokinetic characterization. Lavender essential oil is not intended for internal use — the only oral preparation that has been formally studied and approved as a medicine is this one.
In Germany and Austria, the preparation is approved by BfArM (the German federal medicines agency) for "restlessness related to anxious mood" (a formal indication under German pharmaceutical law) and is dispensed under a brand name. It is not currently approved by the U.S. Food and Drug Administration in the United States and is sold as a dietary supplement under another brand name — the actual product is identical, but the U.S. regulatory framework does not allow the same medical claims.
Other lavender preparations — capsules, teas, tinctures, herbal blends — have very limited clinical trial data. The aromatherapy literature covers situational anxiety (preoperative, intensive care unit (ICU), dental procedures) but uses a different route (inhalational) and a different mechanism (olfactory-limbic). When this page references "lavender for anxiety" it generally means this oral preparation unless explicitly stated otherwise.
Who ran the research matters too. Several authors of the key trials were employed by the maker: the listed affiliations of the 2014 paroxetine trial place two of its seven authors at the company, and the 2025 depression trial states that two authors are employees of its sponsor. A 2019 systematic review that reports no funding rates the average quality of lavender studies as low, with most randomized trials at high overall risk of bias.
The Kasper 2014 Trial: Oral Lavender Oil vs Paroxetine vs Placebo
The Kasper 2014 trial, published in the International Journal of Neuropsychopharmacology, is the largest and most rigorous of the trials of this preparation and the most consequential because it is the only head-to-head comparison of a botanical to a selective serotonin reuptake inhibitor for generalized anxiety disorder.
Design. Randomized, double-blind, double-dummy, placebo-controlled, parallel-group, multicenter trial in 539 outpatients meeting Diagnostic and Statistical Manual of Mental Disorders, fifth edition (DSM-5) criteria for generalized anxiety disorder, with all doses given once daily. Four arms:
- Oral lavender oil preparation 160 mg/day (two 80 mg capsules)
- Oral lavender oil preparation 80 mg/day (one 80 mg capsule)
- Paroxetine 20 mg/day (the standard selective serotonin reuptake inhibitor (SSRI) dose for GAD)
- Placebo
Duration was 10 weeks. The primary outcome was change in the Hamilton Anxiety Rating Scale (HAM-A) total score.
Results. Both lavender doses produced statistically significant and clinically meaningful reductions in HAM-A scores vs placebo (p < 0.01), with the higher dose (160 mg/day) numerically superior to the lower (80 mg/day): the HAM-A fell by 14.1 points on 160 mg, 12.8 on 80 mg, 11.3 on paroxetine and 9.5 on placebo. The effect sizes were comparable to or slightly larger than paroxetine, but paroxetine itself showed only a trend over placebo in the full analysis (p = 0.10), with a clearer difference among those who finished (p < 0.01), so "comparable to paroxetine" comes from a trial where the comparator did not clearly separate in the main analysis. The 160 mg arm separated from placebo on the HAM-A as early as week 2 — faster than paroxetine. The remission rate (HAM-A < 10) was 46.3% on 160 mg and 33.3% on 80 mg, against 34.1% on paroxetine and 29.6% on placebo.
Tolerability. The dropout rate due to adverse events was lower in both lavender groups than in the paroxetine group. The most common adverse event of the lavender capsule was eructation (burping with a lavender flavor), given as approximately 1-3% of subjects; a 2025 trial in depression reported it in 16.5% (see Lavender Oil Capsules and Depression). There were no reports of sexual dysfunction in the lavender groups vs the expected selective serotonin reuptake inhibitor rate in the paroxetine arm.
A 2026 network meta-analysis of 100 trials and 28,637 people included this capsule as the only herbal product: it was as acceptable as placebo, and it was one of four treatments with fewer adverse events than placebo. The analysis and its medical writing were supported by the maker through a grant; the authors state the funder had no further role.
This is the trial that established the preparation as evidence-based pharmacotherapy for GAD in Germany. It is also one of the most cited studies in the modern phytomedicine literature.
The Kasper 2010 Trial: Oral Lavender Oil for Subsyndromal Anxiety
The Kasper 2010 trial in International Clinical Psychopharmacology addressed a different population — subjects with "subsyndromal anxiety disorder" (HAM-A >= 18 but not meeting full DSM criteria for a specific anxiety diagnosis). This is arguably the largest unmet-need population, because subsyndromal anxiety is extremely common but is poorly served by standard pharmacotherapy which generally requires a formal diagnosis.
Design. 221 subjects, randomized to the oral lavender oil preparation 80 mg/day or placebo for 10 weeks, double-blind, multicenter.
Results. The preparation produced a HAM-A reduction of 16.0 points from baseline vs 9.5 points for placebo (large effect). Sleep duration, sleep quality, daytime well-being, and the Clinical Global Impression rating all improved significantly more with the preparation. Onset of effect was rapid — separation from placebo on the HAM-A was evident by week 2.
Implication. The trial authors concluded the preparation is efficacious and safe for anxiety disorder not otherwise specified, in people who do not meet GAD criteria. This is a meaningful clinical gap because conventional anxiety pharmacotherapy is generally restricted to formal anxiety diagnoses — and yet a large proportion of people experiencing distressing anxiety symptoms fall into the subsyndromal category.
The Woelk 2010 Trial: Oral Lavender Oil vs Lorazepam
The Woelk and Schläfke 2010 trial, also in Phytomedicine, is the head-to-head benzodiazepine comparison. 77 subjects with DSM-IV generalized anxiety disorder were randomized to the oral lavender oil preparation 80 mg/day or lorazepam 0.5 mg/day for 6 weeks, double-blind.
Results. HAM-A reduction was statistically non-inferior between groups: 11.3 points with the preparation vs 11.6 points with lorazepam. A 2025 review by trial authors gives a response rate (50% reduction in HAM-A) of 52.5% vs 40.5% (p = 0.04) and remission of 40% vs 27% (p = 0.04), both favouring the preparation, and calls this a proof-of-concept study with lorazepam at its initial therapeutic dose. Importantly, there was no daytime sedation, no rebound anxiety on cessation, and no withdrawal syndrome with the preparation — in contrast to lorazepam, where rebound and discontinuation effects are well documented even at this low dose.
Implication. In this trial the preparation matched a low-dose benzodiazepine for GAD efficacy, and the authors report no sedative effects and no potential for drug abuse with it; benzodiazepine use is limited by the dependence, withdrawal, driving impairment, fall risk, and potential dementia signal listed above. The trial tested 6 weeks of treatment, not switching people off a long-term benzodiazepine, and no study testing the preparation during a taper was found. The lorazepam label's boxed warning states that abrupt discontinuation or rapid dosage reduction after continued use may precipitate acute withdrawal reactions, which can be life-threatening.
Mechanism: Serotonin 5-HT1A Receptor Effects Remain Unclear
One hypothesized mechanism for the preparation's anxiolytic effect is an action at the 5-HT1A serotonin receptor. The 5-HT1A receptor is concentrated in the raphe nuclei (where it acts as an inhibitory autoreceptor on serotonergic neurons), the hippocampus, the prefrontal cortex, and the amygdala. Partial agonists at 5-HT1A include buspirone, vilazodone, and gepirone; the antidepressant vortioxetine is itself a 5-HT1A receptor agonist according to its FDA label, which describes its major metabolite as pharmacologically inactive.
The proposed advantage of direct 5-HT1A partial agonism over selective serotonin reuptake inhibitor mechanism is that the effect would not be delayed by the 2-4 weeks of receptor downregulation that limits selective serotonin reuptake inhibitor onset. The selective serotonin reuptake inhibitor mechanism increases synaptic serotonin acutely, but this initial increase paradoxically activates 5-HT1A autoreceptors and decreases serotonergic firing — which is why anxiety symptoms typically worsen for the first 1-2 weeks of selective serotonin reuptake inhibitor therapy. Only after the autoreceptors downregulate does net serotonergic transmission increase, producing the therapeutic effect.
On this reasoning, a direct 5-HT1A partial agonist would bypass that mechanism — moderate, sustained activation of 5-HT1A receptors without first triggering the autoreceptor inhibitory feedback, with no worsening in the first 2 weeks and no sexual dysfunction (which is a downstream consequence of generalized serotonin elevation, not 5-HT1A activation per se). Buspirone, however, has the slow onset listed above. Whether the lavender preparation works this way has not been shown.
What has been measured points in a different direction from direct agonism. In a brain-imaging study of 17 healthy men, at least 8 weeks of 160 mg/day reduced 5-HT1A receptor binding compared with placebo in the hippocampus and other regions. A 2025 review by trial authors says the preparation "might affect" serotonin receptors, compares that reduced binding with changes seen after prolonged SSRI use, and states that "the exact mechanism" on the serotonin system "remains unclear". The calcium-channel route below is the mechanism described in laboratory experiments.
Mechanism: Voltage-Gated Calcium Channel Inhibition
A well-characterized mechanism for lavender oil in laboratory experiments is inhibition of N-type and P/Q-type voltage-gated calcium channels (VGCCs). Presynaptic VGCCs control neurotransmitter release into the synapse — inhibiting them reduces release of glutamate, the principal excitatory neurotransmitter in the brain. This is the same broad class of mechanism exploited by gabapentin and pregabalin (which bind the alpha-2-delta auxiliary subunit of the VGCC), by ethosuximide (T-type calcium channel block for absence seizures), and by some calcium-channel-blocking migraine prophylactics (verapamil, flunarizine).
For anxiety specifically, glutamatergic hyperactivity in the amygdala and the bed nucleus of the stria terminalis is a major contributor to the anxious state. Reducing presynaptic glutamate release through VGCC inhibition produces a moderating, calming effect on this hyperactivity. This is the proposed mechanism behind pregabalin's anxiolytic effect and is likely a significant component of the lavender preparation's as well.
The VGCC mechanism is also relevant to lavender's analgesic effects in the migraine and tension headache deep-dive, because pain transmission in the spinal cord dorsal horn similarly depends on glutamate release from primary afferent terminals.
Mechanism: Olfactory-Limbic Pathway (Inhalational Route)
The aromatherapy literature for lavender (distinct from the oral capsule literature) demonstrates rapid anxiolytic effects from simple inhalation. The mechanism is anatomically unusual: the olfactory system is the only sensory modality that projects directly to the amygdala, hippocampus, and hypothalamus without first synapsing in the thalamus or being processed by cortex. This direct subcortical pathway is why olfactory stimuli have such powerful and rapid emotional, autonomic, and memory effects.
Lavender molecules (linalool, linalyl acetate, and others) reach the olfactory epithelium in the upper nasal cavity, bind olfactory receptors expressed on the cilia of olfactory sensory neurons, depolarize those neurons, and propagate signals through the olfactory bulb and tract directly to the cortical amygdala. The amygdala then modulates the hypothalamic-pituitary-adrenal axis and the autonomic nervous system. The reported net effect is a rapid (often within minutes) reduction in heart rate and subjective anxiety, and a modest shift toward parasympathetic dominance in heart rate variability.
The classic aromatherapy applications include:
- Preoperative anxiety — multiple controlled trials show reduced State-Trait Anxiety Inventory (STAI) scores in patients waiting for surgery
- Dental procedure anxiety — lavender diffusion in dental waiting rooms reduces anxiety scores
- Intensive care unit patient agitation — aromatherapy reduces sedative medication requirements in mechanically ventilated patients
- Pre-MRI anxiety — reduces claustrophobic discomfort and may reduce sedation needs
- Acute panic — people describe using a lavender roll-on or inhaler as a portable rescue technique; no study testing this was found
The aromatherapy literature is methodologically harder than oral pharmacology trials — blinding is difficult because lavender has a distinctive smell, and "placebo" odorless controls aren't truly inert.
A 2019 systematic review pooled lavender inhalation at Hedges' g −0.73 (95% confidence interval −1.00 to −0.46; 1,682 people), with no significant effect on systolic blood pressure. Its authors rate average study quality as low, with most randomized trials at high overall risk of bias, and because the inhalation studies differ so much they call this "only an indication of an effect". Massage with lavender oil pooled at g −0.66, but the studies cannot show whether the benefit comes from the lavender or the massage. Oral capsules at 80 mg/day for at least 6 weeks lowered the HAM-A by 2.90 points. The review states that available information outlines a safe profile for lavender, while more attention is needed to collecting and reporting safety data. A 2020 meta-analysis of aromatherapy in general for anxiety before surgery (20 trials, 1,717 people) found a standardized mean difference of −0.57, and sessions of 20 minutes or less did better than longer ones, which sits against the 30-minute protocol listed below.
Dosing Used in Studies and Time to Effect
- Oral lavender oil preparation — 80 mg once daily is the dose used in trials for subsyndromal anxiety. For full GAD, 160 mg once daily (two 80 mg capsules together) was used in the Kasper 2014 trial high-dose arm and produced numerically larger effects. Onset is detectable by week 2; full effect by week 6-8. The trial reports describe fixed daily doses with no build-up step.
- Duration of therapy — trials have evaluated 6-10 weeks. Some people continue for several months or longer; the trials report no tolerance or loss of effect over their length, and a 1-week follow-up found no withdrawal effects on stopping.
- Aromatherapy (inhalational route) — a 30-minute exposure to lavender essential oil diffused at 2-3% concentration (a few drops in a typical ultrasonic diffuser) is the typical research protocol. For acute situational anxiety, people describe using a lavender roll-on at the wrists or temples or a personal aromatherapy inhaler stick as a more discreet option.
- Lavender tea — 1-2 teaspoons of dried L. angustifolia flowers steeped in hot water for 5-10 minutes. Mild effect, primarily through the inhalational route (the steam carries volatile linalool) plus modest oral absorption. The capsule trials do not cover tea, which people use mainly as a bedtime ritual.
- Topical / massage — lavender essential oil at 1-3% dilution in a carrier oil (jojoba, sweet almond) for massage. The systemic dose from topical absorption is small but the combination of olfactory exposure and the relaxation of the massage itself is reported to produce a strong subjective anxiolytic effect, though the studies cannot separate the lavender from the massage.
Safety Profile: What the Oral Lavender Oil Preparation Does Not Do
The safety profile of the preparation across the published trial population is striking primarily for what doesn't happen, with the caution that much of this research was run with its maker:
- No daytime sedation — psychomotor performance, driving tests, and reaction-time studies show no impairment at standard doses. This distinguishes the preparation from benzodiazepines and sedating antidepressants.
- No tolerance or dependence — trials show preserved effect over the full study duration; no escalation needed; no withdrawal syndrome on cessation. After abrupt stopping, a withdrawal checklist showed no withdrawal effects over 1 week, and among 34 evaluable recreational drug users, even a 640 mg dose rated like placebo for drug liking, unlike lorazepam. This distinguishes the preparation from benzodiazepines.
- No sexual dysfunction — in contrast to selective serotonin reuptake inhibitors, which produce sexual side effects in 40-60% of users.
- No weight gain — in contrast to mirtazapine, pregabalin, and several second-generation antipsychotics used off-label for anxiety.
- No discontinuation syndrome — the 1-week follow-up found the preparation could be stopped abruptly without the withdrawal symptoms seen with selective serotonin reuptake inhibitors/serotonin-norepinephrine reuptake inhibitors or benzodiazepines.
- QT interval not established — no study of this preparation's effect on the heart's QT interval was found, while several psychiatric medications require electrocardiogram (ECG) monitoring.
The most common adverse events are mild gastrointestinal: eructation with a lavender flavor (1-3% here, 16.5% in the 2025 depression trial), nausea (rare), and dyspepsia (rare). Eructation is mitigated by taking the capsule with food. Allergic reactions are rare but possible.
A 2023 pooled analysis of all 5 placebo-controlled trials at 80 mg/day (1,213 people) found people on the capsule were 1.34 times as likely to respond, with no significant difference from placebo in adverse events, serious adverse events, or dropouts due to adverse events.
Drug interactions are limited but not zero. Additive central nervous system (CNS) depressant effects with benzodiazepines, alcohol, or sedating antihistamines are theoretical; a 2025 review by trial authors reports no evidence of drug interactions in clinical studies or post-marketing experience. The preparation does not appear to be a meaningful CYP450 inhibitor or inducer, so significant interactions with most prescription drugs are unlikely.
The Henley 2007 New England Journal of Medicine case series proposed an association between lavender essential oil and tea tree oil exposure and prepubertal gynecomastia, suggesting weak estrogenic / antiandrogenic activity of certain monoterpenes. Subsequent analyses have been mixed and the proposed mechanism is disputed. The report describes three prepubertal boys with repeated topical exposure to products containing these oils, whose gynecomastia resolved after use stopped, and cell-line work showed estrogenic and antiandrogenic activity. It reports no dose finding and did not study inhalation, the oral capsule, or adults.
Lavender Capsules and Depression
In a randomized trial of 498 people with a mild or moderate episode of major depression, the oral lavender oil preparation at 80 mg/day lowered the Montgomery Åsberg Depression Rating Scale (MADRS) by 2.17 points more than placebo over 8 weeks, against 2.59 points for sertraline 50 mg/day. Both were well tolerated, and burping was the most frequent side effect of the lavender capsule. Two of the authors are employees of the trial's sponsor.
What Practitioners Combine in Integrative Anxiety Care
Integrative practitioners describe combining the items below for people with anxiety who want to start with a low-risk botanical. This is a description of reported practice, not a tested protocol:
- Oral lavender oil preparation 80 mg once daily as the primary anxiolytic agent, with 4-6 weeks described for full effect.
- Lavender essential oil aromatherapy for acute symptoms — people describe a personal inhaler stick or roll-on for situational anxiety, panic episodes, or pre-procedural stress.
- Magnesium glycinate 400-600 mg/day — practitioners describe it as addressing low magnesium, which they report is common in anxious people and potentiates N-methyl-D-aspartate-receptor-mediated excitation, and they favor the glycinate form for tolerability and GABAergic synergy. This figure does not say whether it means elemental magnesium; the US Institute of Medicine set the adult upper limit for supplemental magnesium at 350 mg/day, with diarrhea as the limiting effect.
- Glycine 1-3 g at bedtime — glycine is itself a major inhibitory neurotransmitter and a co-agonist at excitatory N-methyl-D-aspartate receptors, and practitioners report it may improve sleep onset in anxious people.
- L-theanine 200-400 mg as needed — the amino acid from green tea has modest acute anxiolytic effects and is reported to promote alpha brain waves (alpha-EEG).
- Bedtime chamomile tea — the apigenin in chamomile binds the benzodiazepine site of the gamma-aminobutyric acid-A receptor and produces a mild, well-tolerated sleep-facilitating effect.
- Cognitive behavioral therapy (CBT) — the only intervention with effect sizes that rival pharmacotherapy and durable benefit beyond the treatment period.
- Sleep — practitioners often address sleep first, because chronic sleep deprivation produces and worsens anxiety. The companion deep-dive is Lavender for Sleep Quality.
- Exercise — meta-analyses show that 150 minutes of moderate aerobic exercise per week produces effect sizes comparable to selective serotonin reuptake inhibitors for mild-to-moderate anxiety.
- Less caffeine — especially in caffeine-sensitive metabolizers (CYP1A2 slow variant). People who stop caffeine for 2 weeks often report dramatic improvement.
For severe or refractory anxiety, particularly with panic, suicidality, or significant functional impairment, conventional pharmacotherapy (selective serotonin reuptake inhibitor/serotonin-norepinephrine reuptake inhibitor (SNRI)) with psychiatric follow-up is the standard treatment, and suicidal thoughts are a sign hospitals treat as urgent. Some practitioners use the lavender preparation as an add-on. No study testing it as a step-down during a benzodiazepine taper was found; the lorazepam label warns of dependence and withdrawal reactions.
Key Research Papers
- Kasper S, Gastpar M, Müller WE et al. (2014). Lavender oil preparation Silexan is effective in generalized anxiety disorder — a randomized, double-blind comparison to placebo and paroxetine. International Journal of Neuropsychopharmacology. — PubMed PMID: 24456909
- Kasper S, Gastpar M, Müller WE, Volz HP, Möller HJ, Dienel A, Schläfke S (2010). Silexan, an orally administered Lavandula oil preparation, is effective in the treatment of 'subsyndromal' anxiety disorder: a randomized, double-blind, placebo controlled trial. International Clinical Psychopharmacology. — PubMed PMID: 20512042
- Woelk H, Schläfke S (2010). A multi-center, double-blind, randomised study of the Lavender oil preparation Silexan in comparison to Lorazepam for generalized anxiety disorder. Phytomedicine. — PubMed PMID: 19962288
- Kasper S, Anghelescu I, Dienel A (2015). Efficacy of orally administered Silexan in patients with anxiety-related restlessness and disturbed sleep — a randomized, placebo-controlled trial. European Neuropsychopharmacology. — PubMed PMID: 26293583
- Gastpar M, Müller WE, Volz HP, Möller HJ, Schläfke S, Dienel A, Kasper S (2017). Silexan does not cause withdrawal symptoms even when abruptly discontinued. International Journal of Psychiatry in Clinical Practice. — PubMed PMID: 28319423
- Linalool and serotonin 5-HT1A receptor studies — PubMed
- Schuwald AM et al. (2013). Lavender oil-potent anxiolytic properties via modulating voltage-dependent calcium channels. PLOS ONE. — PubMed PMID: 23637742
- Kasper S, Müller WE, Volz HP, Möller HJ, Koch E, Dienel A (2018). Silexan in anxiety disorders: Clinical data and pharmacological background. The World Journal of Biological Psychiatry. — PubMed PMID: 28511598
- Guo P, Li P, Zhang X, et al. (2020). The effectiveness of aromatherapy on preoperative anxiety in adults: A systematic review and meta-analysis of randomized controlled trials. International Journal of Nursing Studies. — PubMed PMID: 32861206
- Donelli D et al. (2019). Effects of lavender on anxiety: a systematic review and meta-analysis. Phytomedicine. — PubMed PMID: 31655395
- Henley DV et al. (2007). Prepubertal gynecomastia linked to lavender and tea tree oils. New England Journal of Medicine. — PubMed PMID: 17267908
- Kasper S, Eckert A (2025). Silexan in anxiety, depression, and related disorders: pharmacological background and clinical data. European Archives of Psychiatry and Clinical Neuroscience. — PubMed PMID: 39453446
- Baldinger P, Höflich AS, Mitterhauser M, et al. (2014). Effects of Silexan on the serotonin-1A receptor and microstructure of the human brain: a randomized, placebo-controlled, double-blind, cross-over study with molecular and structural neuroimaging. The International Journal of Neuropsychopharmacology. — PubMed PMID: 25522403
- Dold M, Bartova L, Volz HP, Seifritz E, Möller HJ, Schläfke S, Kasper S (2023). Efficacy of Silexan in patients with anxiety disorders: a meta-analysis of randomized, placebo-controlled trials. European Archives of Psychiatry and Clinical Neuroscience. — PubMed PMID: 36717399
- Seifritz E, Möller HJ, Volz HP, Müller WE, Hopyan T, Wacker A, Schläfke S, Kasper S (2021). No Abuse Potential of Silexan in Healthy Recreational Drug Users: A Randomized Controlled Trial. The International Journal of Neuropsychopharmacology. — PubMed PMID: 33300578
- Müller TJ, Künzi A, Heitlinger E, et al. (2026). Comparative efficacy and acceptability of anxiolytic drugs for the treatment of anxiety disorders: a systematic review and network meta-analysis. European Archives of Psychiatry and Clinical Neuroscience. — PubMed PMID: 40788541
- Kasper S, Volz HP, Möller HJ, et al. (2025). Lavender oil preparation Silexan is effective in mild-to-moderate major depression: a randomized, placebo- and reference-controlled trial. European Archives of Psychiatry and Clinical Neuroscience. — PubMed PMID: 38558147
- Raiteri L (2024). Interactions Involving Glycine and Other Amino Acid Neurotransmitters: Focus on Transporter-Mediated Regulation of Release and Glycine-Glutamate Crosstalk. Biomedicines. — PubMed PMID: 39062091
- Costello R, Rosanoff A, Nielsen F, West C (2023). Perspective: Call for Re-evaluation of the Tolerable Upper Intake Level for Magnesium Supplementation in Adults. Advances in Nutrition. — PubMed PMID: 37487817