Chamomile for Skin Healing
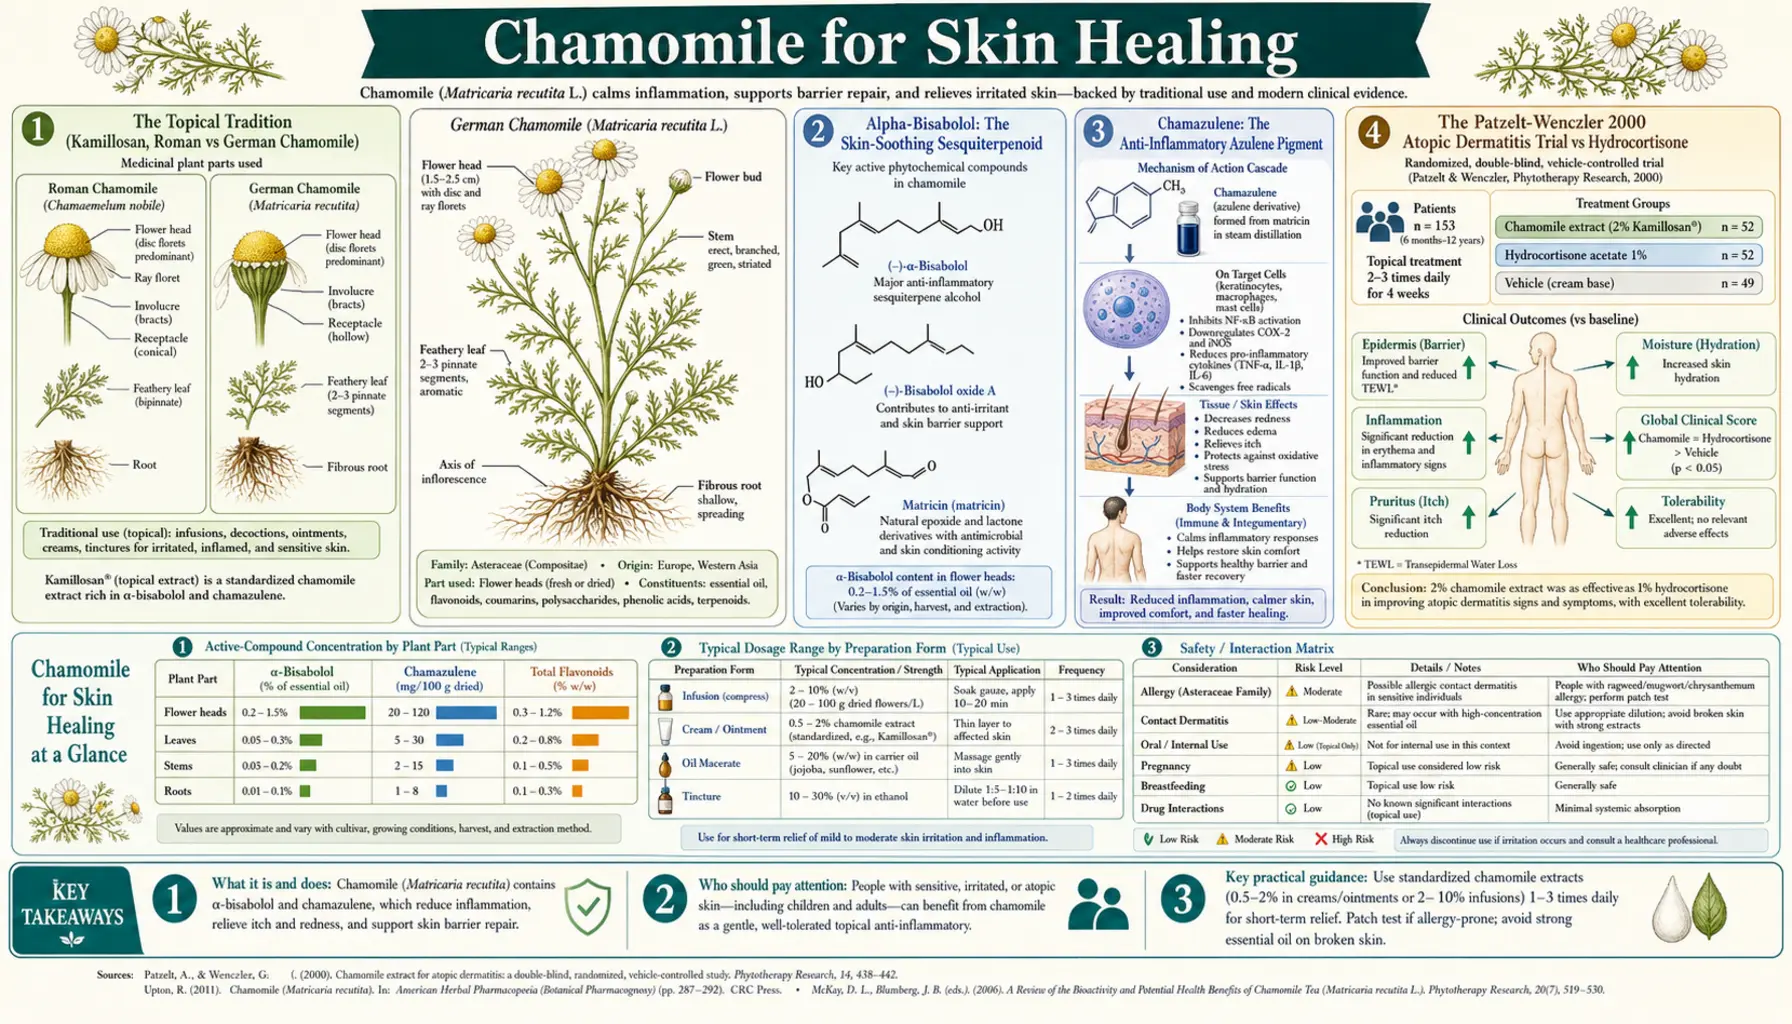
Topical chamomile has the deepest evidence base of any traditional herbal skin remedy. The most cited study is Patzelt-Wenczler and Ponce-Pöschl 2000, a randomized, partially double-blind half-side comparison of a standardized German chamomile cream against 0.5% hydrocortisone and a placebo cream in atopic eczema. After 2 weeks the chamomile cream showed a mild superiority over 0.5% hydrocortisone but only a marginal difference from the placebo cream; the study came from the cream's maker. Unlike hydrocortisone, chamomile cream is not a steroid. The active anti-inflammatory components are alpha-bisabolol (the dominant sesquiterpenoid in chamomile essential oil, a direct skin-soothing terpene used widely in cosmetic preparations) and chamazulene (the deep-blue azulene pigment formed during steam distillation, a 5-lipoxygenase inhibitor that reduces leukotriene-mediated inflammation). Additional evidence supports topical chamomile for episiotomy wound healing, postpartum perineal care, and oral mucositis from chemotherapy and radiation, and chamomile has a long traditional use for minor diaper rash. Practitioners use it as a steroid-free option for chronic mild-to-moderate inflammatory skin conditions where long-term steroid use would be problematic.
Table of Contents
- The Topical Tradition (Standardized Creams, Roman vs German Chamomile)
- Alpha-Bisabolol: The Skin-Soothing Sesquiterpenoid
- Chamazulene: The Anti-Inflammatory Azulene Pigment
- The 1985 and 2000 Eczema Trials vs Hydrocortisone
- Episiotomy and Postpartum Perineal Wound Healing
- Oral Mucositis (Chemotherapy and Radiation)
- Diaper Rash and Pediatric Skin Care
- Wound Healing and Post-Surgical Use
- Topical Preparations and Application
- Cautions (Contact Dermatitis, Asteraceae Allergy)
- Key Research Papers
- Connections
- Featured Videos
The Topical Tradition (Standardized Creams, Roman vs German Chamomile)
The European topical-chamomile tradition is centuries deep. The standard German pharmaceutical preparation is a standardized chamomile cream, a 2% chamomile extract cream that has been a pharmacy-shelf staple in German-speaking Europe for decades. The British, French, Italian, and Eastern European pharmacopoeias each include analogous standardized preparations. In the US, chamomile-based cosmetic and over-the-counter (OTC) topical products are widespread but more variable in standardization and active content.
Two species are conflated in the common name "chamomile" and warrant distinction:
- German chamomile (Matricaria chamomilla, also M. recutita) — the higher-bisabolol, higher-chamazulene species used in nearly all clinical chamomile trials and in the standardized German creams. This is the chamomile referenced in essentially all of the topical evidence discussed below.
- Roman chamomile (Chamaemelum nobile) — lower bisabolol content, different essential-oil profile dominated by isobutyl angelate and methylallyl angelate. Used traditionally in English herbalism and as a perfume ingredient. Less clinical evidence as a topical anti-inflammatory.
When the herbal literature, the European Medicines Agency (EMA) monograph, the German Commission E, or modern clinical trials refer to topical chamomile, they essentially always mean German chamomile. The two species are not interchangeable for therapeutic purposes — Roman chamomile is more of a fragrance herb than a clinical anti-inflammatory.
Alpha-Bisabolol: The Skin-Soothing Sesquiterpenoid
Alpha-bisabolol is a monocyclic sesquiterpene alcohol, the dominant component of German chamomile essential oil (typically 25–65% of the oil, depending on chemotype and growing conditions). It is the principal anti-inflammatory and skin-soothing component for topical use. The pharmacology has been extensively characterized in dermatologic models:
- Direct anti-inflammatory effect via inhibition of inducible nitric oxide synthase (iNOS) and reduction of NF-kB-mediated cytokine production in keratinocytes
- Mast cell stabilization, reducing histamine release in allergic and irritant skin reactions
- Antibacterial activity against common skin pathogens including Staphylococcus aureus
- Penetration enhancement, allowing co-administered topical actives to reach deeper skin layers
- Direct skin barrier support — bisabolol has documented effects on keratinocyte differentiation and stratum corneum integrity
Bisabolol is so reliably skin-soothing that it has become a standard ingredient in commercial cosmetic and over-the-counter topical formulations, often synthesized rather than chamomile-extracted because synthetic bisabolol is purer and more consistent. The chamomile origin is incidental to the commercial use — bisabolol stands on its own pharmacology. When you see "bisabolol" on the ingredient label of a calming facial cream or a baby wash, the active is the same molecule that gives chamomile cream its clinical effect.
An important distinction in the bisabolol literature: German chamomile contains the natural (−)-alpha-bisabolol form (enantiomer), while a racemic mixture of both mirror-image forms is sold for some industrial applications. Some dermatologic preparations state that they use (−)-alpha-bisabolol.
Chamazulene: The Anti-Inflammatory Azulene Pigment
Chamazulene is the deep indigo-blue tricyclic azulene that gives German chamomile essential oil its famous inky-blue color. The molecule is unusual in plant chemistry — the parent terpene azulenes are deep blue rather than the green or colorless typical of other sesquiterpenes. Chamazulene is not present in the intact plant tissue; it forms during the steam-distillation process from the sesquiterpene lactone precursor matricin, which undergoes thermal rearrangement at distillation temperatures to release chamazulene.
The pharmacology:
- 5-Lipoxygenase inhibition, blocking conversion of arachidonic acid to leukotriene B4 (a key chemotactic and pro-inflammatory mediator in atopic dermatitis, psoriasis, and inflammatory skin disease)
- Antioxidant activity, scavenging reactive oxygen species at sites of inflammation
- Inhibition of neutrophil oxidative burst
- Direct anti-inflammatory effect in topical croton-oil and arachidonic-acid-induced ear edema mouse models
The combination of bisabolol (mast cell, NF-kB, iNOS) and chamazulene (5-lipoxygenase, leukotrienes, oxidative stress) hits at least two non-overlapping arms of the cutaneous inflammatory cascade. The synergy explains why whole-extract topical chamomile preparations outperform isolated single components in dermatologic models, and supports the traditional preference for whole-flower or whole-oil topical use rather than purified single-component cosmetic ingredients.
The 1985 and 2000 Eczema Trials vs Hydrocortisone
Atopic dermatitis (eczema) affects approximately 10% of children and 3% of adults in the developed world. The mainstay of pharmacologic management is topical corticosteroids, used in graduated potency from over-the-counter 0.5–1% hydrocortisone (low potency) up to prescription super-potent clobetasol. Topical steroids work, but chronic use carries meaningful risks: skin atrophy, telangiectasia, perioral dermatitis, tachyphylaxis, and hypothalamic-pituitary-adrenal-axis suppression with extensive use. This is why steroid-free creams have been studied.
Two German trials of a standardized chamomile-extract cream are often merged into one in summaries. They were separate studies with different designs and different results.
Aertgeerts and colleagues (1985) studied 161 patients with inflammatory skin disease on the hands, forearms and lower legs who had first been treated with a steroid cream (0.1% difluocortolone valerate). In a 3-to-4-week maintenance phase, each patient used a different cream on each side of the body: the chamomile cream against 0.25% hydrocortisone, 0.75% fluocortin butyl ester (another steroid) or 5% bufexamac (a non-steroidal anti-inflammatory cream). The chamomile cream worked about as well as 0.25% hydrocortisone and better than 5% bufexamac and 0.75% fluocortin butyl ester. This trial had no placebo cream.
Patzelt-Wenczler and Ponce-Pöschl (2000) ran a randomized, partially double-blind, half-side comparison in people with medium-degree atopic eczema. The abstract does not give the number of patients. The study came from the cream's maker: its first author was listed at the company. Design:
- Each patient applied a different topical treatment to each side of the body (right vs left limb)
- Treatment options compared: the chamomile cream, 0.5% hydrocortisone cream, and the vehicle cream (the same cream base without the extract) as placebo
- Duration: 2 weeks twice-daily application
- Outcome: dermatologist-rated severity score (erythema, edema, pruritus, lichenification, excoriation)
Results:
- After 2 weeks the chamomile cream showed a mild superiority over 0.5% hydrocortisone
- The difference between the chamomile cream and the placebo cream was only marginal
- The abstract does not report side effects
The interpretation needs some nuance: 0.5% hydrocortisone is the lowest-potency topical steroid, used for mild eczema only, and in the 2000 trial the chamomile cream did only marginally better than its own cream base. Results against low-dose hydrocortisone say nothing about the high-potency steroids used for severe disease. The appeal of chamomile cream for mild-to-moderate eczema is that it is not a steroid, so it does not carry the skin-thinning risk of long-term steroid use.
Practitioners who use chamomile cream describe it as a steroid-free option for chronic mild atopic dermatitis, particularly on the face (where topical steroid use is limited by skin thinning and eye complications) and for areas that need repeated treatment over weeks to months. In standard dermatology care, severe eczema flares are treated with high-potency topical steroids; chamomile is then described as a maintenance and steroid-sparing option during the taper. For more on the disease, see our Eczema page.
Episiotomy and Postpartum Perineal Wound Healing
Episiotomy and perineal lacerations are common complications of vaginal delivery, affecting a large majority of first-time mothers and a meaningful fraction of multiparous deliveries. Recovery is often painful and slow, and is complicated by the obligate exposure of the wound to urine and stool. Topical preparations that accelerate healing and reduce pain are clinically valuable in the postpartum period.
Several controlled trials have examined topical chamomile preparations for episiotomy and perineal wound healing in postpartum women. Aggregate findings:
- Chamomile ointment or sitz-bath application produces faster wound healing on the standardized REEDA (Redness, Edema, Ecchymosis, Discharge, Approximation) scale than no intervention or routine care alone
- Pain: in an Iranian triple-blind randomized controlled trial (2014, 114 first-time mothers), chamomile cream or a placebo cream was applied to the episiotomy stitches twice a day for 10 days. Pain scores did not differ at 12 hours or on day 1, but were lower with chamomile on days 7, 10 and 14 (McGill pain score on day 7: 11.36 versus 14.88 with placebo)
- No safety concerns in the postpartum perineal use context
The mechanism likely combines the bisabolol anti-inflammatory effect on damaged tissue, the chamazulene leukotriene-modulating effect on the local inflammatory response, modest antibacterial activity against perineal flora (reducing infection risk), and the warm-moist application's general physical benefit on wound closure.
Traditional practice: post-delivery sitz baths with strong chamomile tea infusion (1 cup dried chamomile flowers infused in 4 cups boiling water for 15 minutes, then strained and added to a basin of warm bath water), taken two to three times daily for the first one to two weeks postpartum. Pre-made chamomile sitz-bath sachets are also sold by herbal-pharmacy retailers, and cream is often applied after the sitz bath.
Oral Mucositis (Chemotherapy and Radiation)
Oral mucositis — severe inflammation and ulceration of the oral mucosa — is one of the most distressing toxicities of cancer chemotherapy and head-and-neck radiation therapy. Severe oral mucositis can require parenteral nutrition, opioid pain management, and treatment dose reduction. The conventional management includes meticulous oral hygiene, ice chip prophylaxis, and a variety of topical agents (lidocaine, sucralfate suspension, "magic mouthwash" combinations).
Chamomile mouthwash has been studied as an adjunct for chemotherapy and radiation oral mucositis with mixed but generally encouraging results:
- A 2024 network meta-analysis of 36 randomized controlled trials (RCTs; 2,083 patients) of natural products found that chamomile, along with honey, propolis and the plantain Plantago major, significantly reduced how often oral mucositis developed during cancer therapy
- A 2023 systematic review of 18 studies (1,099 cancer patients; 15 randomized) found that chamomile mouthwash, topical forms and teas reduced oral mucositis, skin complications, vomiting and depression. The studies were too varied to combine in a meta-analysis
- A 2005 case report describes one patient with rheumatoid arthritis whose mouth sores from methotrexate cleared with wild chamomile mouthwashes
- The mechanism is the same bisabolol + chamazulene anti-inflammatory pair, applied topically to the inflamed oral mucosa
- Tolerability is generally excellent — chamomile mouthwash is much better tolerated than alcohol-based mouthwashes or hydrogen peroxide
- The largest single trial was negative: in a Phase III, double-blind, placebo-controlled trial (Fidler and colleagues, 1996), 164 evaluable patients starting 5-fluorouracil (5-FU) chemotherapy, all also given oral cryotherapy (ice chips), used a chamomile or placebo mouthwash three times daily for 14 days. There was no suggestion of any difference in mouth sores (stomatitis) between the groups, and no sign of toxicity
Where chamomile mouthwash is used, it is used as a low-cost add-on to standard oral mucositis care, not in place of ice-chip cooling during high-dose chemotherapy, a dental check before head-and-neck radiation, or opioid pain medicines for severe established mucositis. Standardized preparations or freshly brewed strong chamomile tea, swished and spat three to five times daily, are the typical application.
Diaper Rash and Pediatric Skin Care
Chamomile-containing baby washes and creams have a long European tradition for routine pediatric skin care and for diaper rash. The evidence here is traditional and practical rather than from trials:
- Chamomile cream is traditionally applied to mild-to-moderate diaper rash, and parents and practitioners report that the rash clears faster
- Severe diaper rash with a yeast infection (secondary candidiasis) is treated with antifungal medicine (clotrimazole, nystatin) in standard care; chamomile does not treat the yeast
- Severe diaper rash with a bacterial infection on top is treated with a topical antibiotic in standard care
- Traditionally, chamomile is used as a routine preventive application and for uncomplicated mild diaper rash
The main reported risk of topical chamomile in children is allergy: infants and children with known or suspected Asteraceae (daisy-family) allergy can react to it. The atopic-dermatitis context is particularly relevant — children with eczema are at elevated risk of cross-sensitization to topical herbal allergens including chamomile. A patch test on a small area is the traditional check when a child has any history of atopic disease.
Pediatric chamomile bath is a centuries-old European tradition for calming fussy babies and treating mild skin irritation. The traditional method adds one cup of strong chamomile tea infusion to the bath water. The fragrance has a calming effect on caregivers as well, which is not a trivial benefit during a difficult bedtime.
Wound Healing and Post-Surgical Use
Beyond episiotomy, topical chamomile has been studied in a variety of wound-healing contexts:
- Weeping skin wounds — in a 1987 German double-blind study of 14 patients with weeping wounds after tattoo removal by dermabrasion, chamomile extract shrank the weeping wound area and dried it faster; both effects were statistically significant
- Post-cesarean section wound healing — topical chamomile is traditionally applied to the C-section incision after the dressing is removed, and users report faster closure and a less visible scar
- Hemorrhoid topical use — chamomile sitz baths or cream application reduce pain and pruritus of external hemorrhoids and post-hemorrhoidectomy wounds
- Phlebitis at intravenous (IV) cannula sites — in an Iranian double-blind randomized controlled trial (2017), 40 coronary-care patients receiving the heart drug amiodarone through a vein in the arm had chamomile ointment or a lanolin placebo rubbed above the cannula every 8 hours for 3 days. Vein inflammation (phlebitis) developed in 15 of 20 patients with chamomile versus all 20 with placebo, and it appeared later (relative risk 0.68). The severity of the phlebitis did not differ significantly between the groups
- Pressure ulcers (decubitus) — preliminary evidence supports topical chamomile as an adjunct in stage I-II pressure ulcer care, in combination with standard pressure relief and nutritional support. Not adequate as primary treatment for stage III-IV ulcers
- Burns — chamomile preparations have traditional use for minor first-degree burns (sunburn, minor thermal burns). Aloe vera has stronger evidence in this setting. Chamomile is also used as a second option or in combination
The mechanism across these wound contexts is consistent: the bisabolol-chamazulene anti-inflammatory pair, modest antibacterial activity reducing wound bioburden, mucosal-barrier and keratinocyte support during re-epithelialization. The effect is supportive rather than dramatic; chamomile is a useful adjunct, not a substitute for primary wound care.
Topical Preparations and Application
- Standardized chamomile cream (2% standardized extract) — the type of product tested in the German eczema trials. It is applied thinly to the affected area two to three times daily. Pharmacy-shelf product in German-speaking Europe; mail-order in US.
- Generic chamomile creams (US OTC) — widely available but variable in active content. Some products state their bisabolol concentration or standardized extract content; many do not.
- Strong tea infusion as compress or sitz bath — 1 cup dried chamomile flowers steeped in 4 cups just-boiled water for 15 minutes covered, then strained. It is applied as a warm compress to affected skin, added to a sitz-bath basin for perineal indications, or used as a mouthwash for mouth sores (stomatitis).
- Essential oil dilution — 1–3 drops German chamomile essential oil per teaspoon of carrier oil (jojoba, sweet almond, fractionated coconut). The dilution is applied to the affected area. Undiluted essential oil on the skin carries a meaningful risk of sensitization.
- Tincture — 1:5 in 40% alcohol, applied diluted 1:10 in water as a topical wash for inflamed skin. The alcohol content is drying and not appropriate for chronic eczema use; suits transient acute inflammation.
- Combination products — chamomile is commonly combined with calendula, lavender, and aloe vera in commercial topical preparations. Each adds complementary anti-inflammatory or wound-healing activity. See our Calendula page and Lavender page.
The usual check with any new chamomile topical is a patch test on the inner forearm before larger areas are covered: a small amount is applied, left for 24 hours, and the skin is checked for redness, itching or rash. People with atopic disease or known plant allergies are the ones most likely to react.
Cautions (Contact Dermatitis, Asteraceae Allergy)
- Asteraceae allergy and contact dermatitis — the single most important safety concern with topical chamomile. Patients with known ragweed, daisy, or chrysanthemum allergy are at elevated risk of cross-reactivity. Chamomile contact dermatitis is well-documented in dermatologic literature, particularly with high-concentration essential oil exposure. A patch test shows a reaction before extensive use.
- Photosensitization (rare) — isolated case reports of chamomile-associated phototoxic reactions, mostly with essential oil application. Not a major clinical concern at typical cream concentrations.
- Periorbital application — the eyelids and the skin near the eye are sensitive to direct application. A diluted compress for blepharitis or stye is traditional and generally safe; eye irritation is the sign that it is not suiting the person.
- Open wound application — standardized chamomile creams are generally safe on minor wounds. Essential oil and alcoholic tincture on open wounds carry a risk of irritation and sensitization.
- Pregnancy (topical) — topical chamomile is generally considered safe in pregnancy at standard concentrations. Herbal references traditionally caution against essential oil use in early pregnancy.
- Pediatric — topical chamomile has long traditional safe use in infants and children, but atopic children have a higher risk of contact sensitization; a patch test is the traditional check before broader use.
- Not a substitute for diagnosis of skin disease — new-onset rash, lesions that are not resolving, lesions with unusual features (asymmetric pigmented lesions, ulceration without clear cause, bleeding), or symptoms in the whole body are signs that dermatologists treat as needing examination. Chamomile is used for known inflammatory skin conditions, not for unexplained worrying lesions.
Key Research Papers
- Patzelt-Wenczler R, Ponce-Pöschl E (2000). Proof of efficacy of Kamillosan(R) cream in atopic eczema. European Journal of Medical Research, 5(4):171-175. — PubMed PMID: 10799352
- Albring M, Albrecht H, Alcorn G, Lücker PW (1983). The measuring of the antiinflammatory effect of a compound on the skin of volunteers. Methods and Findings in Experimental and Clinical Pharmacology, 5(8):575-577. — PubMed PMID: 6664158
- Glowania HJ, Raulin C, Swöboda M (1987). Effect of chamomile on wound healing — a clinical double-blind study. Z Hautkr, 62(17):1262, 1267-1271. — PubMed PMID: 3318194
- Mazokopakis EE et al. (2005). Wild chamomile (Matricaria recutita L.) mouthwashes in methotrexate-induced oral mucositis. Phytomedicine, 12(1-2):25-27. (A single case report.) — PubMed PMID: 15693704
- Fidler P et al. (1996). Prospective evaluation of a chamomile mouthwash for prevention of 5-FU-induced oral mucositis. Cancer, 77(3):522-525. — PubMed PMID: 8630960
- Reuter J, Jocher A, Stump J, Grossjohann B, Franke G, Schempp CM (2008). Investigation of the anti-inflammatory potential of Aloe vera gel (97.5%) in the ultraviolet erythema test. Skin Pharmacology and Physiology, 21(2):106-110. (An aloe vera study; it did not test chamomile.) — PubMed PMID: 18253066
- Kamatou GPP, Viljoen AM (2010). A review of the application and pharmacological properties of alpha-bisabolol and alpha-bisabolol-rich oils. Journal of the American Oil Chemists' Society, 87:1-7. — doi:10.1007/s11746-009-1483-3
- Safayhi H et al. (1994). Chamazulene: an antioxidant-type inhibitor of leukotriene B4 formation. Planta Medica, 60(5):410-413. — PubMed PMID: 7997466
- Srivastava JK, Shankar E, Gupta S (2010). Chamomile: A herbal medicine of the past with bright future. Molecular Medicine Reports, 3(6):895-901. — PubMed PMID: 21132119
- Aertgeerts P, Albring M, Klaschka F, Nasemann T, Patzelt-Wenczler R, Rauhut K, Weigl B (1985). Comparative testing of Kamillosan cream and steroidal (0.25% hydrocortisone, 0.75% fluocortin butyl ester) and non-steroidal (5% bufexamac) dermatologic agents in maintenance therapy of eczematous diseases. Z Hautkr, 60(3):270-277. — PubMed PMID: 3158124
- Aradmehr M, Azhari S, Ahmadi S, Azmoude E (2017). The effect of chamomile cream on episiotomy pain in primiparous women: a randomized clinical trial. Journal of Caring Sciences, 6(1):19-28. — PubMed PMID: 28299294
- Sharifi-Ardani M, Yekefallah L, Asefzadeh S, Nassiri-Asl M (2017). Efficacy of topical chamomile on the incidence of phlebitis due to an amiodarone infusion in coronary care patients: a double-blind, randomized controlled trial. Journal of Integrative Medicine, 15(5):373-378. — PubMed PMID: 28844214
- Maleki M, Mardani A, Manouchehri M, Ashghali Farahani M, Vaismoradi M, Glarcher M (2023). Effect of chamomile on the complications of cancer: a systematic review. Integrative Cancer Therapies, 22:15347354231164600. — PubMed PMID: 37052390
- Lee CC, Chen YW, Kang YN, Chen JH, Chen C, Lu CY, Huang TW, Gautama MSN (2024). Efficacy of natural products in preventing oral mucositis resulting from cancer therapies: a network meta-analysis of randomized controlled trials. Critical Reviews in Oncology/Hematology, 199:104373. — PubMed PMID: 38710295