Chamomile for Sleep Quality
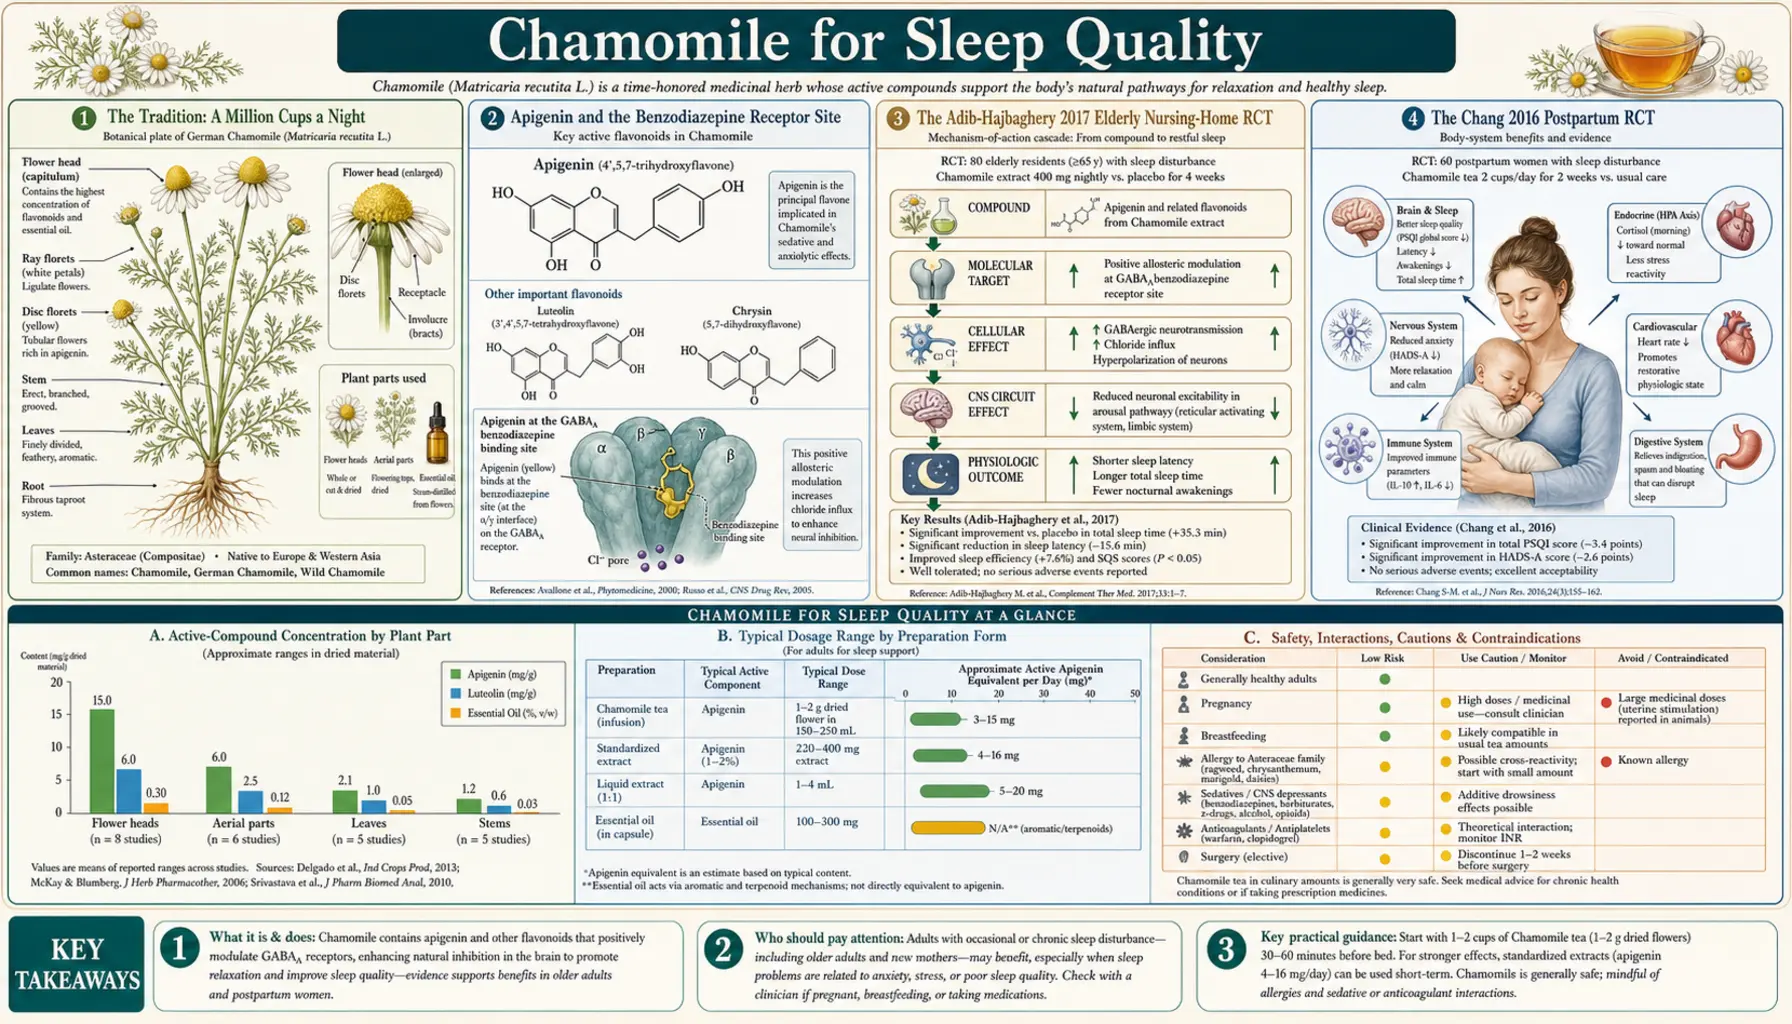
A nighttime cup of chamomile tea is the most widely practiced herbal sleep ritual on Earth — the centuries-old folk medicine endorsement of Matricaria chamomilla as a gentle sleep aid is shared across European, Mediterranean, North African, and Latin American cultures. Modern pharmacology has now identified the molecular basis: the flavonoid apigenin binds the benzodiazepine-recognition site on the gamma-aminobutyric acid-A receptor with measurable, low-micromolar affinity, producing a mild anxiolytic and sleep-promoting effect without the dependency, tolerance, cognitive impairment, or morning hangover of pharmaceutical benzodiazepines. Three randomized controlled trials have tested it. Adib-Hajbaghery 2017 in elderly nursing-home residents (Pittsburgh Sleep Quality Index) and Chang 2016 in sleep-disturbed postpartum women (Postpartum Sleep Quality Scale) reported significant improvements; Zick 2011 in adults with chronic primary insomnia found no significant difference from placebo on sleep-diary measures. Chamomile is often compared with over-the-counter (OTC) antihistamine sleep aids (diphenhydramine, doxylamine), which carry a substantial anticholinergic side-effect burden, and with prescription hypnotics, which carry dependency potential.
Table of Contents
- The Tradition: A Million Cups a Day
- Apigenin and the Benzodiazepine Receptor Site
- The Adib-Hajbaghery 2017 Elderly Nursing-Home Randomized Controlled Trial
- The Chang 2016 Postpartum Randomized Controlled Trial
- The Zick 2011 Chronic Insomnia Randomized Controlled Trial
- Chamomile vs Over-the-Counter Sleep Aids (Diphenhydramine, Doxylamine, Melatonin)
- Chamomile vs Prescription Hypnotics (Benzodiazepines, Z-Drugs)
- Preparation and Dose (Tea, Standardized Extract, Tincture)
- Timing, Stacking, and Sleep-Hygiene Pairing
- Cautions and Interactions
- Key Research Papers
- Connections
- Featured Videos
The Tradition: A Million Cups a Day
Chamomile is the most-consumed single-ingredient herbal tea on the planet. A 2010 review by Srivastava, Shankar and Gupta describes chamomile herbal tea as consumed at more than one million cups per day. The historical record reaches back at least to the ancient Egyptians, who dedicated chamomile to the sun god Ra for fevers; through the Greeks (who called it chamaimelon, "ground apple," for the apple-like aroma of the bruised flower head); through Dioscorides and the medieval European herbalists; through Peter Rabbit, whose mother gave him chamomile tea after his Mr. McGregor escapade because she knew, as every European grandmother knew, that it would settle his nerves and put him to sleep.
The folk-medicine endorsement is unusually consistent across cultures. Spanish manzanilla, Italian camomilla, German Kamille, French camomille, Arabic babunaj, Mexican manzanilla — everywhere the plant grows, the same evening cup for the same indications. When a folk indication is reproduced across cultures that did not share information, that is non-trivial epidemiologic evidence that there is a real underlying effect being detected by ordinary people in ordinary settings.
Modern pharmacology has confirmed that intuition. The question is no longer whether chamomile produces a measurable nighttime calming effect — it does — but how it does so, how big the effect is, and how it stacks against the alternatives a sleep-deprived adult in 2026 actually has in front of them at the drugstore. For broader sleep strategy and non-pharmacologic context, see our Sleep Hygiene page.
Apigenin and the Benzodiazepine Receptor Site
The gamma-aminobutyric acid-A receptor is the principal inhibitory neurotransmitter receptor in the brain. When the inhibitory neurotransmitter gamma-aminobutyric acid (GABA) binds gamma-aminobutyric acid-A, the receptor opens a chloride channel, hyperpolarizing the neuron and reducing its firing probability. This is the single most important "brake" on neural activity in the central nervous system.
The receptor has multiple modulatory sites in addition to the principal gamma-aminobutyric acid-binding site. The most clinically important is the benzodiazepine-recognition site, located at the interface of the alpha and gamma subunits. Drugs that bind here do not open the chloride channel directly — they amplify the effect of endogenous gamma-aminobutyric acid, making the receptor more responsive to whatever gamma-aminobutyric acid happens to be in the synaptic cleft. This is the mechanism of diazepam, alprazolam, lorazepam, clonazepam, and the entire benzodiazepine class. It is also the mechanism of the so-called "Z-drugs" — zolpidem, zaleplon, and eszopiclone — which bind a different subset of gamma-aminobutyric acid-A receptor subunits but at the same general allosteric site.
Apigenin, the principal flavonoid of chamomile, binds the benzodiazepine site with measurable affinity. The classic Viola et al. demonstration in 1995 showed that apigenin displaces tritiated flunitrazepam from rat cortical membranes with a Ki in the low micromolar range. This is dramatically weaker affinity than a pharmaceutical benzodiazepine — diazepam binds in the low nanomolar range, roughly a thousand-fold tighter — but it is real binding, and it is reproducible across laboratories.
The functional consequence appears to be partial agonism rather than full agonism. Apigenin produces measurable anxiolytic effects in standard rodent models (elevated plus maze, light-dark box) at doses below the threshold for sedation, motor incoordination, or muscle relaxation. Higher doses do produce mild sedation but never the deep sedation or anterograde amnesia of pharmaceutical benzodiazepines, even at orders-of-magnitude higher exposure. This profile — mild anxiolytic and sleep-promoting effects without the deeper benzodiazepine pharmacology — is exactly what the clinical chamomile randomized controlled trials (RCTs) report. The molecular mechanism predicts the clinical effect; the clinical effect validates the molecular mechanism.
One important detail: most of the apigenin in dried chamomile flowers is present as the 7-O-glucoside or related glycosides. The glycosides are hydrolyzed to the aglycone in the small intestine and by colonic bacteria. The aglycone is the form that crosses the blood-brain barrier and binds the receptor. Bioavailability is modest (5–15% depending on preparation) but reproducible, and the slow conversion in the gut produces a sustained-release pharmacokinetic profile that suits a nighttime sleep aid.
The Adib-Hajbaghery 2017 Elderly Nursing-Home Randomized Controlled Trial
Sleep complaints in elderly nursing-home residents are extraordinarily common — surveys consistently report that 50–70% of long-term-care residents report clinically meaningful insomnia. The clinical response to this is unfortunately often a benzodiazepine or Z-drug prescription, both of which are on the Beers Criteria list of medications to avoid in the elderly because of their well-documented increase in fall risk, fracture risk, and confusion. A safer alternative is badly needed.
Adib-Hajbaghery and Mousavi (2017) conducted a single-blind randomized controlled trial in 60 people aged 60 or older at a day-care nursing home in Karaj, Iran, randomized to either chamomile extract capsules (200 mg) twice daily for 28 days, or wheat-flour capsules (200 mg) as the control. Sleep quality was measured with the Pittsburgh Sleep Quality Index (PSQI) total score, a 19-item validated instrument that captures sleep duration, latency, efficiency, disturbances, daytime dysfunction, and use of sleep medication.
- At baseline, sleep quality was low in both groups, with no statistically significant between-group difference (P=0.639)
- After the intervention, sleep quality in the chamomile group was significantly better than in the control group (P<0.05)
- The authors concluded that chamomile extract “can significantly improve sleep quality among elderly people”
The trial was small and single-blind, and its abstract does not give the size of the PSQI change. In older adults the comparison that matters is with benzodiazepines and Z-drugs, which the Beers Criteria list because of their link to falls, fractures and confusion.
The Chang 2016 Postpartum Randomized Controlled Trial
Postpartum sleep disturbance is nearly universal and often accompanied by depressive symptoms. The conventional pharmacologic options (benzodiazepines, antihistamines, antidepressants) are complicated by breastfeeding, where any sedating medication transfers into breast milk to some degree and can produce drowsiness in the nursing infant. A non-pharmacologic or minimally pharmacologic option that does not contraindicate breastfeeding is badly needed.
Chang and Chen (2016) randomized 80 Taiwanese postpartum women with poor sleep quality to either chamomile tea for 2 weeks, or routine postpartum care alone. The outcome measures were the Postpartum Sleep Quality Scale (PSQS), the Edinburgh Postnatal Depression Scale (EPDS) and the Postpartum Fatigue Scale.
- Compared with the control group, the chamomile-tea group had significantly lower scores for physical-symptoms-related sleep inefficiency (a PSQS subscale, P=0.015) and for symptoms of depression (P=0.020)
- At the 4-week post-test the scores for all three instruments were similar in both groups, which the authors read as the effect being limited to the immediate term
- No adverse events were reported in either mothers or breastfeeding infants
The transient nature of the benefit (lost when use stops) is consistent with a mild pharmacologic effect rather than a disease-modifying one — chamomile is not curing postpartum depression, it is producing a temporary sleep and mood improvement while consumed. That is, however, exactly what is needed in the early postpartum period: gentle help bridging the most sleep-deprived months without committing to a medication that complicates breastfeeding.
Chamomile is generally regarded as safe in breastfeeding by lactation pharmacology references, with the caveat that high-concentration extracts (capsules at hundreds of milligrams) have less safety data in lactation than the tea preparation used in this trial. The tea is the preparation that was studied in these postpartum mothers. For more on postpartum support, see our Postpartum Depression page, and the Sleep Hygiene framework.
The Zick 2011 Chronic Insomnia Randomized Controlled Trial
Chronic primary insomnia — insomnia not attributable to a medical, psychiatric, or environmental cause and lasting more than three months — affects approximately 10% of adults. The first-line management is cognitive behavioural therapy for insomnia (CBT-I), but access barriers (cost, time, available therapists) often push patients toward pharmacologic options. Chamomile would be welcome as a low-risk adjunct.
Zick and colleagues (2011) at the University of Michigan conducted a preliminary efficacy and safety trial of standardized chamomile extract in 34 adults with chronic primary insomnia of at least six months, defined by the Diagnostic and Statistical Manual of Mental Disorders, Fourth Edition (DSM-IV). Participants were randomized to either 270 mg of a standardized chamomile extract (90 mg tablets with at least 2.5 mg apigenin) twice daily for 28 days, or matched placebo. Outcome measures were sleep diary parameters and validated instruments.
- There were no significant differences between groups in changes in sleep-diary measures, including total sleep time, sleep efficiency and sleep latency; sleep latency showed a moderate effect size in favour of chamomile, while total sleep time showed a moderate effect size in favour of placebo
- Chamomile showed a modest advantage on daytime functioning that did not reach statistical significance; there were no significant group effects on the Insomnia Severity Index (p = 0.44) or the Pittsburgh Sleep Quality Index total score (p = 0.79)
- Adverse events did not differ between the chamomile and placebo groups
Zick et al. concluded that chamomile “could provide modest benefits of daytime functioning and mixed benefits on sleep diary measures relative to placebo” in adults with chronic primary insomnia, and that further studies would be needed.
Chamomile vs Over-the-Counter Sleep Aids (Diphenhydramine, Doxylamine, Melatonin)
For an adult at the drugstore at 10 PM looking at a sleepless night, the practical comparator for chamomile is the over-the-counter sleep aid shelf. The major options:
- Diphenhydramine — the first-generation antihistamine in nearly all over-the-counter sleep aids. Strongly anticholinergic. Produces meaningful sedation, but at substantial cost: anticholinergic side effects (dry mouth, constipation, urinary retention, blurred vision), morning grogginess and impaired psychomotor performance the following day, and accumulating evidence that chronic anticholinergic use in older adults raises dementia risk (Gray et al. JAMA Internal Medicine 2015). Beers Criteria flags diphenhydramine as a medication to avoid in elderly.
- Doxylamine — another first-generation antihistamine, even more strongly sedating than diphenhydramine. Same anticholinergic burden and morning grogginess issues. Suitable for occasional use; problematic for chronic use.
- Melatonin — sold over-the-counter in the US (prescription-only in most other countries). Most useful for circadian phase shifting (jet lag, shift work, delayed sleep phase syndrome). Modest effect on sleep maintenance insomnia. Overdosing is common because consumers do not realize that physiologic doses (0.3–0.5 mg) are typically as effective as the 5–10 mg doses commercially sold. Generally safe but with some interaction with autoimmune disease and pregnancy.
- Valerian extract — another gamma-aminobutyric acid-A modulating herb. Modest sleep-onset benefit in meta-analyses. Strong, unpleasant odor that limits compliance. See our Valerian page.
Chamomile's practical advantages: no anticholinergic burden, no morning grogginess, no dementia signal, generally well-tolerated, available either as tea (most flexible dosing, slowest onset) or standardized capsule (more reproducible, faster onset). The disadvantage: smaller average effect size than diphenhydramine. The right comparator framework is "Beers-Criteria-safe alternative with measurable benefit," not "match a sedating antihistamine on knockout potency."
Chamomile vs Prescription Hypnotics (Benzodiazepines, Z-Drugs)
Prescription hypnotics — benzodiazepines (temazepam, lorazepam, alprazolam) and Z-drugs (zolpidem, eszopiclone, zaleplon) — produce dramatically larger acute effects on sleep than chamomile or any over-the-counter option. They also carry dramatically larger risks:
- Tolerance develops within weeks for the sleep-onset benefit, requiring escalating doses
- Physical dependency develops, with withdrawal insomnia that can be worse than the original baseline
- Rebound anxiety on discontinuation
- Anterograde amnesia and unusual sleep behaviors (sleep-driving, sleep-eating, especially with zolpidem)
- Increased fall and fracture risk, especially in older adults
- Mortality signals in observational data with chronic use (controversial but persistent in the literature)
The clinical positioning of chamomile relative to prescription hypnotics is straightforward: chamomile is not a substitute for prescription hypnotics in severe insomnia. Practitioners describe it as something tried before prescription medicines, as an adjunct alongside them, and as gentle nighttime support after cognitive behavioural therapy for insomnia has resolved the acute insomnia, without a controlled substance.
For prescription benzodiazepine and Z-drug users actively trying to taper, the typical clinical approach is to introduce chamomile (and other gentle GABAergic herbs like lemon balm and valerian, plus melatonin for circadian support, plus aggressive sleep hygiene) early in the taper as part of the supportive scaffolding. None of these is as potent as the drug being tapered, but together they take the edge off withdrawal insomnia and rebound anxiety.
Preparation and Dose (Tea, Standardized Extract, Tincture)
- Tea (the traditional preparation, lowest dose, most flexible) — one or two teaspoons of dried chamomile flowers (or 1–2 tea bags) per cup of just-boiled water, steeped 10–15 minutes with the cup covered to retain the volatile essential-oil terpenoids. Loose-leaf chamomile from a bulk-herb supplier is typically higher quality than mass-market tea bags. One to three cups per evening for sleep. For children, practitioners describe half-strength tea, half a cup.
- Standardized extract (capsule, most reproducible) — the form used in two of the three trials above: the Zick trial used 270 mg twice daily of an extract in 90 mg tablets with at least 2.5 mg apigenin each, and the Adib-Hajbaghery trial used 200 mg capsules twice daily. Herbal practice describes 220–540 mg one hour before bed, and up to 1100 mg/day in divided doses.
- Tincture (alcoholic or glycerite) — 1:5 strength in 25% alcohol, dosed at 1–3 mL one hour before bed. Glycerite preparations are alcohol-free and are used for children and for people avoiding alcohol.
- Essential oil — used on the skin, not by mouth. Chamomile essential oil is used topically and in aromatherapy diffusers. Swallowed essential oil falls outside the safety profile of the whole-plant preparation.
The single most common preparation mistake is steeping the tea uncovered for 3–5 minutes, like a regular black tea. The active volatile terpenoids (bisabolol, chamazulene) and a fraction of the apigenin escape with the steam. A covered cup or a teapot with a lid, and at least 10 minutes of steeping, keep more of them in the tea.
Timing, Stacking, and Sleep-Hygiene Pairing
Timing matters. The apigenin glycosides require gut hydrolysis to release the active aglycone, which then needs to cross the blood-brain barrier. Realistic onset is 30–60 minutes after the tea or capsule. On that timing, tea drunk at lights-out acts late, and a window of 45–90 minutes before intended sleep is commonly described.
Stacking with other gentle nighttime herbs is traditional. Common combinations:
- Chamomile + lemon balm — lemon balm (Melissa officinalis) also has gentle GABAergic activity, plus a pleasant lemon-citrus flavor that complements chamomile. See our Lemon Balm page.
- Chamomile + passionflower — passionflower (Passiflora incarnata) modulates gamma-aminobutyric acid through a different mechanism, mostly via direct gamma-aminobutyric acid-receptor binding rather than the benzodiazepine site. The combination is widely sold as a sleep tea blend.
- Chamomile + magnesium glycinate — magnesium is a separate GABAergic modulator at the N-methyl-D-aspartate (NMDA) receptor. Glycine (the carrier amino acid in magnesium glycinate) is itself an inhibitory neurotransmitter at spinal and brainstem glycine receptors. See our Magnesium Glycinate page.
- Chamomile + L-theanine + glycine — the "alpha-wave plus inhibitory amino acid" stack popular among biohacker / sleep-tracking enthusiasts.
Stacking with melatonin (for circadian phase shifting) and with valerian (for sleep-onset latency in severe insomnia) is also common. The combinations are additive in effect; none are synergistic to a degree that would replace prescription hypnotics in true severe insomnia, but for mild-to-moderate complaints they substantially reduce the perceived need for pharmaceutical options.
Sleep-hygiene measures commonly paired with it: a consistent sleep schedule, a cool bedroom (65–68°F), less blue light for 1–2 hours before bed, and no caffeine after noon. See our full Sleep Hygiene framework for the underlying behavioral foundation that any nighttime herb is meant to support, not replace.
Cautions and Interactions
- Asteraceae family allergy — chamomile is in the daisy/aster family (Asteraceae, also called Compositae) along with ragweed, daisy, marigold, and chrysanthemum. Individuals with documented ragweed allergy may cross-react to chamomile. Rare anaphylaxis has been reported. People with a known Asteraceae allergy are the group these reactions concern.
- Anticoagulant interaction (theoretical) — chamomile contains small amounts of coumarin derivatives. The clinical magnitude of warfarin interaction is debated and probably small, but case reports exist: a 2006 report described a 70-year-old woman on warfarin who was admitted to hospital with multiple internal bleeds after using chamomile tea and body lotion (PubMed PMID: 16636327).
- Pregnancy — small amounts of chamomile tea are widely consumed in pregnancy without apparent harm, but there is little safety data on high-dose extracts and chamomile essential oil. Some sources list chamomile as a uterine stimulant in concentrated form. Herbal references generally treat moderate tea use as acceptable and do not extend that to standardized extract capsules.
- Sedation with other central nervous system (CNS) depressants — modest additive sedation with benzodiazepines, opioids, alcohol, and prescription hypnotics. Not a contraindication at typical doses but worth noting if multiple sedating substances are stacked.
- Cyclosporine and cytochrome P450 3A4 (CYP3A4) substrates — apigenin is a weak cytochrome P450 3A4 inhibitor in vitro. Clinical magnitude is probably small at typical chamomile doses; the concern is greatest with high-dose standardized extracts in people taking narrow-therapeutic-index cytochrome P450 3A4 substrates such as cyclosporine.
- Underlying causes of chronic insomnia — chronic insomnia (more than 3 months) can be caused by sleep apnea, restless legs syndrome, depression, thyroid disease, and other treatable conditions, which chamomile does not treat.
Key Research Papers
- Adib-Hajbaghery M, Mousavi SN (2017). The effects of chamomile extract on sleep quality among elderly people: A clinical trial. Complementary Therapies in Medicine, 35:109-114. — PubMed PMID: 29154054
- Chang SM, Chen CH (2016). Effects of an intervention with drinking chamomile tea on sleep quality and depression in sleep disturbed postnatal women: a randomized controlled trial. Journal of Advanced Nursing, 72(2):306-315. — PubMed PMID: 26483209
- Zick SM et al. (2011). Preliminary examination of the efficacy and safety of a standardized chamomile extract for chronic primary insomnia: a randomized placebo-controlled pilot study. BMC Complementary and Alternative Medicine, 11:78. — PubMed PMID: 21939549
- Viola H et al. (1995). Apigenin, a component of Matricaria recutita flowers, is a central benzodiazepine receptors-ligand with anxiolytic effects. Planta Medica, 61(3):213-216. — PubMed PMID: 7617761
- Salehi B et al. (2019). The therapeutic potential of apigenin. International Journal of Molecular Sciences, 20(6):1305. — PubMed PMID: 30875872
- Avallone R et al. (2000). Pharmacological profile of apigenin, a flavonoid isolated from Matricaria chamomilla. Biochemical Pharmacology, 59(11):1387-1394. — PubMed PMID: 10751547
- Srivastava JK, Shankar E, Gupta S (2010). Chamomile: A herbal medicine of the past with bright future. Molecular Medicine Reports, 3(6):895-901. — PubMed PMID: 21132119
- Hieu TH et al. (2019). Therapeutic efficacy and safety of chamomile for state anxiety, generalized anxiety disorder, insomnia, and sleep quality: A systematic review and meta-analysis. Phytotherapy Research, 33(6):1604-1615. — PubMed PMID: 31006899
- Miraj S, Alesaeidi S (2016). A systematic review study of therapeutic effects of Matricaria recutita chamomile. Electronic Physician, 8(9):3024-3031. — PubMed PMID: 27790360
- McKay DL, Blumberg JB (2006). A review of the bioactivity and potential health benefits of chamomile tea (Matricaria recutita L.) Phytotherapy Research, 20(7):519-530. — PubMed PMID: 16628544
- Gray SL et al. (2015). Cumulative use of strong anticholinergics and incident dementia: a prospective cohort study. JAMA Internal Medicine, 175(3):401-407. — PubMed PMID: 25621434