⚠ Evidence warning: Clinical trials or other evidence do not support the claims that chamomile and apigenin do not produce dependency or withdrawal, carry no respiratory-depression risk and do not interact dangerously with other central nervous system depressants, or that chamomile with other supplements eases withdrawal during benzodiazepine tapers. This page keeps it as a report of what people, websites or other media say.
Chamomile for Anxiety Relief
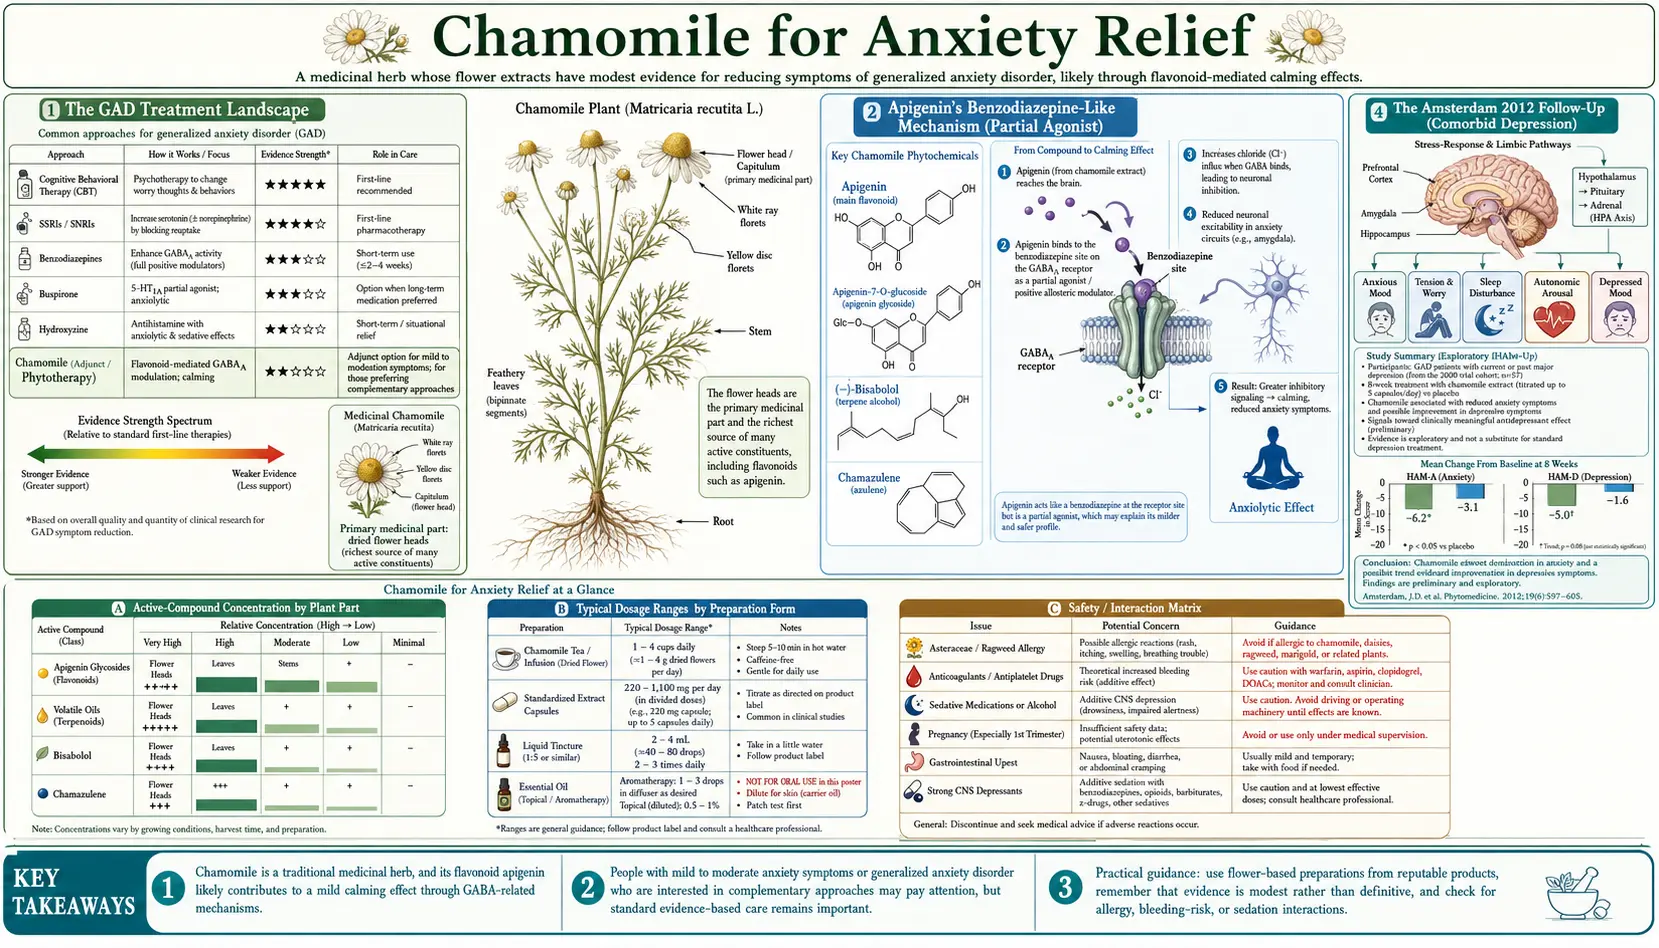
Generalized anxiety disorder (GAD) is the most common anxiety disorder, affecting approximately 3% of the adult population in any given year. The first-line pharmacologic options — selective serotonin reuptake inhibitors (SSRIs)/serotonin-norepinephrine reuptake inhibitors (SNRIs) and benzodiazepines — each carry meaningful trade-offs (slow onset and side-effect burden for selective serotonin reuptake inhibitors; tolerance and dependency for benzodiazepines). Chamomile occupies a unique evidence-based middle ground: the Amsterdam et al. 2009 randomized double-blind placebo-controlled trial of standardized chamomile extract (220–1100 mg/day, 1.2% apigenin) in DSM-IV-defined GAD found a significantly greater reduction in Hamilton Anxiety Rating Scale (HAM-A) scores than placebo (P = 0.047), which its authors described as “modest anxiolytic activity.” The 2012 Amsterdam follow-up examined comorbid depression. A 2016 open-label study of 179 people with moderate-to-severe GAD reported a response rate “comparable to those observed during conventional anxiolytic drug therapy,” and its authors wrote that future comparative trials between chamomile and conventional drugs may help determine the balance of risks and benefits. In laboratory and mouse studies, chamomile's flavonoid apigenin binds the benzodiazepine site of the gamma-aminobutyric acid-A (GABA-A) receptor and reduced anxiety-like behaviour in mice, but a study in rats found no anti-anxiety effect from apigenin; how chamomile acts in people has not been established.
Table of Contents
- The GAD Treatment Landscape
- Apigenin and the Benzodiazepine Site (Animal and Cell Studies)
- The Amsterdam 2009 GAD Trial
- The Amsterdam 2012 Follow-Up (Comorbid Depression)
- The Mao 2016 Long-Term Maintenance Trial
- Chamomile and Sertraline: No Head-to-Head Trial
- Chamomile vs Benzodiazepines
- Stacking with Other Botanical Anxiolytics
- Preparation, Dose, and Practical Use
- Cautions
- How Reviews and Guidelines Rate Chamomile for Anxiety
- Key Research Papers
- Connections
- Featured Videos
The GAD Treatment Landscape
Generalized anxiety disorder is characterized by persistent, excessive worry that the patient finds difficult to control, accompanied by physical symptoms (restlessness, fatigue, difficulty concentrating, irritability, muscle tension, sleep disturbance) lasting at least six months. The lifetime prevalence is around 6%; the 12-month prevalence around 3%. Women are affected approximately twice as often as men. GAD frequently coexists with major depression, other anxiety disorders, and substance use disorders.
The first-line pharmacologic options:
- Selective serotonin reuptake inhibitors (escitalopram, sertraline, paroxetine) — U.S. Food and Drug Administration-approved for GAD. Modest-to-moderate effect size. Onset of action 2–6 weeks. Side effects include sexual dysfunction (very common), gastrointestinal (GI) upset, weight changes, emotional blunting, and a small minority of patients experience worsening anxiety in the first weeks. Withdrawal syndrome is well-documented and can be severe.
- Serotonin-norepinephrine reuptake inhibitors (venlafaxine, duloxetine) — U.S. Food and Drug Administration-approved for GAD. Similar effect size and side-effect profile to selective serotonin reuptake inhibitors. Duloxetine has additional indications for chronic pain and diabetic neuropathy that may be useful in patients with comorbid pain.
- Benzodiazepines (alprazolam, lorazepam, clonazepam) — rapid acute anxiolytic effect within 30–60 minutes. Effective for acute anxiety. Tolerance to the anxiolytic effect develops within weeks. Physical dependency with chronic use. Withdrawal can be severe and dangerous (seizures, rebound anxiety). Falls and fractures in older adults. Generally avoided for chronic GAD management.
- Buspirone — 5-HT1A partial agonist, U.S. Food and Drug Administration-approved for GAD. Slow onset (2–4 weeks). Modest effect size. Reasonably well-tolerated but underutilized in practice.
- Pregabalin — approved for GAD in Europe (not in US). Effective, with relatively rapid onset. Schedule V controlled substance in US due to misuse potential.
- Cognitive behavioral therapy — the first-line evidence-based psychotherapy. As effective as pharmacotherapy for GAD with longer-lasting benefit after discontinuation. Underutilized due to cost and access barriers.
The clinical reality is that many GAD patients are reluctant to start a selective serotonin reuptake inhibitor for chronic worry, do not want a controlled substance, and either cannot access cognitive behavioral therapy (CBT) or want pharmacologic support alongside therapy. Chamomile fits this gap with a meaningful evidence base.
Apigenin and the Benzodiazepine Site (Animal and Cell Studies)
The principal active responsible for chamomile's anxiolytic effect is the flavonoid apigenin. In a 1995 laboratory study, apigenin bound the benzodiazepine-recognition site on the gamma-aminobutyric acid-A receptor with a Ki of 4 micromolar (the low-micromolar range) — weaker than pharmaceutical benzodiazepines by approximately a thousand-fold. In the same study, in mice, apigenin reduced anxiety-like behaviour in the elevated plus-maze without sedation or muscle relaxation at doses similar to those used for classical benzodiazepines; a 10-fold higher dose produced mild sedation (Viola 1995). A 2000 study in rats and cultured nerve cells found a different picture: apigenin reduced GABA-activated currents in cultured cells, showed no anti-anxiety effect when injected into rats, and its slowing of movement in rats was not blocked by the benzodiazepine-site blocker Ro 15-1788, so the authors traced that effect to other nerve-signalling systems (Avallone 2000). Whether apigenin acts as a partial agonist at the benzodiazepine site has not been established.
The partial-agonist idea, proposed but not established for apigenin, rests on a general distinction in pharmacology. A full benzodiazepine agonist (diazepam, alprazolam) produces a near-maximal anxiolytic effect at typical clinical doses, but at the cost of substantial sedation, cognitive impairment, motor incoordination, anterograde amnesia, and dependency potential. A partial agonist produces a submaximal anxiolytic effect at typical doses, but with proportionally smaller effects on sedation, cognition, motor function, and dependency.
The clinical translation: apigenin and chamomile extract reduce anxiety symptoms measurably but do not impair daytime functioning, do not produce dependency, do not produce withdrawal on discontinuation, and do not interact dangerously with other central nervous system (CNS) depressants (modest additive sedation, but no respiratory depression). This is the profile a patient with chronic mild-to-moderate GAD actually wants: real relief without trading the anxiety for a new set of problems.
Several other flavonoids in chamomile (luteolin, quercetin) also have modest BZD-site binding activity, contributing to the total anxiolytic effect of the whole extract. Standardized chamomile extracts (1.2% apigenin) probably underrepresent the contribution of these minor flavonoids; the extract is more anxiolytic than apigenin alone would predict, which supports the traditional use of whole-plant preparations rather than isolated apigenin supplements.
The Amsterdam 2009 GAD Trial
The pivotal modern trial of chamomile for anxiety was conducted by Jay Amsterdam and colleagues at the University of Pennsylvania, published in the Journal of Clinical Psychopharmacology in 2009. This was a randomized, double-blind, placebo-controlled trial of standardized chamomile extract in 57 outpatients with DSM-IV-defined GAD.
Design details:
- Participants: 61 outpatients with mild to moderate GAD (DSM-IV criteria) were enrolled; 57 were randomized, 28 to chamomile and 29 to placebo
- Intervention: pharmaceutical-grade chamomile extract (220 mg capsules standardized to 1.2% apigenin), titrated from one capsule daily to a maximum of five capsules daily based on response and tolerability
- Comparator: matched placebo
- Duration: 8 weeks
- Primary outcome: HAM-A total score change from baseline
Results: the chamomile group showed a significantly greater reduction in mean total HAM-A score than placebo (P = 0.047). The study was not powered to detect small-to-moderate differences in secondary measures (Beck Anxiety Inventory, Psychological General Well-Being Index, Clinical Global Impression-Severity), but all of them moved in the same direction as the main result. One patient in each group stopped treatment because of adverse events, and the number of adverse events per patient did not differ significantly between groups (P = 0.417). Adverse events were mild and comparable between groups; the most common was mild transient gastrointestinal upset. No serious adverse events occurred.
The authors described it as the first controlled clinical trial of chamomile extract for GAD and concluded that chamomile “may have modest anxiolytic activity in patients with mild to moderate GAD,” adding that future studies are needed to replicate these observations.
The Amsterdam 2012 Follow-Up (Comorbid Depression)
Amsterdam and colleagues followed up the GAD trial with a 2012 publication in Alternative Therapies in Health and Medicine examining the antidepressant effect of chamomile in patients with comorbid depression. GAD and major depression cooccur in approximately 60% of GAD cases, and an anxiolytic that does not address comorbid depression is incomplete therapy.
In a re-analysis of the original Amsterdam 2009 trial cohort, the investigators stratified participants by baseline depression status and examined the chamomile-versus-placebo effect on depressive symptoms (measured by the Hamilton Depression Rating Scale).
- Of the 57 participants, 19 had anxiety with current comorbid depression, 16 had a past history of depression, and 22 had no current or past depression
- Across all 57 participants, Hamilton Depression Rating (HAM-D) scores fell significantly more on chamomile than on placebo (P < .05), and so did the HAM-D core mood item scores (P < .05)
- In the 19 participants with current comorbid depression, the greater fall in HAM-D scores on chamomile was a clinically meaningful but nonsignificant trend (P = .062)
- The authors, who called the study exploratory, concluded that chamomile may provide clinically meaningful antidepressant activity in addition to its previously observed anxiolytic activity
- The effect was modest but consistent with antidepressant activity of apigenin in animal models
The mechanism of an antidepressant effect of chamomile is less well-characterized than the anxiolytic mechanism. Hypotheses include modest serotonergic and noradrenergic effects, modulation of hypothalamic-pituitary-adrenal-axis cortisol responses, and apigenin's known monoamine oxidase inhibitory activity at higher doses. The clinical effect appears real but modest — chamomile has not been tested as a replacement for selective serotonin reuptake inhibitor/serotonin-norepinephrine reuptake inhibitor (SNRI) treatment of major depression.
A 2020 analysis looked at the 179 people in the 8-week open-label phase of the later relapse-prevention trial (chamomile extract 1500 mg daily): 100 had GAD without depression and 79 had GAD with comorbid depression. Anxiety relief was similar in both groups. Core depression scores (the six-item core Hamilton depression scale) fell more in those with comorbid depression (p < 0.023), while total depression scores showed only a trend (p = 0.14). The authors called this a preliminary observation and wrote that controlled trials in people with primary major depressive disorder are needed (Amsterdam 2020).
The Mao 2016 Long-Term Maintenance Trial
Mao and colleagues (2016) published a continuation trial in Phytomedicine examining whether long-term chamomile use prevents GAD symptoms from coming back (relapse). This addresses one of the most important practical questions for any chronic GAD treatment.
Design: 179 outpatients with moderate-to-severe GAD received open-label pharmaceutical-grade chamomile extract, 1500 mg/day (one 500 mg capsule three times daily), for 12 weeks; those who responded were then randomized, double-blind, to either continued chamomile or placebo for 26 additional weeks. The primary outcome was time to relapse.
- In the open-label phase, 58.1% of the 179 participants met response criteria by week 8 (Keefe 2016); 93 (51.9%) were responders who agreed to enter the randomized phase
- Relapse occurred in 7 of 46 (15.2%) people kept on chamomile versus 12 of 47 (25.5%) switched to placebo; mean time to relapse was 11.4 weeks on chamomile and 6.3 weeks on placebo. The lower hazard of relapse on chamomile (hazard ratio 0.52, 95% CI 0.20–1.33, P = 0.16) was not statistically significant; the authors attributed this partly to the limited sample size and a lower-than-expected relapse rate on placebo
- During follow-up, people on chamomile kept significantly lower GAD symptom scores than those on placebo (P = 0.0032) and had significant reductions in body weight (P = 0.046) and mean arterial blood pressure (P = 0.0063)
- Both groups had similar low adverse event rates; all adverse events were graded mild, and no participant was withdrawn because of adverse events. The paper does not report on withdrawal or rebound symptoms after the switch to placebo
The authors concluded that long-term chamomile was safe and significantly reduced moderate-to-severe GAD symptoms, but did not significantly reduce the rate of relapse, and that possible chamomile superiority over placebo requires further examination in large-scale studies.
Chamomile and Sertraline: No Head-to-Head Trial
No published trial has compared chamomile directly with sertraline, the selective serotonin reuptake inhibitor widely used for GAD, or with another selective serotonin reuptake inhibitor. The chamomile trials so far compared chamomile with placebo (Amsterdam 2009, Mao 2016) or gave it open-label (Keefe 2016).
The nearest statement comes from the 2016 open-label study of 179 people with moderate-to-severe GAD: its authors reported that chamomile extract produced a clinically meaningful reduction in GAD symptoms over 8 weeks, “with a response rate comparable to those observed during conventional anxiolytic drug therapy and a favorable adverse event profile,” and wrote that “future comparative effectiveness trials between chamomile and conventional drugs may help determine the optimal risk/benefit of these therapies.” In that study, adverse events occurred in 11.7% of participants, with no serious adverse events, and 15.6% stopped treatment early.
Chamomile vs Benzodiazepines
In laboratory studies, chamomile's apigenin binds the same molecular target as benzodiazepines (the benzodiazepine site of the gamma-aminobutyric acid-A receptor), at a dramatically weaker affinity; whether this binding explains chamomile's effect in people has not been established. The comparison is informative for understanding what chamomile can and cannot do.
| Feature | Chamomile (apigenin) | Benzodiazepine (alprazolam) |
|---|---|---|
| BZD-site affinity | Low-micromolar Ki | Low-nanomolar Ki (~1000× tighter) |
| Functional class | Not established (animal and cell studies conflict) | Full agonist |
| Acute anxiolytic onset | 30–90 min | 30–60 min |
| Acute effect size | Modest | Large |
| Sedation at anxiolytic dose | Minimal | Substantial |
| Cognitive impairment | Minimal | Substantial |
| Tolerance | Not documented | Develops within weeks |
| Physical dependency | Not documented | Develops with chronic use |
| Withdrawal syndrome | None | Severe, can include seizures |
| Respiratory depression risk | None at any reasonable dose | Serious with opioid co-use |
| Fall/fracture risk in elderly | Not documented | Substantially elevated |
| Driving impairment | None at typical doses | Documented; legal liability |
The pattern is clear. Chamomile and benzodiazepines are not interchangeable. Chamomile is for chronic mild-to-moderate anxiety where the trade-off is gentle ongoing relief without disrupting daytime function or creating dependency. Benzodiazepines are for severe acute anxiety or panic where rapid full anxiolysis is needed and short-duration use can be assured.
Patients tapering off chronic benzodiazepine use frequently incorporate chamomile (along with magnesium glycinate, glycine, L-theanine, melatonin, and aggressive cognitive behavioral therapy) as supportive scaffolding during the slow benzodiazepine taper. None of these is a benzodiazepine replacement, but together they take the edge off the withdrawal anxiety and rebound symptoms that make tapers fail.
Stacking with Other Botanical Anxiolytics
Chamomile is often combined with other gentle botanical anxiolytics. Common stacking:
- Chamomile + lemon balm (Melissa officinalis) — lemon balm also has modest GABAergic and acetylcholinesterase-modulating activity. The combination is sold in commercial blends. See our Lemon Balm page.
- Chamomile + passionflower (Passiflora incarnata) — passionflower modulates gamma-aminobutyric acid-A through direct binding at the receptor (distinct from the BZD site). Combined effect is additive.
- Chamomile + L-theanine — L-theanine is an amino acid from green tea that increases alpha-wave electroencephalogram (EEG) activity and produces a calm-alert state distinct from sedation. The chamomile-theanine combination produces the somewhat-paradoxical combination of anxiolysis plus mental clarity.
- Chamomile + ashwagandha (Withania somnifera) — ashwagandha is an adaptogen with documented cortisol-reducing activity. The combination addresses both the acute anxiety and the underlying hypothalamic-pituitary-adrenal-axis hyperactivity. See our Ashwagandha page.
- Chamomile + magnesium glycinate — magnesium is itself a GABAergic modulator at N-methyl-D-aspartate (NMDA) receptors, and glycine is an inhibitory neurotransmitter. The combination is particularly useful for anxiety with prominent muscle tension and sleep disturbance.
None of these combinations replace pharmacotherapy in severe GAD or panic disorder. They are useful as primary therapy for mild-to-moderate generalized anxiety, as adjuncts to selective serotonin reuptake inhibitor/serotonin-norepinephrine reuptake inhibitor/cognitive behavioral therapy treatment of more severe anxiety, and as supportive scaffolding during benzodiazepine tapers.
Preparation, Dose, and Practical Use
For anxiety specifically (as opposed to sleep), the standardized capsule formulation has the strongest evidence base because that is what the trials used. Doses used in the trials and in traditional practice:
- Starting dose: the 2009 trial started at 220 mg standardized chamomile extract (1.2% apigenin) once daily for 1 week. Practitioners describe taking it with food to reduce the small risk of gastrointestinal upset.
- Titration: the 2009 trial raised the dose to 2 capsules daily in week 2; people whose HAM-A score had not fallen by more than half went up to 3 capsules in week 3, 4 in week 4 and 5 in weeks 5–8, and doses could be lowered at any time for tolerability. Most patients respond at 440–880 mg/day in divided doses.
- Maximum dose: 1100 mg/day total (the Amsterdam 2009 maximum). The 2016 Keefe and Mao trials used 1500 mg/day (one 500 mg capsule three times daily), for up to 38 weeks in the Mao trial.
- Duration: the trials judged the effect after 8 weeks (Amsterdam 2009, Keefe 2016) and 12 weeks (the open-label phase of Mao 2016). The Amsterdam trial reported continued accumulation of benefit through 8 weeks.
- Tea (adjunct): 1–3 cups of well-steeped chamomile tea per day is a common traditional amount, used alongside or instead of capsules. Tea is lower dose but has the ritual benefit of mindful pause that itself contributes to anxiety reduction.
- Discontinuation: no taper is described as required — chamomile does not produce withdrawal syndrome. In the Mao 2016 trial, responders randomized to placebo were switched from chamomile to placebo without a taper.
Standardized extracts vary considerably in actual apigenin content. The trials used pharmaceutical-grade extracts: 220 mg capsules standardized to 1.2% apigenin (Amsterdam 2009) and 500 mg capsules containing 6 mg of total apigenin-7-glycosides (Mao 2016). Unstandardized over-the-counter (OTC) "chamomile capsule" supplements may have very different apigenin content than the randomized controlled trial (RCT) extracts.
Cautions
- Asteraceae allergy — cross-reactivity with ragweed allergy is well-documented. Rare anaphylaxis. Rash, itching, or breathing changes after starting chamomile are signs of an allergic reaction; breathing changes are a sign hospitals treat as urgent.
- Warfarin and anticoagulants — small case-report risk of international normalized ratio (INR) elevation. A 2006 case report describes a 70-year-old woman on warfarin who was admitted to hospital with multiple internal hemorrhages after using chamomile tea and body lotion; its authors note a theoretical risk that chamomile strengthens warfarin's effect (Segal and Pilote 2006).
- Pregnancy — tea is generally regarded as acceptable in moderate amounts. There is no good safety data on high-dose extracts in pregnancy.
- Pediatric use — chamomile tea has a long tradition of safe use in children for colic, teething pain, and sleep, traditionally at half strength. Standardized extract capsules have less safety data in pediatric populations.
- Cytochrome P450 3A4 (CYP3A4) substrates — apigenin is a weak cytochrome P450 3A4 inhibitor in vitro. Clinical magnitude probably small; it matters most for people on narrow-therapeutic-index drugs (cyclosporine, tacrolimus, certain anticonvulsants).
- Cyclosporine — specific case report of cyclosporine level elevation with chamomile tea. The concern applies to transplant patients, who take cyclosporine to prevent organ rejection.
- Severe disease — for severe GAD, panic disorder, post-traumatic stress disorder (PTSD), and major depression, formal psychiatric evaluation and evidence-based treatment are the standard of care. The chamomile trials enrolled people with mild to moderate GAD (Amsterdam 2009) and moderate-to-severe GAD (Keefe 2016, Mao 2016); PubMed lists no trial of chamomile in panic disorder or PTSD.
How Reviews and Guidelines Rate Chamomile for Anxiety
- 2019 meta-analysis. A systematic review and meta-analysis of 12 randomized trials found that, on the Hamilton Anxiety Rating Scale, people with GAD improved significantly on chamomile after 2 weeks (mean difference −1.43 points) and after 4 weeks (mean difference −1.79 points). Across three trials of anxiety in general, it found no difference (standardized mean difference −0.15, P = 0.4214). Mild adverse events were reported by three trials. The authors wrote that chamomile appears efficacious and safe for sleep quality and GAD, that little evidence shows an effect on anxiety and insomnia, and that larger trials are needed (Hieu 2019).
- 2022 network meta-analysis. A Bayesian network meta-analysis of 29 trials comparing 12 medicinal herbs for anxiety found “insufficient evidence to confirm” whether chamomile is ineffective compared with placebo (mean difference 0.54 points on the Hamilton Anxiety Scale, 95% credible interval −5.13 to 6.25). All the herbs were well tolerated, and the authors called their results preliminary because of small sample sizes and the potential effect of placebos (Zhang 2022).
- 2022 international taskforce. A taskforce of the World Federation of Societies of Biological Psychiatry (WFSBP) and the Canadian Network for Mood and Anxiety Treatments (CANMAT) — 31 academics and clinicians from 15 countries — rated ashwagandha (++), galphimia (+) and lavender (++) as modestly supported for anxiety disorders, while kava (−) and chamomile (+/−) were “not recommended for generalised anxiety disorder” (Sarris 2022).
Key Research Papers
- Amsterdam JD et al. (2009). A randomized, double-blind, placebo-controlled trial of oral Matricaria recutita (chamomile) extract therapy for generalized anxiety disorder. Journal of Clinical Psychopharmacology, 29(4):378-382. — PubMed PMID: 19593179
- Amsterdam JD et al. (2012). Chamomile (Matricaria recutita) may provide antidepressant activity in anxious, depressed humans. Alternative Therapies in Health and Medicine, 18(5):44-49. — PubMed PMID: 22894890
- Mao JJ et al. (2016). Long-term chamomile (Matricaria chamomilla L.) treatment for generalized anxiety disorder: A randomized clinical trial. Phytomedicine, 23(14):1735-1742. — PubMed PMID: 27912875
- Keefe JR et al. (2016). Short-term open-label chamomile (Matricaria chamomilla L.) therapy of moderate to severe generalized anxiety disorder. Phytomedicine, 23(14):1699-1705. — PubMed PMID: 27912871
- Viola H et al. (1995). Apigenin, a component of Matricaria recutita flowers, is a central benzodiazepine receptors-ligand with anxiolytic effects. Planta Medica, 61(3):213-216. — PubMed PMID: 7617761
- Avallone R et al. (2000). Pharmacological profile of apigenin, a flavonoid isolated from Matricaria chamomilla. Biochemical Pharmacology, 59(11):1387-1394. — PubMed PMID: 10751547
- Salehi B et al. (2019). The therapeutic potential of apigenin. International Journal of Molecular Sciences, 20(6):1305. — PubMed PMID: 30875872
- Srivastava JK, Shankar E, Gupta S (2010). Chamomile: A herbal medicine of the past with bright future. Molecular Medicine Reports, 3(6):895-901. — PubMed PMID: 21132119
- Hieu TH et al. (2019). Therapeutic efficacy and safety of chamomile for state anxiety, generalized anxiety disorder, insomnia, and sleep quality: A systematic review and meta-analysis. Phytotherapy Research, 33(6):1604-1615. — PubMed PMID: 31006899
- Yeung KS et al. (2018). Herbal medicine for depression and anxiety: A systematic review with assessment of potential psycho-oncologic relevance. Phytotherapy Research, 32(5):865-891. — PubMed PMID: 29464801
- Amsterdam JD, Li QS, Xie SX, Mao JJ (2020). Putative antidepressant effect of chamomile (Matricaria chamomilla L.) oral extract in subjects with comorbid generalized anxiety disorder and depression. Journal of Alternative and Complementary Medicine, 26(9):813-819. — PubMed PMID: 31808709
- Zhang W et al. (2022). Medicinal herbs for the treatment of anxiety: A systematic review and network meta-analysis. Pharmacological Research, 179:106204. — PubMed PMID: 35378276
- Sarris J et al. (2022). Clinician guidelines for the treatment of psychiatric disorders with nutraceuticals and phytoceuticals: The World Federation of Societies of Biological Psychiatry (WFSBP) and Canadian Network for Mood and Anxiety Treatments (CANMAT) Taskforce. World Journal of Biological Psychiatry, 23(6):424-455. — PubMed PMID: 35311615
- Segal R, Pilote L (2006). Warfarin interaction with Matricaria chamomilla. CMAJ (Canadian Medical Association Journal), 174(9):1281-1282. — PubMed PMID: 16636327