Chamomile for Digestive Health and Irritable Bowel Syndrome (IBS)
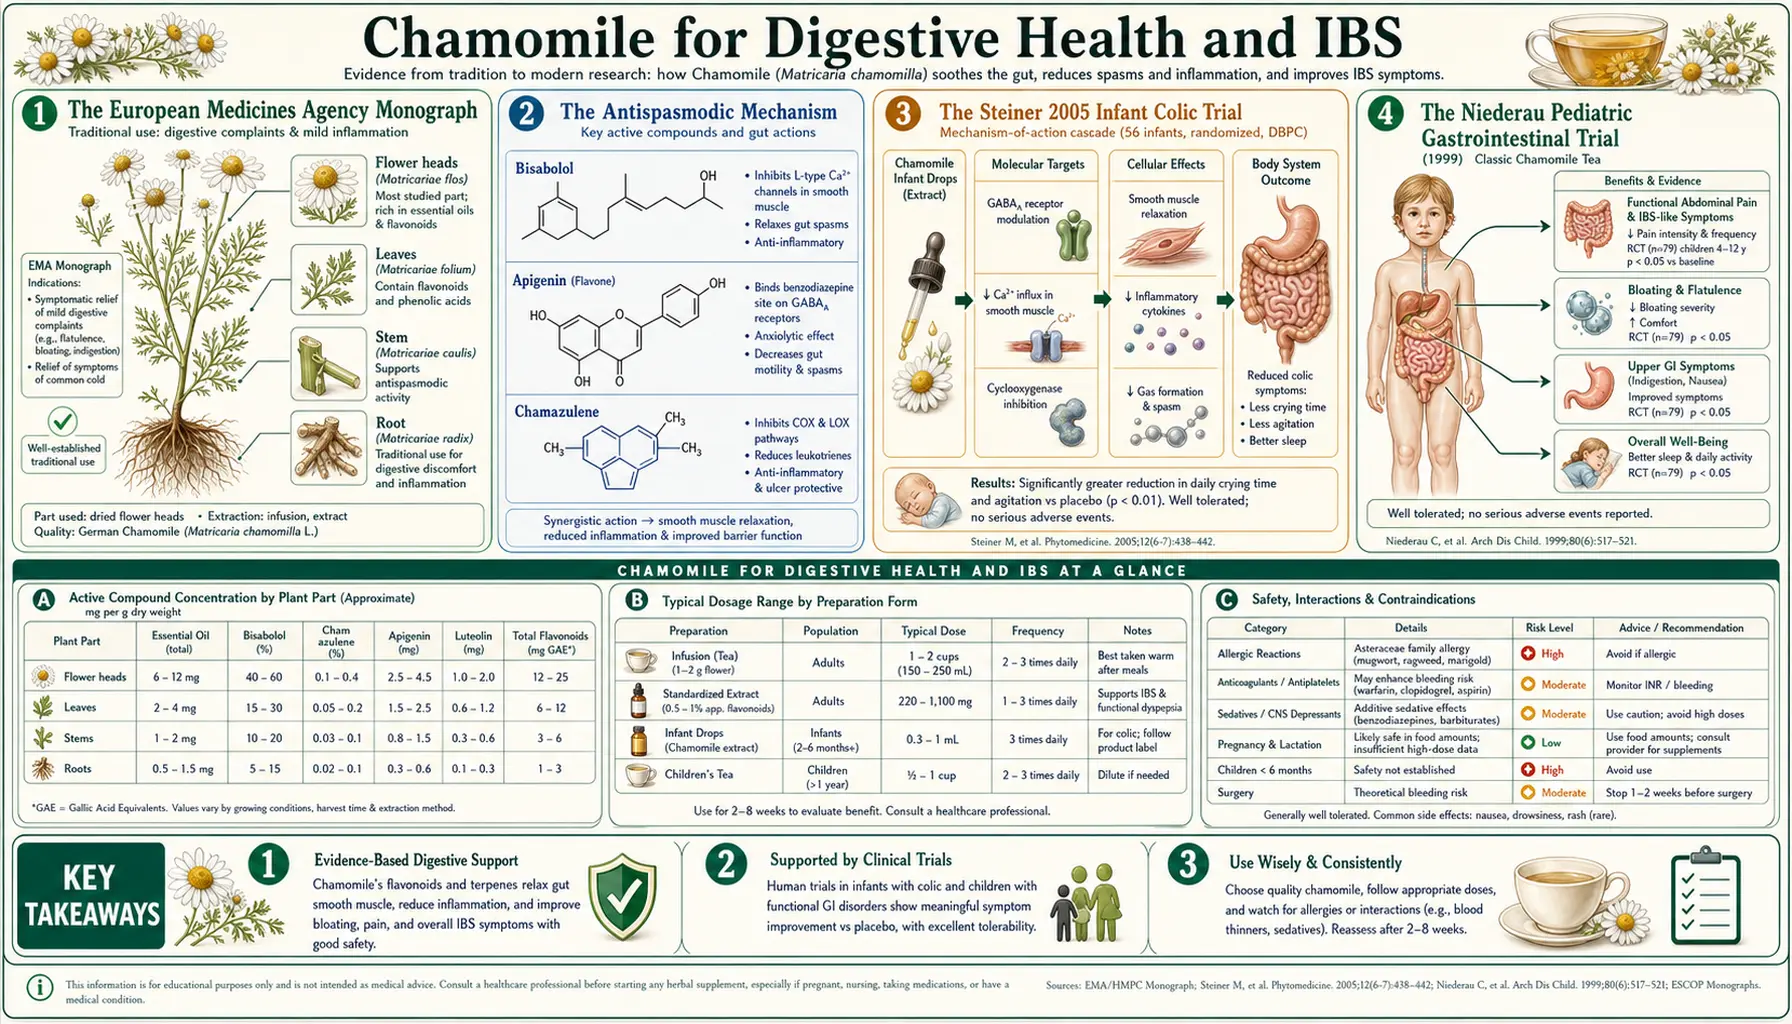
Chamomile's reputation as a digestive remedy is older than its reputation as a sleep aid — the European Medicines Agency monograph lists "mild spasmodic gastrointestinal complaints" as an approved traditional indication, supported by a continuous record of use back to the medieval European herbalists. The mechanism is twofold: direct smooth-muscle antispasmodic activity via the sesquiterpenoid alpha-bisabolol and the flavonoid fraction, and anti-inflammatory activity via the azulene pigment chamazulene. The Savino 2005 trial in infantile colic, testing a standardized extract of chamomile, fennel and lemon balm, found daily crying fell from about 201 to 77 minutes, against 199 to 170 minutes on placebo, in a population where the alternatives (simethicone, gripe water, bicycle legs) are mostly placebo. In children with acute diarrhea, the de la Motte 1997 and Becker 2006 trials found an apple pectin–chamomile preparation worked better than placebo. Chamomile is one of nine herbs in the German liquid extract STW 5 and one of six in its version without greater celandine (STW 5-II); trials report improvement in functional dyspepsia, though a 2023 Cochrane review rates the evidence for STW 5 as very uncertain. For adult irritable bowel syndrome (IBS), practitioners usually use chamomile as part of a multi-herb antispasmodic and gut-soothing approach rather than on its own; a 2026 meta-analysis of plant-based IBS treatments found too few chamomile trials to pool.
Table of Contents
- The European Medicines Agency Monograph
- The Antispasmodic Mechanism (Bisabolol, Apigenin, Chamazulene)
- The Savino 2005 Infant Colic Trial
- The Apple Pectin–Chamomile Diarrhea Trials in Children
- Chamomile in the Nine-Herb STW 5 Combination
- Irritable Bowel Syndrome Adjunct Treatment
- Functional Dyspepsia
- Ulcerative Colitis Remission-Maintenance Pilot Data
- Preparation and Dose for Gastrointestinal Indications
- Cautions
- Key Research Papers
- Connections
- Featured Videos
The European Medicines Agency Monograph
Chamomile flower (Matricariae flos) holds a Traditional Herbal Medicinal Product (THMP) registration with the European Medicines Agency (EMA), and the community monograph lists three formally recognized traditional uses:
- Mild spasmodic gastrointestinal complaints (oral, including bloating, flatulence, mild gastrointestinal cramping)
- Mild inflammation of the oral cavity and skin (topical and as a mouthwash for stomatitis, gingivitis, minor wounds)
- Common cold symptom relief (inhalation for nasal/upper respiratory inflammation)
The gastrointestinal indication carries the longest documented use history (centuries) and the strongest preclinical mechanistic rationale (direct smooth-muscle relaxation, anti-inflammatory effect on intestinal mucosa, modest antibacterial activity against gut pathogens). Modern preclinical work has filled in the molecular details that the historical herbalists could not have known.
The European Medicines Agency registration is important practically because it formalizes traditional-use evidence in a regulatory framework that allows over-the-counter sale of chamomile preparations across the European Union as approved herbal medicinal products (not merely food supplements). In the US, by contrast, chamomile is regulated as a dietary supplement under DSHEA, with less stringent quality control but also wide availability.
The Antispasmodic Mechanism (Bisabolol, Apigenin, Chamazulene)
Three distinct actives in chamomile contribute to its antispasmodic effect on intestinal smooth muscle, working through complementary mechanisms:
- Alpha-bisabolol (sesquiterpenoid) — the dominant component of German chamomile essential oil. Bisabolol is a direct calcium-channel modulator on intestinal smooth muscle, producing a dose-dependent relaxation of carbachol-, KCl-, and barium-induced contractions in isolated ileum and jejunum preparations. The effect is similar in pharmacology to the pharmaceutical antispasmodics mebeverine and otilonium bromide, though weaker in absolute affinity. Bisabolol additionally inhibits mucosal inflammation and has antiulcer activity in animal models of acid-induced gastric injury.
- Apigenin and flavonoid fraction — apigenin and several minor flavonoids (luteolin, quercetin, patuletin) also relax intestinal smooth muscle in isolated preparations, possibly through L-type calcium channel modulation and through mast-cell stabilization. Apigenin's gamma-aminobutyric acid-A receptor activity may also contribute — peripheral gamma-aminobutyric acid (GABA) receptors on enteric neurons modulate gut motility.
- Chamazulene (sesquiterpene azulene) — the deep-blue pigment formed during steam distillation. Chamazulene inhibits leukotriene B4 synthesis through 5-lipoxygenase inhibition and reduces neutrophil oxidative burst — both mechanisms reduce the inflammatory component of gastrointestinal smooth-muscle hyperresponsiveness. Chamazulene is also the principal component responsible for chamomile's antimicrobial activity against several gut bacteria.
The combined effect is greater than any single component would produce. Whole-plant chamomile extract is more potently antispasmodic in isolated tissue than apigenin alone, bisabolol alone, or chamazulene alone — the components are synergistic. This is the pharmacologic basis for the traditional use of the whole flower or whole-extract preparation rather than isolated single components.
The Savino 2005 Infant Colic Trial
Infantile colic is defined by the Rome IV pediatric criteria as recurrent and prolonged periods of infant crying, fussing, or irritability that occur without obvious cause and cannot be prevented or resolved by caregivers, in an otherwise healthy and well-fed infant under 5 months of age. The condition affects approximately 20% of infants. It is self-limited but profoundly stressful for caregivers and is associated with maternal depression, marital strain, and increased risk of shaken-baby syndrome in severe cases.
Pharmacologic options for infant colic are notably limited and weak. Simethicone is widely used but has no consistent efficacy advantage over placebo in controlled trials. Dicyclomine was withdrawn from infant use due to fatal apnea reports. The non-pharmacologic approaches (the 5 Ss, formula changes, probiotics including L. reuteri) have modest evidence but variable individual response. A safe, effective herbal option would be welcome.
Savino and colleagues (2005, Phytotherapy Research) ran a randomized double-blind placebo-controlled trial of a standardized extract of chamomile (Matricaria recutita), fennel and lemon balm in 93 breastfed infants with colic diagnosed by Wessel's criteria. After a three-day observation period, the babies received the extract or placebo twice a day for one week; 88 completed the trial (41 on the extract, 47 on placebo). The outcome was daily crying time.
- Daily crying fell from about 201 minutes to 77 minutes on the herbal extract, and from about 199 minutes to 170 minutes on placebo (p < 0.005)
- Crying time went down in 85% of the babies on the extract and in 49% of those on placebo (p < 0.005)
- No side effects were reported
- The combination is consistent with traditional European pediatric practice of fennel-and-chamomile preparations for infant gastrointestinal complaints
The trial is small and the herbal preparation was a combination, so it does not isolate the chamomile contribution. But it adds to the broader evidence base for chamomile in pediatric gastrointestinal symptoms and validates the centuries-old European tradition of fennel-chamomile-lemon balm tea for fussy infants. The trial abstract gives the dosing as twice daily but not the amount per dose. What is not known: the product combined three herbs, so chamomile's own share of the effect is unknown, and the trial lasted only one week.
For the broader picture, see the irritable bowel syndrome framework covering related functional gastrointestinal conditions in adults.
The Apple Pectin–Chamomile Diarrhea Trials in Children
De la Motte and colleagues (1997, Arzneimittelforschung) reported a double-blind randomized multicentre trial in 79 children aged 6 months to 5.5 years with acute, non-complicated diarrhea. An apple pectin–chamomile extract preparation (39 children) was compared with placebo (40 children), both given on top of the usual rehydration and realimentation diet.
- After three days of treatment, the diarrhea had ended in 33 of 39 children on pectin–chamomile and in 23 of 40 on placebo (p < 0.05)
- Pectin–chamomile shortened the diarrhea by at least 5.2 hours (p < 0.05)
- Parents were content more often with pectin–chamomile (82%) than with placebo (60%), a difference that was not significant; no further differences between the groups were found
A larger follow-up trial (DIALOG II, Becker and colleagues 2006) enrolled 255 children aged 6 months to 6 years with acute diarrhea, treated as outpatients with either an apple pectin–chamomile preparation or placebo; every child also received a glucose-electrolyte (oral rehydration) solution on the first day. The pectin–chamomile group had a significantly lower stool frequency than the placebo group, and side effects occurred at a rate similar to placebo.
The trial reinforces the broader picture of chamomile as a gentle, safe pediatric gastrointestinal option. Mechanistically the effect likely combines antispasmodic relief of cramping, anti-inflammatory activity on inflamed intestinal mucosa, and modest antibacterial activity against the causative pathogens. The pectin contributes through bulking the stool and adsorbing toxins.
Several follow-up European pediatric studies have examined chamomile preparations for various gastrointestinal complaints in childhood — teething-related drooling and oral discomfort, mild gastritis, transient diarrhea, and combined functional gastrointestinal symptoms. The aggregate signal supports the long European tradition.
Chamomile in the Nine-Herb STW 5 Combination
STW 5 is a fixed-combination herbal liquid extract marketed in Germany since 1961 and widely used across Europe for functional gastrointestinal disorders. The preparation contains alcoholic extracts of nine herbs:
- Iberis amara (bitter candytuft) — principal motility modulator, the plant the product is named after
- Matricaria chamomilla (chamomile flower) — antispasmodic, anti-inflammatory
- Carum carvi (caraway fruit) — carminative, antispasmodic
- Melissa officinalis (lemon balm leaf) — mild antispasmodic, anxiolytic
- Mentha × piperita (peppermint leaf) — antispasmodic via menthol
- Glycyrrhiza glabra (licorice root) — mucosal protective
- Chelidonium majus (greater celandine herb) — antispasmodic, biliary
- Angelica archangelica (angelica root) — carminative
- Silybum marianum (milk thistle fruit) — hepatic protective
Several of the trials tested a six-herb version without greater celandine, milk thistle and angelica (STW 5-II: bitter candytuft, chamomile, peppermint, caraway, licorice and lemon balm). In the Madisch 2004 trial (Digestion; 120 patients with functional dyspepsia), symptom scores fell significantly more on the six-herb extract than on placebo during the first four weeks, and after eight weeks 43.3% on active treatment versus 3.3% on placebo reported complete relief of symptoms. The 2023 Cochrane review of non-Chinese herbal medicines for functional dyspepsia (41 trials, 4,477 participants, 27 herbal medicines) found that the nine-herb STW 5 may moderately improve global dyspepsia symptoms compared with placebo at 28 to 56 days, but rated that evidence very uncertain (5 studies, 814 participants); side effects differed little from placebo. STW 5 is on the German Arzneimittelgesetz approved drug list (not merely a supplement) and is widely prescribed by German general practitioners and gastroenterologists.
Two 2024 papers report more on the six-herb STW 5-II. In an 8-week double-blind trial in 272 people with functional dyspepsia (Vinson and colleagues), 61.2% responded on STW 5-II versus 45.1% on placebo (P = 0.008), but the improvement in the average symptom score was not significantly larger (P = 0.07); safety measures did not differ between groups. A meta-analysis of individual patient data (Andresen and colleagues) found four randomized trials with 613 patients, two of them usable for the efficacy analysis: STW 5-II improved the dyspepsia symptom-sum score by a mean of 1.74 points at four weeks and 2.07 points at eight weeks compared with placebo, with no difference in treatment-related or severe side effects. Both 2024 papers list authors employed by or funded by the manufacturer.
The relevance for chamomile: the clinical effect of STW 5 is not attributable to any single herb, but chamomile contributes meaningfully to the antispasmodic and anti-inflammatory effects of the combination. The STW 5 experience also illustrates the general principle that multi-herb antispasmodic combinations tend to outperform single-herb monotherapy in functional gastrointestinal conditions — functional gastrointestinal complaints have multiple contributing mechanisms (motility, sensitivity, mucosal inflammation, microbiome, brain-gut axis), and a combination preparation hits more of them.
One safety note that emerged in 2018: the nine-herb STW 5 received a regulatory warning due to rare cases of hepatotoxicity attributed to the greater celandine (Chelidonium majus) component, not to chamomile. The six-herb STW 5-II tested in the Madisch 2004 trial and the 2024 studies contains chamomile but no greater celandine, so its trial safety data do not involve celandine. The warning does not concern chamomile or the other components.
Irritable Bowel Syndrome Adjunct Treatment
Irritable bowel syndrome (IBS) affects approximately 10–15% of adults globally. The Rome IV criteria define irritable bowel syndrome by recurrent abdominal pain, on average at least one day per week in the last three months, associated with two or more of: related to defecation, change in stool frequency, change in stool form. Three principal subtypes: diarrhea-predominant irritable bowel syndrome (IBS-D) (diarrhea-predominant), constipation-predominant irritable bowel syndrome (IBS-C) (constipation-predominant), irritable bowel syndrome-M (mixed).
The conventional pharmacologic options — antispasmodics (hyoscine, dicyclomine, mebeverine, otilonium), tricyclic antidepressants and selective serotonin reuptake inhibitors (SSRIs) in low dose for visceral hypersensitivity, eluxadoline and rifaximin for diarrhea-predominant irritable bowel syndrome, linaclotide and plecanatide for constipation-predominant irritable bowel syndrome — each have modest effect sizes and meaningful side effects. Multi-modal therapy is the rule, and herbal adjuncts are widely used.
Practitioners usually place chamomile in irritable bowel syndrome as one component of a broader antispasmodic / gut-soothing approach rather than on its own. Common combinations they describe:
- Chamomile + enteric-coated peppermint oil capsules — peppermint oil (menthol) is the most evidence-supported single botanical antispasmodic in irritable bowel syndrome, with multiple positive randomized controlled trials (RCTs). Combined with chamomile tea, the regimen addresses both acute symptom flares and lower-grade chronic discomfort. See our Peppermint page and the Peppermint, Probiotics, and Herbals for irritable bowel syndrome deep-dive sub-article.
- Chamomile + fennel + ginger — the "carminative tea" combination for postprandial bloating and gas. Fennel and ginger add additional smooth-muscle and prokinetic effects.
- Chamomile + the nine-herb STW 5 — largely overlapping, since STW 5 already contains chamomile.
- Chamomile + the underlying irritable bowel syndrome management framework — low-FODMAP elimination diet trial, soluble fiber (psyllium), targeted probiotic, stress reduction, sleep optimization. Chamomile fits as one tool in this multi-pronged approach, not as the principal intervention.
A 2026 systematic review and meta-analysis of plant-based treatments for irritable bowel syndrome (Meyer and colleagues; 60 studies, 6,329 patients) found that peppermint oil (7 studies, risk ratio 1.63) and Chinese herbal medicine (7 studies, risk ratio 1.56) worked better than placebo, and dietary fiber (8 studies, risk ratio 1.22) came close to significance. Other plants tested in at least one randomized trial had too little data to pool, and chamomile was not among the pooled treatments. Its use in adult irritable bowel syndrome therefore rests on tradition, on its place in combination products, and on laboratory studies.
For more on the underlying disease, see our Irritable Bowel Syndrome page, and its deep-dive sub-articles on peppermint, probiotics, and herbals.
Functional Dyspepsia
Functional dyspepsia (Rome IV definition: bothersome postprandial fullness, early satiation, epigastric pain, or epigastric burning, in the absence of organic disease that could explain the symptoms) affects approximately 10% of adults. Two subtypes: postprandial distress syndrome (early satiety, postprandial fullness) and epigastric pain syndrome.
The conventional pharmacologic options are limited and disappointing: proton pump inhibitors (modest effect, mostly in epigastric pain syndrome), prokinetics like metoclopramide (limited use due to tardive dyskinesia risk), and tricyclic antidepressants for visceral hypersensitivity. The condition is genuinely underserved.
The nine-herb STW 5 and its six-herb version have the largest body of herbal trials in functional dyspepsia, as discussed above, though the 2023 Cochrane review rated peppermint plus caraway oil more highly: it probably gives a large improvement in global symptoms compared with placebo at four weeks (2 studies, 210 participants, moderate-certainty evidence). Chamomile is one of the herbs in both STW 5 versions; its own share of their effect has not been measured in a trial. Beyond STW 5, single-herb chamomile (as tea or capsule) is widely used as a gentle adjunct, particularly for the postprandial-distress subtype where smooth-muscle relaxation and mild anti-inflammatory effects address the dominant mechanism. The Madisch et al. 2004 dyspepsia trial of the six-herb STW 5-II remains a principal piece of evidence. Herbalists also use a chamomile-fennel-peppermint-ginger tea, which contains no celandine.
Ulcerative Colitis Remission-Maintenance Pilot Data
Beyond functional gastrointestinal conditions, there is preliminary interest in chamomile (and especially in apigenin, which has documented NF-kB inhibitory and anti-inflammatory activity in animal colitis models) as an adjunct for ulcerative colitis remission maintenance. The clinical evidence remains pilot-stage:
- Animal models of DSS-induced and TNBS-induced colitis consistently show that apigenin and chamomile extract reduce histological inflammation, mucosal myeloperoxidase activity, and inflammatory cytokine production
- Small open-label and pilot trials in human ulcerative colitis suggest symptomatic benefit, but no large randomized controlled trials have established maintenance efficacy
- The mechanism would be a combination of direct anti-inflammatory effect on inflamed colonic mucosa, antispasmodic relief of the cramping that accompanies active colitis, and possible modest microbiome modulation
The current clinical positioning: chamomile is not a substitute for 5-aminosalicylates (mesalamine), biologics, or other standard inflammatory bowel disease (IBD) therapy, but some patients seeking complementary approaches use it as an adjunct alongside conventional treatment. The evidence is too preliminary to support chamomile monotherapy for active or maintenance inflammatory bowel disease. For comprehensive inflammatory bowel disease management, see our pages on Ulcerative Colitis and Crohn's Disease.
Preparation and Dose for Gastrointestinal Indications
- Tea (after meals for postprandial symptoms) — 1–2 teaspoons dried chamomile flowers per cup, steeped 10–15 minutes covered, drunk after meals as needed for bloating, fullness, or mild cramping. Up to 3–4 cups per day.
- Tincture (for acute spasmodic episodes) — 1:5 strength in 25% alcohol, 2–4 mL in a small amount of warm water, taken at onset of cramping; a second dose after 30 minutes is common practice.
- Standardized extract (for chronic functional gastrointestinal symptoms) — 220–440 mg standardized to 1.2% apigenin, two or three times daily before or with meals.
- Nine-herb STW 5 liquid extract (where available) — 20 drops in a small amount of water, three times daily before meals. The most-studied chamomile-containing formulation for functional gastrointestinal complaints.
- Combination herbal tea (fennel + chamomile + lemon balm) — one of the most widely used traditional preparations for bloating and infant colic. Equal parts dried herbs by weight; one teaspoon of the blend per cup, steeped covered 10 minutes.
For children, traditional practice dilutes the tea 1:1 with water and gives an amount by weight: approximately 5–10 mL per 5 kg body weight, two to three times daily for transient gastrointestinal complaints. Persistent infant gastrointestinal symptoms can have serious causes (pyloric stenosis, malrotation, food protein allergy) that herbal tea does not treat.
Cautions
- Asteraceae allergy — cross-reactivity with ragweed allergy, possible anaphylaxis. Rash, swelling or breathing changes after chamomile are the signs of an allergic reaction; swelling of the face or throat and trouble breathing are signs hospitals treat as urgent.
- Warfarin and anticoagulants — theoretical interaction via coumarin content; case reports of international normalized ratio (INR) elevation, which raises bleeding risk.
- Cyclosporine and cytochrome P450 3A4 (CYP3A4) substrates — weak cytochrome P450 3A4 inhibition in vitro; one case report of cyclosporine level elevation. The concern is greatest with high-dose extracts in transplant patients taking cyclosporine.
- Gastroesophageal reflux disease (GERD) nuances — chamomile is generally considered helpful for gastroesophageal reflux disease-associated dyspepsia, but in some individuals warm herbal tea (any kind) at bedtime can worsen reflux through gastric distension; some people with this problem drink chamomile earlier in the evening instead.
- Pregnancy — moderate tea use is generally regarded as acceptable. There is little safety data for high-dose extracts in pregnancy, and some sources list chamomile as a uterine stimulant in concentrated form.
- Nine-herb STW 5 hepatotoxicity warning — rare cases of hepatotoxicity attributed to the greater celandine (Chelidonium majus) component, not chamomile itself. The six-herb STW 5-II contains no celandine. Yellowing of the skin or eyes (jaundice) and dark urine are signs of liver injury.
- Not a substitute for organic-disease workup — new-onset gastrointestinal symptoms in adults over 45, gastrointestinal bleeding, weight loss, dysphagia, persistent vomiting, severe pain, or family history of gastrointestinal cancer are warning signs of organic disease that chamomile does not address; chamomile's studied uses are diagnosed functional gastrointestinal conditions.
Key Research Papers
- Savino F, Cresi F, Castagno E, Silvestro L, Oggero R (2005). A randomized double-blind placebo-controlled trial of a standardized extract of Matricariae recutita, Foeniculum vulgare and Melissa officinalis (ColiMil) in the treatment of breastfed colicky infants. Phytotherapy Research 19(4):335–340. — PubMed PMID: 16041731
- de la Motte S, Böse-O'Reilly S, Heinisch M, Harrison F (1997). Double-blind comparison of an apple pectin-chamomile extract preparation with placebo in children with diarrhea [article in German]. Arzneimittelforschung 47(11):1247–1249. — PubMed PMID: 9463302
- Becker B, Kuhn U, Hardewig-Budny B (2006). Double-blind, randomized evaluation of clinical efficacy and tolerability of an apple pectin-chamomile extract in children with unspecific diarrhea. Arzneimittelforschung 56(6):387–393. — PubMed PMID: 16889120
- Madisch A, Holtmann G, Mayr G, Vinson B, Hotz J (2004). Treatment of functional dyspepsia with a herbal preparation. A double-blind, randomized, placebo-controlled, multicenter trial. Digestion 69(1):45–52. — PubMed PMID: 14755152
- Vinson B, Fink C, Wargenau M, Talley NJ, Holtmann G (2024). Double-blind, randomized, 8-week multicenter study of the efficacy and safety of STW 5-II versus placebo in functional dyspepsia. JGH Open 8(5):e13054. — PubMed PMID: 38699471
- Andresen V, Shah A, Fink C, Rabini S, Wargenau M, Holtmann G (2024). Efficacy and safety of STW 5-II for functional dyspepsia treatment: a patient data-based meta-analysis. Digestion 105(3):166–174. — PubMed PMID: 38246134
- Báez G, Vargas C, Arancibia M, Papuzinski C, Franco JV (2023). Non-Chinese herbal medicines for functional dyspepsia. Cochrane Database of Systematic Reviews 6(6):CD013323. — PubMed PMID: 37323050
- Meyer A, Auer J, Cascant-Ortolano L, Schreiber N, Zimmermann-Klemd A, Gründemann C, Busche P, Schirra J, Fox MR (2026). Systematic review and meta-analysis: plant-based therapy for irritable bowel syndrome. Phytotherapy Research 40(10):5918–5950. — PubMed PMID: 42572206
- Achterrath-Tuckermann U et al. (1980). Pharmacological investigations with compounds of chamomile. V. Investigations on the spasmolytic effect of compounds of chamomile and Kamillosan on the isolated guinea pig ileum. Planta Medica. — PubMed PMID: 7403307
- Wegener T, Wagner H (2006). The active components and the pharmacological multi-target principle of STW 5 (Iberogast). Phytomedicine. — PubMed PMID: 16926095
- McKay DL, Blumberg JB (2006). A review of the bioactivity and potential health benefits of chamomile tea. Phytotherapy Research. — PubMed PMID: 16628544
- Srivastava JK, Shankar E, Gupta S (2010). Chamomile: A herbal medicine of the past with bright future. Molecular Medicine Reports. — PubMed PMID: 21132119
- Bhaskaran N et al. (2010). Chamomile: an anti-inflammatory agent inhibits inducible nitric oxide synthase. Journal of Molecular Medicine. — PubMed PMID: 21042790
- Miraj S, Alesaeidi S (2016). A systematic review study of therapeutic effects of Matricaria recuitta chamomile (chamomile). Electronic Physician 8(9):3024–3031. — PubMed PMID: 27790360
PubMed Topic Searches
Connections
- All Herbs
- Chamomile Overview
- Chamomile Benefits Hub
- Chamomile for Sleep Quality
- Chamomile for Anxiety Relief
- Chamomile for Skin Healing
- Peppermint
- Fennel
- Lemon Balm
- Ginger
- Irritable Bowel Syndrome
- Peppermint, Probiotics and Herbals for Irritable Bowel Syndrome
- Ulcerative Colitis
- Bloating
- Gut Healing
- History