⚠ Evidence warning: Clinical trials or other evidence do not support the claims that people without myalgic encephalomyelitis/chronic fatigue syndrome all reproduce their day-one numbers on a second-day exercise test and that a disability attorney dramatically improves approval odds. This page keeps it as a report of what people, websites or other media say.
Fibromyalgia and Myalgic Encephalomyelitis/Chronic Fatigue Syndrome (ME/CFS) Overlap
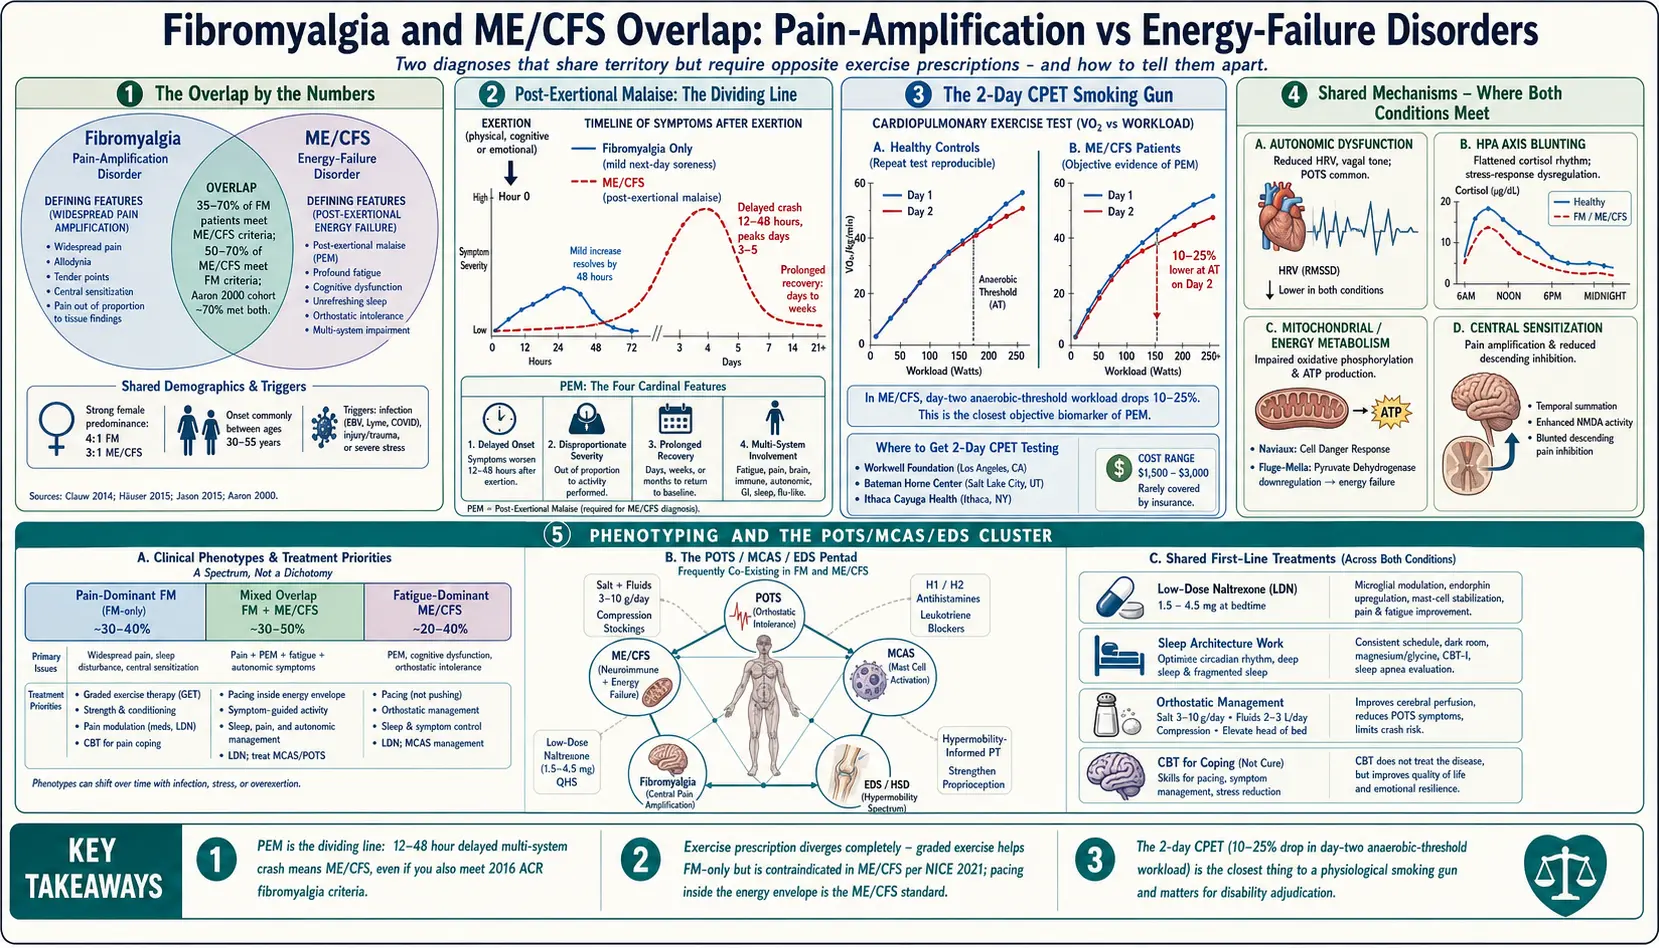
Table of Contents
- Why the Distinction Matters
- The Overlap by the Numbers
- Post-Exertional Malaise — The Dividing Line
- Three Criteria Sets Side by Side
- Shared Biological Mechanisms
- The 2-Day CPET — Objective PEM Proof
- Phenotyping: Pain-Dominant, Fatigue-Dominant, Mixed
- The Postural Orthostatic Tachycardia Syndrome / Mast Cell Activation Syndrome / Ehlers-Danlos Syndrome Cluster
- Exercise: Where the Two Diverge Completely
- Treatments That Work for Both
- Which Diagnosis to Pursue — Disability & Insurance
- Practical Steps If You Suspect Both
- Key Research Papers
- Connections
- Featured Videos
Why the Distinction Matters
If you have been diagnosed with fibromyalgia and the standard exercise advice made you dramatically worse — not just sore for a day, but wiped out for a week — you may not have "just fibromyalgia." You may have myalgic encephalomyelitis / chronic fatigue syndrome (ME/CFS) layered on top, or instead. The two conditions share so much surface territory that primary-care doctors routinely lump them together, but the treatments that help one can actively harm the other.
Fibromyalgia is, at its core, a pain amplification disorder. The central nervous system turns the volume up on every sensory signal, producing widespread pain, tenderness, and a constellation of cognitive and sleep symptoms. Myalgic encephalomyelitis/chronic fatigue syndrome, by contrast, is a post-exertional energy disorder. Its defining feature is that any exertion — physical, cognitive, or emotional — triggers a delayed, prolonged crash that can last days, weeks, or permanently worsen the baseline.
This article walks through where the two diagnoses overlap, where they split, and why getting the label right — or recognizing that both apply — changes everything about exercise prescription, pacing strategy, disability paperwork, and your long-term trajectory.
The Overlap by the Numbers
The diagnostic overlap is enormous. Depending on which study you read:
- 50–70% of myalgic encephalomyelitis/chronic fatigue syndrome patients also meet criteria for fibromyalgia.
- 35–70% of fibromyalgia patients also meet criteria for myalgic encephalomyelitis/chronic fatigue syndrome.
- The 2000 Aaron study compared patients with chronic fatigue syndrome, fibromyalgia and temporomandibular disorder with healthy controls. Patients in each group were more likely than controls to meet the symptom criteria for the other conditions, chronic fatigue syndrome and fibromyalgia included. Lifetime rates of irritable bowel syndrome were 92% in chronic fatigue syndrome, 77% in fibromyalgia and 64% in temporomandibular disorder, against 18% in controls.
- Both conditions show a strong female predominance (roughly 4:1 in fibromyalgia, 3:1 in myalgic encephalomyelitis/chronic fatigue syndrome).
- Both typically appear between ages 30 and 55, often following an infection, injury, or severe stressor.
That level of overlap is not coincidence. It suggests the two labels are carving out partly the same underlying biology from different angles — pain specialists see "fibromyalgia," fatigue specialists see "myalgic encephalomyelitis/chronic fatigue syndrome," and the patient in the middle ends up with whichever label their first specialist happened to use.
Post-Exertional Malaise — The Dividing Line
If there is one symptom that separates myalgic encephalomyelitis/chronic fatigue syndrome from fibromyalgia cleanly, it is post-exertional malaise, or PEM. PEM is not ordinary post-workout fatigue. It has four defining features:
- Delayed onset. The crash usually hits 12–48 hours after the exertion, not during it. You can feel fine at the gym and collapse two days later.
- Disproportionate severity. A grocery trip or a long phone call can produce the same flattening that a marathon would produce in a healthy person.
- Prolonged recovery. Days to weeks, sometimes months. Severe episodes can drop a patient's baseline permanently.
- Multi-system symptoms. PEM is not just fatigue. It includes cognitive "brain fog," flu-like malaise, sore throat, tender lymph nodes, orthostatic symptoms, and widespread pain — a whole-body crash, not just tiredness.
Fibromyalgia patients get sore after overdoing it. Myalgic encephalomyelitis/chronic fatigue syndrome patients get sick, for a long time, and the sickness does not respond to rest in the ordinary way. A fibromyalgia patient who pushes through a bad workout might need a heating pad and an extra nap. A myalgic encephalomyelitis/chronic fatigue syndrome patient who pushes through the same workout might lose the next three weeks of their life.
If PEM is present, treatment strategy changes fundamentally. Graded exercise therapy (GET), which has modest evidence in fibromyalgia, is contraindicated in myalgic encephalomyelitis/chronic fatigue syndrome. The 2021 NICE guidelines in the UK formally withdrew GET as a recommended treatment for myalgic encephalomyelitis/chronic fatigue syndrome after two decades of patient reports of harm and a re-analysis of the underlying trial data. The replacement strategy is pacing — staying inside an "energy envelope" rather than trying to expand it through progressive overload.
Three Criteria Sets Side by Side
Three major criteria sets govern these diagnoses. Knowing which one your doctor is using tells you a great deal about what they will look for and miss.
2016 ACR Fibromyalgia Criteria
The American College of Rheumatology's 2016 revision replaced the old tender-point exam with two questionnaires: the Widespread Pain Index (WPI), which counts painful body regions (0–19), and the Symptom Severity Scale (SSS), which scores fatigue, unrefreshing sleep, cognitive symptoms, and somatic complaints (0–12). Diagnosis requires either WPI ≥ 7 + SSS ≥ 5, or WPI 4–6 + SSS ≥ 9, with symptoms present at similar levels for at least three months. The 2016 revision also added a generalized pain criterion: pain in at least 4 of 5 body regions. Wolfe and colleagues reported that the 2010/2011 criteria misclassified regional pain syndromes and that adding this rule eliminated the misclassification. They also state that the physician-based criteria are valid for diagnosing an individual patient, while the self-report questionnaire version is not valid for diagnosing an individual and is meant for research studies. Crucially, fibromyalgia can now coexist with other diagnoses — the old "diagnosis of exclusion" requirement was dropped.
IOM / NAM 2015 SEID Criteria
In 2015, the Institute of Medicine (now the National Academy of Medicine) proposed renaming myalgic encephalomyelitis/chronic fatigue syndrome to Systemic Exertion Intolerance Disease (SEID) and simplified the diagnostic criteria to four core features, all required:
- Substantial reduction in pre-illness activity level for at least six months, accompanied by profound fatigue that is not relieved by rest.
- Post-exertional malaise.
- Unrefreshing sleep.
- At least one of: cognitive impairment, or orthostatic intolerance.
The SEID name never fully caught on, but the criteria themselves are the most clinician-friendly and are widely used in primary care and disability evaluations. They explicitly center PEM, which is the whole point.
Canadian Consensus Criteria (CCC, 2003) and ICC (2011)
The older Canadian Consensus Criteria and the stricter International Consensus Criteria (ICC) are still preferred by specialist clinics and research cohorts. They require PEM plus multiple symptoms from neurological, immune, autonomic, and energy-production categories. They identify a more severely affected subgroup than the IOM criteria and are the default for rigorous research. Specialist centers such as the Bateman Horne Center or Stanford's ME/CFS Clinic commonly use the CCC or ICC.
How the Criteria Interact
A patient can meet all three. Many do. Meeting the 2016 ACR fibromyalgia criteria does not exclude myalgic encephalomyelitis/chronic fatigue syndrome, and meeting IOM SEID criteria does not exclude fibromyalgia. In practice, if you have widespread pain plus PEM plus unrefreshing sleep plus cognitive symptoms, you likely qualify for both labels, and the correct diagnostic statement is "fibromyalgia and myalgic encephalomyelitis/chronic fatigue syndrome" rather than one or the other.
Shared Biological Mechanisms
Three biological systems keep turning up in both conditions, which is probably why the overlap is so large.
Autonomic Dysfunction
Both groups show abnormal heart-rate variability, reduced vagal tone, and a tendency toward orthostatic intolerance — symptoms on standing, including lightheadedness, palpitations, and fatigue. A sizable minority of patients in both groups meet criteria for postural orthostatic tachycardia syndrome (POTS). Tilt-table testing often reveals findings that explain the fainting, the "gravity is heavy" feeling, and the inability to stand in line at the grocery store. See the postural orthostatic tachycardia syndrome page and the postural orthostatic tachycardia syndrome/mast cell activation syndrome (MCAS)/Ehlers-Danlos syndrome (EDS) triad deep-dive.
Hypothalamic-Pituitary-Adrenal Axis Blunting
The hypothalamic-pituitary-adrenal axis — the body's main stress-response system — is measurably flattened in both fibromyalgia and myalgic encephalomyelitis/chronic fatigue syndrome cohorts. Morning cortisol tends to be low, the normal diurnal rhythm is blunted, and the reactivity to stress is reduced. This is not the same as Addison's disease (cortisol is not pathologically low, just suboptimal), but it helps explain why patients struggle with morning stiffness, post-stress crashes, and poor recovery from ordinary challenges.
Mitochondrial and Energy Metabolism Dysfunction
Research over the last decade has found reproducible abnormalities in cellular energy production in myalgic encephalomyelitis/chronic fatigue syndrome — impaired oxidative phosphorylation, altered pyruvate dehydrogenase activity, and a shift toward anaerobic metabolism at low workloads. Fibromyalgia patients show a milder version of the same signature. Naviaux's "cell danger response" framework and Fluge and Mella's pyruvate dehydrogenase work both describe a state in which cells behave as though they are still fighting a threat and cannot fully return to normal energy production. This is a plausible explanation for why the two conditions share fatigability, exercise intolerance, and the characteristic "wired but tired" sleep pattern.
Central Sensitization
On the pain side, both groups show central sensitization — an amplified, over-reactive pain-processing system. Temporal summation, the phenomenon where repeated mild stimuli build into severe pain, is exaggerated. Descending pain inhibition (the brain's ability to turn down incoming pain signals) is weaker. This is better studied in fibromyalgia but is clearly present in myalgic encephalomyelitis/chronic fatigue syndrome as well. See the central sensitization article for the full mechanism.
The 2-Day CPET — Objective PEM Proof
One of the few objective tests that can document PEM is the two-day cardiopulmonary exercise test (CPET), developed by Staci Stevens, Chris Snell, and Mark Van Ness at the Workwell Foundation. Davenport and colleagues described a conceptual model for physical therapist management of the illness in 2010, and Snell and colleagues published the two-day test results in 2013.
The protocol is simple in concept. The patient performs a maximal CPET on day one, measuring VO2 at peak and at the anaerobic threshold. They rest overnight. The next day, they repeat the identical test. Healthy people, sedentary people, people with heart failure, people with fibromyalgia without myalgic encephalomyelitis/chronic fatigue syndrome — all reproduce their day-one numbers within a few percentage points on day two. In healthy people, results are known to be closely reproducible from one day to the next. Myalgic encephalomyelitis/chronic fatigue syndrome patients show a 10–25% drop in workload and VO2 at the anaerobic threshold on the second test. Researchers attribute this to PEM triggered by the first test. Whether the drop is specific to myalgic encephalomyelitis/chronic fatigue syndrome is not settled: a 2020 meta-analysis states that further trials are needed to compare it with other fatigue-causing disorders, including depression.
In the 2013 study by Snell and colleagues, 51 women with chronic fatigue syndrome and 10 sedentary women without a disability did two maximal tests 24 hours apart. On the first test there was no significant difference between the groups. On the second test the patients had significantly lower oxygen use and workload, both at peak exercise and at the ventilatory (anaerobic) threshold, and the measurements sorted people into the right group 95.1% of the time. The authors concluded that a single exercise test may not be enough to show the impairment. The study included only patients able to complete both maximal tests. The 2020 meta-analysis of two-day studies found that all four measures fell on the second day in patients but rose in controls; the gap was largest for workload at the ventilatory threshold.
Why this matters:
- It is the closest thing to a physiological smoking gun for myalgic encephalomyelitis/chronic fatigue syndrome.
- Disability insurers and the Social Security Administration recognize CPET data far more readily than symptom questionnaires alone.
- It can objectively distinguish "fibromyalgia with fatigue" from "fibromyalgia plus myalgic encephalomyelitis/chronic fatigue syndrome," which changes treatment.
Caveats: the test is expensive (around $1,500–$3,000, rarely covered), it is offered at only a handful of U.S. centers (Workwell Foundation in California, Ithaca Cayuga Medical, Bateman Horne Center in Utah, and a few university labs), and the second-day test itself can worsen a severe patient for weeks. For patients fighting a disability denial, it can be decisive. See the myalgic encephalomyelitis/chronic fatigue syndrome page for more on testing strategy.
Phenotyping: Pain-Dominant, Fatigue-Dominant, Mixed
A useful clinical framework, whether or not your doctor uses this language explicitly, is to ask where your symptoms cluster:
Pain-Dominant Fibromyalgia
Widespread pain is the headline. Fatigue is present but manageable — you are tired, but you can push through a day of moderate activity and recover with a night's sleep. Exercise, done gently and progressively, tends to help. This phenotype responds reasonably well to duloxetine, milnacipran, low-dose naltrexone, and graded movement programs. Disability is driven by pain, not energy failure.
Fatigue-Dominant Myalgic Encephalomyelitis/Chronic Fatigue Syndrome
Fatigue and PEM are the headline. Pain is present but not the main story — it may come and go with crashes rather than sitting at a steady level. Any exercise increment beyond your current envelope triggers a crash. Pacing, aggressive rest, orthostatic management, and avoiding GET are the pillars of treatment. Disability is driven by energy failure, not pain.
Mixed Phenotype
The largest group. Both the pain and the PEM are severe. These patients are often the most disabled and the hardest to treat, because every intervention has to account for both the pain-amplification side and the post-exertional-crash side. Gentle movement that respects PEM can still help, but the ceiling is lower and the margin for error is narrow.
One way people sort this out is a two-week symptom log scoring pain (0–10) and fatigue/PEM (0–10) separately each day. The ratio of the two shows which pattern dominates.
The Postural Orthostatic Tachycardia Syndrome / Mast Cell Activation Syndrome / Ehlers-Danlos Syndrome Cluster
A large minority of fibromyalgia and myalgic encephalomyelitis/chronic fatigue syndrome patients — especially women in their 20s through 40s — cluster with three other diagnoses that travel together:
- postural orthostatic tachycardia syndrome (POTS) — heart rate rises more than 30 beats per minute on standing, with symptoms.
- mast cell activation syndrome (MCAS) — flushing, hives, food intolerances, gastrointestinal (GI) symptoms, and reactions to medications and temperature changes.
- Hypermobile Ehlers-Danlos syndrome (EDS) or generalized joint hypermobility — stretchy skin, bendy joints, velvet-soft skin, frequent subluxations.
When three or four of these co-occur in the same patient, it is sometimes called the fibromyalgia-POTS-MCAS-EDS pentad. Treatment becomes a coordinated effort: H1/H2 blockers for mast cell activation syndrome, salt loading and compression for postural orthostatic tachycardia syndrome, pacing for myalgic encephalomyelitis/chronic fatigue syndrome, low dose naltrexone (LDN) for pain, and physical therapy calibrated for hypermobility. See the postural orthostatic tachycardia syndrome/mast cell activation syndrome/Ehlers-Danlos syndrome triad deep-dive for the full protocol. Recognizing the cluster matters because treating one node in isolation often fails; the others keep pulling the patient backward.
Exercise: Where the Two Diverge Completely
This is the single most important practical difference, and it is the one most often mishandled.
For fibromyalgia without PEM, graded aerobic exercise has moderate evidence of benefit. Trials of walking, swimming, tai chi, and yoga show reduced pain, improved sleep, and better function at 12 weeks. The usual protocol starts low, increases by no more than 10% per week, accepts mild soreness and stops at sharp pain. See the graded movement article.
For myalgic encephalomyelitis/chronic fatigue syndrome (or fibromyalgia with PEM), the same protocol is actively dangerous. The 2011 PACE trial, which originally endorsed graded exercise therapy, has been extensively re-analyzed and its positive findings largely reversed. Real-world patient surveys consistently report that GET worsens their condition, sometimes permanently. The 2021 NICE guidelines in the UK, the U.S. Centers for Disease Control and Prevention (CDC), and the U.S. ME/CFS Clinical Coalition all now advise against GET and in favor of pacing.
Pacing means staying inside your energy envelope. The practical tools:
- A heart-rate monitor set to alert at the anaerobic threshold (commonly estimated at 55–60% of maximum heart rate for myalgic encephalomyelitis/chronic fatigue syndrome patients, or from CPET data if available), so activity can stop before the threshold is crossed.
- An activity diary tracking hours of upright activity, cognitive exertion, and social exertion against next-day symptoms.
- Planned rest before symptoms appear, not after.
- Reducing the envelope voluntarily during flares, viral illness, or emotional stress.
See the pacing and energy envelope article for the full protocol.
Treatments That Work for Both
Despite the divergence on exercise, a surprising amount of treatment overlaps. These interventions help both fibromyalgia and myalgic encephalomyelitis/chronic fatigue syndrome patients at reasonable rates:
- Low-dose naltrexone. At 1.5–4.5 mg nightly, low dose naltrexone reduces central sensitization and microglial activation. It has randomized-controlled-trial evidence in fibromyalgia and observational evidence in myalgic encephalomyelitis/chronic fatigue syndrome. The largest randomized trial so far (Denmark, 2024: 99 women with fibromyalgia, 6 mg once daily for 12 weeks) did not show that it relieved pain better than placebo. Pain fell by 1.3 points on a 0–10 scale with low dose naltrexone and by 0.9 points with placebo, a difference that was not statistically significant. Dropouts due to side effects were similar (8% vs 6%). The authors reported that it might improve the memory problems of fibromyalgia and called for future trials to test this. It is inexpensive and was generally well tolerated. See the low dose naltrexone article.
- Sleep architecture work. Both conditions feature deep-sleep disruption. Low-dose doxepin, mirtazapine, or trazodone; consistent sleep/wake timing; light exposure in the morning; sleep-study evaluation for comorbid apnea or periodic limb movements. See the sleep architecture article.
- Orthostatic management. Increased salt (3–10 g/day) and fluid (2–3 L/day), compression garments (waist-high, 20–30 mmHg), and beta blockers or midodrine where appropriate.
- Cognitive behavioral therapy aimed at coping, not at "curing" the illness. Cognitive behavioral therapy (CBT) does not fix either condition, but it can reduce the secondary suffering of living with chronic illness.
- Nutritional basics. Vitamin D repletion, B12 if low, magnesium glycinate for sleep and muscle pain, and treating iron deficiency aggressively.
Treatments that help fibromyalgia but often fail or worsen myalgic encephalomyelitis/chronic fatigue syndrome include antidepressants at activating doses, progressive aerobic exercise, and — in some patients — stimulant-based therapies that can push the patient over their energy envelope and into a crash.
Which Diagnosis to Pursue — Disability & Insurance
If you are applying for Social Security Disability, long-term disability insurance, or workplace accommodations, the label on the paperwork matters more than you would hope it should.
Fibromyalgia is formally recognized by the U.S. Social Security Administration (SSA) under Social Security Ruling (SSR) 12-2p. Claims succeed when there is a documented history from a rheumatologist, tender-point or WPI/SSS evidence, and functional limitations. Fibromyalgia is easier to get diagnosed and somewhat easier to get approved, but benefit awards for fibromyalgia alone tend to be more modest and more frequently reviewed.
Myalgic encephalomyelitis/chronic fatigue syndrome is formally recognized by the Social Security Administration under SSR 14-1p, which explicitly accepts the diagnosis when made according to U.S. Centers for Disease Control and Prevention criteria and supported by signs such as tender lymph nodes, non-exudative pharyngitis, or abnormal CPET findings. SSR 14-1p is often more favorable for severely disabled patients because it acknowledges that myalgic encephalomyelitis/chronic fatigue syndrome can produce complete work incapacity.
What the paperwork involves when both apply:
- Listing both diagnoses on every form keeps the evidence for each one in the claim; dropping one leaves its evidence out.
- Physician notes that document PEM explicitly, with examples, carry more weight. Vague notes like "fatigue" carry far less weight than "patient reports 3–5 day functional collapse after 20 minutes of housework."
- 2-day CPET data, where it can be obtained, is the most powerful objective evidence either condition has.
- A functional diary kept for several months before applying — hours of upright activity, hours of work capacity, crashes and their triggers — documents the pattern over time.
- Disability attorneys who handle myalgic encephalomyelitis/chronic fatigue syndrome claims usually work on a contingency fee, so nothing is paid upfront. Hiring one usually costs nothing upfront (contingency fee) and dramatically improves approval odds.
Practical Steps If You Suspect Both
- Self-scoring. The 2016 ACR questionnaire (WPI + SSS) and the IOM SEID checklist give written scores. The 2016 criteria paper states that the self-report version is valid for research but not for diagnosing an individual patient, so a self-score is a record to show a clinician, not a diagnosis.
- A two-week symptom log. Pain 0–10, fatigue 0–10, PEM episodes and triggers give the doctor a written record to read.
- Orthostatic vitals at home. The home check is lying flat for 10 minutes and measuring heart rate and blood pressure, then standing and measuring again at 1, 3, 5, and 10 minutes. A heart-rate increase greater than 30 beats per minute (or 40 in teenagers) flags postural orthostatic tachycardia syndrome.
- Two kinds of specialist. A rheumatologist covers the fibromyalgia side and a clinician who knows myalgic encephalomyelitis/chronic fatigue syndrome covers the PEM side. The Bateman Horne Center, the ME/CFS Clinical Coalition, and the Solve ME/CFS Initiative all maintain provider lists.
- Graded exercise therapy and worsening. The 2021 NICE guideline withdrew GET as a treatment for myalgic encephalomyelitis/chronic fatigue syndrome, and people with PEM commonly report that GET made them worse. That worsening is a recognized feature of PEM, not imagination.
- Pacing. Staying inside the energy envelope is the approach NICE 2021 and the U.S. bodies above describe, and it carries no known downside while the full diagnostic picture is sorted out.
- Low dose naltrexone. Inexpensive and generally well tolerated. The largest fibromyalgia trial (2024) did not find it better than placebo for pain, and the evidence in myalgic encephalomyelitis/chronic fatigue syndrome is observational.
Key Research Papers
- Institute of Medicine. Beyond Myalgic Encephalomyelitis/Chronic Fatigue Syndrome: Redefining an Illness. National Academies Press, 2015. — doi:10.17226/19012 (IOM / SEID criteria)
- Aaron LA, Burke MM, Buchwald D. Overlapping conditions among patients with chronic fatigue syndrome, fibromyalgia, and temporomandibular disorder. Arch Intern Med. 2000;160(2):221–227. — doi:10.1001/archinte.160.2.221
- Davenport TE, Stevens SR, VanNess JM, Snell CR, Little T. Conceptual model for physical therapist management of chronic fatigue syndrome/myalgic encephalomyelitis. Phys Ther. 2010. — doi:10.2522/ptj.20090047 (conceptual model, not the 2-day test results)
- Snell CR, Stevens SR, Davenport TE, Van Ness JM. Discriminative validity of metabolic and workload measurements for identifying people with chronic fatigue syndrome. Phys Ther. 2013;93(11):1484–1492. — PubMed PMID: 23813081
- Lim EJ, Kang EB, Jang ES, Son CG. The Prospects of the Two-Day Cardiopulmonary Exercise Test (CPET) in ME/CFS Patients: A Meta-Analysis. J Clin Med. 2020;9(12):4040. — PubMed PMID: 33327624
- Wolfe F, et al. 2016 Revisions to the 2010/2011 fibromyalgia diagnostic criteria. Semin Arthritis Rheum. 2016. — doi:10.1016/j.semarthrit.2016.08.012
- Fluge Ø, Mella O, et al. Metabolic profiling indicates impaired pyruvate dehydrogenase function in myalgic encephalopathy/chronic fatigue syndrome. JCI Insight. 2016. — doi:10.1172/jci.insight.89376
- Bateman L, Bested AC, Bonilla HF, et al. Myalgic Encephalomyelitis/Chronic Fatigue Syndrome: Essentials of Diagnosis and Management. Mayo Clin Proc. 2021;96(11):2861–2878. — PubMed PMID: 34454716
- Due Bruun K, Christensen R, Amris K, et al. Naltrexone 6 mg once daily versus placebo in women with fibromyalgia: a randomised, double-blind, placebo-controlled trial. Lancet Rheumatol. 2024;6(1):e31–e39. — PubMed PMID: 38258677
PubMed Topic Searches
For further reading, the following PubMed topic searches return current peer-reviewed work on the fibromyalgia / myalgic encephalomyelitis/chronic fatigue syndrome overlap and its management:
- PubMed: Fibromyalgia and chronic fatigue syndrome overlap
- PubMed: Post-exertional malaise in ME/CFS
- PubMed: Two-day CPET and chronic fatigue syndrome
- PubMed: Graded exercise therapy and reported harm in ME/CFS
- PubMed: Pacing and the energy envelope concept
- PubMed: Autonomic dysfunction in fibromyalgia and ME/CFS
- PubMed: HPA axis findings across both conditions
- PubMed: Low-dose naltrexone in fibromyalgia and ME/CFS
- PubMed: POTS, MCAS, and fibromyalgia cluster
- PubMed: 2016 ACR fibromyalgia diagnostic criteria
Connections
- Orthopedics
- Postural Orthostatic Tachycardia Syndrome
- Chronic Fatigue Syndrome
- Postural Orthostatic Tachycardia Syndrome/Mast Cell Activation Syndrome/Ehlers-Danlos Syndrome Triad
- Low-Dose Naltrexone for Fibromyalgia
- Sleep and Non-Restorative Sleep
- Central Sensitization Explained
- Exercise Pacing and Graded Movement
- Mast Cell Activation Syndrome
- Fibromyalgia Overview
- ACR 2016 Diagnostic Criteria
- Low-Dose Naltrexone
- Chronic Pain
- Fatigue
- Nutrient Gaps in Fibromyalgia
- Small-Fiber Neuropathy Overlap
- Post-Viral Triggers in Myalgic Encephalomyelitis/Chronic Fatigue Syndrome
- Magnesium
- Post Exertional Malaise Explained