Mast Cell Activation Syndrome (MCAS) Testing Guide
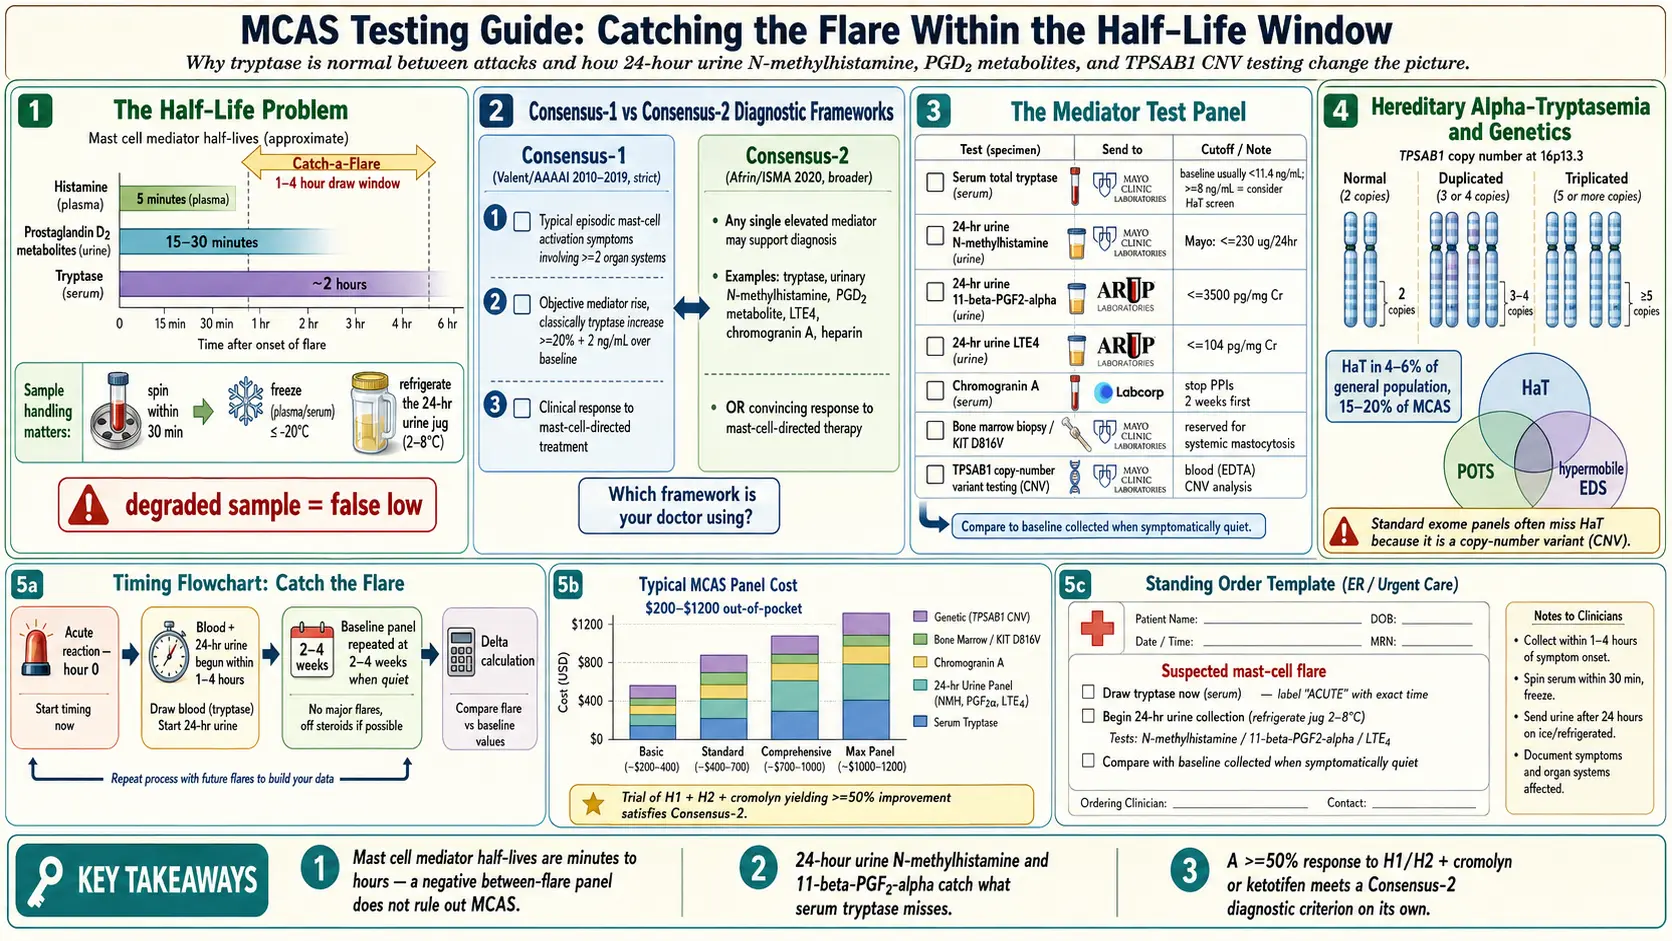
Table of Contents
- Why Mast Cell Activation Syndrome Testing Is Frustrating
- The Two Competing Diagnostic Frameworks
- Serum Tryptase
- 24-Hour Urine N-Methylhistamine
- 24-Hour Urine Prostaglandin D2 Metabolite
- 24-Hour Urine Leukotriene E4
- Chromogranin A
- Plasma Histamine
- Bone Marrow Biopsy
- Genetic Testing for Hereditary Alpha-Tryptasemia
- Timing Strategy — The “Catch a Flare” Approach
- What “All-Normal” Tests Mean
- Laboratories That Run Mast Cell Activation Syndrome Tests
- At-Home Test Kits
- Costs and Insurance
- Key Research Papers
- Connections
- Featured Videos
1. Why Mast Cell Activation Syndrome Testing Is Frustrating
If you’ve been told your tryptase is “normal” and therefore you don’t have mast cell activation syndrome, you need to understand something before your next appointment: mast cell mediators have extremely short half-lives. The biology of the test is working against you.
- Tryptase has a half-life of roughly 2 hours.
- Histamine — just 5 minutes in plasma.
- Prostaglandin D2 metabolites — 15–30 minutes.
If your blood is drawn between flares — which is the default when you show up at a routine appointment — most results will look perfectly normal. This does not mean you don’t have mast cell activation syndrome (MCAS). It means the test was timed badly. You are measuring whether a fire is burning by walking through the kitchen an hour after it was put out.
The second hidden obstacle: sample handling. Mast cell mediators are delicate. 24-hour urine samples must be kept chilled during collection. Plasma samples for histamine and PGD2 must be placed on ice and spun down into plasma within specific time windows (often under 30 minutes), then frozen. Many hospital labs don’t handle these samples correctly, and the degraded result comes back falsely low. Each lab sets its own rules for how samples are collected, transported and processed, so a sample handled outside those rules can give a falsely low result.
None of this is your fault, and none of it is in your head.
2. The Two Competing Diagnostic Frameworks
There is no single agreed-upon definition of mast cell activation syndrome. There are two, and which one your doctor uses dictates whether you get a diagnosis.
Consensus-1 (Valent and colleagues; working conference 2010, published 2012)
Requires all three:
- Typical episodic symptoms involving at least two organ systems (skin, gastrointestinal (GI), cardiovascular, respiratory).
- An acute ≥20% + 2 ng/mL rise in serum tryptase above the patient’s own baseline, measured during a flare.
- Response to antihistamines or mast-cell-targeted therapy.
This is the stricter framework. The tryptase-rise criterion is the one most patients “fail” either because the flare wasn’t timed right for a draw, or because their mast cells release histamine and prostaglandins without releasing much tryptase. Many real patients are excluded.
Consensus-2 (Afrin and colleagues; first published 2011, restated 2020)
Requires:
- Typical mast-cell-mediator symptoms (same multi-system picture).
- Any single elevated mast cell marker — tryptase, urinary histamine metabolites, prostaglandin D2, leukotriene E4, chromogranin A, or heparin — OR a convincing clinical response to mast-cell-directed treatment.
This framework is broader and catches far more real-world patients. It was built by clinicians who were watching patients with textbook symptoms get turned away because of the tryptase-rise rule.
Which framework your doctor uses matters enormously. Most allergist-immunologists trained in the last decade default to Consensus-1 and will tell you “you don’t meet criteria.” mast cell activation syndrome-specialized physicians (often fewer in number and further away) tend toward Consensus-2. Patients often describe asking which of the two sets of criteria (Consensus-1 or Consensus-2) a clinician uses, because the answer decides whether they qualify.
The authors of each framework explain their own view. The Consensus-1 group (Valent and colleagues, 2019) writes that “overt MCAS is an unusual condition” and that many people referred because of suspected mast cell activation syndrome turn out to have other diseases (autoimmune, cancer-related or infectious), or allergic conditions that do not meet the criteria. The Consensus-2 group (Afrin and colleagues, 2021) writes that under-diagnosis by Consensus-1 seems the far larger problem and that, until research gives clearer answers, “diagnosis by either proposal is valid, reasonable, and helpful.”
3. Serum Tryptase
Order: “total serum tryptase.”
Baseline reference: <11.4 ng/mL is normal. Anything above that raises suspicion for hereditary alpha-tryptasemia (HαT) or systemic mastocytosis.
During a flare: draw within 1–4 hours of an acute reaction; the ideal window is 1–2 hours. Repeat at a quiet baseline 2–4 weeks later. The Consensus-1 diagnostic rise is ≥20% + 2 ng/mL above that personal baseline.
Tryptase is relatively forgiving on handling — it’s stable at room temperature for 24–48 hours, so sample mishandling is less of an issue than with other mast cell markers.
4. 24-Hour Urine N-Methylhistamine
For many patients this is the single most useful mast cell activation syndrome test — more useful than tryptase — because it captures accumulated histamine activity over an entire day rather than a single moment.
Order: “24-hour urine N-methylhistamine.” Offered by large reference laboratories.
How it works: you are given a large collection jug and asked to collect every urination for 24 hours. The jug must be kept in the refrigerator throughout the collection. Skip that step and the histamine degrades.
Reference cutoffs vary by lab. One large reference laboratory lists ≤230 µg/24 hr as normal. Because reference ranges differ, the range printed on the report itself is the one that applies to that result.
This test’s great advantage is that it is far less dependent on flare timing. If you have frequent low-grade activation, the histamine piles up across 24 hours and shows as an elevated metabolite — even if no single moment looked dramatic.
5. 24-Hour Urine Prostaglandin D2 Metabolite (11β-PGF2α)
PGD2 is a mast-cell-specific prostaglandin. Its urine metabolite 11β-prostaglandin F2α is one of the strongest indicators of mast cell activation syndrome when elevated, particularly in patients whose tryptase is stubbornly normal.
Order: “24-hour urine 11-beta-prostaglandin F2-alpha” (or “PGD2 metabolite”).
One reference laboratory’s range: roughly ≤3500 pg/mg creatinine (ranges vary by lab and method).
If your clinician doubts you, an elevated PGD2 metabolite is often the finding that tips the conversation. It is highly specific for mast cell activity.
6. 24-Hour Urine Leukotriene E4 (LTE4)
Leukotrienes drive airway and gastrointestinal symptoms. Elevated LTE4 is especially informative in patients with asthma, chronic rhinosinusitis, nasal polyps, or gastrointestinal-dominant mast cell activation syndrome.
One reference laboratory’s range: ≤104 pg/mg creatinine.
A positive LTE4 also hints that montelukast or zileuton may help — useful information for the treatment plan.
7. Chromogranin A
A serum test that rises in mast cell activation syndrome, systemic mastocytosis, and neuroendocrine tumors.
Critical caveat: proton pump inhibitors (PPIs) (omeprazole, pantoprazole, esomeprazole) produce falsely elevated chromogranin A. In 17 healthy volunteers, one week of a proton pump inhibitor (lansoprazole) raised chromogranin A about 2.5-fold; after the drug was stopped the level fell with a half-life of 4–5 days, and the authors concluded that about 2 weeks off the drug is needed to remove the effect (Mosli 2012). In a study of 196 people with neuroendocrine tumours, 19 had unexpectedly high chromogranin A and all of them took a proton pump inhibitor; chromogranin A fell by 82% in those who stopped all acid-lowering drugs and by 77% in those who switched to an H2 blocker, a difference that was not significant (Korse 2011). H2 blockers did not cause the same rise in that study.
8. Plasma Histamine
Generally not useful. Histamine’s 5-minute half-life means that unless you are drawing blood mid-anaphylaxis, the level will be normal. Plasma N-methylhistamine is slightly more durable but still inferior to the 24-hour urine version for practical use. For this reason the 24-hour urine N-methylhistamine is often used in place of plasma histamine.
9. Bone Marrow Biopsy
Reserved for suspected systemic mastocytosis, not routine mast cell activation syndrome. Indications include a persistently elevated baseline tryptase (often above 20 ng/mL), unexplained cytopenias, or hepatosplenomegaly. The biopsy looks for mast cell clusters, aberrant CD25 expression, and the KIT D816V mutation. Most mast cell activation syndrome patients never need this test.
10. Genetic Testing for Hereditary Alpha-Tryptasemia (HαT)
When a baseline tryptase runs above 8 ng/mL — even though that’s technically in the “normal” range — TPSAB1 copy number variant (CNV) testing is the test that looks for hereditary alpha-tryptasemia. Duplication or triplication of the TPSAB1 gene defines hereditary alpha-tryptasemia.
Labs: the assay is run by commercial genetic-testing laboratories. Most standard exome panels miss it because it’s a copy-number variant, not a point mutation.
Raised baseline tryptase is found in 4–6% of the general population, and in the 2016 study that defined hereditary alpha-tryptasemia, raised baseline tryptase was linked only to extra copies of the TPSAB1 gene (Lyons 2016). Hereditary alpha-tryptasemia is often reported alongside postural orthostatic tachycardia syndrome (POTS) and hypermobile Ehlers-Danlos syndrome (EDS). A 2025 systematic review searched four medical databases for studies of mast cell activation disorders or hereditary alpha-tryptasemia in people with POTS or Ehlers-Danlos syndrome. It screened 200 records and found no study that met its diagnostic criteria, so the often-described three-way link is not yet confirmed; one study came close, and the authors call for more research using strict, validated criteria (Farley 2025). See the Hereditary Alpha-Tryptasemia article for the full story.
11. Timing Strategy — The “Catch a Flare” Approach
Because mediator levels collapse between flares, the only reliable way to capture a positive result is to test while you are actively reacting, which is why patients often arrange it before a flare starts.
- During an acute reaction (within 1–4 hours): an urgent care, emergency room or arranged outpatient draw for (a) serum tryptase; (b) the start of the 24-hour urine collection (N-methylhistamine, PGD2 metabolite, LTE4).
- Baseline comparison (2–4 weeks later, when quiet): repeat the same panel. The delta is what makes the diagnosis under Consensus-1.
- Pre-emptive flare induction — a controlled food, temperature, or exercise challenge done only at an experienced mast cell activation syndrome center, then immediate testing. Rarely needed and carries real risk.
A standing order is one way patients describe handling this: some immunologists write a blood-draw order that lives in the chart, so that during a flare the patient can walk into a lab or emergency room and hand it over without negotiating.
12. What “All-Normal” Tests Mean
Perfectly normal tests do not rule out mast cell activation syndrome. This is the single most important sentence on this page. The next steps described in the literature and by patients:
- Repeat the panel during another flare. Timing is everything. A negative between-flare panel and a positive during-flare panel are two different experiments.
- Trial of mast-cell-targeted treatment. A convincing response — generally a ≥50% symptom improvement on an H1 + H2 blocker stack plus cromolyn or ketotifen — satisfies a Consensus-2 criterion on its own. This is diagnostically legitimate, not a placebo experiment.
- Expand to less-common markers: chymase, heparin (difficult to measure accurately), plasma PGD2, or a broader reference-laboratory mast cell activation syndrome panel.
- A mast cell activation syndrome-literate immunologist. Not all allergists read the mast cell activation syndrome literature. Patient advocacy groups (The Mastocytosis Society, TMS) maintain informal lists of clinicians known to take mast cell activation syndrome seriously.
One panel inside the reference range does not settle the question on its own.
13. Laboratories That Run Mast Cell Activation Syndrome Tests
- Large reference laboratories — run the mast cell activation syndrome panel, with their own reference ranges for N-methylhistamine, PGD2 metabolite and LTE4.
- Large commercial laboratories — offer the mainstream markers; sample-handling rules differ from lab to lab.
- A cancer center laboratory — historically referenced for specialized PGD2 assays.
- A commercial genetic-testing laboratory — TPSAB1 copy-number variant testing for HαT.
Sample handling requirements differ between laboratories. A single mishandled tube can waste a flare that may not return for months.
14. At-Home Test Kits (Limited Options)
- Direct-to-consumer mast cell activation syndrome panels — some include urinary histamine, PGD2 and LTE4. Insurance often denies coverage, so these are usually paid in cash.
- Direct-to-consumer histamine and immune panels — also sold by specialty laboratories.
Results from these kits are not always accepted by mainstream allergist-immunologists, who may view them as “not standardized.” Some patients use them as one more signal when mainstream labs keep coming back unremarkable.
15. Costs and Insurance
- Serum tryptase: $30–80, usually covered.
- 24-hour urine mediator panels: $150–400 per marker. Large reference laboratories are typically covered with prior authorization; commercial plans vary.
- TPSAB1 CNV testing: $300–600 cash; rarely covered by insurance.
- Prior authorization is often required. A letter from your clinician citing mast cell activation syndrome clinical criteria and the specific suspected mediator pattern materially improves approval odds.
When cost is a barrier, the order patients and clinicians commonly describe is: (1) serum tryptase during a flare + baseline pair, (2) 24-hour urine N-methylhistamine, (3) 24-hour urine PGD2 metabolite. That three-test bundle catches the majority of positives.
Key Research Papers
- Valent P, et al. Proposed diagnostic algorithm for patients with suspected mast cell activation syndrome. J Allergy Clin Immunol Pract. 2019;7(4):1125–1133. — doi:10.1016/j.jaip.2019.01.006
- Afrin LB, et al. Diagnosis of mast cell activation syndrome: a global “consensus-2.” Diagnosis (Berl). 2021;8(2):137–152. — doi:10.1515/dx-2020-0005
- Weiler CR, Austen KF, Akin C, et al. AAAAI Mast Cell Disorders Committee Work Group Report: mast cell activation syndrome (MCAS) diagnosis and management. J Allergy Clin Immunol. 2019;144(4):883–896. — doi:10.1016/j.jaci.2019.08.023
- Lyons JJ, et al. Elevated basal serum tryptase identifies a multisystem disorder associated with increased TPSAB1 copy number. Nat Genet. 2016;48(12):1564–1569. — doi:10.1038/ng.3696
- Valent P, Akin C, Arock M, et al. Definitions, criteria and global classification of mast cell disorders with special reference to mast cell activation syndromes: a consensus proposal. Int Arch Allergy Immunol. 2012;157(3):215–225. — doi:10.1159/000328760
- Farley M, Estrada-Mendizabal RJ, Gansert EA, et al. Prevalence of mast cell activation disorders and hereditary alpha tryptasemia among patients with postural orthostatic tachycardia syndrome and Ehlers-Danlos syndrome: a systematic review. Ann Allergy Asthma Immunol. 2025;135(1):97–102. — doi:10.1016/j.anai.2025.03.022
- Mosli HH, Dennis A, Kocha W, et al. Effect of short-term proton pump inhibitor treatment and its discontinuation on chromogranin A in healthy subjects. J Clin Endocrinol Metab. 2012;97(9):E1731–E1735. — doi:10.1210/jc.2012-1548
- Korse CM, Muller M, Taal BG. Discontinuation of proton pump inhibitors during assessment of chromogranin A levels in patients with neuroendocrine tumours. Br J Cancer. 2011;105(8):1173–1175. — doi:10.1038/bjc.2011.380
PubMed Topic Searches
Curated PubMed topic searches of peer-reviewed literature on mast cell activation syndrome testing. Each link opens a live PubMed query so you always see the most current studies.
Connections
- Neurology
- Mast Cell Activation Syndrome Overview
- Hereditary Alpha-Tryptasemia
- H1 and H2 Blocker Stacks
- Cromolyn and Ketotifen Protocols
- Alpha-Gal Syndrome
- Postural Orthostatic Tachycardia Syndrome
- Triggers and Flare Management
- Natural Mast Cell Stabilizers
- Low-Histamine Diet
- Mediators and Symptom Map
- Allergies
- Small Intestinal Bacterial Overgrowth
- Ehlers-Danlos Syndrome
- Chronic Fatigue Syndrome (Myalgic Encephalomyelitis/Chronic Fatigue Syndrome)
- Hormone Sensitivity: Estrogen & Menstrual Flares
- Postural Orthostatic Tachycardia Syndrome Mast Cell Activation Syndrome Ehlers-Danlos Syndrome Triad
- Postural Orthostatic Tachycardia Syndrome Mast Cell Activation Syndrome and the Ehlers-Danlos Syndrome Triad
- Tryptase — the lab test itself: reference ranges, draw timing, and what a baseline value means.