⚠ Evidence warning: Clinical trials or other evidence do not support the claims that estradiol lowers the mast cell trigger threshold in people, that mast cell activation syndrome flares follow the menstrual cycle and calm in pregnancy, and that quercetin, luteolin and vitamin C calm flares. This page keeps it as a report of what people, websites or other media say.
Mast Cell Activation Syndrome (MCAS) Hormone Sensitivity: Estrogen & Menstrual Flares
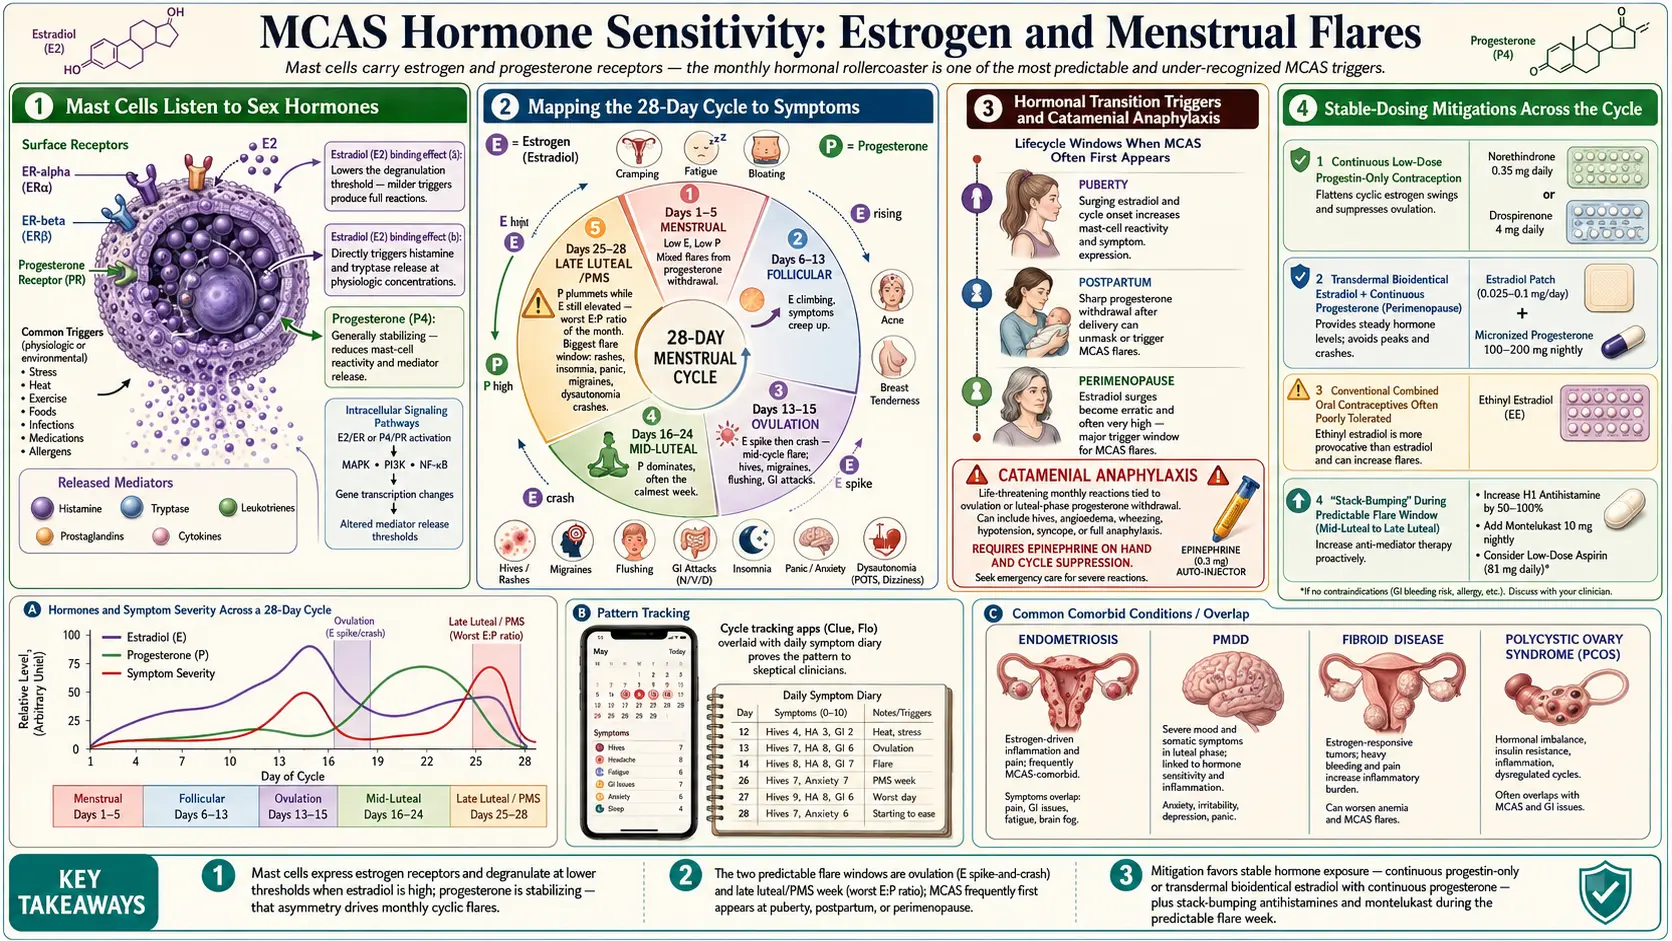
If your mast cell activation syndrome (MCAS) symptoms seem to have a rhythm — worse the week before your period, calmer during pregnancy, suddenly explosive in perimenopause — you are not imagining it. Mast cells are exquisitely tuned to sex hormones, and the monthly estrogen rollercoaster is one of the most common, most predictable, and most under-recognized triggers in mast cell disease. This page describes why, how people track it, and what people and practitioners report using.
Table of Contents
- Mast Cells Have Estrogen & Progesterone Receptors
- Mapping the Cycle to Your Symptoms
- Why Mast Cell Activation Syndrome Often Appears at Puberty, Postpartum, or Perimenopause
- Catamenial Anaphylaxis — When Your Period Is Life-Threatening
- Cycle Tracking: How to Prove It to Yourself (and Your Doctor)
- Contraception When You Have Mast Cell Activation Syndrome
- Pregnancy, Postpartum & Mast Cell Activation Syndrome
- Perimenopause, Menopause & Mast Cell Activation Syndrome-Friendly Hormone Replacement Therapy
- Endometriosis & PMDD Overlap
- Practical Mitigation: Stable Dosing Across the Cycle
- Key Research Papers
- PubMed Topic Searches
- Connections
- Featured Videos
Mast Cells Have Estrogen & Progesterone Receptors
Mast cells are not passive bystanders of your hormones — they listen closely. On their surface and inside their cytoplasm they express estrogen receptors (ER-alpha and ER-beta) and progesterone receptors. When estradiol binds, it does two things that matter to you:
- It lowers the threshold for degranulation. Estradiol is described as priming mast cells so a trigger that would normally cause mild flushing now causes a full histamine dump — hives, tachycardia, gastrointestinal (GI) cramping, brain fog. The study behind this is cell culture only: estradiol enhanced IgE-dependent mast cell activation in culture (Zaitsu 2007).
- It can directly trigger release. Estradiol all by itself is described as causing histamine and tryptase release from mast cells. What Zaitsu 2007 measured was different: at physiologic concentrations, estradiol alone caused partial release of the granule protein beta-hexosaminidase, and also leukotriene C4 in one line, from two mast cell/basophil cell lines (RBL-2H3 and HMC-1) and primary cultures of bone marrow derived mast cells.
Progesterone, by contrast, is generally stabilizing. It reduces mast-cell reactivity and tends to calm mediator release. This asymmetry — estrogen stirs, progesterone settles — is the physiologic engine behind almost every pattern discussed on this page.
The evidence behind this picture comes from the laboratory. The progesterone result comes from purified rat mast cells: progesterone at 100 nM reduced histamine secretion (Vasiadi 2006). In a mouse study of anaphylaxis, reactions were stronger in females, disappeared after an estrogen blocker or ovary removal, and returned with estradiol; estrogen did not affect mast cell responsiveness, and the effect ran through nitric oxide made by blood vessels (Hox 2015). This is an animal result. A 2012 review also describes both estradiol and progesterone inducing mast cell maturation and degranulation in the uterus (Zierau 2012), so "estrogen stirs, progesterone settles" is not the whole picture. How far these laboratory findings apply to people with mast cell activation syndrome is not known.
Mapping the Cycle to Your Symptoms
A textbook 28-day cycle has two estrogen peaks and one progesterone peak. Your mast cell activation syndrome symptoms usually track them like this:
- Days 1–5 (menstrual phase). Both hormones are low. Some patients are relatively calm here; others flare from the sudden progesterone withdrawal that triggered the bleed.
- Days 6–13 (follicular/late follicular). Estrogen climbs. Symptoms creep up.
- Days 13–15 (ovulation). Estrogen spikes sharply, then falls. This is the mid-cycle flare window — hives, migraines, flushing, gastrointestinal attacks, sometimes frank anaphylactoid reactions.
- Days 16–24 (mid-luteal). Progesterone dominates. Many mast cell activation syndrome patients feel their best here.
- Days 25–28 (late luteal/premenstrual syndrome window). Progesterone plummets while estrogen is still elevated — the estrogen-to-progesterone ratio is at its worst. This is the single biggest mast cell activation syndrome flare window of the month: rashes, insomnia, panic surges, migraines, diarrhea, joint pain, dysautonomia crashes.
Some people whose worst week is the week before their period, and who always thought of it as "bad premenstrual syndrome," come to see it as a hormone-mast-cell event, and practitioners describe treating the two differently.
Why Mast Cell Activation Syndrome Often Appears at Puberty, Postpartum, or Perimenopause
Mast cell activation syndrome rarely announces itself out of nowhere. It almost always has a precipitating event, and in women and patients assigned female at birth the precipitant is frequently a hormonal transition:
- Puberty. A nervous system that tolerated food, exercise, and stress through childhood suddenly develops hives, postural orthostatic tachycardia syndrome (POTS), irritable bowel syndrome (IBS), or migraines the year estrogen comes online.
- Pregnancy & postpartum. Some patients actually feel better while pregnant (high progesterone), then collapse in the six to twelve weeks after delivery as estrogen and progesterone both crash to near-zero. Sleep deprivation, blood loss, and immune reset pile on.
- Perimenopause. Not the low-estrogen stage people expect — it is the wildly fluctuating stage, typically ages 40–52. Estradiol can spike 2–3x normal one week and crash below postmenopausal levels the next. Mast cells, which prefer steady signals, go haywire.
- Surgical menopause. Sudden ovary removal is the most abrupt hormone cliff a body can experience and is a classic mast cell activation syndrome-unmasking event.
If your timeline shows a healthy decade followed by a symptom explosion that lines up with one of these transitions, hormone-driven mast cell activation is a leading suspect.
Catamenial Anaphylaxis — When Your Period Is Life-Threatening
Catamenial anaphylaxis is anaphylaxis tied directly to the menstrual cycle, classically occurring in the late luteal phase or the first days of bleeding. It has been reported in the medical literature since at least the 1980s (Meggs 1984; Slater 1987), and a 2013 series still calls the reports few and the condition uncommon and probably under-recognized. Proposed mechanisms include progesterone withdrawal, direct sensitivity to endogenous progesterone (autoimmune progesterone dermatitis), and estrogen-primed mast cell instability.
Signs that your monthly flare has crossed into catamenial anaphylaxis territory:
- Throat tightness, lip/tongue swelling, or trouble swallowing in a predictable cycle window.
- Sudden hypotension, near-syncope, or presyncope that tracks your cycle.
- Widespread urticaria plus wheeze or gastrointestinal collapse cyclically.
- Need for epinephrine or emergency room visits that cluster around ovulation or pre-menses.
These are signs of anaphylaxis, which hospitals treat as an emergency. Practitioners describe people at risk carrying two epinephrine auto-injectors. Suppression of ovulation (continuous progestin, gonadotropin-releasing hormone (GnRH) analogues) is sometimes described as the treatment that finally breaks the cycle.
What the published cases report:
- A series of 8 women (Bauer 2013). The median age at onset was 34 and the median was 10 attacks before diagnosis. Skin tests for progesterone were negative in 3 of the 4 tested. High-dose steroids, ketotifen and oral contraceptives did not control the attacks and antihistamines failed in 7, while others responded to leuprolide, medroxyprogesterone or removal of the tubes and ovaries. Systemic mastocytosis was ruled out in all of them.
- A very small randomized double-blind trial (Slater 1987). Two of 4 women with recurrent anaphylaxis went into remission on a drug that shuts down the ovaries (a luteinizing hormone-releasing hormone agonist). Both responders had reacted to provocation tests beforehand.
- Autoimmune progesterone dermatitis (Lipman 2022). A systematic review of 132 cases found that treatments which suppress ovulation, and surgery, had the most success, while antihistamines and systemic steroids frequently gave no relief.
Cycle Tracking: How to Prove It to Yourself (and Your Doctor)
Doctors are trained to be skeptical of "my symptoms are hormonal." Data wins arguments. People who track usually record at least two full cycles, ideally three:
- Cycle day. Day 1 is counted as the first day of full flow.
- Symptom score 0–10 for each of: flushing, hives, gastrointestinal, migraine, brain fog, postural orthostatic tachycardia syndrome/tachycardia, mood.
- Ovulation marker. Luteinizing hormone (LH) strips, basal body temperature, or a tracking app. Ovulation lets you label the luteal phase precisely.
- Medication & food held as constant as possible so the cycle pattern is isolated from lifestyle noise.
When plotted, peaks that line up at ovulation and the late luteal window across multiple cycles make a defensible case for hormone-driven mast cell activation syndrome and a target for intervention.
Contraception When You Have Mast Cell Activation Syndrome
This is one of the most common questions mast cell activation syndrome patients ask, and the honest answer is: it depends, and you may need to try more than one.
- Combined oral contraceptives (estrogen + progestin). The daily estrogen dose, especially ethinyl estradiol, can provoke worse mast cell activation syndrome symptoms in sensitive patients. Some tolerate them fine, but for many the first three cycles on a combined pill are miserable.
- Progestin-only options. Low-dose progestin-only pills ("mini-pill"), the etonogestrel implant, levonorgestrel intrauterine devices, or depot medroxyprogesterone acetate avoid the exogenous estrogen load. Many mast cell activation syndrome patients are reported to do noticeably better on these. The known exception is progesterone hypersensitivity: people with it can react to progestins, and one case report describes autoimmune progesterone dermatitis after an intrauterine device was placed, treated by removing the device and giving tamoxifen (Alheeh 2024). That is a single case.
- Continuous / no-placebo regimens. Taking an active pill every day with no withdrawal week eliminates the monthly hormone crash and the flare it drives. Works with either combined or progestin-only formulations.
- Levonorgestrel intrauterine device. Often well tolerated because systemic hormone levels stay low while local endometrial progestin suppresses bleeding and ovulation in a meaningful fraction of users.
- Non-hormonal. Copper intrauterine device, barrier methods, or tubal options sidestep the hormonal question entirely — but do not address the endogenous cycle flares, which is fine if those are mild.
Patients describe naming mast cell activation syndrome and mast-cell instability as the constraint when discussing contraception. They report that a prescriber who has never heard of mast cell activation syndrome will default to combined pills, and that one who understands it will usually start with a progestin-only or intrauterine device approach.
Pregnancy, Postpartum & Mast Cell Activation Syndrome
Pregnancy is a natural experiment in high-progesterone physiology. For many mast cell activation syndrome patients, the first trimester is rough — nausea, histamine-intolerance foods newly intolerable, migraines — but the second and third trimesters often bring dramatic improvement. Progesterone rises roughly 10-fold by term, and the normal immune tilt of pregnancy (away from Th1, toward tolerogenic Th2/regulatory signaling) appears to quiet mast cells along with everything else.
The postpartum period is the mirror image. Within 48–72 hours of delivery, progesterone drops from its peak to nearly undetectable levels. Estrogen falls similarly. Patients who glided through the third trimester can crash in the first two weeks postpartum with hives, rage-level insomnia, skin-crawling anxiety, gastrointestinal chaos, and a dysautonomia flare that overlaps with postpartum depression. This is not in your head; it is one of the most extreme hormone transitions in human physiology, and mast cells are described as reacting to it.
What practitioners describe planning for:
- Antihistamines through pregnancy. Most H1 blockers (cetirizine, loratadine) and H2 blockers (famotidine) are generally described as compatible with pregnancy and breastfeeding. The labels are more cautious: the over-the-counter cetirizine label states "if breast-feeding: not recommended" and, in pregnancy, to ask a health professional; the loratadine label says to ask a health professional in pregnancy or breastfeeding; the famotidine label states available data in pregnant women are insufficient to establish a drug-associated risk, and that there are limited data on famotidine in breast milk.
- Cromolyn. Oral cromolyn is minimally absorbed and is often considered one of the safer mast-cell stabilizers in pregnancy. See the cromolyn and ketotifen protocols.
- Postpartum. Practitioners describe keeping medication steady in the last trimester even when symptoms ease, keeping the baseline stack in place, and expecting a bumpier postpartum than a typical patient.
- Epinephrine readiness. Practitioners describe people with a history of anaphylaxis carrying auto-injectors and reviewing the anesthesia plan with the delivery team in advance.
Perimenopause, Menopause & Mast Cell Activation Syndrome-Friendly Hormone Replacement Therapy
Perimenopause is where many women receive their first formal mast cell activation syndrome diagnosis, often after decades of being told their symptoms were "just anxiety." The wild estrogen swings of the 40s do two things at once: they directly destabilize mast cells, and they unmask latent sensitivities (to foods, fragrances, weather) that a younger, more stable endocrine system was masking.
The question of hormone replacement is nuanced. Done poorly, hormone replacement therapy (HRT) makes mast cell activation syndrome worse. Done well, it can be stabilizing because it replaces chaotic hormonal surges with a steady baseline.
Mast cell activation syndrome-friendlier hormone replacement therapy principles as practitioners describe them. The safety fact behind all of them: the estradiol patch label carries a boxed warning for endometrial cancer, cardiovascular disorders, probable dementia and breast cancer.
- Transdermal estradiol (patch, gel, or spray) rather than oral estradiol. Bypasses first-pass liver metabolism, gives smoother blood levels, and avoids the oral-estrogen inflammatory signature.
- Lowest effective dose. Starting low (e.g., a 0.025 mg/day patch) and titrating by symptoms, not a preset target.
- Oral micronized progesterone (not synthetic progestins) taken nightly, cyclically or continuously. Bioidentical progesterone is generally better tolerated by mast cells than medroxyprogesterone or norethindrone.
- Continuous, not cyclic. Daily dosing without a withdrawal bleed eliminates monthly crashes.
- Slow introduction. Practitioners describe pre-medicating with an H1/H2 stack for the first two weeks. Flares in the first month do not necessarily mean a person cannot tolerate hormone replacement therapy — they often settle as the system re-stabilizes.
For readers who want the broader menopause picture beyond mast cell activation syndrome, see Menopause & hormone replacement therapy and Perimenopause.
Gonadotropin-Releasing Hormone Agonists and Letrozole — Last-Resort Options
In refractory hormone-driven mast cell activation syndrome — especially with catamenial anaphylaxis, severe endometriosis, or perimenopausal flares that do not respond to anything else — clinicians occasionally reach for cycle suppression with gonadotropin-releasing hormone agonists (leuprolide) or aromatase inhibitors (letrozole). Both drive estrogen to near-zero. Some patients with hormone-flare mast cell activation syndrome find this transformational; others tolerate the medically induced menopause poorly. These are specialist-level interventions, usually short-term, often paired with low-dose add-back hormone replacement therapy to protect bone.
Endometriosis & PMDD Overlap
Two conditions overlap heavily with hormone-sensitive mast cell activation syndrome and are often looked for when the cycle-symptom pattern is strong.
Endometriosis. Endometriotic lesions contain elevated mast-cell densities, and the chronic pelvic pain of endometriosis is partly a mast-cell neuroinflammatory phenomenon. Mast cell activation syndrome patients with severe cyclic pelvic pain, dyspareunia, or infertility are commonly evaluated for endometriosis. See Endometriosis.
PMDD (premenstrual dysphoric disorder). Severe late-luteal mood, anxiety, and somatic symptoms with a clean cycle-locked pattern. Mast cell mediators (histamine, prostaglandin D2, leukotrienes, tumor necrosis factor-alpha) are plausible contributors to the "PMDD" phenotype in mast cell activation syndrome patients, and treating the mast cell side sometimes resolves what was labeled PMDD for years.
Practical Mitigation: Stable Dosing Across the Cycle
What people and practitioners report doing without a prescription change:
- H1/H2 doses kept up in "good weeks." People describe the most common mistake as tapering antihistamines when feeling fine mid-luteal, then getting blindsided by a pre-menstrual flare with no cover. They describe holding a stable baseline (e.g., cetirizine 10 mg in the morning, famotidine 20–40 mg twice daily) every single day. See H1 & H2 blocker stacks.
- Pre-emptive bump in the late luteal window. Some clinicians add a second daily H1 (e.g., fexofenadine in the afternoon), add an H2 dose, or add ketotifen starting three to five days before expected symptom onset. See cromolyn and ketotifen protocols.
- Oral cromolyn 30–60 minutes before meals during the flare week, reported to quiet gastrointestinal mast cells in particular.
- Quercetin 500–1000 mg twice daily is a classic flavonoid mast-cell stabilizer. Many patients report starting it five to seven days before their expected flare.
- Luteolin (often combined with rutin) has supportive evidence for mast-cell and neuroinflammatory calming and is useful when brain fog and anxiety dominate the luteal pattern.
- Vitamin C 1–2 g/day in divided doses supports histamine catabolism.
- A tighter low-histamine diet during the flare week, reported even by people who tolerate more foods at mid-luteal. See Low-Histamine Diet.
- Sleep. Short sleep is reported to amplify histamine-driven symptoms, and people describe the late-luteal window as the week when this matters most.
- Alcohol at ovulation and pre-menses. Alcohol is described as blocking DAO (diamine oxidase), the enzyme that clears histamine, right when estrogen is described as already giving mast cells the green light; people report leaving it out at these times.
For the broader stabilizer toolkit see Natural Mast Cell Stabilizers and Triggers & Flare Management.
Key Research Papers
- Zaitsu M, et al. Estradiol activates mast cells via a non-genomic estrogen receptor-alpha and calcium influx. Mol Immunol. 2007. — doi:10.1016/j.molimm.2006.09.030 · PubMed PMID: 17084457
- Bonds RS, Midoro-Horiuti T. Estrogen effects in allergy and asthma. Curr Opin Allergy Clin Immunol. 2013;13:92-99. — doi:10.1097/aci.0b013e32835a6dd6 · PubMed PMID: 23090385
- Vasiadi M, Kempuraj D, Boucher W, Kalogeromitros D, Theoharides TC. Progesterone inhibits mast cell secretion. Int J Immunopathol Pharmacol. 2006;19:787-794. — PubMed PMID: 17166400
- Bauer CS, Kampitak T, Messieh ML, Kelly KJ, Vadas P. Heterogeneity in presentation and treatment of catamenial anaphylaxis. Ann Allergy Asthma Immunol. 2013;111:107-111. — PubMed PMID: 23886228
- Reviews of mast cell estrogen receptor biology (ER-alpha, ER-beta). — Search PubMed
- Autoimmune progesterone dermatitis case series and pathophysiology. — Search PubMed
- Meggs WJ, Pescovitz OH, Metcalfe D, Loriaux DL, Cutler G Jr, Kaliner M. Progesterone sensitivity as a cause of recurrent anaphylaxis. N Engl J Med. 1984;311:1236-1238. — PubMed PMID: 6149462
- Slater JE, Raphael G, Cutler GB Jr, Loriaux DL, Meggs WJ, Kaliner M. Recurrent anaphylaxis in menstruating women: treatment with a luteinizing hormone-releasing hormone agonist--a preliminary report. Obstet Gynecol. 1987;70:542-546. — PubMed PMID: 3306508
- Lipman ZM, Labib A, Vander Does A, Yosipovitch G. Autoimmune Progesterone Dermatitis: A Systematic Review. Dermatitis. 2022;33:249-256. — PubMed PMID: 34405830
- Hox V, Desai A, Bandara G, Gilfillan AM, Metcalfe DD, Olivera A. Estrogen increases the severity of anaphylaxis in female mice through enhanced endothelial nitric oxide synthase expression and nitric oxide production. J Allergy Clin Immunol. 2015;135:729-736. — PubMed PMID: 25553642
- Zierau O, Zenclussen AC, Jensen F. Role of female sex hormones, estradiol and progesterone, in mast cell behavior. Front Immunol. 2012;3:169. — PubMed PMID: 22723800
- Alheeh I, Shalalfeh N, Wajeeh S, Farah R, Farah R. A Case of Autoimmune progesterone dermatitis post-intrauterine device placement in rural occupied Palestine. SAGE Open Med Case Rep. 2024;12:2050313X241283601. — PubMed PMID: 39345830
PubMed Topic Searches
For further reading, these PubMed searches return current peer-reviewed work on hormone-mast-cell biology, cycle-driven symptoms, and treatment:
- Estrogen and mast cell degranulation
- Progesterone and mast cell stabilization
- Catamenial anaphylaxis
- Perimenopause, histamine, and mast cells
- Pregnancy and mast cell activation syndrome
- Endometriosis and mast cells
- PMDD and histamine
- Transdermal estradiol and micronized progesterone
- Gonadotropin-releasing hormone agonists in catamenial anaphylaxis
- Quercetin and luteolin as mast cell stabilizers
Connections
- Neurology
- Mast Cell Activation Syndrome Overview
- Perimenopause
- Endometriosis
- Menopause and Hormone Replacement Therapy
- Cromolyn and Ketotifen Protocols
- Natural Mast Cell Stabilizers
- Triggers and Flare Management
- Low-Histamine Diet
- H1 and H2 Blocker Stacks
- Mast Cell Activation Syndrome Testing Guide
- Hereditary Alpha-Tryptasemia
- Mediators and Symptom Map
- Postural Orthostatic Tachycardia Syndrome
- Alpha-Gal Syndrome
- Anxiety
- Quercetin
- Brain Fog