Mast Cell Activation Syndrome (MCAS) Mediators and Symptom Map
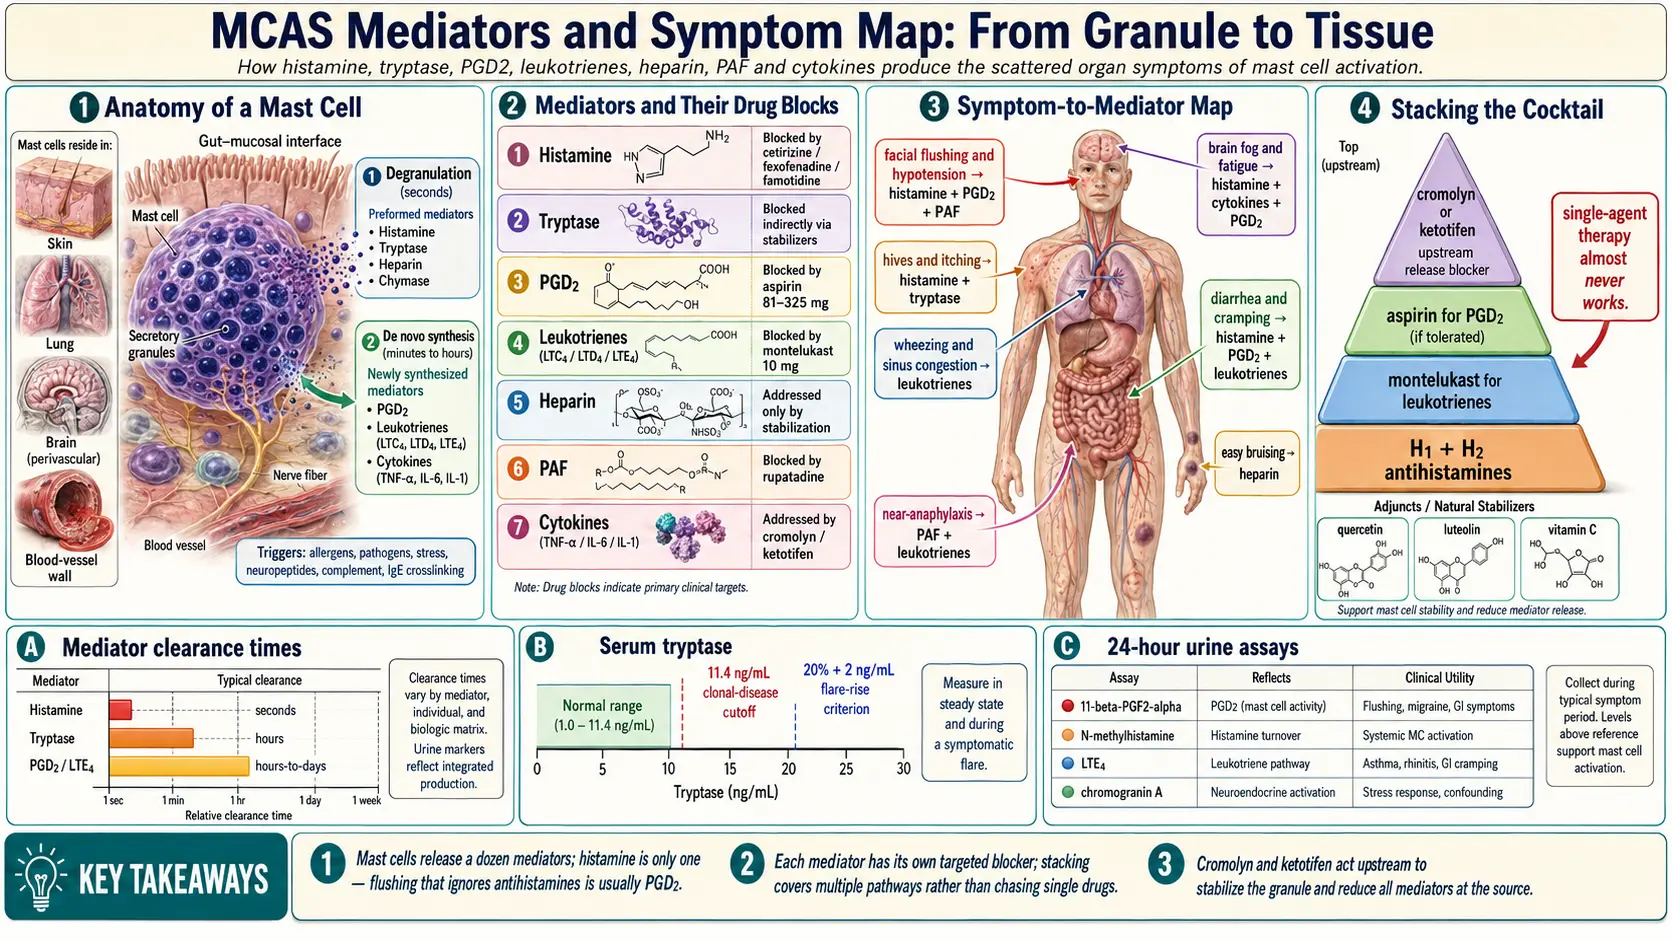
Table of Contents
- What a Mast Cell Is
- The Two Release Modes
- Histamine
- Tryptase
- Prostaglandin D2 (PGD2)
- Leukotrienes (LTC4, LTD4, LTE4)
- Heparin
- Chromogranin A
- Chymase
- Tumor Necrosis Factor-alpha, Interleukin-6, Interleukin-1
- Platelet Activating Factor (PAF)
- A Quick Symptom-to-Mediator Map
- Why Targeting the Right Mediator Matters
- Stacking Medications to Cover Multiple Mediators
- Mediators Amplified by Hormones, Stress, Infection
- Key Research Papers
- Connections
- Featured Videos
1. What a Mast Cell Is
Mast cells are immune cells stationed at every tissue-environment interface in your body — the skin, the lining of the gut, the airways of the lungs, the nasal passages, the brain's perivascular spaces, and the walls of your blood vessels. They sit exactly where the outside world meets the inside of you, and their job is to notice threats and sound the alarm.
Each mast cell holds thousands of tiny packets called granules, pre-loaded with chemical messengers. When a mast cell is triggered, it releases those chemicals — which is how you fight off parasites, seal a wound, or mount an allergic reaction. In a healthy person, the release is proportionate to the threat.
In Mast Cell Activation Syndrome (MCAS), that release is no longer proportionate. The cells either leak mediators continuously at a low level — giving you the nagging daily symptoms many patients describe as "always running at 30% sick" — or they fire off massive bursts during flares, producing hives, flushing, brain fog, diarrhea, and near-anaphylactic drops in blood pressure all at once. Understanding which chemicals they release is the key to understanding why your symptoms look so scattered and to choosing the right medications to block them.
2. The Two Release Modes
Mast cells have two distinct ways of releasing their chemicals, and the difference explains why mast cell activation syndrome flares have both an immediate phase and a delayed tail.
Degranulation (seconds)
Preformed mediators already packaged inside granules are dumped out within seconds of triggering. This is the source of the immediate flare: the sudden flush, the pounding heart, the itching, the hive that erupts in under a minute. The chemicals released this way include histamine, tryptase, heparin, and chymase.
De novo synthesis (minutes to hours)
Newly manufactured mediators are assembled on demand from membrane lipids and from gene expression. These take minutes to hours to peak and are responsible for the delayed and sustained symptoms — the brain fog that sets in 90 minutes after a meal, the fatigue that hits the next day, the wheeze that builds slowly overnight. Prostaglandins, leukotrienes, and cytokines are made this way.
Most mast cell activation syndrome patients feel both phases — which is why a flare from one exposure can last 24 to 72 hours.
3. Histamine — the mediator most people think of
Histamine is the chemical that allergy medication ads have made famous. It is preformed, stored in granules, and released within seconds. It acts on four receptor subtypes (H1, H2, H3, H4) scattered across almost every organ.
What it does: widens blood vessels (vasodilation), makes capillaries leaky (vascular permeability), triggers itching on nerve endings, contracts smooth muscle in the lungs and gut, stimulates gastric acid secretion (H2), and modulates neurotransmitters in the brain (H3).
Symptoms driven by histamine: flushing, urticaria (hives), itching, vascular headache, runny nose, nasal congestion, gastrointestinal (GI) cramping, diarrhea, bloating, gastric reflux, hypotension, palpitations, anxiety, insomnia, vertigo, and urinary urgency.
Blocked by: H1 antihistamines (cetirizine, fexofenadine, loratadine, hydroxyzine) combined with H2 antihistamines (famotidine, cimetidine). See H1 and H2 Blocker Stacks for dosing.
4. Tryptase — the most-measured marker of mast cell activity
Tryptase is a protein-cutting enzyme stored almost exclusively in mast cells, which is what makes it such a valuable diagnostic marker — if your tryptase is rising, a mast cell is almost certainly responsible.
What it does: cleaves tissue proteins, activates PAR-2 receptors on nerve endings and epithelium (triggering pain and inflammation locally), and amplifies the activity of other inflammatory molecules in its neighborhood. Chronic high tryptase is believed to contribute to small-fiber neuropathy by sensitizing peripheral nerves.
Symptoms driven by tryptase: itching, burning pain, flushing (indirect via kinin activation), bronchoconstriction, vascular permeability, neuropathic pain, and nerve-fiber sensitization.
Measured: serum total tryptase. A baseline above 11.4 ng/mL is above the usual reference range; it is seen in hereditary alpha-tryptasemia (an inherited trait caused by extra copies of the TPSAB1 gene, found in 4–6% of people) and in mastocytosis (a clonal mast cell disease). A transient rise of at least 20% plus 2 ng/mL during a flare is one of the accepted criteria for mast cell activation syndrome. 24-hour urine is not useful for tryptase. See Testing Guide.
5. Prostaglandin D2 (PGD2) — the most underestimated driver of Mast Cell Activation Syndrome flares
If histamine is famous, PGD2 is the one that actually drives many of the hardest-to-treat symptoms. It is not preformed — it is synthesized on demand from arachidonic acid — so it peaks later in a flare and lasts longer.
What it does: powerful vasodilation, bronchoconstriction, sleep induction, platelet inhibition.
Symptoms driven by PGD2: facial flushing (especially the bright, warm kind that does not respond to antihistamines), hypotension, tachycardia, gastrointestinal cramping, diarrhea, migraine, brain fog, and somnolence after meals (the "post-meal coma" many mast cell activation syndrome patients describe).
Blocked by: aspirin or other nonsteroidal anti-inflammatory drugs (NSAIDs) when tolerated. Clinicians who write about "aspirin-responsive mast cell activation syndrome" describe these patients as mostly PGD2-dominant — their symptoms come from prostaglandin synthesis rather than histamine — and report aspirin doses of 81–325 mg. Aspirin can itself set off reactions in mast cell disease: in a 2018 placebo-controlled challenge study of 50 adults with mastocytosis, aspirin (up to 520 mg) caused hives in 1, and 8 of 191 patients in the same clinic's records (4.1%) had reacted to an NSAID, 3 of them severely. Aspirin also raises the risk of bleeding.
Measured: 24-hour urine 11β-PGF2α, a stable metabolite of PGD2, is the usual test.
6. Leukotrienes (LTC4, LTD4, LTE4) — the asthma-respiratory mediators
The leukotrienes are another family of lipid mediators synthesized on demand. They are the main drivers of the respiratory and allergic-shock components of mast cell activation syndrome.
What they do: potent bronchoconstriction (roughly 1,000 times more potent than histamine on airway smooth muscle), mucus production, vascular permeability, and chemotaxis — they actively recruit more immune cells to the site, escalating a local reaction into a systemic one.
Symptoms driven by leukotrienes: wheezing, chest tightness, cough, chronic rhinosinusitis, nasal polyps, gastrointestinal spasm, and severity of anaphylactic shock.
Blocked by: montelukast 10 mg daily or zafirlukast. Practitioners describe montelukast as helping with stubborn chest tightness and sinus congestion that antihistamines alone do not relieve. Since 2020 the montelukast label has carried an FDA boxed warning for serious neuropsychiatric events, including agitation, aggression, depression, sleep disturbances and suicidal thoughts and behavior. See H1 and H2 Blocker Stacks.
Measured: 24-hour urine LTE4.
7. Heparin — the bleeding mediator
Heparin is best known as an injectable anticoagulant drug — but it is naturally made by mast cells and stored in their granules. During mast cell activation, small amounts are released locally, enough to affect clotting.
What it does: inhibits the coagulation cascade and thins blood locally.
Symptoms driven by heparin: easy bruising, prolonged bleeding after minor cuts or dental work, hemorrhagic or unusually heavy menses, and unexplained hematomas after bumps.
Heparin is not directly blocked by any mast cell activation syndrome medication. It is addressed by stabilizing the mast cells overall so less is released in the first place.
8. Chromogranin A
Chromogranin A is an adjunct marker — a protein that is packaged into granules alongside the main mediators and spilled out when they are released. It does not directly cause a recognizable symptom, but its level in blood rises with mast cell activity. It is also elevated in neuroendocrine tumors, so it is interpreted alongside other markers. Useful for confirming that activation is happening when tryptase is stubbornly normal.
9. Chymase
Chymase is another protease, similar to tryptase, and drives tissue remodeling, scarring, and fibrosis over time. Patients with long-standing, untreated mast cell activation syndrome may develop chronic tissue changes — thickened gut walls, fibrotic skin, cardiac stiffness — traceable in part to chymase. Practitioners cite this as a reason to start mast-cell stabilization early.
10. Tumor Necrosis Factor-alpha, Interleukin-6, Interleukin-1
These are the cytokines — small signaling proteins that coordinate a systemic inflammatory response. Mast cells synthesize and release them over hours following activation.
Symptoms driven by cytokines: flu-like malaise, fatigue, low-grade fever or chills, brain fog, depression, post-exertional malaise, and diffuse body aches. These are exactly the symptoms that overlap with long COVID and myalgic encephalomyelitis/chronic fatigue syndrome (ME/CFS), and the cytokine pathway is thought to be a major point of overlap between those conditions and mast cell activation syndrome.
11. Platelet Activating Factor (PAF)
PAF is a lipid mediator that is extremely potent at low concentrations. It is a powerful vasodilator and bronchoconstrictor, and a 2008 study found that blood PAF levels rose with the severity of anaphylaxis — the life-threatening reaction whose drop in blood pressure goes beyond what histamine alone can explain.
Patients whose reactions escalate to near-anaphylaxis despite good H1/H2 coverage often have a PAF-heavy component. Rupatadine is a second-generation antihistamine that also has anti-PAF activity and is used in some countries for this purpose.
12. A Quick Symptom-to-Mediator Map
This map links each symptom to its likely mediators, and so to the medicines that target them.
- Flushing + hypotension → histamine + PGD2 + PAF
- Diarrhea + cramping → histamine + PGD2 + leukotrienes
- Hives + itching → histamine (primary) + tryptase
- Brain fog + fatigue → histamine + cytokines (tumor necrosis factor-α, interleukin-6) + PGD2
- Wheezing + sinus congestion → leukotrienes + histamine
- Easy bruising → heparin
- Anxiety + insomnia → histamine (H1/H3 in brain) + PGD2
- Food reactions → histamine + tryptase + leukotrienes
- Menstrual flares → estrogen amplifies release of all mediators
- Near-anaphylaxis → PAF + leukotrienes + histamine
- Chronic nerve pain → tryptase + chymase
13. Why Targeting the Right Mediator Matters
The most common mast cell activation syndrome disappointment is the patient who takes Cetirizine and Famotidine for three months, sees partial improvement, and assumes that is as good as it gets. Often the remaining symptoms — the flushing, the diarrhea, the wheeze — are not being driven by histamine at all.
A classic example: flushing that does not respond to H1 or H2 antihistamines is almost always PGD2-dominant and is described as responding to low-dose aspirin. Diarrhea that ignores antihistamines is often prostaglandin- or leukotriene-driven, and montelukast or cromolyn, which blocks the release of all mediators rather than any single one, are used for it. Wheeze without clear allergy trigger points squarely at the leukotriene pathway.
Knowing which mediator is dominant points to the drug class that targets it.
14. Stacking Medications to Cover Multiple Mediators
Because mast cells release many chemicals, single-agent therapy almost never works. The typical mast cell activation syndrome "cocktail" is built to cover each mediator class:
- H1 + H2 antihistamines — histamine on both receptor families
- Montelukast — leukotrienes
- Aspirin (when tolerated, cautiously) — PGD2 and other prostaglandins
- Cromolyn or ketotifen — release blocker; reduces all mediators at the source
- Quercetin, luteolin, vitamin C — natural stabilizers that reduce granule release and scavenge downstream oxidants
- Low dose naltrexone (LDN) — dampens glial and cytokine component
See Natural Mast Cell Stabilizers for the flavonoid-based layer that complements the prescription drugs.
15. Mediators Amplified by Hormones, Stress, Infection
Mast cells sit at the intersection of the immune, endocrine, and nervous systems, and they listen to all three. Three specific amplifiers show up in almost every patient's history:
- Estrogen — peaks during ovulation, PMS, pregnancy, and hormone replacement therapy (HRT) amplify release of all mediators. Many women trace their mast cell activation syndrome onset to puberty, pregnancy, or perimenopause.
- Cortisol and adrenaline — acute stress spikes trigger degranulation. A bad phone call can set off a flare as reliably as a food trigger.
- Infections and vaccines — viral infections (Epstein-Barr virus (EBV), influenza, and SARS-CoV-2 among them) and some vaccines can acutely flare mast cell activation syndrome by stimulating the innate immune system that mast cells are embedded in.
Flares that track a menstrual cycle, stressful week, or recent illness are not imagined — they are the predictable output of this amplifier network.
Key Research Papers
- Valent P, et al. Proposed diagnostic algorithm for patients with suspected MCAS. J Allergy Clin Immunol Pract. 2019;7(4):1125–1133. — doi:10.1016/j.jaip.2019.01.006
- Afrin LB, Ackerley MB, Bluestein LS, et al. Diagnosis of mast cell activation syndrome: a global "consensus-2". Diagnosis (Berl). 2021;8(2):137–152. — doi:10.1515/dx-2020-0005
- Weiler CR, Austen KF, Akin C, et al. AAAAI Mast Cell Disorders Committee work group report: mast cell activation syndrome (MCAS) diagnosis and management. J Allergy Clin Immunol. 2019;144(4):883–896. — doi:10.1016/j.jaci.2019.08.023
- Akin C. Mast cell activation syndromes. J Allergy Clin Immunol. 2017;140(2):349–355. — doi:10.1016/j.jaci.2017.06.007
- Vadas P, Gold M, Perelman B, et al. Platelet-activating factor, PAF acetylhydrolase, and severe anaphylaxis. N Engl J Med. 2008;358(1):28–35. — PubMed PMID: 18172172
- Hermans MAW, van der Vet SQA, van Hagen PM, van Wijk RG, van Daele PLA. Low frequency of acetyl salicylic acid hypersensitivity in mastocytosis: the results of a double-blind, placebo-controlled challenge study. Allergy. 2018;73(10):2055–2062. — PubMed PMID: 29569284
PubMed Topic Searches
Open searches on PubMed for ongoing literature on each mediator class:
- PubMed: Mast cell mediators and symptoms
- PubMed: Histamine intolerance and MCAS
- PubMed: Prostaglandin D2 and flushing
- PubMed: Tryptase and mast cell activation
- PubMed: Leukotriene and mast cell activation
- PubMed: Heparin and mast cell
- PubMed: MCAS, cytokines, and TNF
- PubMed: Platelet activating factor and anaphylaxis
Connections
- Neurology
- Mast Cell Activation Syndrome Overview
- H1/H2 Blocker Stacks
- Natural Mast Cell Stabilizers
- Testing Guide
- Cromolyn and Ketotifen Protocols
- Triggers and Flare Management
- Low-Histamine Diet
- Hereditary Alpha-Tryptasemia
- Alpha-Gal Syndrome
- Postural Orthostatic Tachycardia Syndrome
- Small Intestinal Bacterial Overgrowth
- Allergies
- Quercetin
- Brain Fog
- Fatigue
- Vitamin C
- Testing and Diagnosis
- Postural Orthostatic Tachycardia Syndrome Mast Cell Activation Syndrome and the EDS Triad
- Tryptase (Lab Test) — how the serum tryptase level is drawn and interpreted, including the baseline and flare thresholds.