⚠ Evidence warning: Clinical trials or other evidence do not support the claim that taking antihistamines and H2 blockers at 2–4 times the over-the-counter dose is evidence-based, standard care for mast cell activation syndrome. This page keeps it as a report of what people, websites or other media say.
H1 and H2 Blocker Stacks for Mast Cell Activation Syndrome (MCAS)
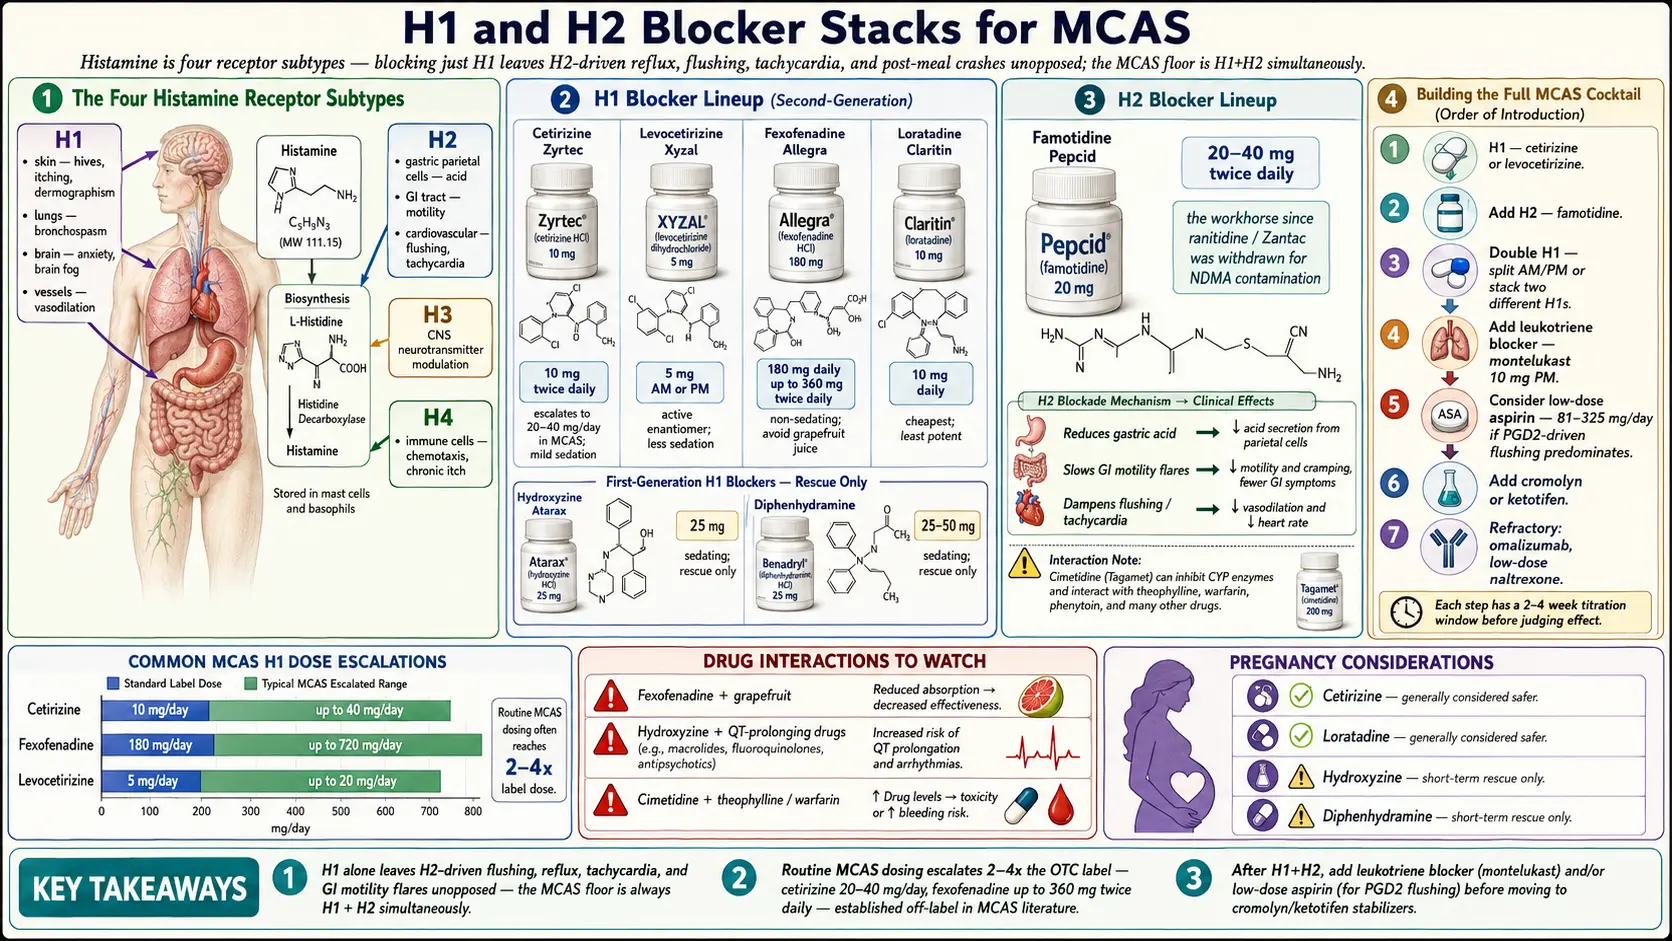
Table of Contents
- Why Mast Cell Activation Syndrome Needs More Than One Antihistamine
- H1 Blockers (Skin, Lungs, Brain, Vascular)
- H2 Blockers (Gastrointestinal, Flushing, Cardiovascular)
- Leukotriene Receptor Antagonists
- Aspirin for PGD2-Dominant Disease
- The “Mast Cell Activation Syndrome Cocktail” Order of Introduction
- Morning vs Night Dosing
- Doses Above the Label
- Drug Interactions to Watch
- Side Effects and How They Are Managed
- Pregnancy Considerations
- Pediatric Dosing
- Cost & Access
- When Stacks Aren’t Enough
- Key Research Papers
- Connections
- Featured Videos
1. Why Mast Cell Activation Syndrome Needs More Than One Antihistamine
Histamine is not one signal — it’s four. Four different receptor subtypes (H1, H2, H3, H4) sit on different tissues and produce different symptoms. H1 drives itching, hives, bronchospasm, vasodilation, and the brain-fog/anxiety component. H2 drives gastric acid production, gastrointestinal (GI) motility changes, and a major share of flushing and tachycardia. H3 is primarily central nervous system (CNS) (neurotransmitter modulation). H4 is concentrated on immune cells and mediates chemotaxis and chronic itch.
If you block only H1 with a single cetirizine a day, every H2-driven symptom — reflux, bloating, flushing, post-meal crashes — rolls on unopposed. That’s why mast cell activation syndrome (MCAS) practitioners describe H1 + H2 together as the starting point, and why patients who stall out on that combination go on to add a leukotriene blocker, a mast cell stabilizer, and often aspirin or natural stabilizers like quercetin on top.
For a full map of which mediators drive which symptoms, see Mediators & Symptom Map.
2. H1 Blockers (for Skin, Lungs, Brain, Vascular Symptoms)
Second-generation H1 antihistamines are the backbone. They cross the blood-brain barrier less than the first-generation drugs (diphenhydramine, hydroxyzine), so they don’t wreck your cognition. In mast cell activation syndrome, practitioners routinely dose them above the over-the-counter (OTC) labeling. This is off-label: the trial evidence for doses up to four times the label comes from chronic hives (urticaria), not from mast cell activation syndrome studies (see Doses Above the Label).
Cetirizine
The usual starting dose is 10 mg every morning. Many mast cell activation syndrome patients are described as needing 10 mg twice daily (off-label), and practitioners report escalating to 20–40 mg/day total. Cetirizine has the best balance of potency and tolerability of the second-gen H1s — it quiets skin and airway symptoms aggressively and has real activity on eosinophil recruitment. Minimal but non-zero sedation (~10% of patients).
Levocetirizine
5 mg AM or PM. This is the active enantiomer of cetirizine and is often better tolerated at equivalent potency — less sedation, less dry mouth. Now over-the-counter in the US. Practitioners often turn to it when cetirizine causes drowsiness but cetirizine-level effect is wanted.
Fexofenadine
180 mg daily, escalating to 360 mg twice daily in refractory mast cell activation syndrome. Truly non-sedating — fexofenadine barely crosses the blood-brain barrier at all. The trade-off is that it’s less potent than cetirizine for some patients, particularly for skin symptoms. Often chosen by people who drive, work, or cannot tolerate any cognitive dulling. Fruit juices reduce its absorption; the over-the-counter label directs taking it with water, not with fruit juices.
Loratadine
10 mg daily. The least potent of the common second-gen H1s, but the cheapest and one of the best-tolerated. Acceptable as a maintenance H1 for mild mast cell activation syndrome, or as a second H1 stacked with cetirizine to cover a dip in the middle of the day.
Hydroxyzine
10–50 mg at bedtime. First-generation and frankly sedating — but that’s exactly why it earns a place in mast cell activation syndrome protocols. Hydroxyzine is an outstanding nighttime H1 for patients with nocturnal itching, sleep-destroying flushing, or the anxiety component of mast cell activation syndrome (it has some 5-HT1A activity). Many mast cell activation syndrome patients take 25–50 mg at bedtime as their evening anchor. Its sedation is the reason it is kept to bedtime; a morning dose brings that drowsiness into the working and driving day.
Diphenhydramine
25–50 mg — used for rescue, not daily maintenance. The 2015 JAMA Internal Medicine study by Gray and colleagues followed 3,434 adults aged 65 and older, free of dementia at the start, for a mean of 7.3 years. Those with the heaviest use of strong anticholinergic drugs over the previous 10 years (more than 1,095 standard daily doses) had a higher rate of dementia than non-users (hazard ratio 1.54; 95% confidence interval 1.21–1.96), and first-generation antihistamines were among the most commonly used anticholinergic classes. Practitioners describe that finding as the reason many mast cell activation syndrome clinicians now reserve diphenhydramine for acute reactions, situations where epinephrine may also be needed, and episodic flares — a rescue drug rather than a daily one.
Doxepin
10–25 mg at bedtime. Technically a tricyclic antidepressant, but at low doses doxepin is one of the most potent H1 antihistamines ever characterized — reportedly more potent per milligram than diphenhydramine. Reserved for severe mast cell activation syndrome with refractory urticaria or insomnia. Sedating; dry mouth; not compatible with monoamine oxidase inhibitors (MAOIs) and caution-required with selective serotonin reuptake inhibitors (SSRIs).
Ketotifen
Dual H1 blocker + mast cell stabilizer; not a standard second-gen antihistamine and covered separately — see Cromolyn & Ketotifen Protocols.
3. H2 Blockers (for Gastrointestinal Symptoms, Flushing, Cardiovascular)
H2 blockers were developed for peptic ulcers, but in mast cell activation syndrome they pull double duty: they block the H2-mediated flushing, tachycardia, and gut-motility symptoms that H1 blockers cannot touch. Mast cell activation syndrome practitioners typically pair every H1 blocker with an H2 blocker unless there is a specific contraindication.
Famotidine
20–40 mg twice daily. This is the default H2 blocker in 2024–2026 practice. Ranitidine was pulled from the market in 2020 after the U.S. Food and Drug Administration (FDA) found N-nitrosodimethylamine (NDMA) contamination in manufactured lots. Famotidine is over-the-counter, cheap, has essentially no cytochrome P450 (CYP) drug interactions, and is well-tolerated. Practitioners report many mast cell activation syndrome patients doing best on 40 mg twice or even three times daily.
Nizatidine
150–300 mg twice daily. An alternative when famotidine is insufficient or unavailable. Equivalent efficacy in most head-to-head data. Useful as a rotation if famotidine seems to lose effect (uncommon).
Cimetidine
400 mg twice daily. The original H2 blocker. It works, but it is a strong CYP450 inhibitor (1A2, 2C9, 2D6, 3A4) and thus a drug-interaction minefield — warfarin, theophylline, phenytoin, many selective serotonin reuptake inhibitors, tricyclics, beta-blockers. Cimetidine also has weak anti-androgen effects. For these reasons practitioners generally use famotidine first.
Proton pump inhibitors (PPIs) do not substitute for H2 blockers in this role. Omeprazole, pantoprazole, and esomeprazole shut down gastric acid production entirely but do nothing to H2-receptor histamine signaling on cardiovascular, enteric, or dermal tissue. Chronic proton pump inhibitor (PPI) use also drives small intestinal bacterial overgrowth (see small intestinal bacterial overgrowth (SIBO)), which in turn aggravates mast cell activation syndrome symptoms in a painful loop. Mast cell activation syndrome practitioners describe reflux in this condition as frequently histamine-driven and use famotidine first. The 2016 Molderings review of treatments for mast cell activation disease does list proton pump inhibitors for gastric complaints (“de-escalating dose-finding”) and for proven gastroesophageal reflux.
4. Leukotriene Receptor Antagonists (for Respiratory + Some Gastrointestinal)
Mast cells release not just histamine but also leukotrienes (LTC4, LTD4, LTE4) — lipid mediators 1000× more potent than histamine at causing bronchoconstriction and airway edema. If your mast cell activation syndrome has a strong respiratory, sinus, or asthma-overlap component, an H1+H2 stack will not reach those symptoms.
Montelukast
10 mg daily, typically at bedtime. Blocks the CysLT1 receptor for LTD4 and LTE4. Highly effective for chronic rhinosinusitis, aspirin-exacerbated respiratory disease, and mast-cell-driven asthma overlap. In 2020 the U.S. Food and Drug Administration applied a boxed warning for neuropsychiatric adverse effects (depression, suicidality, sleep disturbance, vivid dreams) — these are uncommon but real, and they tend to appear within the first weeks. The label tells prescribers to discuss these risks with patients and caregivers and to stop montelukast immediately if neuropsychiatric symptoms occur.
Zafirlukast
20 mg twice daily. A less-used alternative. It is taken on an empty stomach (the label reports that food reduces absorption by about 40%). Rare liver injury (hepatotoxicity) is reported; practitioners check liver function tests (LFTs) during long-term use. Used as a backup when montelukast is not tolerated.
5. Aspirin (for PGD2-Dominant Disease)
Mast cells also release prostaglandin D2 (PGD2), which is the dominant mediator in flushing-dominant mast cell activation syndrome and in systemic mastocytosis. If your flushing, tachycardia, and vascular symptoms ignore a fully-optimized H1+H2 stack, PGD2 is the likely culprit.
Low-dose aspirin 81–325 mg daily inhibits cyclooxygenase-1 (COX-1) and blocks PGD2 synthesis. Many flushing-dominant mast cell activation syndrome patients report a dramatic response, and practitioners describe a formal aspirin trial in this subgroup before escalating further, starting at 81 mg/day with food and raising the dose over weeks as tolerated. The 2016 Molderings review of treatments for mast cell activation disease lists aspirin (acetylsalicylic acid) at 50–350 mg/day, used “with extreme caution”, because aspirin can itself trigger mast cell degranulation (the release of the mast cell’s stored contents).
The catch: roughly 15% of mast cell activation syndrome patients cannot take aspirin. Some have aspirin-exacerbated respiratory disease (Samter’s triad — asthma, nasal polyps, aspirin sensitivity); some have true aspirin-triggered mast cell reactions. Practitioners describe observing the first dose, and in high-suspicion patients a formal desensitization protocol in an allergist’s office.
6. The “Mast Cell Activation Syndrome Cocktail” Order of Introduction
Mast cell activation syndrome practitioners describe adding one layer at a time, roughly every 1–2 weeks, rather than starting everything at once: when several drugs start together, there is no way to tell which drug did what, or which one to stop after a flare. The sequence they describe:
- Step 1 (Week 1–2): Cetirizine 10 mg in the morning + famotidine 20 mg twice daily — the usual mast cell activation syndrome starting point.
- Step 2 (Week 3–4): If that is not enough: cetirizine goes up to 20 mg in the morning (or 10 mg twice daily) and hydroxyzine 10–25 mg at bedtime is added for sleep and nocturnal itching.
- Step 3 (Week 5–6): Montelukast 10 mg at bedtime is added, especially if respiratory, sinus, or asthma-overlap symptoms are prominent; mood changes are watched for because of the boxed warning.
- Step 4 (Week 7–8): An aspirin trial (81 mg/day, raised gradually) if flushing or vascular symptoms dominate and persist despite the stack.
- Step 5: If the pharmacologic stack is still inadequate, cromolyn sodium or ketotifen — true mast cell stabilizers — is added. See Cromolyn & Ketotifen Protocols.
- Step 6: Natural stabilizers are layered in: quercetin, luteolin, vitamin C, and others — see Natural Mast Cell Stabilizers.
Practitioners describe giving each step 10 to 14 days before judging it, with a simple symptom log (1–10 scale, morning and evening) to separate signal from noise.
7. Morning vs Night Dosing
A well-constructed mast cell activation syndrome stack is not “once a day.” It is a 24-hour coverage plan with a morning side and an evening side:
- Morning: non-sedating H1 (cetirizine 10–20 mg, or fexofenadine 180 mg) + first H2 dose (famotidine 20–40 mg) + aspirin (if on it).
- Noon / mid-afternoon: second H1 dose for people on twice-daily cetirizine; a mid-day famotidine for people on three-times-daily dosing; this is also when many patients describe a symptom trough, and some take quercetin then.
- Evening: second H1 dose (hydroxyzine 25 mg or doxepin 10 mg) for nocturnal itching and sleep + third famotidine if needed + montelukast (the published trials used evening dosing; most benefit appears to occur overnight).
Histamine peaks cyclically; many patients notice a 2–4 AM flare window. An evening hydroxyzine or ketotifen dose specifically targets this.
8. Doses Above the Label
Most over-the-counter antihistamines are labeled “once daily” because the extended-release formulation maintains therapeutic serum levels for 24 hours in most people. Mast cell activation syndrome patients are not most people. Mast cell degranulation is not a 24-hour smooth release; it’s bursty, provoked, and overwhelms steady-state receptor blockade.
Mast cell activation syndrome practitioners describe dosing second-generation H1 and H2 blockers at 2–4× the over-the-counter recommendation. The mast cell activation syndrome papers cited below (Valent, Afrin, Molderings) are diagnostic and treatment reviews and give no such dose multiple; the trial evidence for higher antihistamine doses comes from chronic hives (urticaria), where European guidelines recommend increasing antihistamine doses up to 4-fold. The doses practitioners describe:
- Cetirizine: over-the-counter 10 mg/day → mast cell activation syndrome 20–40 mg/day.
- Fexofenadine: over-the-counter 180 mg/day → mast cell activation syndrome up to 360 mg twice daily (BID).
- Famotidine: over-the-counter 20 mg BID → mast cell activation syndrome 40 mg BID or three times daily.
These doses are off-label. In mast cell activation syndrome they are practitioner practice carried over from the chronic-hives evidence; the Afrin “consensus-2” paper cited below compares diagnostic criteria and does not address dosing.
The best trial evidence for higher-than-label antihistamine doses comes from chronic hives. In a 2010 double-blind trial, 80 people with difficult-to-treat chronic urticaria took levocetirizine or desloratadine at the usual 5 mg a day, raised weekly to 10 mg and then 20 mg when symptoms persisted. Thirteen became symptom-free at 5 mg, compared with 28 at the higher doses. Higher doses improved quality of life without increasing drowsiness, and no serious or severe side effects led anyone to stop. About 15% of patients responded well to the usual dose, about 10% did not respond, and about 75% responded to higher-than-conventional doses (Staevska 2010). This trial was in chronic hives, not mast cell activation syndrome.
9. Drug Interactions to Watch
- Cimetidine — CYP450 inhibitor across 1A2, 2C9, 2D6, 3A4. Interacts with warfarin, phenytoin, theophylline, many antidepressants, beta-blockers. Famotidine has essentially no CYP interactions.
- Hydroxyzine — prolongs the QT interval; the label reports QT prolongation and torsade de pointes, mostly in people with other risk factors, and lists a prolonged QT interval as a contraindication. The risk adds up with other QT-prolonging drugs (citalopram >20 mg, ondansetron, macrolides, fluoroquinolones, methadone). Practitioners describe an electrocardiogram (EKG) before chronic dosing in older patients.
- Doxepin — contraindicated with monoamine oxidase inhibitors; serotonin-syndrome risk with selective serotonin reuptake inhibitors and serotonin-norepinephrine reuptake inhibitors (low at 10–25 mg but real). Anticholinergic load adds to any other anticholinergic in the regimen.
- Diphenhydramine — additive anticholinergic cognitive effects with tricyclics, oxybutynin, benztropine, and hydroxyzine. Cumulative anticholinergic burden is a legitimate long-term concern.
- Montelukast — induced by phenytoin, rifampin, and phenobarbital (levels drop); neuropsychiatric interactions with anything that affects mood.
10. Side Effects and How They Are Managed
- Drowsiness: the usual change is a morning switch to fexofenadine 180 mg, with sedating H1s (hydroxyzine, doxepin, diphenhydramine) kept to bedtime.
- Dry mouth: common with hydroxyzine, doxepin, and diphenhydramine. First-generation H1s are worst. Hydration and sugar-free gum are commonly used; when it is disabling, a lower dose or a shift toward fexofenadine / levocetirizine is the usual change.
- Urinary retention: older men with benign prostatic hyperplasia plus first-generation H1s are a predictable problem. Second-generation H1s are generally preferred in this group.
- Weight gain: cetirizine produces mild appetite stimulation in some patients. Doxepin and mirtazapine produce substantially more. Some practitioners track weight monthly on a new regimen.
- Neuropsychiatric effects on montelukast: depression, suicidal ideation, vivid dreams, insomnia, irritability. Boxed warning; the label says to stop montelukast immediately if neuropsychiatric symptoms occur.
- Itching after stopping cetirizine or levocetirizine: a recognized syndrome of intense itching (pruritus) after stopping long-term use. An FDA review of 146 cases reported through April 2017 found a median of 24 months of cetirizine use before stopping and itch starting a median of 2 days after the last dose; of 55 people who restarted and stopped again, 54 had the itch return (Chung 2019).
This itch after stopping is now on the FDA’s radar. According to an FDA review published in 2026 (Konkel and colleagues), the FDA issued a drug safety communication in 2025, and safety labeling changes are underway, including the new term “new onset pruritus” for prescription and nonprescription cetirizine and levocetirizine products. FDA staff found 209 more reports from April 2017 to July 2023 in people without a skin condition: median use was 33 months, and the itch began a median of 2 days after stopping. Of 93 people who restarted the drug and later tried to stop again, 99% had the itch return. In these reports tapering was modestly effective and took up to 6 months: fewer than half of the 24 people who tapered succeeded, and the FDA authors write that no clearly defined mitigation strategy exists.
11. Pregnancy Considerations
Mast cell activation syndrome frequently worsens or improves dramatically during pregnancy, and the usual stack needs revisiting. General guidance (pre-2015 U.S. Food and Drug Administration category system, still widely cited):
- Cetirizine — Category B, generally preferred.
- Loratadine — Category B.
- Diphenhydramine — Category B, acceptable for rescue.
- Famotidine — Category B.
- Montelukast — Category B.
- Hydroxyzine — contraindicated in early pregnancy; caution later.
- Doxepin — generally not used in pregnancy.
- Aspirin — low-dose is used in some obstetric contexts, under obstetric (OB) care.
12. Pediatric Dosing
- Cetirizine: 2.5 mg age 2–5; 5 mg age 6+; 10 mg adolescents.
- Fexofenadine: 30 mg BID (children’s formulation); 180 mg daily from ~12 yrs.
- Hydroxyzine: 0.5 mg/kg per dose; excellent pediatric data, long track record.
- Famotidine: 0.5 mg/kg BID; well tolerated.
- Montelukast: 4 mg age 2–5, 5 mg age 6–14, 10 mg 15+. The boxed warning on mood and behavior changes applies to children too.
13. Cost & Access
This is one of the rare chronic conditions where the first-line medication stack is genuinely cheap. Almost nothing in the core mast cell activation syndrome regimen is patent-protected.
- Over-the-counter generics: cetirizine, loratadine, fexofenadine, levocetirizine, famotidine, diphenhydramine, aspirin — typically $5–$15/month each.
- Prescription generics: hydroxyzine, doxepin, montelukast, nizatidine — $5–$15/month each through discount pharmacy programmes.
- Levocetirizine is now over-the-counter. Hydroxyzine remains prescription-only.
- Total cost of a complete H1 + H2 + montelukast + aspirin stack: typically $20–$60/month even cash-pay.
The expensive pieces of mast cell activation syndrome management are the next layer — oral cromolyn sodium, ketotifen (compounded in the US), and specialty biologics like omalizumab. The antihistamine stack is not the budget problem.
14. When Stacks Aren’t Enough
If you’ve run an optimized H1 + H2 + leukotriene + aspirin stack at maximum tolerated doses for 6–8 weeks and symptoms persist, you’ve hit the ceiling of what receptor blockade alone can do. Released histamine, PGD2, and leukotrienes saturate their receptors faster than the blockers can compete.
The next layer targets mast cells themselves:
- Cromolyn sodium: inhaled or oral; prevents mast cell degranulation in the first place.
- Ketotifen: dual H1 antagonist + mast cell stabilizer; compounded in the US; widely used in Europe.
Dosing, titration, and the common gastrointestinal-solution tricks live in Cromolyn & Ketotifen Protocols. Beyond that: omalizumab, low-dose naltrexone (LDN), and in refractory cases tyrosine kinase inhibitors (imatinib, midostaurin) for biopsy-confirmed mastocytosis — these are specialist-managed.
Key Research Papers
- Valent P, et al. Proposed diagnostic algorithm for patients with suspected mast cell activation syndrome. J Allergy Clin Immunol Pract. 2019;7(4):1125–1133.e1. — doi:10.1016/j.jaip.2019.01.006
- Afrin LB, et al. Diagnosis of mast cell activation syndrome: a global “consensus-2.” Diagnosis (Berl). 2021;8(2):137–152 (online 2020). — doi:10.1515/dx-2020-0005
- Molderings GJ, Haenisch B, Brettner S, et al. Pharmacological treatment options for mast cell activation disease. Naunyn-Schmiedeberg’s Archives of Pharmacology. 2016;389(7):671–694. — doi:10.1007/s00210-016-1247-1
- Vitte J, Amadei L, Gouitaa M, et al. Paired acute-baseline serum tryptase levels in perioperative anaphylaxis: an observational study. Allergy. 2019;74(6):1157–1165. — doi:10.1111/all.13752
- Staevska M, Popov TA, Kralimarkova T, Lazarova C, Kraeva S, Popova D, Church DS, Dimitrov V, Church MK. The effectiveness of levocetirizine and desloratadine in up to 4 times conventional doses in difficult-to-treat urticaria. J Allergy Clin Immunol. 2010;125(3):676–682. — PubMed PMID: 20226302
- Gray SL, Anderson ML, Dublin S, Hanlon JT, Hubbard R, Walker R, Yu O, Crane PK, Larson EB. Cumulative use of strong anticholinergics and incident dementia: a prospective cohort study. JAMA Intern Med. 2015;175(3):401–407. — PubMed PMID: 25621434
- Chung AH, La Grenade L, Harinstein LM. Pruritus after discontinuation of cetirizine. Ther Adv Drug Saf. 2019;10:2042098619859996. — PubMed PMID: 31308927
- Konkel K, Lee JY, Jones SC, Adereti M, Muhammad S, Suresh R, Jhamnani R, Green J, Gill R, McCulley L. New onset pruritus following discontinuation of cetirizine or levocetirizine. J Allergy Clin Immunol Pract. 2026;14(3):725–728. — PubMed PMID: 41380841
PubMed Topic Searches
Curated PubMed topic searches — each link opens a live query so you always see the most recent literature.
- PubMed: H1 + H2 antihistamines in MCAS
- PubMed: Cetirizine and mast cell activity
- PubMed: Famotidine in MCAS
- PubMed: Hydroxyzine for chronic urticaria
- PubMed: Montelukast and mast cell disease
- PubMed: Aspirin for flushing in mastocytosis
- PubMed: Doxepin for chronic urticaria
- PubMed: High-dose fexofenadine in urticaria
Connections
- Neurology
- Mast Cell Activation Syndrome Overview
- Natural Mast Cell Stabilizers
- Mediators and Symptom Map
- Cromolyn and Ketotifen Protocols
- Triggers and Flare Management
- Mast Cell Activation Syndrome Testing Guide
- Hereditary Alpha-Tryptasemia
- Low-Histamine Diet
- Hormone Sensitivity and Menstrual Flares
- Postural Orthostatic Tachycardia Syndrome
- Allergies
- Small Intestinal Bacterial Overgrowth
- Asthma
- Quercetin
- Vitamin C
- Bloating
- Inflammatory Markers