⚠ Evidence warning: Clinical trials or other evidence do not support the claim that hereditary alpha-tryptasemia, postural orthostatic tachycardia syndrome and Ehlers-Danlos syndrome form one syndrome, or that treating mast cells improves dizziness and joint instability. This page keeps it as a report of what people, websites or other media say.
Hereditary Alpha-Tryptasemia (HαT)
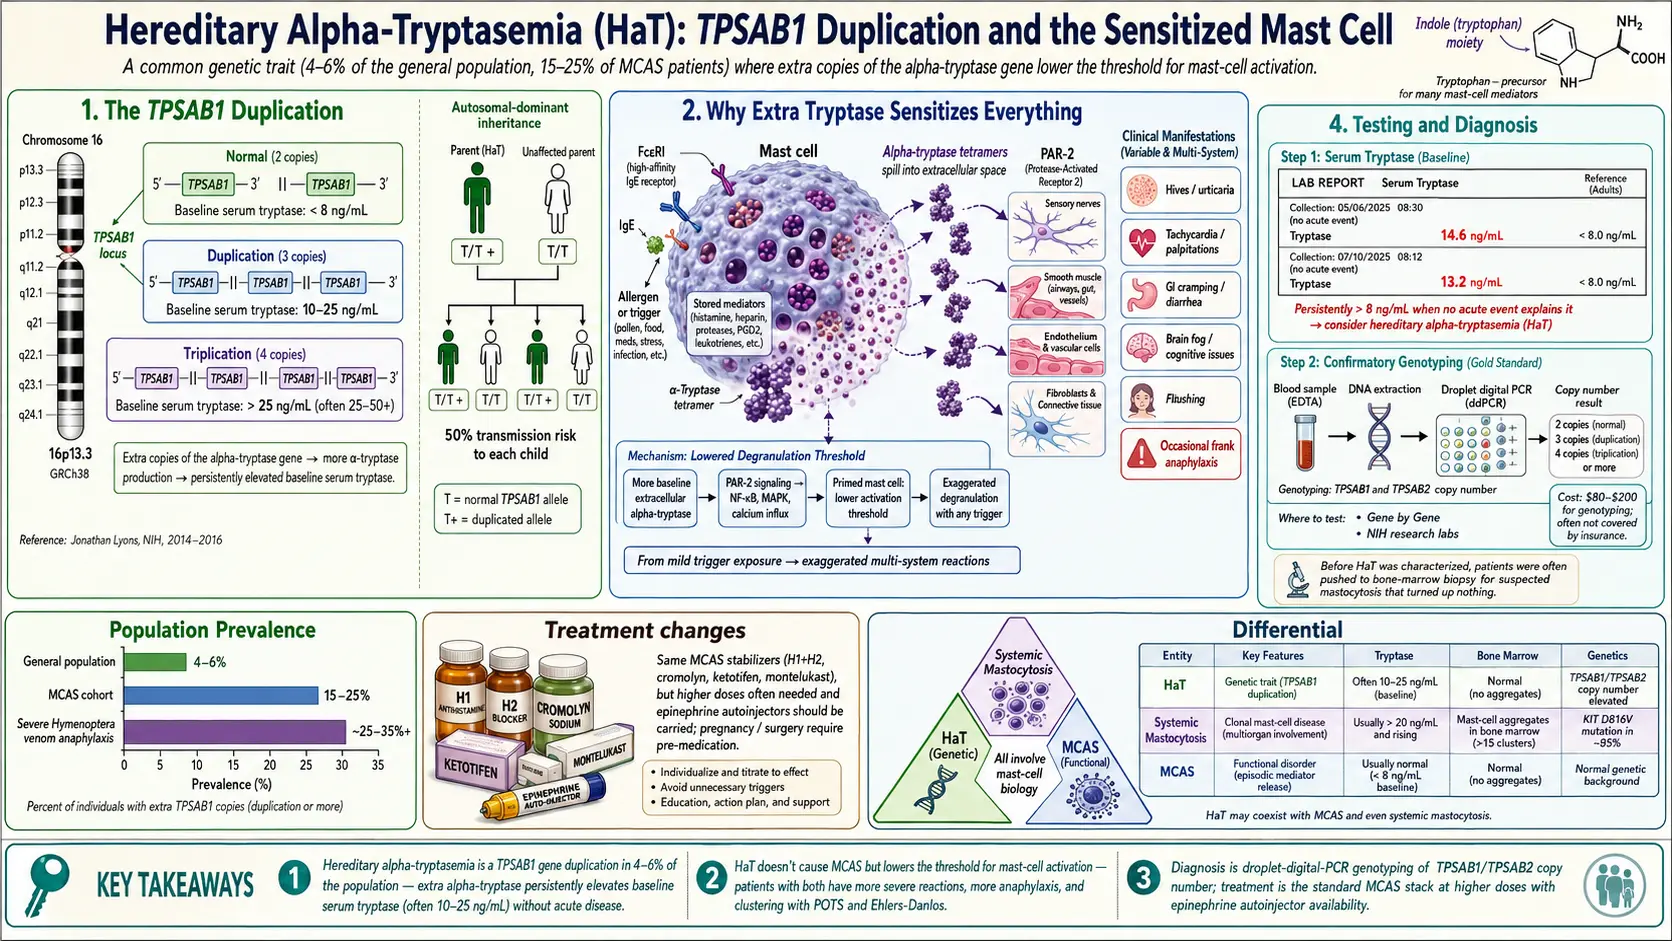
Table of Contents
- What Hereditary Alpha-Tryptasemia Is
- How Common It Is
- Why It Matters for Mast Cell Activation Syndrome
- Symptoms Associated with HαT
- Overlap with the Postural Orthostatic Tachycardia Syndrome/Mast Cell Activation Syndrome/Ehlers-Danlos Syndrome Triad
- Testing for HαT
- Inheritance
- What HαT Diagnosis Changes About Treatment
- HαT vs. Systemic Mastocytosis vs. Mast Cell Activation Syndrome
- Practical Implications for Life Planning
- Emerging Research
- Resources & Support
- Key Research Papers
- Connections
- Featured Videos
1. What Hereditary Alpha-Tryptasemia Is
Hereditary alpha-tryptasemia (HαT) is a genetic trait, not a disease in the classical sense. It is caused by a duplication or triplication of the TPSAB1 gene on chromosome 16, the gene that encodes alpha-tryptase. People with HαT carry extra copies of TPSAB1 and therefore make more alpha-tryptase at baseline — even when their mast cells are sitting quietly and not actively degranulating.
Tryptase is the enzyme mast cells release when they activate, and it is measured in the blood as a proxy for mast cell burden. Most of the population has two copies of TPSAB1 (one from each parent) and a baseline serum tryptase below 8 ng/mL. HαT patients, because of gene dosage, run baseline tryptase values that are persistently elevated — often 10 to 25 ng/mL — without any acute allergic event to explain it.
The trait was first characterized by Jonathan Lyons and colleagues at the U.S. National Institutes of Health (NIH) between 2014 and 2016. Before that work, patients with unexplained elevated tryptase were often labeled as having “idiopathic” tryptasemia or pushed toward bone marrow biopsies for suspected mastocytosis that turned up nothing. The discovery of the TPSAB1 duplication gave a name and a mechanism to a population that had been invisible to medicine.
The 2016 study in Nature Genetics that named the cause traced the raised tryptase to extra copies of the alpha-tryptase gene (duplications and triplications of TPSAB1) in 35 families, passed down from one parent (dominant inheritance). The families reported skin flushing and itching, dizziness and racing heart on standing (dysautonomia), irritable-bowel symptoms, chronic pain and loose joints (joint hypermobility). People whose gene carried three copies of alpha-tryptase had higher tryptase and more symptoms than those whose gene carried two copies, a sign that the dose of the gene matters. (Lyons 2016, PMID 27749843.)
2. How Common It Is
HαT is remarkably common. A raised baseline tryptase is found in 4–6% of the general population (Lyons 2016); in that study, raised levels were linked only with the extra gene copies. In a 2021 study across Italy, Slovenia and the United States, about 5 to 6 in 100 healthy people carried the extra copies (7 of 125 healthy volunteers; 21 of 398 controls without allergic disease), compared with 17 in 100 people with unexplained (idiopathic) anaphylaxis (8 of 47) and 12 in 100 people with systemic mastocytosis (10 of 82). The trait was linked with twice the risk of the most severe grade of insect-sting anaphylaxis (relative risk 2.0), and among people with mastocytosis, carrying it raised the risk of severe whole-body allergic reactions about nine-fold (relative risk 9.5). (Lyons 2021, PMID 32717252.)
That makes HαT one of the most common genetic conditions that almost nobody — including most primary care physicians and many allergists — has heard of. A raised tryptase in a family that has always been “the allergic one” or “the flushing one” or “the bendy one” matches the pattern described in the first family studies of HαT.
3. Why It Matters for Mast Cell Activation Syndrome
HαT does not directly cause mast cell activation syndrome. You can have HαT and be completely asymptomatic. But when HαT is present, it lowers the threshold at which mast cells activate and amplifies the downstream symptoms when they do. The measured link is with severe allergic reactions: in the 2021 study, HαT carried twice the risk of the most severe grade of insect-sting anaphylaxis (relative risk 2.0), and in people with systemic mastocytosis it raised the risk of whole-body anaphylaxis about 9.5-fold (Lyons 2021). Clinicians also report that patients with HαT + mast cell activation syndrome have more flushing, more gut (gastrointestinal, GI) involvement and more medication reactions than patients with mast cell activation syndrome alone; that comparison was not measured in the 2021 study.
The working model is that extra baseline alpha-tryptase — because of its activity on PAR-2 (protease-activated receptor 2) on sensory nerves, smooth muscle, and connective tissue — sensitizes the whole downstream signaling environment. Mast cells don’t need as large a trigger to produce a clinically significant reaction. In laboratory tests on cells that line blood vessels (from human umbilical cords), a natural mix of mature tryptases made the vessel lining leaky through the PAR-2 receptor, while alpha-tryptase alone or beta-tryptase alone did not (Lyons 2021). This is a cell-dish result; it suggests why carriers may react more severely, but it was not measured in people.
For a patient struggling to control mast cell activation syndrome, a positive HαT result is actually good news in one sense: it explains why “standard” doses of antihistamines feel underpowered and why your reactions are more severe than textbook mast cell activation syndrome cases predict.
4. Symptoms Associated with HαT
Not every HαT carrier is symptomatic — probably half are silent. Among those who do have symptoms, the common features include:
- Easy flushing — face, neck, and chest, often with alcohol, heat, or stress
- Headache and migraine
- Itching, hives, and dermographism (the ability to “draw” raised red lines on the skin with light pressure)
- Gastrointestinal symptoms — irritable bowel syndrome-like bloating, reflux, abdominal pain, altered bowel habits
- Bone and joint pain — often unexplained, sometimes migratory
- Autonomic symptoms — lightheadedness on standing, palpitations, temperature dysregulation (overlap with postural orthostatic tachycardia syndrome, POTS)
- Joint hypermobility — clear overlap with Ehlers-Danlos and hypermobility spectrum disorder
- Anaphylaxis — especially venom anaphylaxis. HαT is substantially overrepresented in patients with severe bee, wasp, and hornet sting reactions
- Anxiety and depression — thought to be mediated in part through mast cell activation in the brain and meninges
No single symptom is specific to HαT; the pattern is what matters. A patient with flushing + bone pain + anxiety + hypermobility + a persistently elevated tryptase is a textbook picture.
5. Overlap with the Postural Orthostatic Tachycardia Syndrome/Mast Cell Activation Syndrome/Ehlers-Danlos Syndrome Triad
Practitioners describe HαT as clustering strongly with the postural orthostatic tachycardia syndrome/mast cell activation syndrome/hypermobile Ehlers-Danlos syndrome (EDS) triad, and some specialists treat the three as a single neuroimmune-connective-tissue syndrome rather than three separate diagnoses. This is a proposed link that the research has not confirmed: a 2025 systematic review searched four medical databases for studies of mast cell disorders or HαT in people with postural orthostatic tachycardia syndrome or Ehlers-Danlos syndrome, screened 200 records and found no study that met strict diagnostic criteria. It concluded that the evidence does not yet confirm a relationship between these conditions and that better studies with strict, validated criteria are needed (Farley 2025, PMID 40185471).
The proposed mechanism: elevated alpha-tryptase cleaves PAR-2 on autonomic nerve endings and on the fibroblasts that lay down collagen. Chronic PAR-2 activation contributes to autonomic dysregulation (the postural orthostatic tachycardia syndrome phenotype) and to connective tissue fragility (the EDS/HSD phenotype). Practitioners report that treating the mast cell side often improves both dizziness and joint instability. For a deeper dive, see the triad of postural orthostatic tachycardia syndrome, mast cell activation syndrome and Ehlers-Danlos syndrome (EDS).
6. Testing for HαT
Step 1: Baseline Serum Tryptase
The usual first step is a simple, cheap blood test: baseline serum tryptase, drawn at least 24 hours after any suspected flare. The standard lab reference range tops out at 11.4 ng/mL, but the threshold for clinical suspicion is lower:
- Tryptase > 8 ng/mL — the level at which some specialists consider HαT testing, especially with matching symptoms
- Tryptase > 11.4 ng/mL — above the standard reference range; specialists commonly order HαT testing
- Tryptase > 20 ng/mL — specialists test for HαT and look for systemic mastocytosis
Step 2: TPSAB1 Copy Number Variant Testing
The definitive test is TPSAB1 copy number variant (CNV) testing, done by droplet digital polymerase chain reaction (PCR). This is not a standard commercial lab offering — blood has to be sent to a specialty laboratory. Options include:
- A commercial genetic-testing laboratory — direct-to-consumer, roughly $350–500, no physician order required
- Other specialty genetic-testing laboratories — generally require a physician order
- Academic centers — the U.S. National Institutes of Health and Brigham & Women’s research groups offer testing for enrolled study participants
Interpreting Results
- 2 copies — normal, one from each parent, no HαT
- 3 copies — duplication on one allele, heterozygous HαT (most common positive result)
- 4 copies — homozygous duplication or heterozygous triplication, typically more severe phenotype
- 5 or more copies — rare, tends to produce the most severe clinical picture
Total cost, depending on route, runs $350–700 out of pocket. Insurance coverage is improving as awareness of the trait spreads, but many patients still pay cash.
7. Inheritance
HαT is inherited in an autosomal dominant pattern. A single copy of the duplicated allele is sufficient to produce the biochemical phenotype of elevated baseline tryptase. Children of a parent with HαT have a 50% chance of inheriting the duplication.
Because penetrance for symptoms is variable — some carriers are asymptomatic, others are severely affected — a positive result in one family member commonly leads to cascade screening of first-degree relatives, particularly if there is any family history of anaphylaxis, unexplained flushing, hypermobility, or mast cell activation syndrome-like symptoms. Silent carriers often have subtle findings they had written off as personal quirks for decades.
8. What HαT Diagnosis Changes About Treatment
Confirming HαT rarely changes the core medication stack for mast cell activation syndrome, but it changes several important things around the edges:
- Mast cell activation syndrome treatment stays the same. The H1 + H2 + stabilizer backbone remains the foundation — see H1 and H2 Blocker Stacks and Cromolyn and Ketotifen Protocols.
- Venom immunotherapy (desensitization) is used for people who have had a documented whole-body (systemic) insect sting reaction. HαT is linked with twice the risk of the most severe grade of sting anaphylaxis (Lyons 2021), and specialists describe the long-term risk of recurrence in carriers as high enough that desensitization is usually considered worth it.
- Epinephrine auto-injectors are prescribed generously. Specialists regard HαT patients as carrying a higher lifetime anaphylaxis risk than other mast cell activation syndrome patients, and carrying two epinephrine auto-injectors at all times is common practice.
- Pre-medication before procedures becomes more important. Anesthesia, intravenous (IV) contrast, and first-dose antibiotics are higher-risk events; a standard pre-med (H1 + H2 + steroid ± hydroxyzine) is commonly written into the chart.
- Family cascade screening. First-degree relatives are commonly tested and the family counselled together.
- Redefine the patient’s “normal” tryptase. An HαT patient’s baseline may be 15–25 ng/mL. The diagnostic criterion for an acute mast cell event is still the 20%-plus-2-ng/mL rise above baseline — but the baseline has to be known in advance for that rule to be useful.
9. HαT vs. Systemic Mastocytosis vs. Mast Cell Activation Syndrome
Three conditions present with elevated tryptase, and distinguishing them is essential.
- Systemic mastocytosis (SM). Increased number of mast cells, often clonal. Confirmed by bone marrow biopsy, which shows characteristic aggregates. The KIT D816V somatic mutation is usually present. Tryptase is typically > 20 ng/mL and rises over time.
- Mast cell activation syndrome (non-clonal). Normal mast cell numbers, but dysregulated activation. No KIT mutation. Tryptase may be normal, elevated, or fluctuate around a normal baseline.
- HαT. A genetic trait. Normal mast cell numbers. Baseline tryptase is elevated because of TPSAB1 gene dosage, not because of mast cell pathology. Can coexist with either SM or mast cell activation syndrome.
The most common combination in clinical practice is HαT + mast cell activation syndrome, and the two together produce the severe, hard-to-control phenotype many patients experience. HαT is also significantly more common in patients with systemic mastocytosis than in the general population — suggesting the extra tryptase copies may contribute to the clinical expression of both conditions.
10. Practical Implications for Life Planning
Pregnancy
Pregnancy-associated hormonal shifts can trigger more severe mast cell flares in HαT mothers. Mast cell specialists’ protocols describe planning pre-medication in advance, a labor-and-delivery team aware of the diagnosis, and anesthesia choices settled before labor begins (fentanyl and propofol are usually well tolerated; morphine and succinylcholine are usually left out).
Children with HαT
Cascade testing often identifies children early. Pediatric counseling usually covers anaphylaxis risk, school epinephrine plans, and awareness of venom sensitivity. Many symptomatic children improve markedly on a simple H1 + H2 regimen.
Surgery
Specialist protocols use a written pre-op plan: H1 + H2 + steroid ± hydroxyzine the night before and morning of surgery. They leave out succinylcholine, morphine, and nonsteroidal anti-inflammatory drugs (NSAIDs), prefer fentanyl and propofol, and keep epinephrine drawn up and immediately accessible.
Vaccination
Vaccines are generally safe. Specialist protocols describe an H1 + H2 dose two hours before, spacing multi-component vaccines into separate visits when possible, and 30 minutes of observation after the injection.
Travel
Specialists’ travel lists include at least two epinephrine auto-injectors, a written allergy action plan, a medication list with doses, and copies of key lab results. For international travel, a letter from a physician explaining the diagnosis is reported to clear most customs and medical-supply issues.
11. Emerging Research
- HαT and mastocytosis overlap. HαT is substantially more common in systemic mastocytosis cohorts than in the general population, suggesting the duplication may contribute to disease expression.
- Basophil activation test (BAT). Emerging as an adjunct diagnostic for mediator release, particularly for drug and food reactions that are hard to provoke safely in a clinical setting.
- Anti-tryptase biologics. Experimental monoclonal antibodies that bind and neutralize tryptase directly have reached early trials. The one with published human results, MTPS9579A, was well tolerated in 106 healthy volunteers and lowered active tryptase in the nose (Rymut 2022). In a 48-week trial in 134 people with uncontrolled asthma it did not reduce asthma attacks; the dose tested did not block tryptase deep in the airways (Rhee 2024). No trial of these antibodies in HαT has been published.
- Mepolizumab (anti-IL-5). A single 2025 case report describes a patient with HαT and presumed eosinophilic granulomatosis with polyangiitis (a blood-vessel inflammation with high eosinophil counts) who was treated with mepolizumab for the vasculitis; the authors suggest it may also have helped the HαT symptoms (Iqbal 2025). It has not been tested in a trial for HαT.
- A decade of research. A 2025 review by the trait’s discoverer and colleagues describes HαT as a common inherited trait that changes how often and how severely mast cell reactions happen, and summarizes the data on venom allergy, drug allergy, food allergy, clonal mast cell disease and unexplained (idiopathic) anaphylaxis (Korošec 2025, PMID 41429728).
12. Resources & Support
- The Mast Cell Disease Society (TMS) — patient advocacy organization, physician directory, patient education materials
- Dysautonomia International — overlap resources for the postural orthostatic tachycardia syndrome/HαT/mast cell activation syndrome population
- U.S. National Institutes of Health HαT research — the trait was described in 2016 by a team at the National Institute of Allergy and Infectious Diseases, whose natural-history study of severe allergic reactions is listed as completed on ClinicalTrials.gov (NCT01164241). The trait’s discoverer, Dr. Jonathan Lyons, lists the University of California San Diego and the Veterans Affairs San Diego Healthcare System as his affiliation in 2025.
- MastAttack.org — patient education website about mast cell disease
Key Research Papers
- Lyons JJ, et al. Elevated basal serum tryptase identifies a multisystem disorder associated with increased TPSAB1 copy number. Nat Genet. 2016;48(12):1564–1569. — doi:10.1038/ng.3696
- Lyons JJ. Hereditary alpha tryptasemia: genotyping and associated clinical features. Immunol Allergy Clin North Am. 2018;38(3):483–495. — doi:10.1016/j.iac.2018.04.003
- Akin C. How to evaluate the patient with a suspected mast cell disorder and how/when to manage symptoms. Hematology Am Soc Hematol Educ Program. 2022;2022(1):55–63. — doi:10.1182/hematology.2022000366
- Afrin LB, et al. Diagnosis of mast cell activation syndrome: a global “consensus-2.” Diagnosis (Berl). 2021;8(2):137–152. — doi:10.1515/dx-2020-0005
- Lyons JJ, Chovanec J, O'Connell MP, et al. Heritable risk for severe anaphylaxis associated with increased α-tryptase-encoding germline copy number at TPSAB1. J Allergy Clin Immunol. 2021;147(2):622–632. — PubMed PMID: 32717252
- Farley M, Estrada-Mendizabal RJ, Gansert EA, Voelker D, Marks LA, Gonzalez-Estrada A. Prevalence of mast cell activation disorders and hereditary alpha tryptasemia among patients with postural orthostatic tachycardia syndrome and Ehlers-Danlos syndrome: a systematic review. Ann Allergy Asthma Immunol. 2025;135(1):97–102. — PubMed PMID: 40185471
- Korošec P, González-de-Olano D, Lyons JJ. Alpha-tryptase overexpression as a modifier of mast cell-mediated reactions. J Allergy Clin Immunol Pract. 2025;13(12):3180–3186. — PubMed PMID: 41429728
- Rymut SM, Sukumaran S, Sperinde G, et al. Dose-dependent inactivation of airway tryptase with a novel dissociating anti-tryptase antibody (MTPS9579A) in healthy participants: a randomized trial. Clin Transl Sci. 2022;15(2):451–463. — PubMed PMID: 34581002
- Rhee H, Henderson LM, Bauer RN, et al. Airway tryptase levels inform the lack of clinical efficacy of the tryptase inhibitor MTPS9579A in asthma. Allergy. 2024;79(11):2993–3004. — PubMed PMID: 39250147
- Iqbal S, Baxter JA, Adams KE. A case of hereditary alpha tryptasemia and presumptive eosinophilic granulomatosis with polyangiitis. J Allergy Clin Immunol Glob. 2025;4(3):100481. — PubMed PMID: 40458680
PubMed Topic Searches
Curated PubMed topic searches for HαT and adjacent mast cell biology. Each link opens a live PubMed query so you always see current studies.
- PubMed: Hereditary alpha tryptasemia
- PubMed: TPSAB1 copy number variant
- PubMed: Tryptase, MCAS, and mastocytosis
- PubMed: Lyons — hereditary tryptasemia
- PubMed: Alpha tryptase and anaphylaxis
- PubMed: Venom anaphylaxis and tryptase
- PubMed: PAR-2, mast cells, and tryptase
- PubMed: Hypermobility and mast cell activation
Connections
- Neurology
- Mast Cell Activation Syndrome Overview
- H1 and H2 Blocker Stacks
- Cromolyn and Ketotifen Protocols
- Mediators and Symptom Map
- Mast Cell Activation Syndrome Testing Guide
- Low-Histamine Diet
- Triggers and Flare Management
- Natural Mast Cell Stabilizers
- Hormone Sensitivity and Menstrual Flares
- Alpha-Gal Syndrome
- Alpha-Gal Natural History and Tolerance
- Postural Orthostatic Tachycardia Syndrome
- Postural Orthostatic Tachycardia Syndrome-MCAS-EDS Triad
- Allergies
- Small Intestinal Bacterial Overgrowth
- Quercetin
- Vitamin C
- Testing and Diagnosis
- Tryptase — the baseline serum test whose persistent elevation defines the HαT trait.