Boswellia
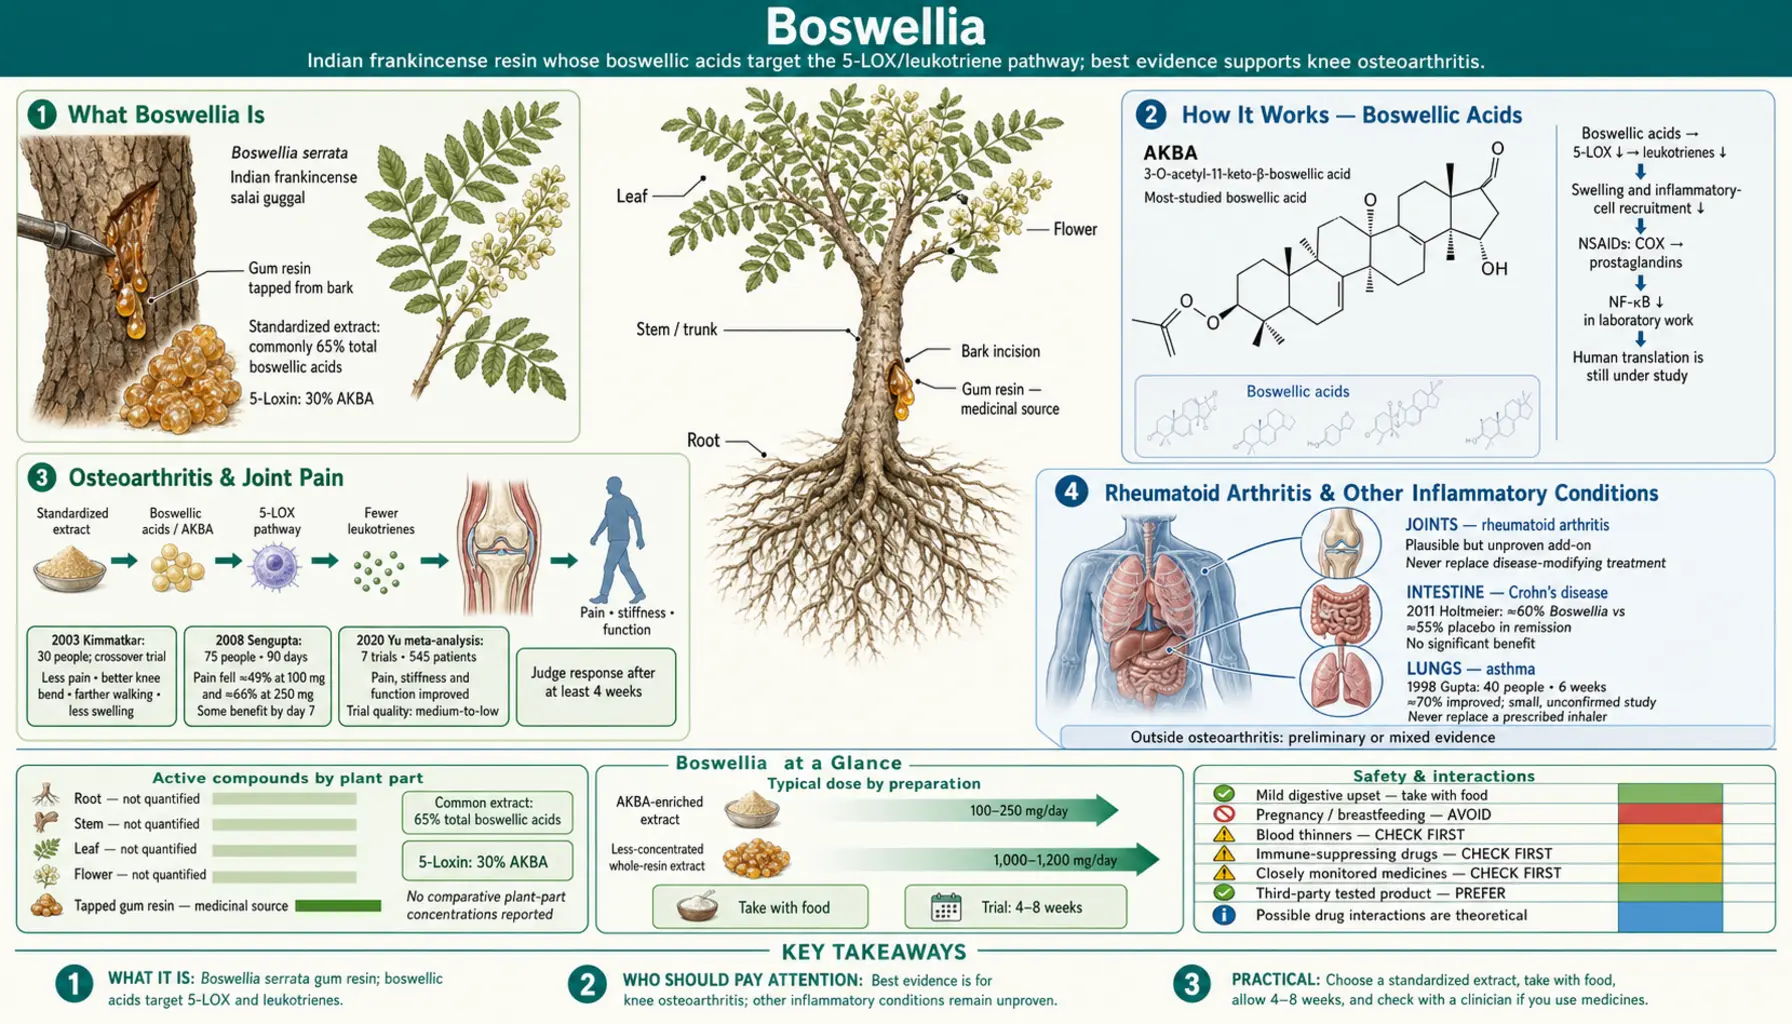
Boswellia (Boswellia serrata), the resin of a tree native to India and known as Indian frankincense, has been used in Ayurvedic medicine for centuries to calm inflammation and ease joint pain. Modern interest centers on its active compounds, the boswellic acids, which work through a different pathway than common anti-inflammatory drugs. The strongest evidence is for knee osteoarthritis, where several randomized controlled trials and a 2020 meta-analysis show meaningful reductions in pain and stiffness, though the trials are mostly small and of modest quality. For other conditions — rheumatoid arthritis, inflammatory bowel disease, and asthma — the evidence is preliminary or mixed, including at least one well-run trial that found no benefit for Crohn's disease. Boswellia was generally well tolerated in the trials.
Table of Contents
What Boswellia Is
Boswellia is the gum resin tapped from the bark of the Boswellia serrata tree, which grows in the dry hills of India and parts of the Middle East and Africa. When the bark is cut, the tree weeps a fragrant resin that hardens into the aromatic substance we know as frankincense. The Indian species is often called Indian frankincense, and in traditional Ayurvedic texts it goes by the name salai guggal (sometimes written shallaki).
People have used this resin for a very long time — it appears in Ayurvedic medicine going back well over a thousand years, prescribed for joint problems, swelling, digestive complaints, and breathing difficulties. That long history is interesting, but it is not the same as proof that it works. What makes Boswellia worth a closer look today is that researchers have identified the specific molecules responsible for its effects and tested them in actual clinical trials.
When you buy a Boswellia supplement, you are usually buying a concentrated standardized extract, not the raw resin. Standardization means the manufacturer measures and guarantees a certain percentage of the active compounds in each capsule. Most products are standardized to a total of 65% boswellic acids, and the better-studied extracts are further enriched for one particular boswellic acid called AKBA (more on that below). The main osteoarthritis trials used AKBA-standardized extracts (for example, one standardized to 30% AKBA), which is why AKBA comes up so often in the research.
How It Works — Boswellic Acids
The active ingredients in Boswellia are a family of compounds called boswellic acids. There are several of them, but the one that has drawn the most scientific attention is a mouthful named 3-O-acetyl-11-keto-β-boswellic acid, mercifully abbreviated to AKBA. AKBA is considered the most potent of the group, which is why premium extracts are enriched for it.
Here is the part that makes Boswellia genuinely different from a typical painkiller. Most over-the-counter anti-inflammatory drugs — ibuprofen, naproxen, aspirin, the whole class called nonsteroidal anti-inflammatory drugs (NSAIDs) — work by blocking an enzyme called COX (cyclooxygenase). Blocking COX reduces inflammatory messengers called prostaglandins, which is great for pain but is also why nonsteroidal anti-inflammatory drugs can irritate the stomach lining and stress the kidneys over time.
Boswellic acids take a different route. Their best-described action is blocking a separate enzyme called 5-lipoxygenase, usually shortened to 5-LOX. Think of inflammation as a factory with two main production lines. Nonsteroidal anti-inflammatory drugs shut down the COX line (prostaglandins). Boswellia targets the 5-LOX line instead, which produces a different set of inflammatory chemicals called leukotrienes. Leukotrienes drive swelling, recruit inflammatory cells, and play a role in conditions from arthritis to asthma. By turning down leukotriene production, Boswellia aims to reduce inflammation through a pathway that nonsteroidal anti-inflammatory drugs largely leave untouched.
Laboratory work in the 1990s and 2000s, much of it led by the German pharmacologist H.P.T. Ammon, showed that AKBA inhibits 5-LOX in an unusual way — it binds to a specific site on the enzyme and acts as a kind of dimmer switch rather than competing head-to-head with the enzyme's normal target. Boswellic acids also appear to dial down other inflammatory signals, including a master switch called NF-κB and an enzyme involved in cartilage breakdown. It is worth being honest here: a great deal of this mechanistic work was done in test tubes and on isolated cells, sometimes at concentrations higher than what the body easily achieves after swallowing a capsule. The mechanism is real and well-characterized in the lab, but how completely it translates into the human body is still an active research question — which is exactly why the clinical trials matter more than the biochemistry.
Osteoarthritis & Joint Pain
This is where Boswellia has its strongest case. Osteoarthritis is the common "wear-and-tear" arthritis in which the cartilage cushioning a joint gradually thins, leaving bones to grind and the joint to ache, stiffen, and swell — most often in the knees. Several randomized controlled trials have tested Boswellia extracts here, and the results have been encouraging.
An early and frequently cited trial by Kimmatkar and colleagues in 2003 studied 30 people with knee osteoarthritis in a crossover design (each person took both the real extract and a placebo at different times, so they served as their own comparison). Everyone who took the Boswellia extract reported less knee pain, better knee bend, and the ability to walk farther, with less joint swelling — and the difference versus placebo was statistically significant. It was a small study, but a clean one.
A larger and more rigorous trial came from Sengupta and colleagues in 2008, testing an extract standardized to 30% AKBA in 75 people with knee osteoarthritis over 90 days. The results were striking on paper: compared with placebo, pain on a standard visual scale fell by about 49% at the lower 100 mg dose and about 66% at the 250 mg dose, with parallel improvements in the WOMAC and Lequesne function scores that doctors use to grade arthritis. Notably, some benefit appeared as early as 7 days. The same research group followed up in 2010 with a head-to-head trial of two AKBA-standardized extracts at 100 mg a day: both gave significant pain and function gains at 90 days, and gains as early as 7 days were reported for one of the two standardized extracts.
Pulling the trials together, a 2020 systematic review and meta-analysis by Yu and colleagues combined seven randomized trials covering 545 patients. Its conclusion is the honest bottom line for this section: Boswellia appears to be an effective and reasonably safe option for osteoarthritis, with benefits for pain, stiffness, and function, and the authors suggested taking it for at least four weeks to judge whether it helps. A 2014 Cochrane review of herbal therapies for osteoarthritis rated as high quality the evidence from two studies (85 people) that 90 days of 100 mg of an enriched Boswellia serrata extract improved symptoms compared with placebo; it rated the evidence for the other Boswellia extracts as moderate, low or very low quality.
Two cautions keep this realistic. First, the individual trials are small — most enrolled a few dozen people — and reviewers rated their overall quality as medium-to-low, with some at unclear risk of bias. Second, the very large percentage improvements reported in some industry-conducted trials may look more dramatic than what you would personally feel; effect sizes in supplement research often shrink when studies get bigger and more independent. So a fair expectation is a modest-to-moderate, real reduction in knee pain and stiffness for many people who try it — not a cure, and not a guarantee.
Rheumatoid Arthritis & Other Inflammatory Conditions
Because Boswellia tamps down inflammation, it has been tried in several conditions beyond osteoarthritis. Here the evidence gets thinner and the honest verdict is "promising in places, but not proven."
Rheumatoid arthritis (RA) is a different beast from osteoarthritis — it is an autoimmune disease in which the immune system attacks the joints. The theoretical case for Boswellia is reasonable, and a few small or combination-product studies have been done, but there is no solid body of high-quality trials showing that Boswellia reliably controls rheumatoid arthritis. Rheumatoid arthritis is a serious, joint-destroying disease that is treated with disease-modifying prescription drugs (like methotrexate or biologics).
Inflammatory bowel disease (IBD) — ulcerative colitis and Crohn's disease — is an area where the leukotriene-blocking mechanism is biologically appealing, and early studies were hopeful. An older trial suggested a Boswellia gum-resin preparation worked about as well as the standard drug sulfasalazine for ulcerative colitis, and another reported it was comparable to mesalazine in active Crohn's disease. But the most rigorous test, a 2011 randomized, placebo-controlled trial by Holtmeier and colleagues, set out to see whether Boswellia could keep Crohn's disease in remission — and it could not. About 60% of the Boswellia group and 55% of the placebo group stayed in remission, a difference that was statistically meaningless. The extract was safe and well tolerated, but it simply did not beat placebo. This is an important, clarifying result: a plausible mechanism and some early positive studies do not always survive a well-designed trial.
Asthma is interesting because leukotrienes are well known to drive airway inflammation — in fact, prescription asthma drugs called leukotriene blockers (such as montelukast) work on the very pathway Boswellia targets. A small 1998 trial by Gupta and colleagues gave Boswellia gum resin to 40 people with bronchial asthma for six weeks; about 70% improved on measures like breathlessness, attack frequency, and lung-function tests, versus a much smaller fraction on placebo. That is an encouraging signal, but it is a single small study from many years ago and it has not been confirmed by large modern trials. Asthma can be life-threatening, and the Boswellia evidence for it is this one small study.
The throughline for this whole section: outside of osteoarthritis, the research shows Boswellia as a plausible but unproven add-on, not an established treatment for a serious inflammatory or autoimmune disease.
How It Is Used
With Boswellia, the label details say more about a product than its brand name does. The practical points from the trials and labels:
- Standardized extracts. A standardized supplement states a percentage of boswellic acids — commonly 65% total boswellic acids. The AKBA-enriched extracts used in the trials also state a percentage of AKBA (for example, standardized to 30% AKBA). Raw resin or an unstandardized "Boswellia powder" gives no way to know how much active compound it contains.
- Typical trial doses. In the osteoarthritis studies, effective amounts ranged widely depending on the extract. AKBA-enriched extracts were used at roughly 100–250 mg per day of the concentrated extract. Studies using less concentrated whole-resin extracts used higher total amounts — often in the range of 1,000–1,200 mg per day, sometimes split into two or three doses. Doses are not interchangeable between products: "300 mg" of one extract is not equivalent to "300 mg" of another.
- With food. Boswellic acids are fat-soluble and are absorbed better when taken with a meal that contains some fat. This also tends to reduce the chance of mild stomach upset.
- Time frame. Although some trials saw improvement within a week, the 2020 meta-analysis authors suggested at least four weeks of use to judge whether it helps. The osteoarthritis trials described above lasted up to 90 days.
Safety & Interactions
Boswellia has a reassuring safety record in the clinical trials — it is generally well tolerated, and even the trial that found no benefit for Crohn's disease specifically noted a good safety profile. The cautions that apply:
- Most common side effects are mild and digestive: nausea, acid reflux, stomach discomfort, or loose stools. Taking it with food usually helps.
- Pregnancy and breastfeeding: there is not enough safety data on Boswellia in pregnancy, in women trying to conceive, or in breastfeeding, and traditional sources have long flagged concern about effects on the uterus.
- Possible drug interactions: because Boswellia is processed by the same liver enzymes (the cytochrome P450 system) that handle many prescription medications, there is a theoretical chance it could change the levels of certain drugs. That matters most for medicines with a narrow safety margin — blood thinners, immune-suppressing drugs, and other medicines whose levels are checked with blood tests — where a small change in level can cause bleeding, rejection or toxicity.
- Quality varies. Supplements are not regulated as strictly as medicines. Third-party testing and a clearly labeled standardization are the ways to check that a product contains what its label claims.
- Add-on, not replacement. This is the most important point. The research described above does not show Boswellia standing in for prescribed treatment of rheumatoid arthritis, inflammatory bowel disease, asthma, or any serious condition, and the interaction concern above applies most to people who take regular medication.
The Bottom Line
Boswellia is one of the more credible herbal anti-inflammatories, mainly because we understand how it works and because it has actually been put through randomized trials rather than relying on tradition alone. Its mechanism — blocking the 5-LOX/leukotriene pathway — is genuinely different from how ibuprofen and other nonsteroidal anti-inflammatory drugs work, which makes it an appealing option for people who cannot tolerate those drugs.
The evidence is strongest for knee osteoarthritis, where the trials studied easing pain and stiffness. There, the evidence supports a fair, realistic expectation: a modest-to-moderate reduction in pain and improvement in function over a few weeks, in a substantial fraction of people — though not everyone responds, and the trials behind those numbers are small.
For rheumatoid arthritis, inflammatory bowel disease, or asthma, the science is too preliminary or too mixed to count on Boswellia, and at least one strong trial came up empty for Crohn's. In the joint-pain trials, standardized extracts were low-risk and modestly helped joint pain. That is a fair and honest place to land.
Key Research Papers
- Sengupta K, Alluri KV, Satish AR, et al. (2008). A double blind, randomized, placebo controlled study of the efficacy and safety of 5-Loxin for treatment of osteoarthritis of the knee. Arthritis Research & Therapy, 10(4):R85. — The largest single RCT of an AKBA-enriched extract: significant, dose-dependent reductions in knee-OA pain and improved function, with some benefit by day 7. — doi:10.1186/ar2461
- Kimmatkar N, Thawani V, Hingorani L, Khiyani R (2003). Efficacy and tolerability of Boswellia serrata extract in treatment of osteoarthritis of knee — a randomized double blind placebo controlled trial. Phytomedicine, 10(1):3–7. — Early crossover trial in 30 patients; everyone on Boswellia reported less knee pain, better flexion, and farther walking versus placebo. — doi:10.1078/094471103321648593
- Sengupta K, Krishnaraju AV, Vishal AA, et al. (2010). Comparative efficacy and tolerability of 5-Loxin and Aflapin against osteoarthritis of the knee: a double blind, randomized, placebo controlled clinical study. International Journal of Medical Sciences, 7(6):366–377. — Two AKBA-standardized extracts (100 mg a day) both significantly improved knee-OA pain and function at 90 days; improvement as early as day 7 was reported for one of the two extracts. — doi:10.7150/ijms.7.366
- Yu G, Xiang W, Zhang T, et al. (2020). Effectiveness of Boswellia and Boswellia extract for osteoarthritis patients: a systematic review and meta-analysis. BMC Complementary Medicine and Therapies, 20:225. — Pooled 7 trials (545 patients); Boswellia improved pain, stiffness, and function, with at least 4 weeks of use recommended — but trial quality was medium-to-low. — doi:10.1186/s12906-020-02985-6
- Cameron M, Chrubasik S (2014). Oral herbal therapies for treating osteoarthritis. Cochrane Database of Systematic Reviews, (5):CD002947. — Independent Cochrane review: high-quality evidence from two studies (85 participants) that 90 days of 100 mg enriched Boswellia serrata extract improved pain and function versus placebo; moderate- to very-low-quality evidence for other Boswellia extracts; no serious adverse events reported. — doi:10.1002/14651858.CD002947.pub2
- Holtmeier W, Zeuzem S, Preiss J, et al. (2011). Randomized, placebo-controlled, double-blind trial of Boswellia serrata in maintaining remission of Crohn's disease: good safety profile but lack of efficacy. Inflammatory Bowel Diseases, 17(2):573–582. — Well-designed negative trial: Boswellia was safe but did not beat placebo at keeping Crohn's disease in remission (~60% vs ~55%). — doi:10.1002/ibd.21345
- Ammon HPT (2016). Boswellic acids and their role in chronic inflammatory diseases. Advances in Experimental Medicine and Biology, 928:291–327. — Authoritative mechanism review explaining how AKBA and related boswellic acids inhibit 5-lipoxygenase and other inflammatory pathways. — doi:10.1007/978-3-319-41334-1_13
Conditions Boswellia Is Used For
Each condition below links to its page. The coloured half of every capsule shows how much human evidence supports this herb for that specific use — traditional use is history, not proof, and is marked as such.
Connections
- All Herbs
- Boswellia History
- Boswellia Benefits
- Turmeric
- Willow Bark
- Ginger
- Tart Cherry
- Arthritis
- Osteoarthritis — the joint disease Boswellia has its strongest trial evidence for.
- Conditions on this site that reference this page: Nonsteroidal Anti-Inflammatory Drug Strategy for Ankylosing Spondylitis · DMARDs and Biologics for Rheumatoid Arthritis · Exercise and Joint Protection in Rheumatoid Arthritis · Herbs and Supplements for Rheumatoid Arthritis · Omega-3 Fatty Acids and Fish Oil for Rheumatoid Arthritis · Crohn's Disease · Small Intestinal Bacterial Overgrowth Root Causes · Ulcerative Colitis