⚠ Evidence warning: Clinical trials or other evidence do not support the claim that mesalazine reduces recurrence risk and symptoms after acute uncomplicated diverticulitis. This page keeps it as a report of what people, websites or other media say.
Diverticulitis
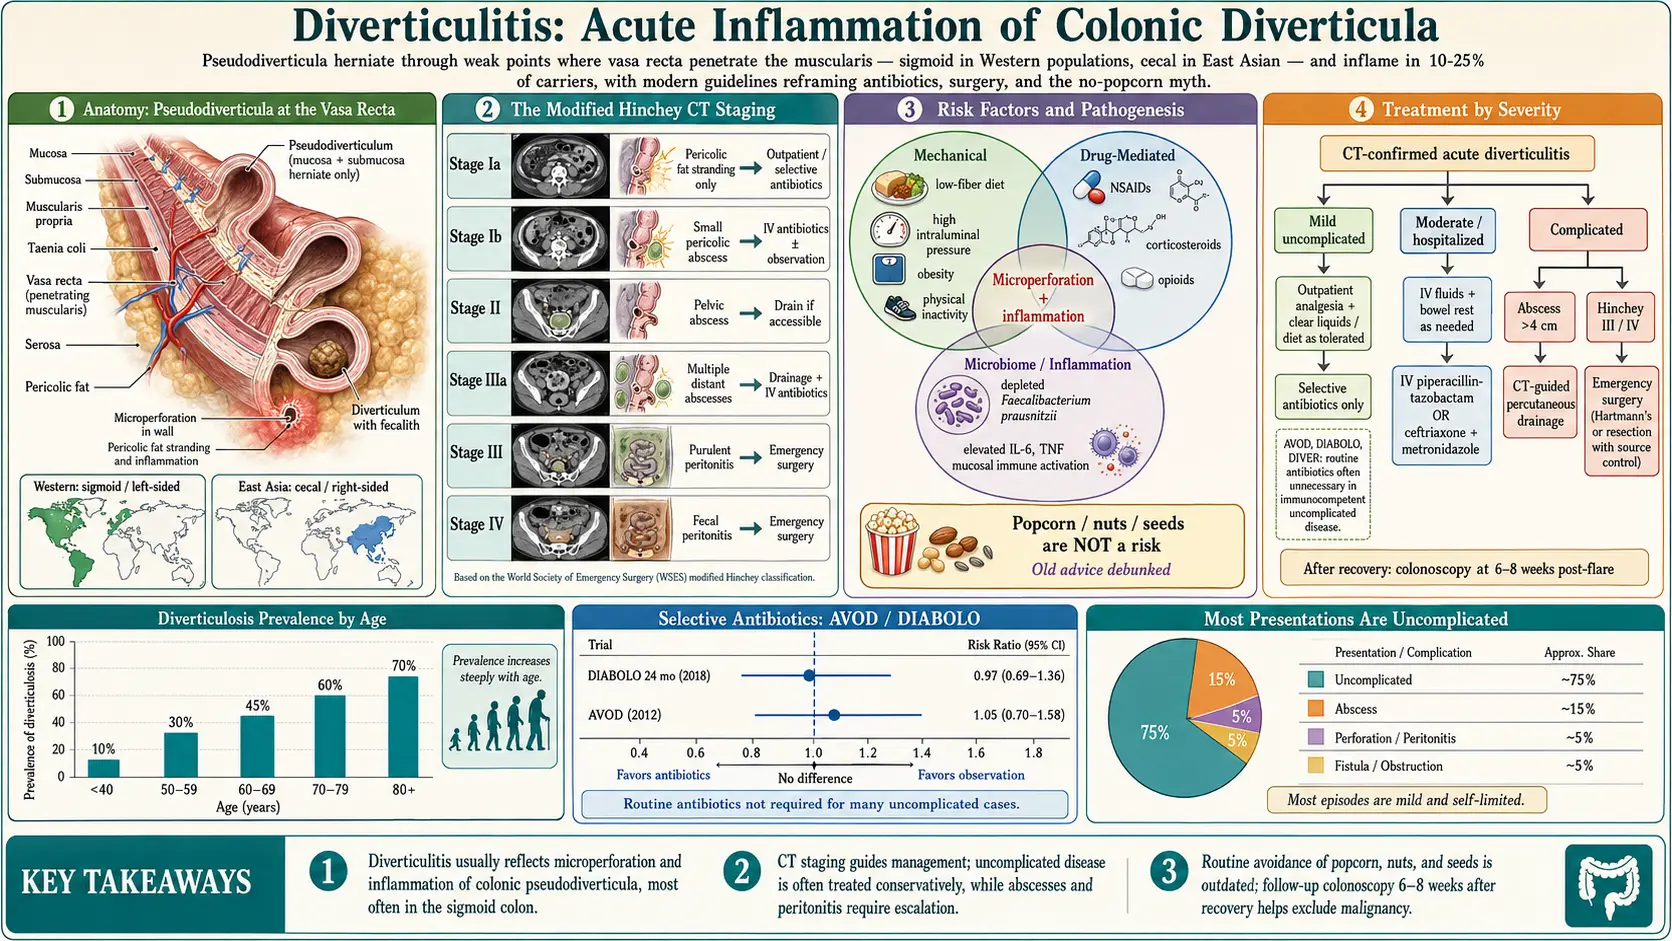
Table of Contents
1. Overview
Diverticular disease of the colon encompasses a spectrum of conditions arising from colonic diverticula — acquired pulsion herniae of the colonic mucosa and submucosa through weaknesses in the muscularis propria at sites where vasa recta penetrate the bowel wall. The spectrum includes:
- Diverticulosis: The asymptomatic presence of diverticula (the anatomical substrate); affects the majority of individuals with diverticula
- Symptomatic uncomplicated diverticular disease (SUDD): Chronic or recurrent abdominal symptoms attributable to diverticula in the absence of macroscopic inflammation or complications
- Diverticulitis: Macroscopic inflammation and/or infection of one or more diverticula, with a spectrum from mild uncomplicated diverticulitis to complicated disease (abscess, perforation, fistula, obstruction)
- Diverticular hemorrhage: Acute lower gastrointestinal hemorrhage from rupture of a vas rectum at the neck or dome of a diverticulum
The sigmoid colon is the predominant site in Western populations due to high intraluminal pressures generated in this segment. Right-sided diverticulitis predominates in East Asian populations.
2. Epidemiology
Diverticulosis is one of the most prevalent gastrointestinal conditions in the Western world. Autopsy studies estimate prevalence of approximately 5% in individuals under 40, rising to 30% by age 60 and 65–70% by age 85 in Western populations. The overall prevalence in the United States is estimated at 35–50% in adults over 50, corresponding to approximately 70 million Americans with diverticulosis.
Guidelines have long stated that 10–25% of people with diverticulosis develop diverticulitis over a lifetime, but that figure was based on limited data gathered before colonoscopy was widespread. In a 2013 study of 2,222 people whose diverticulosis was found on colonoscopy in a Los Angeles veterans' health system, 95 (4.3%) developed diverticulitis over 11 years, and only 23 (1%) when the diagnosis had to be confirmed by imaging or surgery. Younger people had the higher risk: each extra decade of age at diagnosis lowered the risk by 24%. Annually, diverticulitis accounts for approximately 300,000 hospitalizations and 1.5 million outpatient visits in the US, with direct healthcare costs exceeding $2 billion. The incidence of acute diverticulitis is increasing, particularly in younger adults (under 50), where it now accounts for 25–30% of all diverticulitis hospitalizations.
Complicated diverticulitis accounts for 15–20% of all acute diverticulitis episodes. Perforation carries significant mortality (5–20%), particularly in elderly and immunocompromised patients and when surgery is required.
3. Pathophysiology
Diverticulosis Formation
Colonic diverticula in Western populations are pseudodiverticula (false diverticula) — containing only mucosa and submucosa, lacking the muscularis propria layer. They form at anatomical weak points where vasa recta (terminal branches of the marginal artery) penetrate the circular muscle layer to supply the submucosa and mucosa. High intraluminal pressures — generated by segmental colonic contractions against formed stool in the narrow sigmoid — drive mucosal herniation through these points.
The "low-fiber hypothesis" proposes that reduced dietary fiber leads to smaller, denser stools requiring greater phasic contraction pressures for propulsion. Structural changes in the colonic wall (increased elastin deposition, collagen cross-linking, and reduced smooth muscle compliance with aging) amplify susceptibility. Microbiome dysbiosis and increased intestinal permeability may perpetuate low-grade mucosal inflammation even in "asymptomatic" diverticulosis.
Diverticulitis Pathogenesis
The exact initiating event is debated. The traditional erosion hypothesis proposes that inspissated fecal material (fecalith) within a diverticulum causes pressure-mediated erosion of the diverticular wall, leading to micro- or macro-perforation and pericolic inflammation. Alternatively, increased intraluminal pressure from segmental contraction may directly cause microperforations.
Colonic microbiome dysbiosis — with relative depletion of Faecalibacterium prausnitzii and overgrowth of Bacteroides and Fusobacterium species — leads to mucosal immune dysregulation and susceptibility to inflammation. Mast cell activation and increased mucosal pro-inflammatory cytokines (interleukin-6 (IL-6), tumor necrosis factor alpha (TNF-α)) have been demonstrated in SUDD and are implicated in the transition to overt diverticulitis. The degree of pericolic involvement determines classification into uncomplicated (confined) versus complicated (abscess, free perforation) disease.
4. Etiology and Risk Factors
Risk factors for diverticulosis development:
- Advancing age (most important — strongly age-associated)
- Low dietary fiber intake (relative risk approximately 1.3–2.0 for highest vs. lowest fiber quintile)
- Western dietary pattern (high in processed foods, red meat, refined carbohydrates)
- Physical inactivity — sedentary lifestyle
- Obesity (body mass index (BMI) >30) — particularly visceral adiposity
- Connective tissue disorders: Marfan syndrome, Ehlers-Danlos syndrome (associated with right-sided diverticulosis)
Risk factors for diverticulitis in individuals with diverticulosis:
- Nonsteroidal anti-inflammatory drug (NSAID) use (odds ratio (OR) ~1.5–2.5; impairs mucosal prostaglandin defenses and promotes microperforation)
- Corticosteroid use (odds ratio ~2.0; impairs immune response and mucosal repair)
- Opioid use (reduces colonic motility, increases intraluminal pressure)
- Immunosuppression (transplant recipients, human immunodeficiency virus (HIV)/acquired immunodeficiency syndrome (AIDS), chemotherapy): increased severity and atypical presentations
- Smoking (odds ratio ~1.4)
- Physical inactivity and obesity
- Red and processed meat consumption
- Low dietary fiber intake — controversial for diverticulitis specifically (some studies show no independent protective effect beyond diverticulosis prevention)
5. Clinical Presentation
Uncomplicated diverticulitis (75–80% of acute episodes):
- Acute onset left lower quadrant (LLQ) pain (most common) — constant, dull, or cramping; right-sided or periumbilical pain in right-sided diverticulitis (more common in East Asian patients) or cecal diverticulitis (may mimic appendicitis)
- Low-grade fever (38–38.5°C)
- Localized tenderness in LLQ on palpation; voluntary guarding; bowel sounds typically present
- Altered bowel habits (constipation more common than diarrhea; either may occur)
- Nausea, anorexia
- Urinary symptoms (dysuria, frequency) if pericolic inflammation involves the bladder or ureter
Complicated diverticulitis (20–25% of acute episodes):
- Pericolic abscess: Fever >38.5°C, more severe pain, tender palpable mass (if large), raised white blood cell count (WBC)
- Free perforation with peritonitis: Sudden severe generalized abdominal pain, peritoneal signs (board-like rigidity, rebound tenderness), absent bowel sounds, septic shock — surgical emergency
- Fistula: Colovesical fistula presents with pneumaturia, fecaluria, recurrent urinary tract infections (UTIs); colovaginal fistula with vaginal flatus or feculent vaginal discharge; colocutaneous fistula with skin drainage
- Colonic obstruction: Progressive abdominal distension, obstipation, vomiting — from acute inflammation, abscess compression, or chronic fibrous stricture after recurrent episodes
Differential diagnosis: Colorectal carcinoma (may be indistinguishable clinically and radiologically), irritable bowel syndrome, ischemic colitis, inflammatory bowel disease (Crohn's colitis), appendicitis (right-sided), ovarian cyst, tubo-ovarian abscess, endometriosis, gynecologic pathology.
6. Diagnosis
Laboratory Studies
- Full blood count: leukocytosis (WBC >11,000/mm³) in 65–75%; absence does not exclude diverticulitis
- C-reactive protein (CRP): elevated (>50 mg/L typical; >150 mg/L suggests complicated disease); most useful for severity assessment and monitoring response
- Serum creatinine and electrolytes: baseline renal function; hyperkalemia may suggest obstruction
- Urinalysis: mild pyuria or hematuria may occur from ureteral or bladder proximity to inflamed colon; does not necessarily indicate urinary tract infection (UTI)
- Blood cultures: in febrile patients with suspected complicated disease or sepsis
Imaging
Computed tomography (CT) abdomen and pelvis with intravenous (IV) contrast is the imaging modality of choice (sensitivity 94%, specificity 99% for diverticulitis):
- Characteristic findings: pericolic fat stranding, diverticular thickening of the sigmoid colon wall, presence of diverticula, pericolic abscess (if complicated)
- Computed tomography allows classification of severity (Hinchey/modified Hinchey classification) and guides management decisions regarding interventional radiology drainage or surgery
- Computed tomography colonography (virtual colonoscopy) can be performed after acute episode resolution to evaluate the colon if optical colonoscopy is not feasible
Abdominal ultrasound: Can identify pericolic inflammation and diverticula in experienced hands; sensitivity approximately 92%, specificity 90%; preferred in pregnancy, young patients, and when limiting radiation exposure; operator-dependent
Magnetic resonance imaging (MRI) abdomen/pelvis: Excellent sensitivity and specificity without radiation; reserved for pregnant patients, young adults, and equivocal computed tomography cases; less available in acute settings
Hinchey Classification (Modified — Computed Tomography-Based)
The modified Hinchey classification (Wasvary and colleagues, 1999), as set out in a 2012 review of diverticular disease classifications, has six stages:
- Stage 0: Mild clinical diverticulitis (diverticula, with or without thickening of the colon wall on computed tomography)
- Stage Ia: Confined inflammation or phlegmon around the colon (pericolic)
- Stage Ib: Pericolic or mesocolic abscess
- Stage II: Pelvic, distant intra-abdominal, or retroperitoneal abscess
- Stage III: Generalized purulent peritonitis (pus spread through the abdominal lining)
- Stage IV: Generalized fecal peritonitis (stool spread through the abdominal lining)
Colonoscopy
Colonoscopy is contraindicated during acute diverticulitis (perforation risk). It has traditionally been advised 6–8 weeks after the attack settles. The 2021 American Gastroenterological Association (AGA) Clinical Practice Update states that whether a person needs a colonoscopy after an episode depends on their history, their most recent colonoscopy, and how severe the disease was and how it ran its course; it notes that a colon cancer is rarely misdiagnosed as diverticulitis. When it is done, its purposes are to:
- Exclude colorectal carcinoma (computed tomography may not distinguish diverticulitis from perforated colon cancer)
- Evaluate for inflammatory bowel disease (IBD), ischemic colitis, or other colonic pathology
- Assess extent and distribution of diverticulosis
7. Treatment
Uncomplicated Diverticulitis
Outpatient management (mild uncomplicated, hemodynamically stable, able to tolerate oral fluids, no significant comorbidities):
- Clear liquid diet progressing to low-fiber diet as tolerated; evidence does not support routine bowel rest in mild uncomplicated disease
- Antibiotics — evolving paradigm: Randomized controlled trials (AVOD, DIABOLO and DINAMO) found that people with mild uncomplicated diverticulitis treated without antibiotics did as well as those given antibiotics in terms of hospital admissions, complications, recurrence, or need for surgery. In the 2021 Spanish DINAMO trial of 480 people with mild diverticulitis treated at home, hospital admission occurred in 8 of 242 (3.3%) treated without antibiotics versus 14 of 238 (5.8%) given them, and return visits to the emergency department in about 7% of both groups. (The earlier Spanish DIVER trial compared home with hospital care; every patient in it received antibiotics.) The 2021 AGA update states that antibiotics can be used selectively rather than routinely in immunocompetent people with mild uncomplicated diverticulitis, and are strongly advised for immunocompromised people. Current guidelines (ACG, AGA, and the European Association for Endoscopic Surgery, EAES) recommend selective antibiotic use — reserving antibiotics for immunocompromised patients, significant comorbidities, fever >38.5°C, leukocytosis >15,000/mm³, or significant C-reactive protein elevation (>150 mg/L).
- When antibiotics are indicated (oral): amoxicillin-clavulanate 875/125 mg twice daily × 7–10 days (first-line); alternatively ciprofloxacin 500 mg twice daily + metronidazole 500 mg three times daily; trimethoprim-sulfamethoxazole double-strength (DS) twice daily + metronidazole in penicillin-allergic patients
- Pain relief: paracetamol (acetaminophen) is the usual first choice; nonsteroidal anti-inflammatory drugs (NSAIDs) and opioids are kept to a minimum where possible (nonsteroidal anti-inflammatory drugs worsen mucosal integrity; opioids increase colonic pressure)
Inpatient management (fever >38.5°C, WBC >15,000/mm³, inability to tolerate oral intake, C-reactive protein >150 mg/L, elderly or immunocompromised, failed outpatient management, or uncertain diagnosis):
- Intravenous fluids, bowel rest (clear liquids advancing as tolerated)
- Intravenous antibiotics: piperacillin-tazobactam 3.375 g intravenous every 6 hours; or ceftriaxone 2 g intravenous daily + metronidazole 500 mg intravenous every 8 hours; or ertapenem 1 g intravenous daily (for penicillin allergy or polymicrobial coverage)
- Transition to oral antibiotics after clinical improvement (48–72 hours afebrile, WBC normalizing, tolerating oral intake)
Complicated Diverticulitis
- Small pericolic abscess (Hinchey Ib, <4 cm): intravenous antibiotics alone; high success rate (85–90%) without drainage
- Larger (≥4 cm) or distant abscess (Hinchey Ib–II): computed tomography-guided or ultrasound-guided percutaneous drainage + intravenous antibiotics; drainage of >4 cm abscesses reduces failure rate and avoids emergent surgery; elective sigmoid resection planned 4–6 weeks after resolution in selected patients
- Free perforation with peritonitis (Hinchey III/IV): Emergency surgery; Hartmann's procedure (sigmoid resection, end colostomy, closure of rectal stump) or primary resection and anastomosis with or without diverting ileostomy (in select hemodynamically stable patients with experienced surgeon); in randomized trials for Hinchey III (the LOLA arm of the LADIES trial, and SCANDIV), laparoscopic lavage and drainage did not do better than resection and led to more reoperations or early trial stopping
- Fistula: Surgical resection with fistula takedown and anastomosis; one-stage procedures preferred in elective settings
- Colonic obstruction: Endoscopic stenting as bridge to surgery vs. emergency resection depending on degree of obstruction and patient condition
Elective Sigmoid Colectomy
The contemporary view (supported by American Society of Colon and Rectal Surgeons guidelines, 2020) is that elective sigmoid resection should be individualized rather than based on number of episodes:
- Recommended after complicated diverticulitis (abscess, fistula, stricture)
- Considered in patients with frequent recurrences severely affecting quality of life
- Considered in immunocompromised patients
- Laparoscopic sigmoid colectomy is the preferred approach when technically feasible — reduced complications, shorter hospital stay, faster recovery
- The previous guideline of "elective resection after 2 uncomplicated episodes" is no longer supported — recurrence risk after second episode (<20%) does not justify routine resection
8. Complications
- Pericolic abscess: Most common complication; 10–15% of acute diverticulitis episodes; may complicate uncomplicated diverticulitis not treated with antibiotics
- Free perforation with peritonitis: Fecal peritonitis carries 20–30% mortality; purulent peritonitis 5–10% mortality; highest risk in elderly and immunocompromised
- Colovesical fistula: Most common diverticular fistula (65%); predominantly affects men (uterus protects posterior bladder in women); presents with pneumaturia, fecaluria, recurrent polymicrobial urinary tract infections
- Colovaginal fistula: Second most common; occurs in women; post-hysterectomy uterine absence increases risk
- Colonic stricture: From fibrosis following recurrent inflammation; may require resection; a cancer has to be ruled out as the cause
- Diverticular hemorrhage: Complicates 5% of diverticulosis; most common cause of acute lower gastrointestinal (GI) bleeding in the elderly; right-sided diverticula bleed more frequently than left-sided despite lower prevalence; 80% stop spontaneously; managed with colonoscopic hemostasis, angiographic embolization, or surgical resection
- Post-diverticulitis syndrome: Persistent abdominal symptoms after resolution of acute diverticulitis, attributable to visceral hypersensitivity and altered gut microbiome; overlaps clinically with irritable bowel syndrome (IBS) and may require management as a functional gastrointestinal disorder
9. Prognosis
The prognosis of uncomplicated diverticulitis is excellent with appropriate management; over 95% of patients with mild uncomplicated diverticulitis recover without sequelae. The recurrence rate after a first episode of uncomplicated diverticulitis is approximately 10–20% at 5 years, with most recurrences also being uncomplicated. The risk of complications at recurrence is not significantly higher than at first presentation.
After complicated diverticulitis (abscess, fistula), the risk of recurrent complicated diverticulitis is higher, supporting elective resection in these patients. Perforation with fecal peritonitis carries significant mortality (20–30%), particularly in elderly and immunocompromised patients requiring emergency surgery. Long-term complications of Hartmann's procedure (irreversible colostomy in a significant proportion due to non-reversal) substantially affect quality of life.
10. Prevention
- Dietary fiber: High-fiber diet (25–38 g/day from fruits, vegetables, legumes, whole grains) reduces the risk of diverticulosis development and may reduce SUDD; evidence specifically for preventing diverticulitis is less consistent
- Physical activity: Regular vigorous physical activity is associated with approximately 20–40% lower risk of diverticulitis in prospective cohort studies (Nurses' Health Study, Health Professionals Follow-up Study)
- Red meat: High red meat consumption (particularly unprocessed red meat >4 servings/week) is associated with increased diverticulitis risk (hazard ratio (HR) ~1.3–1.5)
- Nuts, seeds, popcorn: Historical advice to avoid these foods to prevent diverticulitis has been refuted by prospective data (Health Professionals Follow-up Study); these foods are not associated with increased diverticulitis risk and may actually be protective
- Mesalazine (mesalamine, 5-aminosalicylic acid): Mesalazine (1.6–3.0 g/day) reduces recurrence risk and SUDD symptoms after acute uncomplicated diverticulitis; use is not universally endorsed in guidelines but is widely used in clinical practice. The US DIVA trial (117 people after an attack of diverticulitis) found symptom scores fell in all groups with no significant difference between mesalamine and placebo, though complete symptom relief was more frequent with mesalamine at weeks 6 and 52; recurrence of diverticulitis was low and similar across groups. Two phase 3 trials (PREVENT1 and PREVENT2, 1,182 people treated for up to 2 years) found mesalamine did not reduce recurrence, and their authors concluded it is not recommended for this use. A 2017 Cochrane review of 7 trials (1,805 people) found recurrence in 31.3% with mesalamine versus 29.8% with control, with no evidence of an effect (very low quality evidence).
- Rifaximin: Cyclic rifaximin (400 mg twice daily × 7 days/month) reduces symptoms in SUDD and may reduce diverticulitis recurrence; more robust evidence in Italian guidelines
- Nonsteroidal anti-inflammatory drugs and other habits: The 2021 AGA update lists a high-quality diet, a normal body weight, physical activity, not smoking, and not using nonsteroidal anti-inflammatory drugs (except aspirin prescribed to prevent further heart disease) as the habits that lower the risk of recurrence; it adds that genes also contribute to diverticulitis risk
- Recurrence and surgery: The same update states that the risk of complicated diverticulitis is highest at the first attack, and that elective surgery is not decided by the number of attacks but discussed person by person, weighing the severity of disease, the person's preferences and values, and the risks and benefits
11. Recent Research and Advances
- Paradigm shift on antibiotics: The AVOD (Sweden and Iceland, 2012), DIABOLO (Netherlands, 2017), and DINAMO (Spain, 2021) trials found that routine antibiotic therapy for mild uncomplicated acute diverticulitis gave no benefit over pain relief and observation in immunocompetent patients with respect to complications, recurrence, or hospital readmission. AVOD (623 patients) found complications such as perforation or abscess in 1.9% without antibiotics versus 1.0% with them (P = 0.302, not a significant difference), a median hospital stay of 3 days in both groups, and readmission for recurrence within 1 year in 16% of both groups. DIABOLO (528 patients) found a median recovery time of 14 days with observation versus 12 days with antibiotics (not a significant difference) and a shorter hospital stay without antibiotics (2 versus 3 days). DINAMO (480 outpatients) found hospital admission in 3.3% without antibiotics versus 5.8% with them. A separate Spanish trial, DIVER (2014, 132 patients), compared home with hospital care, all patients receiving antibiotics: treatment failed in 3 versus 4 patients, and the cost per episode was three times lower at home. This has fundamentally changed management guidelines globally.
- Laparoscopic lavage rejection: The LADIES and SCANDIV trials (2015) found that laparoscopic lavage was not better than sigmoid resection for Hinchey III perforated diverticulitis, leading to withdrawal of this approach from standard guidelines. The LOLA arm of the LADIES trial (90 patients with purulent peritonitis) was stopped early by its safety board because of more events after lavage; major complications or death within 12 months occurred in 30 of 45 (67%) after lavage versus 25 of 42 (60%) after sigmoid resection. In SCANDIV (199 patients), severe complications within 90 days occurred in 30.7% after lavage versus 26.0% after resection (not a significant difference), but reoperations were more frequent after lavage (20.3% versus 5.7% in people without fecal peritonitis), and 4 sigmoid cancers were missed with lavage.
- Gut microbiome and diverticular disease: Metagenomic profiling has consistently identified dysbiosis in diverticulosis and diverticulitis, including depletion of butyrate-producing species (Roseburia intestinalis, Faecalibacterium prausnitzii) and enrichment of pro-inflammatory species. Fecal microbiota transplantation (FMT) and targeted probiotic strategies for SUDD and post-diverticulitis syndrome are under investigation.
- Post-diverticulitis syndrome phenotyping: Recognition that 20–30% of patients have persistent symptoms after acute diverticulitis ("post-diverticulitis irritable bowel" or functional overlay) has prompted studies of neuromodulators, low-FODMAP diet, and gut-directed psychotherapy in this population.
- Mesalamine for recurrence prevention: A 2017 Cochrane review of 7 randomized controlled trials (1,805 people) found no evidence that mesalamine prevents recurrent diverticulitis, rated the evidence very low quality, and called for better-designed trials.
- Personalized elective surgery decision-making: Risk calculators incorporating age, body mass index, C-reactive protein, and comorbidity score are being developed to individualize elective sigmoid colectomy recommendations beyond the traditional episode-count-based approach.
Key Research Papers
- Feuerstein JD, Falchuk KR. Diverticulosis and Diverticulitis. Mayo Clin Proc. 2016;91(8):1094–1104. — doi:10.1016/j.mayocp.2016.03.012
- Strate LL, Morris AM. Epidemiology, Pathophysiology, and Treatment of Diverticulitis. Gastroenterology. 2019;156(5):1282–1298. — doi:10.1053/j.gastro.2018.12.033
- Schultz JK, Azhar N, Binda GA, et al. European Society of Coloproctology: guidelines for the management of diverticular disease of the colon. Colorectal Dis. 2020;22(Suppl 2):5–28. — doi:10.1111/codi.15140
- Feingold D, Steele SR, Lee S, et al. Practice parameters for the treatment of sigmoid diverticulitis. Dis Colon Rectum. 2014;57(3):284–294. — doi:10.1097/DCR.0000000000000075
- Hall J, Hardiman K, Lee S, et al. The American Society of Colon and Rectal Surgeons Clinical Practice Guidelines for the Treatment of Left-Sided Colonic Diverticulitis. Dis Colon Rectum. 2020;63(6):728–747. — doi:10.1097/DCR.0000000000001679
- Jaung R, Nisbet S, Gosselink MP, et al. Antibiotics Do Not Reduce Length of Hospital Stay for Uncomplicated Diverticulitis in a Pragmatic Double-Blind Randomized Trial. Clin Gastroenterol Hepatol. 2021;19(3):503–510.e1. — doi:10.1016/j.cgh.2020.03.049
- Daniels L, Unlü Ç, de Korte N, et al. Randomized clinical trial of observational versus antibiotic treatment for a first episode of CT-proven uncomplicated acute diverticulitis. Br J Surg. 2017;104(1):52–61. — doi:10.1002/bjs.10309
- Schultz JK, Yaqub S, Wallon C, et al. Laparoscopic Lavage vs Primary Resection for Acute Perforated Diverticulitis: The SCANDIV Randomized Clinical Trial. JAMA. 2015;314(13):1364–1375. — doi:10.1001/jama.2015.12076
- Strate LL, Liu YL, Aldoori WH, Syngal S, Giovannucci EL. Obesity increases the risks of diverticulitis and diverticular bleeding. Gastroenterology. 2009;136(1):115–122. — doi:10.1053/j.gastro.2008.09.025
- Strate LL, Liu YL, Syngal S, Aldoori WH, Giovannucci EL. Nut, corn, and popcorn consumption and the incidence of diverticular disease. JAMA. 2008;300(8):907–914. — doi:10.1001/jama.300.8.907
- Aldoori WH, Giovannucci EL, Rockett HR, Sampson L, Rimm EB, Willett WC. A prospective study of dietary fiber types and symptomatic diverticular disease in men. J Nutr. 1998;128(4):714–719. — doi:10.1093/jn/128.4.714
- Binda GA, Cuomo R, Laghi A, et al. Practice parameters for the treatment of colonic diverticular disease: Italian Society of Colon and Rectal Surgery (SICCR) guidelines. Tech Coloproctol. 2015;19(10):615–626. — doi:10.1007/s10151-015-1370-x
- Tursi A, Brandimarte G, Elisei W, et al. Randomised clinical trial: mesalazine and/or probiotics in maintaining remission of symptomatic uncomplicated diverticular disease — a double-blind, randomised, placebo-controlled study. Aliment Pharmacol Ther. 2013;38(7):741–751. — doi:10.1111/apt.12463
- Peery AF, Crockett SD, Murphy CC, et al. Burden and Cost of Gastrointestinal, Liver, and Pancreatic Diseases in the United States: Update 2018. Gastroenterology. 2019;156(1):254–272. — doi:10.1053/j.gastro.2018.08.063
- Tursi A, Papa A, Danese S. Review article: the pathophysiology and medical management of diverticulosis and diverticular disease of the colon. Aliment Pharmacol Ther. 2015;42(6):664–684. — doi:10.1111/apt.13322
- Andeweg CS, Knobben L, Hendriks JC, Bleichrodt RP, van Goor H. How to diagnose acute left-sided colonic diverticular disease: proposal for a clinical scoring system. Ann Surg. 2011;253(5):940–946. — doi:10.1097/sla.0b013e3182113614
- Stollman N, Magowan S, Shanahan F, Quigley EM; DIVA Investigator Group. A randomized controlled study of mesalamine after acute diverticulitis: results of the DIVA trial. J Clin Gastroenterol. 2013;47(7):621–629. — PubMed PMID: 23426454
- Raskin JB, Kamm MA, Jamal MM, et al. Mesalamine did not prevent recurrent diverticulitis in phase 3 controlled trials. Gastroenterology. 2014;147(4):793–802. — PubMed PMID: 25038431
- Carter F, Alsayb M, Marshall JK, Yuan Y. Mesalamine (5-ASA) for the prevention of recurrent diverticulitis. Cochrane Database Syst Rev. 2017;10(10):CD009839. — PubMed PMID: 28973845
- Chabok A, Påhlman L, Hjern F, Haapaniemi S, Smedh K; AVOD Study Group. Randomized clinical trial of antibiotics in acute uncomplicated diverticulitis. Br J Surg. 2012;99(4):532–539. — PubMed PMID: 22290281
- Biondo S, Golda T, Kreisler E, et al. Outpatient versus hospitalization management for uncomplicated diverticulitis: a prospective, multicenter randomized clinical trial (DIVER Trial). Ann Surg. 2014;259(1):38–44. — PubMed PMID: 23732265
- Mora-López L, Ruiz-Edo N, Estrada-Ferrer O, et al. Efficacy and Safety of Nonantibiotic Outpatient Treatment in Mild Acute Diverticulitis (DINAMO-study): A Multicentre, Randomised, Open-label, Noninferiority Trial. Ann Surg. 2021;274(5):e435–e442. — PubMed PMID: 34183510
- Vennix S, Musters GD, Mulder IM, et al. Laparoscopic peritoneal lavage or sigmoidectomy for perforated diverticulitis with purulent peritonitis: a multicentre, parallel-group, randomised, open-label trial. Lancet. 2015;386(10000):1269–1277. — PubMed PMID: 26209030
- Peery AF, Shaukat A, Strate LL. AGA Clinical Practice Update on Medical Management of Colonic Diverticulitis: Expert Review. Gastroenterology. 2021;160(3):906–911.e1. — PubMed PMID: 33279517
- Klarenbeek BR, de Korte N, van der Peet DL, Cuesta MA. Review of current classifications for diverticular disease and a translation into clinical practice. Int J Colorectal Dis. 2012;27(2):207–214. — PubMed PMID: 21928041
- Shahedi K, Fuller G, Bolus R, et al. Long-term risk of acute diverticulitis among patients with incidental diverticulosis found during colonoscopy. Clin Gastroenterol Hepatol. 2013;11(12):1609–1613. — PubMed PMID: 23856358
PubMed Topic Searches
Curated PubMed topic searches of peer-reviewed literature on Diverticulitis. Each link opens a live PubMed query so you always see the most current studies.
- PubMed: Diverticulitis treatment guidelines
- PubMed: Antibiotic therapy in diverticulitis
- PubMed: Dietary fiber and diverticular disease
- PubMed: CT imaging of diverticulitis
- PubMed: Surgery for complicated diverticulitis
- PubMed: Recurrent diverticulitis
- PubMed: Colonoscopy after diverticulitis
- PubMed: Sigmoid diverticulitis
- PubMed: Perforation and abscess
- PubMed: Mesalamine and rifaximin trials
- PubMed: Epidemiology of diverticular disease
- PubMed: Outpatient management
Connections
- Gastroenterology
- Inflammatory Bowel Disease
- Irritable Bowel Syndrome
- Crohn's Disease
- Small Intestinal Bacterial Overgrowth
- Magnesium
- Gut Healing Protocol
- Lentils
- Turmeric
- Resistant Starches and Gut Microbiome
- Probiotics
- Constipation
- Abdominal Pain
- Sepsis
- Cancer
- Gallbladder Disease
- Ulcerative Colitis
- Peptic Ulcer Disease
- Surgery Decisions Resection J Pouch Ostomy
- Colorectal Cancer
- Hemorrhoids
- Polycystic Kidney Disease