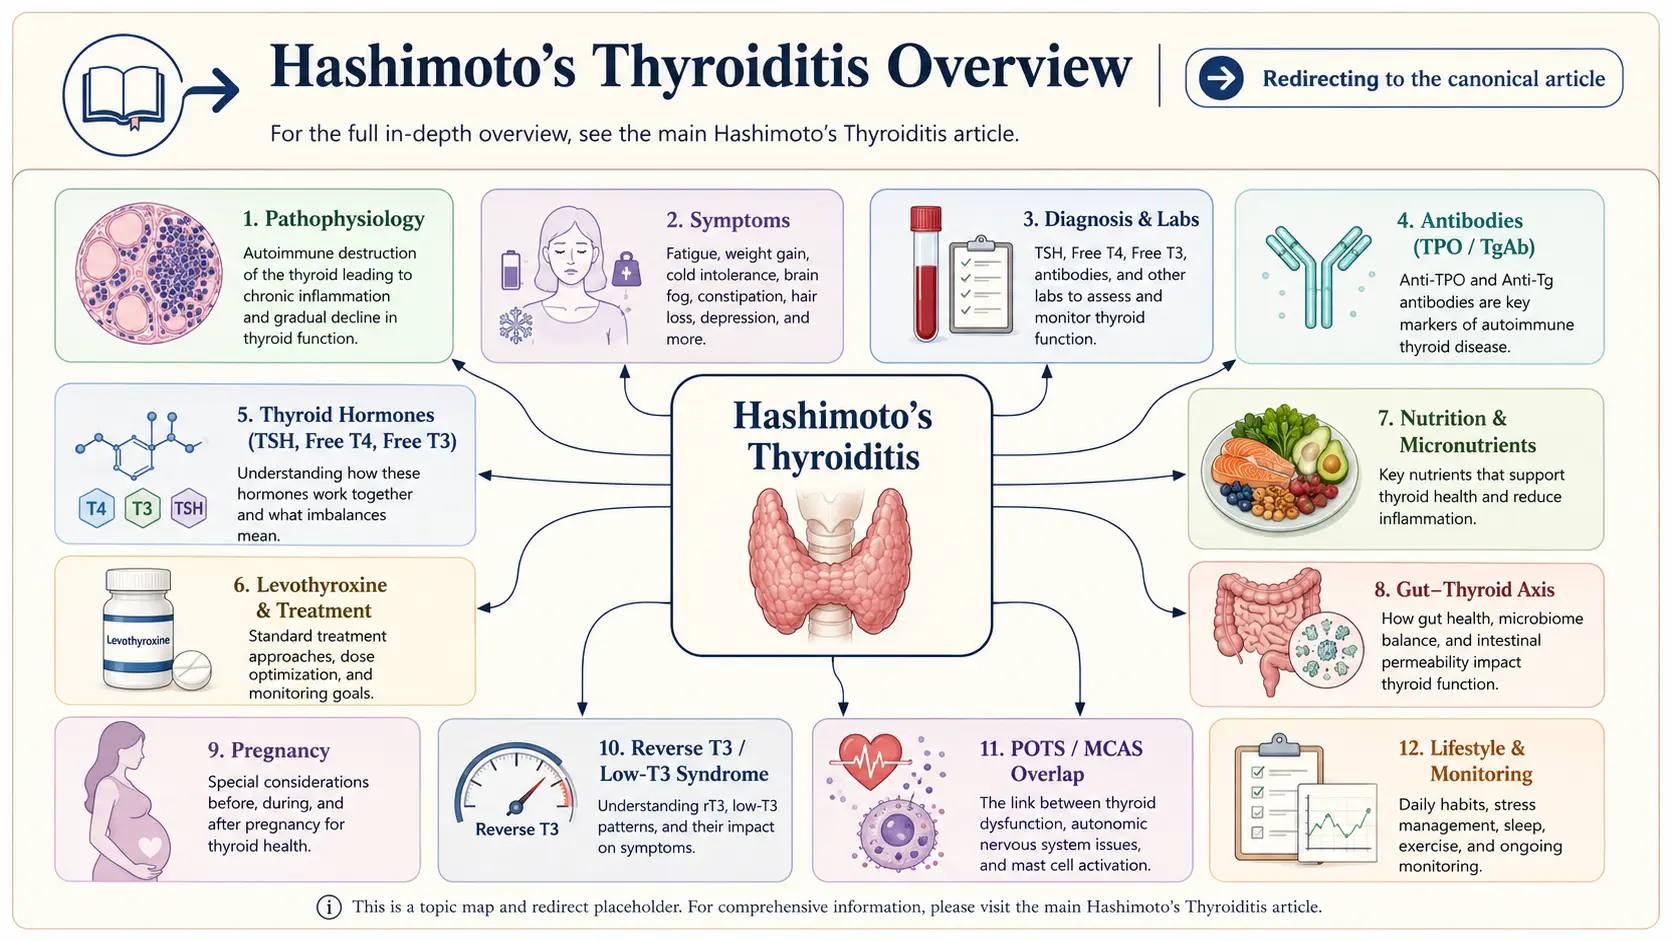
Hashimoto's Thyroiditis: The Most Common Cause of Hypothyroidism in the Developed World
Deep-Dive Articles
Hashimoto’s is almost never just “take your Synthroid and move on.” The eight guides below tackle the pieces your endocrinologist may never explain — what TPO and TgAb antibodies actually mean, why the “normal” thyroid-stimulating hormone (TSH) range hides so many undertreated patients, the levothyroxine-vs-NDT-vs-T3 debate, the AIP diet and gluten connection, mineral cofactors for conversion, reverse T3 and low-T3 syndrome, pregnancy dose changes, and the Hashimoto’s / postural orthostatic tachycardia syndrome (POTS) / mast cell activation syndrome (MCAS) overlap. Start wherever you are.
TPO & TgAb Antibodies Explained
What anti-thyroid peroxidase and anti-thyroglobulin antibodies actually measure, what a “positive with normal thyroid-stimulating hormone” result means, why antibody levels rise and fall, and the evidence on bringing them down.
Read the deep dive →Thyroid-Stimulating Hormone / T4 / T3 Optimal Ranges
The lab “normal” range is 0.5–4.5 — the optimal range is narrower. How to read a full thyroid panel (thyroid-stimulating hormone, free T4, free T3, reverse T3, TPO, TgAb), and the case for treating to free T4 and free T3 targets, not just thyroid-stimulating hormone.
Read the deep dive →Levothyroxine vs NDT vs T3
Levothyroxine / Tirosint vs. natural desiccated thyroid (Armour, NP Thyroid, WP Thyroid) vs. combination T4+T3 (Cytomel / liothyronine). Why T4-only fails some patients, DIO2 polymorphism, and how to advocate for alternatives.
Read the deep dive →AIP Diet & Gluten Elimination
The Autoimmune Protocol, the gluten-thyroid molecular-mimicry evidence, Hakaru Hashimoto’s original observation, and the 30- and 90-day trials that shift antibody levels — what the evidence supports and what it doesn’t.
Read the deep dive →Selenium, Zinc, Iron & Iodine
Selenium 200 mcg/day — the trial evidence for antibody reduction. Zinc for conversion. Iron (ferritin > 70) for symptoms. Iodine — when to supplement, when to strictly avoid, and why Hashimoto’s changes the usual answer.
Read the deep dive →Reverse T3 & Low-T3 Syndrome
Why some Hashi patients feel awful on “optimized” T4 — conversion failure, stress/cortisol interference, the rT3/fT3 ratio, nonthyroidal illness, and the protocols clinicians use to restore T3.
Read the deep dive →Pregnancy & Hashimoto’s
The trimester-specific thyroid-stimulating hormone targets (<2.5 first trimester), the 25–30% dose increase starting week 4–8, miscarriage risk with antibodies, and postpartum thyroiditis — the triphasic pattern clinicians miss.
Read the deep dive →Hashi / Postural Orthostatic Tachycardia Syndrome / Mast Cell Activation Syndrome Overlap
Why Hashimoto’s patients disproportionately have postural orthostatic tachycardia syndrome, mast cell activation syndrome, celiac, and endometriosis. The shared autoimmune/dysautonomia/mast-cell wiring, and a workup order that saves years.
Read the deep dive →Gut-Thyroid Axis & Intestinal Permeability
Leaky gut, small intestinal bacterial overgrowth (SIBO), H. pylori, and how gut health drives thyroid autoimmunity.
Read the deep dive →Hashimoto’s thyroiditis (also called Hashimoto’s disease or chronic autoimmune thyroiditis) is an autoimmune condition in which the immune system attacks the thyroid gland, progressively destroying thyroid tissue and impairing hormone production. It is the most common cause of hypothyroidism in iodine-replete populations, affecting roughly 5% of women and 1% of men in the United States. Diagnosis hinges on the combination of thyroid dysfunction and circulating antibodies against thyroid peroxidase (TPO) and/or thyroglobulin.
Interactive Visualization How Your Thyroid Is Controlled — run the feedback loop Watch thyroid-stimulating hormone drive the thyroid, T4 convert to T3, and the loop feed back — then switch on Hashimoto's, Graves', or iodine deficiency. Launch → Interactive Visualization Autoimmunity: When Defence Turns on You Watch immune cells lose the ability to tell self from invader and attack the body's own tissue — then see how tolerance normally prevents it and why it breaks down. Launch →Table of Contents
What Hashimoto’s Is
The immune system generates antibodies (anti-TPO, anti-thyroglobulin) and cytotoxic T-cell infiltration that progressively destroy thyroid follicular cells. The gland initially enlarges (goiter), then shrinks over years to decades. Many patients have circulating antibodies for years before clinical hypothyroidism develops. Genetic predisposition is real — HLA-DR3, HLA-DR5, CTLA-4, and PTPN22 variants are associated — but environmental triggers clearly matter, since the condition has become much more common in recent decades.
Symptoms of Thyroid Failure
- Fatigue, particularly mid-afternoon energy crash
- Cold intolerance, perpetually cold hands and feet
- Weight gain, difficulty losing weight
- Dry skin, brittle hair, hair loss including the lateral eyebrow
- Constipation
- Depression, brain fog, slowed thinking
- Puffiness (myxedema), particularly periorbital
- Menstrual irregularities, heavy periods
- Muscle aches, weakness, slow reflex relaxation
- Elevated cholesterol
- Bradycardia
- Hoarseness
Diagnosis — Labs That Matter
- Thyroid-stimulating hormone — elevated in overt hypothyroidism. The reference range top (often 4.5 mIU/L) is debated; many functional practitioners target <2.5.
- Free T4, free T3 — complete picture of hormone availability.
- Reverse T3 — sometimes elevated in illness and chronic stress, blocking T3 action.
- Anti-TPO antibodies — positive in roughly 90% of Hashimoto’s.
- Anti-thyroglobulin antibodies — positive in roughly 50%.
- Thyroid ultrasound — characteristic heterogeneous hypoechoic pattern with increased vascularity early, atrophy late.
Standard Pharmaceutical Treatment
- Levothyroxine (T4) — standard first-line. Taken on empty stomach, separate from coffee, calcium, iron, and proton pump inhibitors (PPIs) by at least 30–60 minutes. Dose titrated to thyroid-stimulating hormone target, typically 0.5–2.5.
- Liothyronine (T3) or combined T4/T3 therapy for patients who remain symptomatic on levothyroxine alone despite normal thyroid-stimulating hormone, particularly those with impaired T4-to-T3 conversion (DIO2 polymorphism).
- Desiccated thyroid extract (NDT, Armour, Nature-Throid) — contains both T4 and T3 in a fixed ratio from porcine thyroid. Popular in integrative practice. Not preferred by endocrinology guidelines but valued by many patients.
Low-Dose Naltrexone and Immune Modulation
Case series and clinical experience suggest low-dose naltrexone at 1.5–4.5 mg nightly can reduce TPO antibodies and improve symptoms in some Hashimoto’s patients. Evidence is early and not from large randomized controlled trials (RCTs), but safety is favorable and the intervention is inexpensive.
Root-Cause and Functional Approaches
Triggers and contributors frequently addressed in functional and naturopathic approaches:
- Gluten sensitivity. Celiac disease co-occurs in up to 5% of Hashimoto’s; functional practitioners suggest a trial of gluten elimination even without biopsy-confirmed celiac.
- Selenium. 200 µg/day of selenium lowered TPO antibodies in a meta-analysis of randomized trials (Wichman 2016), but a 2017 meta-analysis found no improvement in quality of life in untreated patients (Winther 2017).
- Vitamin D. Deficiency is associated with worse disease activity; replete to >40 ng/mL.
- Iron and ferritin. Low ferritin impairs thyroid hormone synthesis and conversion; target ferritin >70 ng/mL.
- Gut health. Intestinal permeability and dysbiosis correlate with antibody levels in some studies.
- Environmental toxins. Halogens (fluoride, bromide), heavy metals, and endocrine disruptors can impair thyroid function.
- Stress and cortisol. Chronic stress impairs T4-to-T3 conversion and worsens symptoms.
- Epstein-Barr virus (EBV) reactivation has been implicated as a trigger in some cases.
- Iodine. Controversial in Hashimoto’s — both deficiency and excess can worsen disease. Avoid high-dose iodine supplementation without clinician guidance.
Pregnancy and Fertility Considerations
Adequate thyroid hormone is essential for fertility, pregnancy, and fetal neurodevelopment. Women with Hashimoto’s attempting conception should target thyroid-stimulating hormone <2.5 mIU/L before pregnancy and in first trimester. Levothyroxine dose typically needs to be increased by 25–30% immediately upon confirming pregnancy, with frequent monitoring thereafter.
Connections
- Endocrinology
- Autoimmunity: When Defence Turns on You — interactive animation
- How Your Thyroid Is Controlled — interactive animation
- Levothyroxine vs NDT vs T3
- AIP and Gluten Elimination
- Gut-Thyroid Axis and Intestinal Permeability
- Thyroid-Stimulating Hormone, T4, and T3 Optimal Ranges
- Selenium, Zinc, Iron, and Iodine
- TPO and TgAb Antibodies
- Reverse T3 and Low T3 Syndrome
- Pregnancy and Hashimoto's
- Hashimoto, Postural Orthostatic Tachycardia Syndrome, and Mast Cell Activation Syndrome Overlap
- Selenium
- Iron
- Iodine
- Thyroid Disorders
- Graves' Disease
- Celiac Disease
- Postural Orthostatic Tachycardia Syndrome
- Vitamin D3
- Hair Loss
- Postpartum Depression
- Theodor Kocher and the thyroid — the commonest cause of hypothyroidism in iodine-sufficient countries, with the levothyroxine practicalities and the T4/T3 debate given from both sides
- All Conditions — the complete index of diseases covered on this site.
- Dr. Bryan Ardis: Nicotine and Hashimoto’s
- Thyroid Panel
Key Research Papers
- Caturegli P, De Remigis A, Rose NR (2014). Hashimoto thyroiditis: clinical and diagnostic criteria. Autoimmunity Reviews — PubMed PMID: 24434360
- Hollowell JG, Staehling NW, Flanders WD, et al. (2002). Serum TSH, T(4), and thyroid antibodies in the United States population (1988 to 1994): National Health and Nutrition Examination Survey (NHANES III). The Journal of Clinical Endocrinology and Metabolism — PubMed PMID: 11836274
- Jonklaas J, Bianco AC, Bauer AJ, et al. (2014). Guidelines for the treatment of hypothyroidism: prepared by the american thyroid association task force on thyroid hormone replacement. Thyroid — PubMed PMID: 25266247
- Wichman J, Winther KH, Bonnema SJ, et al. (2016). Selenium Supplementation Significantly Reduces Thyroid Autoantibody Levels in Patients with Chronic Autoimmune Thyroiditis: A Systematic Review and Meta-Analysis. Thyroid — PubMed PMID: 27702392
- Winther KH, Wichman JE, Bonnema SJ, et al. (2017). Insufficient documentation for clinical efficacy of selenium supplementation in chronic autoimmune thyroiditis, based on a systematic review and meta-analysis. Endocrine — PubMed PMID: 27683225
- Roy A, Laszkowska M, Sundström J, et al. (2016). Prevalence of Celiac Disease in Patients with Autoimmune Thyroid Disease: A Meta-Analysis. Thyroid — PubMed PMID: 27256300
- Alexander EK, Pearce EN, Brent GA, et al. (2017). 2017 Guidelines of the American Thyroid Association for the Diagnosis and Management of Thyroid Disease During Pregnancy and the Postpartum. Thyroid — PubMed PMID: 28056690
- Wang J, Lv S, Chen G, et al. (2015). Meta-analysis of the association between vitamin D and autoimmune thyroid disease. Nutrients — PubMed PMID: 25854833
PubMed Topic Searches
The following PubMed topic searches aggregate the current peer-reviewed literature. Each link opens a live PubMed query — results update as new studies are indexed.
- PubMed: Hashimoto thyroiditis
- PubMed: Autoimmune hypothyroidism
- PubMed: Anti-TPO antibodies
- PubMed: Thyroglobulin antibodies
- PubMed: Levothyroxine therapy
- PubMed: Subclinical hypothyroidism
- PubMed: Selenium Hashimoto
- PubMed: Gluten Hashimoto autoimmunity
- PubMed: Low dose naltrexone autoimmune
- PubMed: Pregnancy hypothyroidism
- PubMed: Vitamin D hypothyroidism
- PubMed: Thyroid lymphocytic infiltration
Featured Videos