⚠ Evidence warning: Clinical trials or other evidence do not support the claims that preemptive levothyroxine is a reasonable question for women with TPO antibodies, recurrent miscarriage or a rising thyroid-stimulating hormone, that two extra levothyroxine pills a week are safe and reversible, and that two Brazil nuts a day provide a reasonable food-based selenium dose. This page keeps it as a report of what people, websites or other media say.
Pregnancy and Hashimoto's Thyroiditis
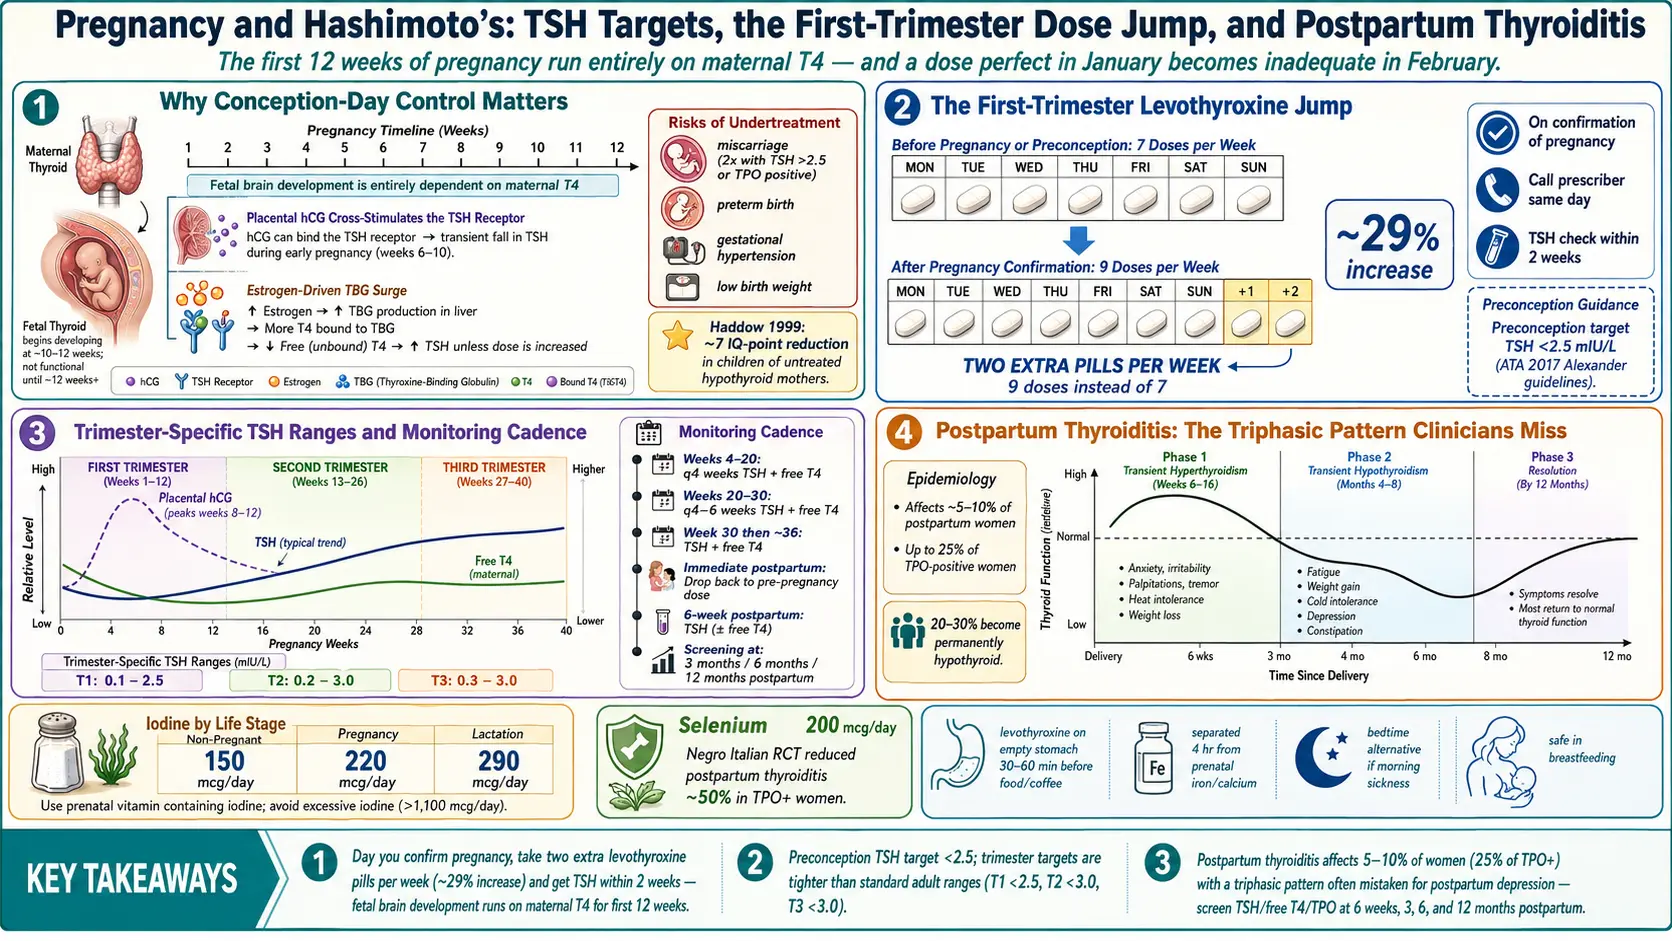
Table of Contents
- Why Hashimoto's Matters Before You Conceive
- The Preconception Thyroid-Stimulating Hormone Target: Under 2.5
- TPO Antibodies and Euthyroid Infertility
- The First-Trimester Levothyroxine Jump
- Trimester-Specific Thyroid-Stimulating Hormone Ranges
- Monitoring Cadence Through Pregnancy
- Postpartum Thyroiditis — The Missed Diagnosis
- Breastfeeding on Thyroid Medication
- Iodine and Selenium in Pregnancy
- Practical Tactics — Pills, Prenatals, Travel
- Thyroid Care Between the Obstetrician and the Endocrinologist
- Key Research Papers
- Connections
- Featured Videos
Why Hashimoto's Matters Before You Conceive
If you have Hashimoto's thyroiditis and you are thinking about getting pregnant, the first thing to know is this: the single biggest variable that affects your pregnancy outcome is how well your thyroid is controlled at the moment of conception. Not in the second trimester. Not when you find out. At conception.
That is because the first ten to twelve weeks of pregnancy, the fetus cannot make any thyroid hormone of its own. Every molecule of T4 that builds the early fetal brain, skeleton, and placenta comes from you. If your thyroid is struggling — even in ways that feel mild or invisible — the fetus feels it too.
The risks of untreated or undertreated hypothyroidism in pregnancy are real and well documented:
- Miscarriage. Women with thyroid-stimulating hormone above 2.5 mIU/L or positive thyroid peroxidase (TPO) antibodies have roughly double the miscarriage rate of euthyroid, antibody-negative women.
- Preterm birth. Rates climb measurably when maternal thyroid-stimulating hormone stays elevated, especially above 4.0 mIU/L.
- Gestational hypertension and preeclampsia. Undertreated hypothyroidism is an independent risk factor.
- Placental abruption and low birth weight. Both show up more often in inadequately treated pregnancies.
- Reduced child IQ. The 1999 Haddow study found children of untreated hypothyroid mothers scored roughly 7 IQ points lower at ages seven to nine than controls. That finding changed how obstetrics treats this disease.
None of this is said to frighten you. It is said because the fix is cheap, safe, and extraordinarily effective. A generic pill that costs pennies a day, titrated correctly, brings your risk profile back to that of a woman without thyroid disease. The catch is that "titrated correctly" requires more vigilance in pregnancy than at any other time in your life.
The largest treatment trial since then (Casey and colleagues, 2017) screened pregnant women before 20 weeks and randomly assigned 677 women with subclinical hypothyroidism (thyroid-stimulating hormone of 4.00 mU/L or more with a normal free T4) to levothyroxine or placebo, starting at a mean of 16.7 weeks. The children's median IQ at age 5 was 97 with levothyroxine and 94 with placebo — not a significant difference — and no other neurocognitive or pregnancy outcome differed. That trial treated mild thyroid changes found in mid-pregnancy; it was not a trial of treating known Hashimoto's from before conception.
The Preconception Thyroid-Stimulating Hormone Target: Under 2.5
The American Thyroid Association's 2017 guidelines (Alexander et al.) recommend a preconception thyroid-stimulating hormone of less than 2.5 mIU/L in women with known hypothyroidism who are trying to conceive. Some endocrinologists aim even lower — 1.0 to 2.0 — especially in women with a history of miscarriage or infertility.
Why this number matters: a "normal" lab range of roughly 0.5 to 4.5 mIU/L was never designed for pregnancy. It reflects the middle 95% of non-pregnant adults, including many with undiagnosed subclinical disease. In pregnancy, the normal range shifts downward because the placenta produces human chorionic gonadotropin (hCG), which cross-stimulates the thyroid-stimulating hormone receptor and pushes your own thyroid-stimulating hormone lower. A thyroid-stimulating hormone of 3.8 before pregnancy may look reassuring on a generic report, but it signals a gland that will struggle to meet first-trimester demand.
For a woman planning pregnancy whose thyroid-stimulating hormone sits between 2.5 and 4.5, the open question is whether levothyroxine is started or raised before conception rather than after. Waiting until a positive pregnancy test means the first four to six weeks of fetal development pass on the old dose.
TPO Antibodies and Euthyroid Infertility
A second, more subtle issue: you can have TPO or thyroglobulin (TgAb) antibodies without being hypothyroid yet. Your thyroid-stimulating hormone sits in the normal range, your free T4 looks fine, and a standard workup pronounces your thyroid healthy. But those antibodies are still associated with:
- Lower fertility rates, particularly in women over 35.
- Higher miscarriage rates, even when thyroid-stimulating hormone stays below 2.5.
- Reduced response to in vitro fertilisation (IVF) stimulation protocols.
- Higher risk of progressing to overt hypothyroidism during pregnancy, as the placenta's thyroid demands outstrip a weakened gland's reserve.
The Negro 2006 trial (JCEM) is the landmark study here. In euthyroid, TPO-positive pregnant women, a small dose of levothyroxine cut the miscarriage rate from 13.8% to 3.5% and the preterm-birth rate from 22.4% to 7.0%. Larger placebo-controlled trials did not confirm this. The UK TABLET trial (2019) gave 50 µg of levothyroxine a day or placebo, from before conception, to 952 antibody-positive women with normal thyroid tests and a history of miscarriage or infertility: 37.4% of the levothyroxine group and 37.9% of the placebo group had a live birth, with no difference in pregnancy loss or preterm birth.
The Dutch–Belgian–Danish T4LIFE trial (2022) studied the recurrent-miscarriage group directly: 187 antibody-positive women with normal thyroid tests and two or more pregnancy losses took levothyroxine (0.5 to 1.0 µg per kg of body weight a day, set by their thyroid-stimulating hormone before conception) or placebo from before conception to the end of pregnancy. Live births were 50% with levothyroxine and 48% with placebo (risk ratio 1.03) — no difference. The trial stopped early, at 187 of a planned 240 women, because recruitment was slow, and its authors wrote that their findings do not support routine levothyroxine for antibody-positive women with recurrent pregnancy loss and normal thyroid function. Together, the two trials do not show a benefit of levothyroxine for antibody-positive women whose thyroid tests are normal.
But for a woman with TPO antibodies, a history of recurrent miscarriage, or a thyroid-stimulating hormone drifting upward quarter by quarter, preemptive treatment is an entirely reasonable question for her endocrinologist.
See the TPO and TgAb article for a deeper dive on what these antibodies mean and how they change over time.
The First-Trimester Levothyroxine Jump
Here is the single most important practical fact on this page: in a woman already taking levothyroxine, the dose needed usually rises by about 25–30% or more once pregnancy begins, and the rise starts in the first weeks.
The reason is a surge in thyroid-binding globulin (TBG) driven by rising estrogen. TBG is the taxi service that carries thyroid hormone through the bloodstream. When estrogen spikes, the liver makes more taxis, and more of your circulating T4 gets bound and becomes biologically unavailable. A gland that was comfortably meeting demand before pregnancy suddenly cannot keep up. Add the placenta's own hormonal appetite, and a dose that was perfect in January becomes inadequate in February.
A 2004 study that followed 19 women with hypothyroidism from before conception (Alexander and colleagues, New England Journal of Medicine) found that their levothyroxine requirement rose by an average of 47% during the first half of pregnancy, starting as early as the fifth week (median onset eight weeks) and levelling off by week 16; the higher dose was needed until delivery. The authors proposed that women with hypothyroidism raise their dose by about 30% as soon as pregnancy is confirmed, then have thyroid-stimulating hormone checked and the dose adjusted. Two extra doses a week (nine doses in place of seven) works out to roughly a 29% increase.
Because the need starts climbing around weeks five to eight, it usually comes before the first obstetrician (OB) appointment at eight or ten weeks. The two-extra-pills-per-week move is safe, reversible, and supported by 2017 ATA guidelines.
Trimester-Specific Thyroid-Stimulating Hormone Ranges
Pregnancy has its own reference intervals, and the American Thyroid Association (ATA) changed its numbers between its two pregnancy guidelines. Studies comparing the guidelines describe the change: the 2011 guideline used fixed upper limits of 2.5 mIU/L in the first trimester and 3.0 in the second and third, while the 2017 guideline asks for pregnancy- and trimester-specific ranges drawn from the local population, with an upper limit of about 4.0 mU/L in the first trimester where no such range exists (1 mU/L is the same as 1 mIU/L).
- 2011 ATA fixed limits: first trimester 0.1 to 2.5 mIU/L; second trimester 0.2 to 3.0 mIU/L; third trimester 0.3 to 3.0 mIU/L (some guidelines extend the third trimester to 3.5).
- 2017 ATA approach: the laboratory's own pregnancy-specific range first; where none exists, about 4.0 mU/L as the first-trimester upper limit.
- Local ranges differ: a study of 52,027 pregnant women in Shanghai found thyroid-stimulating hormone ranges of 0.03 to 3.52 mU/L in the first trimester and 0.39 to 3.67 mU/L in the third. Against that local range, the 2011 limits would have over-diagnosed about 7.0% of first-trimester women, and the 2017 limits would have missed about 1.2%.
- Which limit is used changes the count: in 896 pregnant women in Beijing, subclinical hypothyroidism was found in 5.92% with the 4.0 mU/L limit and in 20.87% with the older 2.5 mU/L limit.
A report printed with a standard adult range (0.5 to 4.5 or similar) does not flag a first-trimester value such as 3.1, although that value is above the old 2011 limit of 2.5 and below the 2017 fallback of 4.0. Which limit the laboratory or clinic uses decides whether the number counts as raised and whether a dose change is considered.
On the other end, a first-trimester thyroid-stimulating hormone that drops to 0.05 or even becomes undetectable is usually not hyperthyroidism — it is the normal hCG-driven dip. Free T4 and clinical symptoms (rapid heart rate, tremor, heat intolerance) are better guides than thyroid-stimulating hormone alone in early pregnancy.
Monitoring Cadence Through Pregnancy
For any pregnancy involving Hashimoto's or known hypothyroidism:
- Weeks 4–20 (first half): thyroid-stimulating hormone and free T4 every four weeks. This is the window where requirements climb fastest and most dose adjustments happen.
- Weeks 20–30: thyroid-stimulating hormone and free T4 every four to six weeks. Dose needs usually plateau.
- Weeks 30–delivery: at least once more around week 30. Some OBs check again near 36 weeks.
- Immediately postpartum: the dose usually returns to the pre-pregnancy level after delivery, with a thyroid-stimulating hormone check at about six weeks postpartum.
- 6 weeks, 3 months, 6 months, 12 months postpartum: screen for postpartum thyroiditis (see below). Many endocrinologists miss this.
Four-weekly labs in the first half of pregnancy are the schedule the guidelines describe, not overkill.
Postpartum Thyroiditis — The Missed Diagnosis
This is the chapter of the Hashimoto's story that most new mothers never hear about. Roughly 5 to 10% of all postpartum women — and up to 25% of those with pre-existing TPO antibodies — develop postpartum thyroiditis in the year after delivery.
The classic pattern is three phases:
- Transient hyperthyroidism (weeks 6 to 16 postpartum). The inflamed gland leaks stored hormone. You feel anxious, wired, heat-intolerant. Heart pounds. You lose weight you had not expected to lose. It is often blamed on new-parent stress or postpartum anxiety.
- Transient hypothyroidism (months 4 to 8 postpartum). Hormone stores deplete. Exhaustion, cold intolerance, constipation, weight gain, brain fog, hair falling out in the shower, low milk supply, mood flattening into what looks exactly like postpartum depression — because the symptoms are identical.
- Resolution (by 12 months postpartum in most women). Thyroid function returns to baseline.
Not every woman moves through all three phases. Some only get the hyper phase. Some only get the hypo phase. Some stay hypothyroid permanently — an estimated 20 to 30% of women who have postpartum thyroiditis remain hypothyroid long-term or relapse into overt Hashimoto's within five years.
The practical point: postpartum fatigue, mood change, hair loss, or a milk-supply problem that lasts beyond a few weeks can come from the thyroid, and the symptoms overlap with ordinary new-parent exhaustion; a thyroid-stimulating hormone, free T4, and TPO antibody test is what tells them apart.
A 2022 review of thyroid disorders after birth (Peng and Pearce) states that routine thyroid testing after birth is not recommended for women without symptoms, and that testing at 6 to 12 weeks after birth is to be considered for higher-risk women: those with an earlier episode of postpartum thyroiditis, Graves' disease, Hashimoto's thyroiditis on thyroid hormone, known thyroid peroxidase antibodies, type 1 diabetes, another autoimmune disease, or chronic hepatitis C. The same review lists postpartum depression and difficulty breastfeeding as reasons to check thyroid-stimulating hormone, and describes periodic thyroid testing after recovery from postpartum thyroiditis because of the high lifetime risk of permanent hypothyroidism. A 2019 review (Nguyen and Mestman) puts the prevalence of postpartum thyroiditis at about 5% in the first year after birth.
Thyroid antibodies and postpartum depression are a separate question. A 2023 Rotterdam study, which measured thyroid tests at 9 to 17 weeks of pregnancy and combined its cohort with three earlier studies in a meta-analysis, found no significant link between thyroid peroxidase antibodies, thyroid-stimulating hormone, or free T4 and postpartum depression (antibodies: odds ratio 0.79, 95% CI 0.47 to 1.33). Its authors wrote that antibody-positive women warrant monitoring for postpartum thyroiditis, but that the findings do not support routine screening for postpartum depression on that basis.
Breastfeeding on Thyroid Medication
Levothyroxine is entirely safe in breastfeeding. The amount that crosses into breast milk is vanishingly small — smaller than the variation a nursing infant experiences from their own developing thyroid. There is no need to pump-and-dump, time feeds around doses, or worry about infant exposure.
The same is true for desiccated thyroid extracts (NDT) and liothyronine (T3), though these are less commonly used in pregnancy and postpartum, so there is less experience with them there. See the levothyroxine versus NDT versus T3 article for the formulation comparison.
What can disrupt breastfeeding is undertreated thyroid disease. Low free T4 reduces prolactin response and milk supply. When milk does not come in, or supply drops around three months postpartum, thyroid levels are one cause to rule out alongside pumping schedule or latch; the 2022 postpartum review lists difficulty breastfeeding as a reason to check thyroid-stimulating hormone.
Iodine and Selenium in Pregnancy
Iodine requirements rise sharply in pregnancy and lactation. The recommended daily intake goes from 150 mcg in non-pregnant adults to 220 mcg in pregnancy and 290 mcg during breastfeeding. Most U.S. prenatal vitamins now contain 150 mcg of iodine, which together with dietary iodine from dairy, eggs, and iodized salt usually covers the need.
Here is the trap: more is not better. In Hashimoto's specifically, excess iodine can accelerate autoimmune thyroid destruction and push a compensated gland into frank hypothyroidism. Kelp tablets, iodine-heavy seaweed, high-dose iodine supplements (10,000 mcg and up), and povidone-iodine exposures can all trigger flares. Studies from iodine-sufficient countries show a U-shaped relationship: too little is bad, too much is also bad.
What these findings mean in a Hashimoto's pregnancy:
- Not every prenatal vitamin contains iodine; the label states whether it has the usual 150 mcg.
- An ordinary diet — a few eggs a week, some dairy, the occasional seaweed salad — supplies iodine without aiming for high-iodine foods.
- Kelp supplements, iodine tablets, and megadose iodine products are the high-dose sources linked above to flares in Hashimoto's; in pregnancy they are used only when a clinician prescribes them.
- Vegan and dairy-free diets leave out dairy and eggs, two of the main dietary iodine sources named above, so iodine intake on these diets is harder to judge.
Selenium is the second key micronutrient. Selenium supplementation (200 mcg per day as selenomethionine) lowers TPO antibody titers and, in one Italian trial of 151 TPO-positive pregnant women, selenomethionine 200 mcg a day during and after pregnancy lowered postpartum thyroid dysfunction from 48.6% to 28.6% and permanent hypothyroidism from 20.3% to 11.7% compared with placebo. Brazil nuts are a food source of selenium. Two Brazil nuts a day provide a reasonable food-based dose. See the selenium, zinc, iron, and iodine article for the full micronutrient map.
Practical Tactics — Pills, Prenatals, Travel
Levothyroxine absorption is fragile. A perfect dose badly timed may be no dose at all. Pregnancy adds complications: prenatal vitamins with iron and calcium, morning sickness, changing sleep schedules.
Pill timing. Levothyroxine is absorbed best on an empty stomach, with plain water, at least 30 to 60 minutes before food, coffee, or any other supplement. The most reliable slot for most women is first thing on waking. When morning sickness makes that impossible, bedtime dosing — at least three hours after the last food — is the usual alternative. Switching back and forth between morning and night skews lab results, so one consistent slot gives the steadiest numbers.
Iron and calcium block absorption. Prenatal vitamins almost always contain both. A gap of at least four hours between levothyroxine and the prenatal is the spacing usually described. A common working schedule: levothyroxine at 6 a.m. on waking, prenatal with breakfast at 7:30 or later, iron supplement (if separate) at lunch or dinner.
Morning sickness. A pill vomited up within an hour of taking it has probably not been absorbed. Levothyroxine has a half-life of about seven days, so a single extra or missed dose barely moves steady-state levels.
Travel dose coverage. Because of the long half-life, levothyroxine tolerates a missed day without drama; a single missed pill makes little difference to levels. Missing three or more days in a row is where levels start to fall. Pills packed in a carry-on stay with the traveller when checked luggage is lost, and a spare week's supply and a written prescription for customs are common travel precautions. Time zone changes do not require a dose adjustment — the pill simply moves to the new local morning.
Refills and supply. Pharmacies sometimes switch between generic manufacturers, and different generics can have absorption differences of up to 12.5%. A thyroid-stimulating hormone check about four weeks after a manufacturer switch mid-pregnancy shows whether the dose is still right.
Thyroid Care Between the Obstetrician and the Endocrinologist
Obstetric care in the U.S. is often compressed, and thyroid management can fall between the obstetrician and the endocrinologist — each assuming the other is handling it. The points from this page that most often come up at appointments:
- Which first-trimester thyroid-stimulating hormone limit the clinic uses — the laboratory's own pregnancy range, the 2017 ATA fallback of about 4.0 mU/L, or the older 2011 figure of 2.5.
- That a standard adult lab range does not flag a value that is raised by a pregnancy limit.
- Free T4 measured alongside thyroid-stimulating hormone, rather than thyroid-stimulating hormone alone.
- Lab checks every four weeks in the first half of pregnancy, the schedule described above.
- Thyroid testing at 6 to 12 weeks after birth for women with Hashimoto's on treatment or known TPO antibodies, as described in the 2022 postpartum review.
Maternal-fetal medicine specialists and endocrinologists experienced with pregnancy are the clinicians who handle the harder cases.
Key Research Papers
Foundational and recent peer-reviewed publications on thyroid disease in pregnancy and the postpartum period — preconception planning, dose adjustment in trimester one, postpartum thyroiditis, and the antibody-and-fertility literature. Each citation links to the full text via DOI.
- Alexander EK, Pearce EN, Brent GA, et al. 2017 Guidelines of the American Thyroid Association for the Diagnosis and Management of Thyroid Disease During Pregnancy and the Postpartum. Thyroid. 2017;27(3):315–389. — doi:10.1089/thy.2016.0457
- Stagnaro-Green A, Abalovich M, Alexander E, et al. Guidelines of the American Thyroid Association for the Diagnosis and Management of Thyroid Disease During Pregnancy and Postpartum. Thyroid. 2011;21(10):1081–1125. — doi:10.1089/thy.2011.0087
- Negro R, Formoso G, Mangieri T, Pezzarossa A, Dazzi D, Hassan H. Levothyroxine Treatment in Euthyroid Pregnant Women with Autoimmune Thyroid Disease: Effects on Obstetrical Complications. Journal of Clinical Endocrinology & Metabolism. 2006;91(7):2587–2591. — doi:10.1210/jc.2005-1603
- Haddow JE, Palomaki GE, Allan WC, et al. Maternal Thyroid Deficiency During Pregnancy and Subsequent Neuropsychological Development of the Child. New England Journal of Medicine. 1999;341(8):549–555. — doi:10.1056/NEJM199908193410801
- Dhillon-Smith RK, Middleton LJ, Sunner KK, et al. Levothyroxine in Women with Thyroid Peroxidase Antibodies before Conception (TABLET Trial). New England Journal of Medicine. 2019;380(14):1316–1325. — doi:10.1056/NEJMoa1812537
- Negro R, Greco G, Mangieri T, Pezzarossa A, Dazzi D, Hassan H. The Influence of Selenium Supplementation on Postpartum Thyroid Status in Pregnant Women with Thyroid Peroxidase Autoantibodies. Journal of Clinical Endocrinology & Metabolism. 2007;92(4):1263–1268. — doi:10.1210/jc.2006-1821
- Negro R, Schwartz A, Gismondi R, Tinelli A, Mangieri T, Stagnaro-Green A. Universal Screening Versus Case Finding for Detection and Treatment of Thyroid Hormonal Dysfunction During Pregnancy. Journal of Clinical Endocrinology & Metabolism. 2010;95(4):1699–1707. — doi:10.1210/jc.2009-2009
- Mannisto T, Mendola P, Grewal J, Xie Y, Chen Z, Laughon SK. Thyroid Diseases and Adverse Pregnancy Outcomes in a Contemporary US Cohort. Journal of Clinical Endocrinology & Metabolism. 2013;98(7):2725–2733. — doi:10.1210/jc.2012-4233
- Casey BM, Thom EA, Peaceman AM, et al. Treatment of Subclinical Hypothyroidism or Hypothyroxinemia in Pregnancy. New England Journal of Medicine. 2017;376(9):815–825. — doi:10.1056/NEJMoa1606205
- Alexander EK, Marqusee E, Lawrence J, Jarolim P, Fischer GA, Larsen PR. Timing and Magnitude of Increases in Levothyroxine Requirements During Pregnancy in Women with Hypothyroidism. New England Journal of Medicine. 2004;351(3):241–249. — doi:10.1056/NEJMoa040079
- Hollowell JG, Staehling NW, Flanders WD, et al. Serum TSH, T4, and Thyroid Antibodies in the United States Population (NHANES III). Journal of Clinical Endocrinology & Metabolism. 2002;87(2):489–499. — doi:10.1210/jcem.87.2.8182
- van Dijk MM, Vissenberg R, Fliers E, et al. Levothyroxine in euthyroid thyroid peroxidase antibody positive women with recurrent pregnancy loss (T4LIFE trial): a multicentre, randomised, double-blind, placebo-controlled, phase 3 trial. Lancet Diabetes & Endocrinology. 2022;10(5):322–329. — doi:10.1016/S2213-8587(22)00045-6
- Peng CC, Pearce EN. An update on thyroid disorders in the postpartum period. Journal of Endocrinological Investigation. 2022;45(8):1497–1506. — doi:10.1007/s40618-022-01762-1
- Nguyen CT, Mestman JH. Postpartum Thyroiditis. Clinical Obstetrics and Gynecology. 2019;62(2):359–364. — doi:10.1097/GRF.0000000000000430
- Sileo F, Osinga JAJ, Visser WE, et al. Association of gestational thyroid function and thyroid peroxidase antibody positivity with postpartum depression: a prospective cohort study and systematic literature review with meta-analysis. European Journal of Endocrinology. 2023;189(2):S26–S36. — doi:10.1093/ejendo/lvad092
- Yang X, Meng Y, Zhang Y, et al. Thyroid function reference ranges during pregnancy in a large Chinese population and comparison with current guidelines. Chinese Medical Journal. 2019;132(5):505–511. — doi:10.1097/CM9.0000000000000051
- Du J, Lin L, Li Z, et al. [The influence of different thyroid stimulating hormone cut-offs to diagnose subclinical hypothyroidism during the first trimester of pregnancy]. Zhonghua Yi Xue Za Zhi. 2019;99(2):120–123. (Article in Chinese.) — doi:10.3760/cma.j.issn.0376-2491.2019.02.009
- Zimmermann MB, Boelaert K. Iodine Deficiency and Thyroid Disorders. Lancet Diabetes & Endocrinology. 2015;3(4):286–295. — doi:10.1016/S2213-8587(14)70225-6
PubMed Topic Searches
Live PubMed queries that update as new papers are indexed.
- PubMed: Hashimoto's in pregnancy
- PubMed: levothyroxine dose adjustment
- PubMed: subclinical hypothyroidism + miscarriage
- PubMed: TPO antibodies + infertility
- PubMed: postpartum thyroiditis
- PubMed: trimester-specific TSH
- PubMed: iodine + pregnancy + Hashimoto's
- PubMed: selenium + postpartum thyroiditis
- PubMed: levothyroxine + breastfeeding
Connections
- Endocrinology
- How Your Thyroid Is Controlled — interactive animation
- Hashimoto's Thyroiditis Overview
- Levothyroxine vs NDT vs T3
- Selenium, Zinc, Iron, and Iodine
- TPO and TgAb Antibodies
- Thyroid-Stimulating Hormone, T4, and T3 Optimal Ranges
- Reverse T3 and Low T3 Syndrome
- Hashimoto, Postural Orthostatic Tachycardia Syndrome, and Mast Cell Activation Syndrome Overlap
- AIP and Gluten Elimination
- Gut-Thyroid Axis and Intestinal Permeability
- Infertility
- Preeclampsia
- Gestational Diabetes
- Perimenopause
- Thyroid Disorders
- Selenium
- Iodine
- Iron
- Polycystic Ovary Syndrome
- Reproductive Medicine