⚠ Evidence warning: Clinical trials or other evidence do not support the claim that low-dose naltrexone has growing evidence in multiple autoimmune conditions. This page keeps it as a report of what people, websites or other media say.
AIP and Gluten Elimination for Hashimoto's
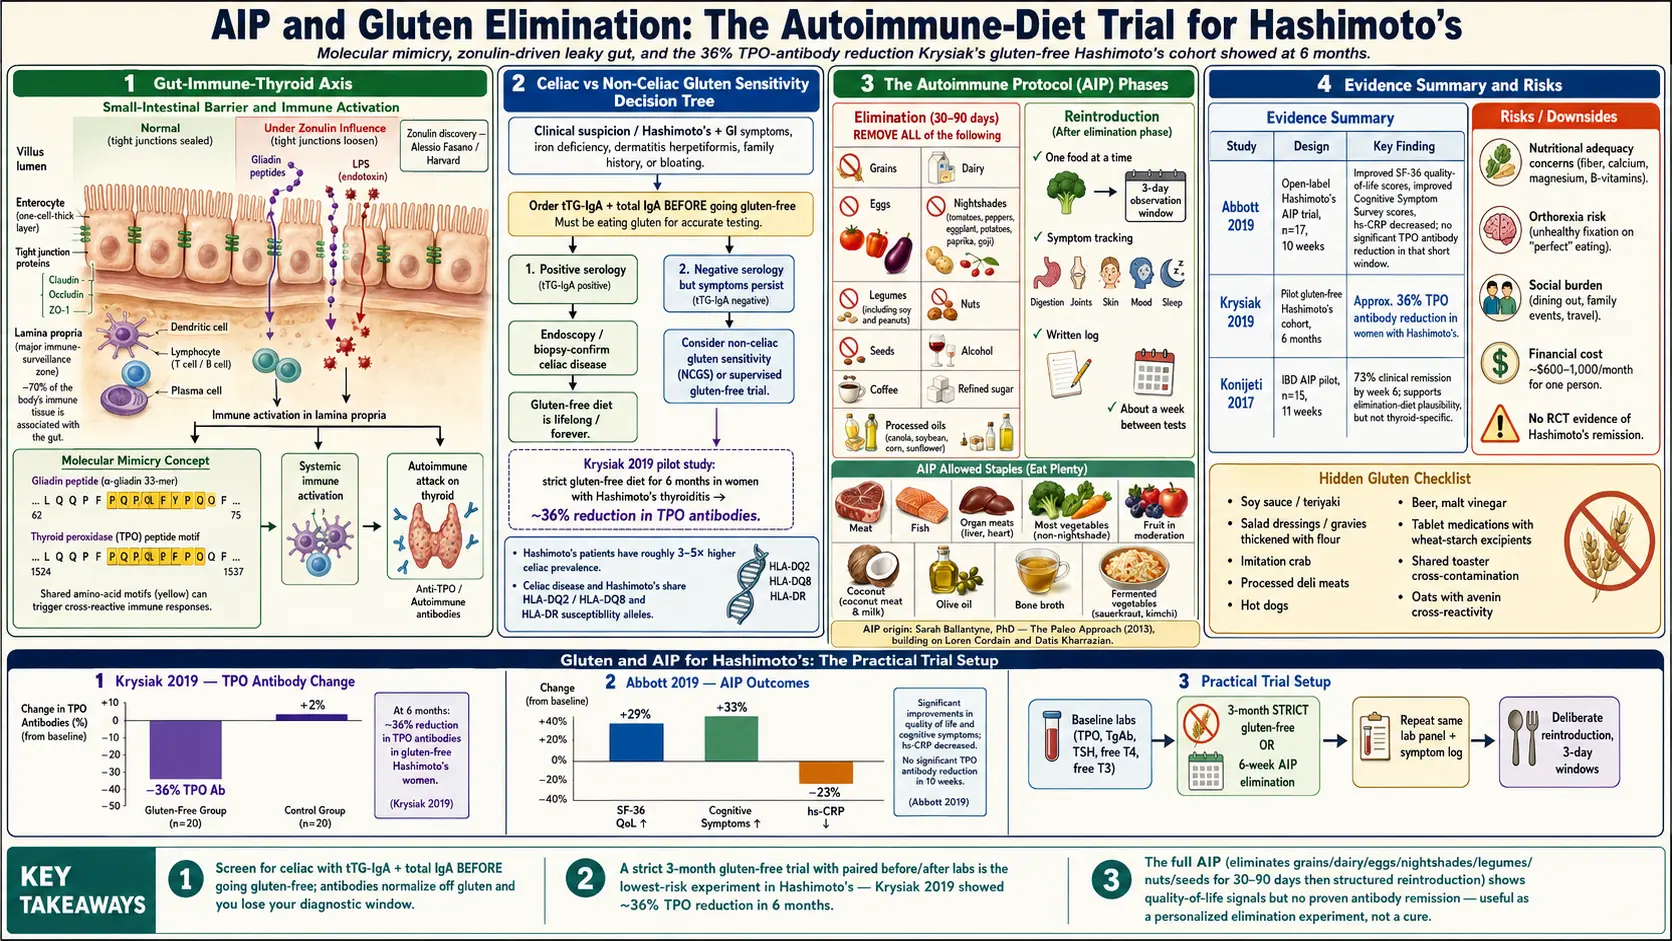
Table of Contents
- Why Diet Might Matter in Autoimmunity
- Gluten and Thyroid Molecular Mimicry
- Celiac Disease and Hashimoto's
- Non-Celiac Gluten Sensitivity and Hashimoto's
- How Gluten-Free Trials Are Structured
- Hidden Gluten Sources
- The Autoimmune Protocol (AIP)
- Who Created AIP
- Evidence for AIP in Hashimoto's
- Evidence for AIP in Inflammatory Bowel Disease
- Practical AIP Structure
- What AIP Foods Look Like
- What AIP Excludes
- Risks and Limits
- Safety Points During an AIP Trial
- Mediterranean as a Lower-Bar Alternative
- The Long-Term Plan When AIP Helps
- Other Hashimoto's Options When AIP Does Not Help
- Where AIP Hype Outruns Evidence
- Key Research Papers
- Connections
- Featured Videos
Why Diet Might Matter in Autoimmunity
The idea that food can drive an autoimmune disease of the thyroid sounds like a stretch — until you look at what the gut actually does. Your small-intestine lining is a single cell layer thick. On one side is the outside world (partly digested food, bacteria, viruses, fungal spores). On the other side is the largest concentration of immune tissue in your body: roughly 70% of your immune system patrols the gut. The barrier between those two worlds is held together by tight-junction proteins, and when those junctions loosen, food proteins and bacterial fragments can leak into circulation where the immune system is not used to seeing them.
This phenomenon has a scientific name — increased intestinal permeability, colloquially "leaky gut" — and a leading researcher behind it, Dr. Alessio Fasano of Harvard and Mass General. Fasano's lab discovered the human protein zonulin, which reversibly opens tight junctions. Elevated zonulin has now been documented in celiac disease, type 1 diabetes, multiple sclerosis, inflammatory bowel disease, and, in smaller studies, Hashimoto's thyroiditis. The hypothesis is not that leaky gut causes autoimmunity by itself but that it is one of three required conditions: a genetic predisposition, an environmental trigger (often a food protein or infection), and a permeable gut that lets the trigger reach immune tissue in a form the body reacts to.
The second piece of the puzzle is molecular mimicry. When the immune system is primed against a foreign protein, it can misread a similar-looking human protein as the same enemy. If a leaky gut keeps feeding the immune system food-derived peptides that happen to resemble thyroid tissue, antibodies against those peptides can spill over onto the thyroid gland itself. This is the theoretical bridge between what you eat and what your own antibodies attack.
Gluten and Thyroid Molecular Mimicry
Gluten is the protein complex in wheat, barley, and rye. Its most immune-reactive fragment is gliadin, a component that the human digestive tract does not fully break down — everyone leaves some intact gliadin peptides in the gut. Research published over the past two decades has shown that several gliadin sequences share short amino-acid motifs with thyroid peroxidase (TPO) and thyroglobulin, the two proteins that TPO and TgAb antibodies attack in Hashimoto's.
In laboratory experiments, antibodies raised against gliadin cross-react with thyroid tissue in vitro. That does not prove the same thing happens inside a living patient, but it gives the hypothesis biological teeth. Combined with an already-open gut barrier and a genetic susceptibility (HLA-DQ2 or HLA-DQ8 in celiac, and overlapping human leukocyte antigen (HLA) risk alleles in Hashimoto's), the mimicry argument is at least mechanistically plausible.
What this does not mean: that every Hashimoto's patient has an immune reaction to gluten. It means the mechanism exists and, in a subset of patients, probably matters.
Celiac Disease and Hashimoto's
The cleanest evidence for a wheat-thyroid connection is the epidemiology of celiac disease. Celiac is a full-blown autoimmune reaction to gluten that damages the small-intestine villi. The co-prevalence with Hashimoto's is striking: people with Hashimoto's have roughly a 3- to 5-fold higher risk of also having celiac, and vice versa. The association is bidirectional, and untreated celiac can worsen thyroid antibody titers until gluten is removed.
This is why most endocrinologists and functional-medicine practitioners now recommend that every newly diagnosed Hashimoto's patient be screened for celiac disease. A 2016 pooled analysis of 6,024 people with autoimmune thyroid disease found biopsy-confirmed celiac disease in 1.6% — about 1 in 62 — including 6.2% of children and 2.7% of adults, and its authors argue for celiac screening in people with autoimmune thyroid disease (Roy et al., 2016). The standard first-line test is tissue transglutaminase immunoglobulin A (IgA) (tTG-IgA), with a total immunoglobulin A level drawn at the same time to rule out immunoglobulin A deficiency (which would make tTG-IgA falsely negative). If tTG-IgA is positive, confirmation is by upper endoscopy with duodenal biopsy.
Testing comes before going gluten-free. Celiac blood tests and biopsy both need ongoing gluten in the diet to be accurate. Starting a gluten-free diet first can make them falsely negative within weeks, leaving the diagnosis uncertain.
If celiac is diagnosed, a strict lifelong gluten-free diet is the treatment for the celiac disease itself — not a trial. An Italian multicenter study (Sategna-Guidetti et al., 2001) compared 241 adults with newly diagnosed, untreated celiac disease with 212 people without it. Thyroid disease was 3 times more common in the celiac group; underactive thyroid (hypothyroidism) was found in 12.9% of the celiac patients versus 4.2% of the controls, and thyroid antibodies with normal thyroid function in 16.2% versus 3.8%. In most patients who kept strictly to a gluten-free diet for one year (confirmed by a healed gut lining on biopsy), mild (subclinical) hypothyroidism returned to normal. Among the patients with thyroid antibodies but normal thyroid function, 25% shifted toward mildly overactive or mildly underactive thyroid function a year later, and in these people the diet had been followed poorly. Some people recover thyroid function enough to reduce or discontinue levothyroxine; dose changes are judged by repeat thyroid-stimulating hormone and free T4 tests.
Non-Celiac Gluten Sensitivity and Hashimoto's
This is the murkier category and the one most Hashimoto's patients actually live in. Non-celiac gluten sensitivity (NCGS) describes people who test negative for celiac and for wheat allergy but nonetheless feel better off gluten. Mainstream gastroenterology has debated whether NCGS is real or mostly a response to FODMAPs in wheat, and the honest answer is that both are happening in different people.
For Hashimoto's specifically, the most-cited trial is Krysiak and colleagues (2019), a prospective pilot study of 34 women with Hashimoto's who were not taking thyroid medication and who had positive tissue transglutaminase antibodies (a celiac-type antibody) found by chance; 16 followed a gluten-free diet for six months and 18 kept their usual diet. Participants who adhered to a strict gluten-free diet for six months showed a roughly 36% reduction in TPO antibody levels and improved thyroid-stimulating hormone and free T4 trends compared to controls who kept eating gluten. The study was not a double-blind randomized controlled trial (RCT), the sample was modest, and it has not been independently replicated at the same scale. Because every woman in it had celiac-type antibodies, the study does not show what a gluten-free diet does in Hashimoto's without them.
Two later pooled analyses looked at people with Hashimoto's and no celiac disease. A 2023 meta-analysis of 4 small studies (87 patients with no symptoms or biopsy signs of celiac disease, about 6 months gluten-free) found that thyroid-stimulating hormone fell and free T4 rose slightly, while the drops in thyroglobulin and TPO antibodies were not statistically clear; the authors wrote that the evidence is not yet sufficient to recommend the diet to all patients with Hashimoto's (Piticchio et al., 2023). A 2025 meta-analysis of the 3 randomized controlled trials (110 people with Hashimoto's but no celiac disease) found that a gluten-free diet lowered thyroglobulin antibodies but raised TPO antibodies, with no significant change in thyroid-stimulating hormone, free T3 or free T4; the authors rated the evidence very uncertain (Araújo et al., 2025).
In short: for Hashimoto's without celiac disease, the evidence on a gluten-free diet is small and mixed. The diet itself is cheap, and its main cost is social.
How Gluten-Free Trials Are Structured
A gluten-free trial gives a clear answer only if the diet was actually gluten-free; a half-hearted trial that shows nothing means nothing. Points practitioners describe for a meaningful trial:
- Duration — usually 3 months or more. Thyroid antibodies turn over slowly, so one month is too short to show a change; the studies pooled in 2023 lasted about 6 months.
- Strict, not "mostly." A single beer, a shared cutting board, a pizza at a friend's house reintroduces enough gluten to restart the immune reaction in sensitive individuals.
- Baseline labs before starting. TPO, TgAb, thyroid-stimulating hormone, free T4, free T3. The same panel repeated at the 3-month mark shows the difference rather than leaving it to a guess.
- Symptom tracking. A weekly log of fatigue, brain fog, joint aches, digestive symptoms, mood, and skin issues on a 1–10 scale is the usual way to track change.
- Deliberate reintroduction. In the usual protocol, regular wheat bread or pasta is eaten again for 3 days after the 3 months while the same symptom log is kept. A flare in symptoms and/or a rise in antibodies on follow-up labs is read as a reaction to gluten.
Hidden Gluten Sources
Gluten hides in more places than any first-timer expects:
- Soy sauce, teriyaki, and many Asian marinades (wheat is the first ingredient in most soy sauce; tamari is the gluten-free version).
- Salad dressings, gravies, and soups thickened with flour.
- Imitation crab, processed deli meats, and hot dogs (wheat used as filler).
- Beer, malt vinegar, malted flavorings including many breakfast cereals.
- Medications and supplements — wheat starch is a common excipient (inactive filler) in tablets, and the inactive ingredients are listed on each product's label.
- Cross-contamination at home. A shared toaster, a wooden spoon, or a knife used on regular bread is enough to transfer a crumb into the next meal.
- Oats. Pure oats are gluten-free, but most commodity oats are processed on the same equipment as wheat. Certified gluten-free oats are sold for this reason, and practitioners often leave oats out for the first few months of a trial, since some celiac patients also react to the oat protein avenin.
The Autoimmune Protocol (AIP)
The Autoimmune Protocol, usually written AIP, is an extension of the paleo diet built specifically for autoimmune disease. It removes not only gluten but every food group suspected of driving gut inflammation or immune cross-reactivity. The elimination phase removes gluten and all other grains, all dairy, all eggs, all nightshade vegetables (tomatoes, peppers, eggplant, potatoes, goji berries), all legumes including soy and peanuts, all nuts and seeds, alcohol, coffee, refined sugar, and all processed/industrial foods. What remains is meat, fish, most vegetables, fruit in moderation, coconut, olive oil, bone broth, and fermented foods.
After an elimination period of 30 to 90 days, foods are reintroduced one at a time on a structured schedule. Reactions are logged and any food that triggers symptoms is dropped. The goal is never to stay in strict elimination permanently; it is to identify the small subset of foods that actually cause trouble for the individual and then eat a much broader diet that simply avoids those.
Who Created AIP
The protocol was systematized by Sarah Ballantyne, PhD, a medical biophysicist who developed autoimmune conditions of her own and wrote The Paleo Approach (2013), the first comprehensive AIP book. She was building on earlier clinical work by Loren Cordain, PhD on paleolithic nutrition and by Datis Kharrazian, DC, a functional-medicine practitioner whose book Why Do I Still Have Thyroid Symptoms? popularized dietary approaches to Hashimoto's in the early 2010s. Ballantyne's contribution was turning a loose set of recommendations into a structured, phased protocol with reintroduction rules. The roots of AIP are in paleo and functional medicine, not in any mainstream gastroenterology or endocrinology guideline.
Evidence for AIP in Hashimoto's
The most-cited Hashimoto's-specific AIP trial is the Abbott 2019 open-label study. Seventeen women aged 20 to 45 with Hashimoto's joined a 10-week online health-coaching program — six weeks of AIP elimination followed by four weeks of maintenance — run by a physician, a team of nutritional therapy practitioners and health coaches; 16 completed the questionnaires. At ten weeks the group showed statistically significant improvements in two standardized measures: the SF-36 quality-of-life survey (all eight of its scales improved) and the Medical Symptoms Questionnaire (MSQ), whose average symptom score fell from 92 to 29. The inflammatory marker high-sensitivity C-reactive protein (hs-CRP) fell 29%, from an average of 1.63 to 1.15 mg/L. There was no significant change in thyroid-stimulating hormone, T4, T3 or thyroid antibodies. The paper's conflict-of-interest statement discloses that one co-author co-founded the company whose online coaching program was the intervention.
The caveats are real. No control group. No placebo arm. Seventeen participants is a small cohort. Intensive coaching — which most patients will never receive — is itself a powerful intervention that a real-world self-directed attempt lacks. And, notably, the study did not show a statistically significant drop in TPO antibodies in the time frame studied. Symptoms and quality of life improved; the antibody titer did not consistently follow.
A second small study, from Poland (Ihnatowicz et al., 2023), followed 28 people with Hashimoto's and normal thyroid function on AIP for 12 weeks, again with no control group. Fewer people reported feeling unwell, the thyroid gland became smaller on ultrasound, body weight fell, and free T3, free T4 and thyroid-stimulating hormone fell while staying within the normal range. Thyroglobulin antibodies fell slightly, but TPO antibodies rose significantly.
So AIP has a signal for Hashimoto's symptoms, but a modest one, in two small studies without blinding or control groups, and in neither did TPO antibodies fall. What is not known: whether AIP changes the course of Hashimoto's — no randomized controlled trial of AIP in Hashimoto's has been published. AIP remains an experiment, not a proven therapy.
Evidence for AIP in Inflammatory Bowel Disease
AIP's best trial evidence is not in thyroid disease at all but in inflammatory bowel disease. The Konijeti 2017 pilot at Scripps enrolled 15 patients with active Crohn's disease or ulcerative colitis on AIP for six weeks of elimination plus five weeks of maintenance. At week six, 73% (11 of 15) achieved clinical remission, and all 11 stayed in remission through the maintenance phase. Blood inflammation markers did not follow: C-reactive protein did not change significantly, and fecal calprotectin (a stool marker of gut inflammation) fell from an average of 471 to 112 by week 11 without reaching statistical significance. Improvements on endoscopy were noted in the 7 patients who had a follow-up endoscopy. Again, small sample and no control group, but a dramatic effect size in a notoriously treatment-resistant population.
This matters for Hashimoto's patients because autoimmune conditions cluster. If gut inflammation is doing real damage in inflammatory bowel disease (IBD) — where we can see it directly on endoscopy — the same gut inflammation may be feeding thyroid autoimmunity in parallel.
Practical AIP Structure
- Elimination phase: 30–90 days. Most people need at least 6 weeks before symptoms shift noticeably. Ninety days is the usual upper bound before reintroduction starts.
- Reintroduction phase: one food at a time. Protocols usually start with a much-missed food that is likely to be tolerated (typical first reintroductions: egg yolks, seed-based spices, ghee, then nuts, then nightshades, then dairy last).
- The 3-day window. A normal portion of the test food is eaten on day one only, and symptoms are watched over the next 72 hours: digestive changes, joint aches, skin flares, mood shifts, fatigue, sleep disturbance. With no reaction, the food stays in; after a reaction, it is dropped and a week passes before the next food is tested.
- A written log. Memory of symptoms is unreliable; a written log is the only way to know which foods actually caused a reaction.
What AIP Foods Look Like
A typical AIP day might be:
- Breakfast: salmon, sauteed greens, half an avocado, bone broth.
- Lunch: grass-fed beef, roasted carrots and beets, olive oil, sauerkraut.
- Dinner: chicken thigh, steamed broccoli, sweet potato, coconut oil.
- Snacks: berries, cucumber, olives, coconut yogurt (unsweetened, without additives the protocol excludes).
Allowed staples: all meat and fish, organ meats, most vegetables (except nightshades), fruit in moderation, coconut products, olive oil, avocado oil, bone broth, fermented vegetables (sauerkraut, kimchi without chili), fresh herbs, sea salt, apple cider vinegar.
What AIP Excludes
The complete "no" list, organized the way a grocery trip feels:
- Grains: bread, pasta, rice, oats, quinoa, corn, anything with wheat, barley, or rye.
- Dairy: milk, cheese, yogurt, butter, cream (ghee is reintroduced first, often tolerated).
- Eggs: both yolks and whites during elimination; yolks usually reintroduced first and often fine.
- Nightshades: tomatoes, bell peppers, hot peppers, eggplant, white potatoes, paprika, cayenne.
- Legumes: beans, lentils, peas, peanuts, soy (tofu, tempeh, soy sauce, edamame).
- Nuts and seeds: almonds, cashews, walnuts, chia, flax, sesame (and seed-based spices like cumin and coriander).
- Other: coffee, alcohol, wine, chocolate, refined sugar, artificial sweeteners, processed oils (canola, soy, corn, sunflower).
Reading that list in one sitting is when most people panic. It is genuinely restrictive.
Risks and Limits
AIP is not risk-free. Honest warnings:
- Nutritional adequacy. Cutting grains, legumes, dairy, eggs, nuts, and seeds simultaneously drops fiber, calcium, magnesium, and certain B vitamins. Without careful planning, deficiencies follow within months.
- Orthorexia risk. AIP rewards rule-following and vigilance. In people prone to disordered eating, the protocol can calcify into an obsessive, fear-based pattern that persists long after any health benefit. Signs: dreading restaurants, cutting social events, panic when "forbidden" food is accidentally consumed, shrinking safe-food list over time rather than growing it.
- Not evidence-based for cure. There is no randomized controlled trial showing AIP puts Hashimoto's in remission. The best studies are small, open-label, and measure quality of life more than hard disease markers.
- Social cost. Weddings, work lunches, travel, holidays. Over 90 days this is manageable; as a lifestyle, it isolates people.
- Financial cost. Grass-fed meat, wild fish, organic produce, coconut products, and specialty AIP-compliant packaged foods add up. A realistic monthly grocery budget on strict AIP for one person is often $600–$1,000, noticeably higher than an omnivorous baseline.
Safety Points During an AIP Trial
- Nutrition planning. Menu planning that covers the nutrient gaps listed above — fiber, calcium, magnesium and B vitamins — prevents most of the nutrition pitfalls; registered dietitians familiar with AIP offer this.
- Baseline labs at day zero: TPO, TgAb, thyroid-stimulating hormone, free T4, free T3, 25-hydroxy vitamin D, ferritin, serum iron, vitamin B12, and a comprehensive metabolic panel, with the same panel repeated at 90 days.
- Strict elimination is a phase, not a permanent diet. The elimination phase is diagnostic, not a lifestyle. The target endpoint is the broadest diet you can eat without symptoms, not the narrowest.
- Warning signs of deterioration. Unwanted weight loss, new hair loss, worsening fatigue, or menstrual changes during elimination are signs that the diet is doing harm; cutting more foods does not address them.
Mediterranean as a Lower-Bar Alternative
A Mediterranean-style diet is the less restrictive option that some practitioners describe as giving much of the benefit at a fraction of the restriction. Mediterranean patterns — abundant vegetables, fruit, legumes, fish, olive oil, moderate whole grains, minimal processed food and refined sugar — are among the best-studied anti-inflammatory diets in medicine, with randomized controlled trial evidence for cardiovascular disease, rheumatoid arthritis, and cognitive outcomes.
Practitioners who favour this route describe dropping ultra-processed food, seed oils, and refined sugar while adding fatty fish three times a week as delivering most of the inflammation-lowering effect that full AIP aims for — without nightshade, legume, nut, seed, or coffee restriction. In that approach, AIP comes next only if Mediterranean plus gluten-free eating has not helped after about 3 months of honest trial.
The Long-Term Plan When AIP Helps
Success on AIP means the elimination phase cleared symptoms and reintroductions identified specific foods that cause flares. The protocol's long-term plan is not permanent strict AIP but a personalized post-AIP diet, typically:
- Gluten out permanently (for most Hashimoto's patients who respond).
- One to three specific individual triggers out (for many people: dairy, or eggs, or nightshades, almost never all of them).
- Everything else back on the plate. Grains, legumes, nuts, seeds, coffee, chocolate, wine — whatever did not react gets reintroduced.
- Labs repeated at 6 and 12 months to confirm antibody trends and catch any drift.
Other Hashimoto's Options When AIP Does Not Help
When a genuine 90-day AIP elimination with careful reintroduction improves neither symptoms nor labs, that is a legitimate answer, not a personal failure: diet did not move the needle for that person. Other options discussed for Hashimoto's:
- Selenium — a 2002 placebo-controlled trial in 70 women (Gärtner et al.) gave 200 mcg of sodium selenite a day for 3 months, and TPO antibodies fell to 63.6% of their starting level, versus 88% on placebo (see the selenium article) — the one supplement with randomized controlled trial-level evidence for lowering TPO antibodies.
- Low-dose naltrexone — used off-label by some practitioners for autoimmune conditions. Off-label, 1.5–4.5 mg at bedtime, growing evidence in multiple autoimmune conditions.
- Optimizing thyroid hormone replacement — levothyroxine dose refinement, adding T3 or switching to natural desiccated thyroid (NDT) if symptoms persist on adequate T4 alone (see levo vs NDT vs T3).
- Sleep, stress, and resistance training — the unglamorous basics practitioners describe as part of any plan.
Where AIP Hype Outruns Evidence
AIP is a useful diagnostic tool for finding personal food triggers. It is not a cure for Hashimoto's, and no credible evidence supports the claim that it puts the disease into lasting remission in most people. Blog posts, social-media testimonials, and book jackets imply otherwise — they are testimonials, not trial results.
What is fair to say: some Hashimoto's patients see meaningful antibody reductions, symptom improvement, and quality-of-life gains on AIP or on gluten-free alone. That is worth something, especially when conventional care leaves symptoms on the table despite "normal" labs. What is not fair to say: that food alone fixes the disease for everyone, or that remaining on thyroid hormone replacement means you did the diet wrong. Hashimoto's is a chronic autoimmune condition of the thyroid gland; diet is one lever of several, and for most people levothyroxine remains part of treatment.
Key Research Papers
Foundational and recent peer-reviewed publications on gluten, the autoimmune protocol diet, intestinal permeability, and the Hashimoto's-celiac overlap. Each citation links to the full text via DOI.
- Krysiak R, Szkróbka W, Okopień B. The Effect of Gluten-Free Diet on Thyroid Autoimmunity in Drug-Naïve Women with Hashimoto's Thyroiditis: A Pilot Study. Experimental and Clinical Endocrinology & Diabetes. 2019;127(7):417–422. — doi:10.1055/a-0653-7108
- Piticchio T, Frasca F, Malandrino P, Trimboli P, Carrubba N, Tumminia A, Vinciguerra F, Frittitta L. Effect of gluten-free diet on autoimmune thyroiditis progression in patients with no symptoms or histology of celiac disease: a meta-analysis. Frontiers in Endocrinology. 2023;14:1200372. — doi:10.3389/fendo.2023.1200372
- Araújo EMQ, Coutinho-Lima CRO, Sousa AS, Souza LMS, Ramos HE, Almeida-Pititto B, Canto GL, Trevisani VFM. Effects of Gluten-Free Diet in Non-Celiac Hashimoto's Thyroiditis: A Systematic Review and Meta-Analysis. Nutrients. 2025;17(21):3437. — doi:10.3390/nu17213437
- Abbott RD, Sadowski A, Alt AG. Efficacy of the Autoimmune Protocol Diet as Part of a Multi-Disciplinary, Supported Lifestyle Intervention for Hashimoto's Thyroiditis. Cureus. 2019;11(4):e4556. — doi:10.7759/cureus.4556
- Ihnatowicz P, Gębski J, Drywień ME. Effects of Autoimmune Protocol (AIP) diet on changes in thyroid parameters in Hashimoto's disease. Annals of Agricultural and Environmental Medicine. 2023;30(3):513–521. — doi:10.26444/aaem/166263
- Konijeti GG, Kim N, Lewis JD, et al. Efficacy of the Autoimmune Protocol Diet for Inflammatory Bowel Disease. Inflammatory Bowel Diseases. 2017;23(11):2054–2060. — doi:10.1097/MIB.0000000000001221
- Fasano A. Zonulin and Its Regulation of Intestinal Barrier Function: The Biological Door to Inflammation, Autoimmunity, and Cancer. Physiological Reviews. 2011;91(1):151–175. — doi:10.1152/physrev.00003.2008
- Sategna-Guidetti C, Volta U, Ciacci C, et al. Prevalence of Thyroid Disorders in Untreated Adult Celiac Disease Patients and Effect of Gluten Withdrawal: An Italian Multicenter Study. American Journal of Gastroenterology. 2001;96(3):751–757. — doi:10.1016/s0002-9270(00)02410-2
- Lerner A, Jeremias P, Matthias T. Gut-Thyroid Axis and Celiac Disease. Endocrine Connections. 2017;6(4):R52–R58. — doi:10.1530/EC-17-0021
- Caturegli P, De Remigis A, Rose NR. Hashimoto Thyroiditis: Clinical and Diagnostic Criteria. Autoimmunity Reviews. 2014;13(4-5):391–397. — doi:10.1016/j.autrev.2014.01.007
- Hollowell JG, Staehling NW, Flanders WD, et al. Serum TSH, T4, and Thyroid Antibodies in the United States Population (NHANES III). Journal of Clinical Endocrinology & Metabolism. 2002;87(2):489–499. — doi:10.1210/jcem.87.2.8182
- Knezevic J, Starchl C, Tmava Berisha A, Amrein K. Thyroid–Gut-Axis: How Does the Microbiota Influence Thyroid Function? Nutrients. 2020;12(6):1769. — doi:10.3390/nu12061769
- Ch'ng CL, Jones MK, Kingham JG. Celiac Disease and Autoimmune Thyroid Disease. Clinical Medicine & Research. 2007;5(3):184–192. — doi:10.3121/cmr.2007.738
- Roy A, Laszkowska M, Sundström J, Lebwohl B, Green PH, Kämpe O, Ludvigsson JF. Prevalence of Celiac Disease in Patients with Autoimmune Thyroid Disease: A Meta-Analysis. Thyroid. 2016;26(7):880–890. — doi:10.1089/thy.2016.0108
- Volta U, Tovoli F, Cicola R, et al. Serological Tests in Gluten Sensitivity (Nonceliac Gluten Intolerance). Journal of Clinical Gastroenterology. 2012;46(8):680–685. — doi:10.1097/mcg.0b013e3182372541
- Gärtner R, Gasnier BCH, Dietrich JW, Krebs B, Angstwurm MWA. Selenium Supplementation in Patients with Autoimmune Thyroiditis Decreases Thyroid Peroxidase Antibodies Concentrations. Journal of Clinical Endocrinology & Metabolism. 2002;87(4):1687–1691. — doi:10.1210/jcem.87.4.8421
PubMed Topic Searches
Live PubMed queries that update as new papers are indexed.
- PubMed: gluten-free Hashimoto's
- PubMed: autoimmune protocol diet
- PubMed: zonulin leaky gut autoimmune
- PubMed: celiac disease + Hashimoto's
- PubMed: gliadin thyroid molecular mimicry
- PubMed: non-celiac gluten sensitivity
- PubMed: Mediterranean diet + autoimmune thyroid
- PubMed: elimination diet orthorexia
Connections
- Endocrinology
- How Your Thyroid Is Controlled — interactive animation
- Hashimoto's Thyroiditis Overview
- Levothyroxine vs NDT vs T3
- Selenium, Zinc, Iron, and Iodine
- Thyroid-Stimulating Hormone, T4, and T3 Optimal Ranges
- TPO and TgAb Antibodies
- Reverse T3 and Low T3 Syndrome
- Pregnancy and Hashimoto's
- Hashimoto, Postural Orthostatic Tachycardia Syndrome, and Mast Cell Activation Syndrome Overlap
- Gut-Thyroid Axis and Intestinal Permeability
- Celiac Disease
- Ulcerative Colitis
- Crohn's Disease
- Selenium
- Iron
- Elimination Diet
- Gut Healing
- Fatigue
- Thyroid Disorders