⚠ Evidence warning: Clinical trials or other evidence do not support the claims that gut bacteria convert about 20% of T4 to T3, that gliadin mimics thyroid peroxidase, and that gut-healing protocols calm Hashimoto's. This page keeps it as a report of what people, websites or other media say.
Gut-Thyroid Axis & Intestinal Permeability
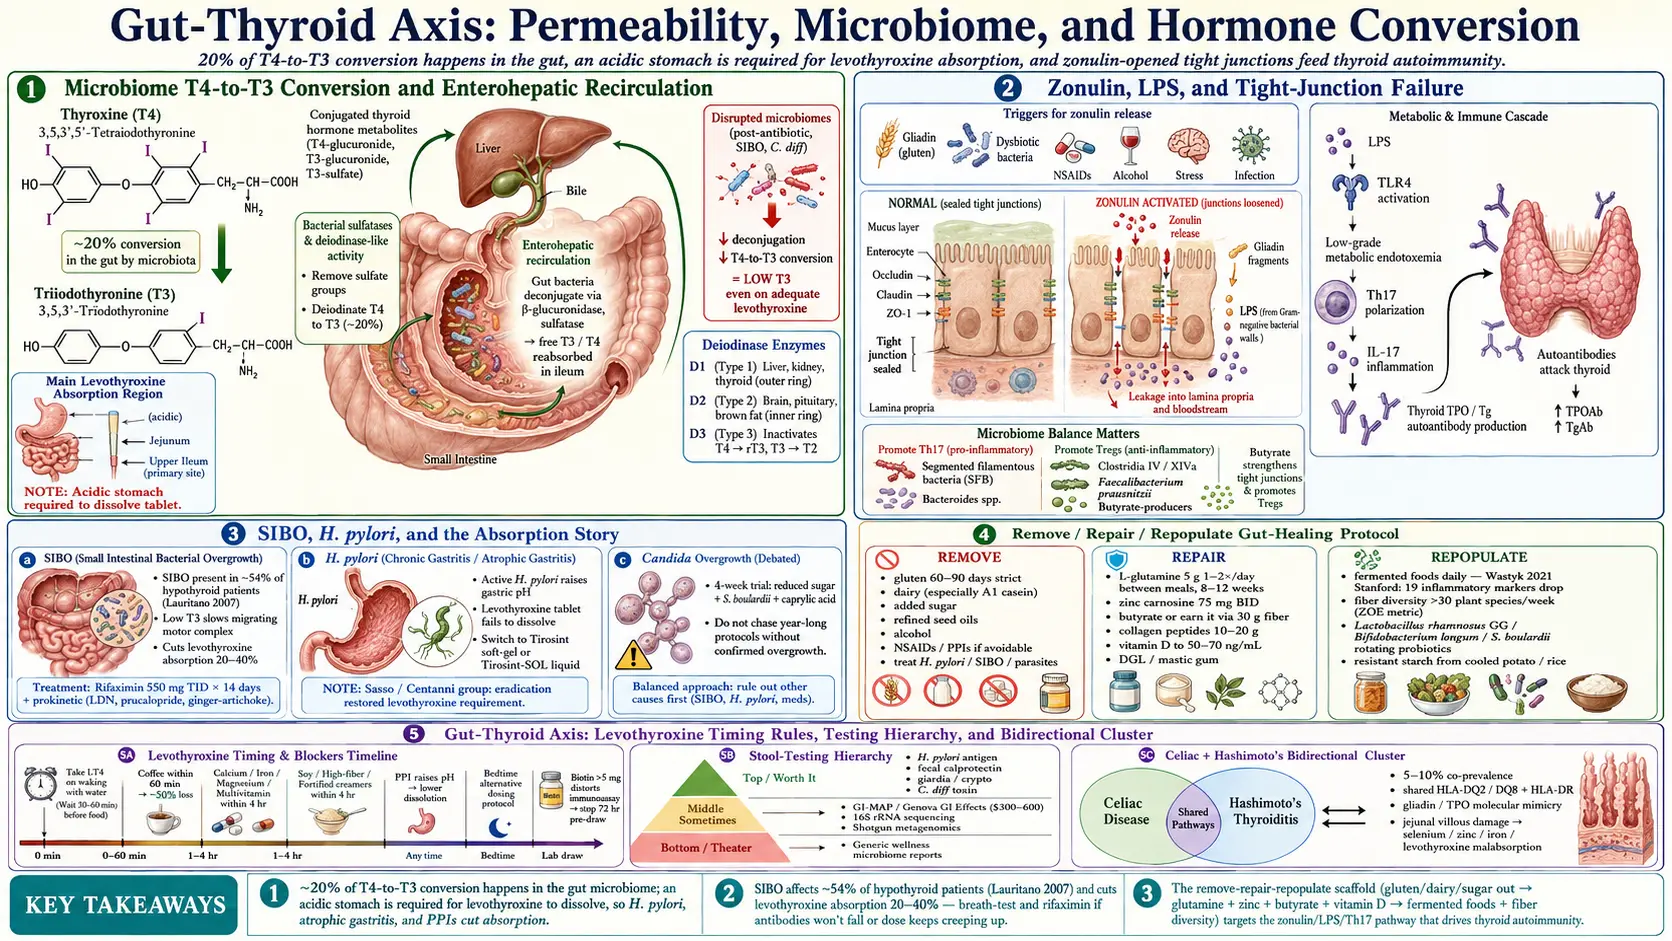
If you have Hashimoto's and a lifetime of bloating, reflux, constipation, or a diagnosis of irritable bowel syndrome (IBS) you never really accepted, you already suspect what the research is finally confirming: your gut and your thyroid are running on the same wire. Fix one and the other improves. Ignore one and the other stalls, no matter how perfectly your thyroid-stimulating hormone (TSH) is dialed in.
The gut-thyroid axis is not alternative-medicine hand-waving. It is conventional physiology: the intestinal lining controls what reaches your immune system, the microbiome converts a meaningful fraction of T4 to T3, stomach acid determines whether your levothyroxine is absorbed, and a breached gut barrier is now a documented feature of most autoimmune disease. The practical question is not whether your gut matters. It is which levers actually move the needle.
This article walks through the mechanisms in plain language, then describes the protocol integrative practitioners use — what to eat, which supplements they use, what to test, and how the timing of thyroid medication affects how much of it reaches the bloodstream.
Interactive Visualization How Your Thyroid Is Controlled — run the feedback loop Watch thyroid-stimulating hormone drive the thyroid, T4 convert to T3, and the loop feed back — then switch on Hashimoto's, Graves', or iodine deficiency. Launch →Table of Contents
- How Gut Bacteria Convert and Absorb Thyroid Hormone
- Intestinal Permeability, Lipopolysaccharide, and Zonulin
- Th17 Polarization — Why Dysbiosis Drives Autoimmunity
- Why Celiac and Hashimoto's Travel Together
- Small Intestinal Bacterial Overgrowth as a Thyroid Trigger and Medication Blocker
- H. pylori, Low Stomach Acid, and Thyroid Antibodies
- The Yeast/Candida Debate
- The Integrative Gut-Healing Protocol: Remove, Repair, Repopulate
- Levothyroxine Timing, Proton Pump Inhibitors, and What Actually Blocks Absorption
- Stool Testing — What Is Worth Paying For
- Key Research Papers
- PubMed Topic Searches
- Connections
- Featured Videos
How Gut Bacteria Convert and Absorb Thyroid Hormone
Your thyroid mostly produces T4, the storage form of thyroid hormone. The active form your cells actually use is T3, and the bulk of that conversion happens in the liver and peripheral tissues via deiodinase enzymes. What is less widely known is that your gut microbiome converts roughly 20% of T4 to T3 through bacterial sulfatases and deiodinase-like activity. Patients with severely disrupted microbiomes — after long antibiotic courses, in small intestinal bacterial overgrowth (SIBO), or after C. diff — often run low-T3 labs even on adequate levothyroxine.
The gut also houses a reservoir of conjugated thyroid hormone in bile. Healthy gut bacteria deconjugate these metabolites so they can be reabsorbed, a loop called enterohepatic recirculation. Constipation, dysbiosis, or bile-acid problems leak that reservoir, and free T3 trends lower than thyroid-stimulating hormone would predict.
Absorption of oral levothyroxine happens primarily in the jejunum and upper ileum. It requires an acidic stomach to dissolve the tablet and an intact small-bowel mucosa to cross into the bloodstream. Anything that disrupts either end — H. pylori, atrophic gastritis, proton pump inhibitors (PPIs), celiac villous flattening — can reduce absorption and push your thyroid-stimulating hormone up even though your dose has not changed. In a 2006 study, people with H. pylori gastritis, atrophic gastritis or both needed 22–34% more thyroxine than people without stomach disease.
Intestinal Permeability, Lipopolysaccharide, and Zonulin
"Leaky gut" was a fringe term ten years ago and is now a measurable phenomenon published in mainstream journals. The single-cell layer lining your small intestine is sealed by tight junctions — protein complexes that decide what passes through. A protein called zonulin, described in 2000 by Alessio Fasano's group at the Center for Vaccine Development in Baltimore, is the main human regulator that opens those junctions. Elevated serum zonulin correlates with increased permeability in celiac disease, type 1 diabetes, Hashimoto's, and several other autoimmune conditions.
When the barrier loosens, bacterial fragments from your gut — especially lipopolysaccharide (LPS), a component of Gram-negative bacterial cell walls — leak into your bloodstream. Lipopolysaccharide is a potent immune trigger. Even low-grade "metabolic endotoxemia" activates toll-like receptor 4 (TLR4) on immune cells and drives systemic inflammation. In Hashimoto's, that inflammation both damages thyroid tissue directly and trains your immune system to treat thyroid proteins (TPO, Tg) as enemies.
Triggers that open zonulin and widen the junctions include gliadin (from wheat gluten), certain gut bacteria, chronic stress, nonsteroidal anti-inflammatory drugs (NSAIDs), alcohol, and intestinal infections. The cascade is: trigger → zonulin release → tight junctions loosen → lipopolysaccharide and undigested proteins cross → immune activation → autoimmune flare. This is why gluten elimination helps some Hashimoto's patients even when they test negative for celiac — gliadin still opens zonulin in most humans; they simply do not have the HLA-DQ2/DQ8 genes to mount a full celiac attack.
Th17 Polarization — Why Dysbiosis Drives Autoimmunity
Your immune system has several flavors of T-helper cells. Th17 cells, which produce the cytokine IL-17, are the ones implicated in Hashimoto's, psoriasis, ankylosing spondylitis, and inflammatory bowel disease. Healthy guts keep Th17 in balance with regulatory T cells (Tregs), which calm the immune response.
Specific gut bacteria shift this balance. Segmented filamentous bacteria and certain Bacteroides species push Th17 up. Clostridia cluster IV and XIVa, plus Faecalibacterium prausnitzii, push Tregs up. A gut dominated by the wrong species tilts your immune system toward chronic Th17-driven inflammation — the exact biology driving thyroid autoantibody production. Short-chain fatty acids (especially butyrate), produced when healthy bacteria ferment fiber, are the key molecule that induces Tregs. A fiber-poor, low-diversity diet starves these bugs and the brake on autoimmunity comes off.
Why Celiac and Hashimoto's Travel Together
The largest pooled analysis (a 2016 meta-analysis of 6,024 people with autoimmune thyroid disease) found biopsy-confirmed celiac disease in 1.6% — about 1 in 62. The rate was higher in children with thyroid autoimmunity (6.2%) than in adults (2.7%), and 1.4% in people with an underactive thyroid. Conversely, Hashimoto's is the single most common autoimmune disease outside the gut in celiac patients. The reasons are stacked:
- Shared human leukocyte antigen (HLA) risk genes. HLA-DQ2 and HLA-DQ8 predispose to celiac; overlapping HLA-DR alleles predispose to Hashimoto's.
- Molecular mimicry. Segments of gliadin resemble thyroid peroxidase (TPO). Antibodies raised against gliadin can cross-react with thyroid tissue.
- Malabsorption. Untreated celiac damages the jejunal villi where selenium, zinc, iron, vitamin D, and levothyroxine are absorbed. The resulting deficiencies further impair thyroid function (see the minerals article).
- Shared zonulin biology. Both conditions run high serum zonulin and high permeability.
The authors of that meta-analysis argue for screening people with autoimmune thyroid disease for celiac disease, given the higher rate. Screening only works before a gluten-free diet starts: the antibodies normalize off gluten and the diagnostic window closes. The standard blood tests are tissue transglutaminase immunoglobulin A (tTG-IgA) plus total immunoglobulin A (IgA); a positive or equivocal result is confirmed by a gastroenterologist with a duodenal biopsy. With a negative result, a gluten-free trial for Hashimoto's symptoms is an n-of-1 experiment some people choose — see the AIP & gluten elimination article.
Small Intestinal Bacterial Overgrowth as a Thyroid Trigger and Medication Blocker
Small intestinal bacterial overgrowth (SIBO) is a disproportionately common companion of hypothyroidism. A 2007 Italian study of 50 people with a history of overt hypothyroidism from autoimmune thyroiditis found 54% (27 of 50) had a positive glucose breath test for small intestinal bacterial overgrowth, compared with 5% (2 of 40) of controls. Those with overgrowth had more abdominal discomfort, wind and bloating; after rifaximin 1,200 mg a day for a week cleared the overgrowth, these symptoms improved, but thyroid hormone levels did not change significantly. The mechanism is straightforward: low T3 slows small-bowel motility, the migrating motor complex (MMC) — the cleansing wave that sweeps bacteria downstream between meals — weakens, and bacteria creep upward into the jejunum where they do not belong.
Once established, small intestinal bacterial overgrowth hits the thyroid back three ways:
- Absorption interference. Overgrown bacteria deconjugate bile acids, damage the brush border, and physically compete for drug uptake. In the 2007 study, however, clearing the overgrowth did not change thyroid hormone levels, and the authors concluded that these bacteria do not interfere with thyroid hormone levels.
- Immune activation. Small intestinal bacterial overgrowth elevates lipopolysaccharide and drives chronic low-grade inflammation that feeds Hashimoto's antibody production.
- Conversion disruption. Disordered bacteria mean disordered peripheral T4-to-T3 conversion.
When Hashimoto's antibodies will not come down, the levothyroxine dose keeps creeping up, or bloating comes within 90 minutes of eating, a lactulose or glucose breath test is the usual check. A common treatment is rifaximin 550 mg three times daily for 14 days (with neomycin added for methane-dominant small intestinal bacterial overgrowth), followed by a prokinetic at bedtime (low-dose naltrexone, prucalopride, or ginger-artichoke extract) to restart the MMC. Full details are in the small intestinal bacterial overgrowth overview.
H. pylori, Low Stomach Acid, and Thyroid Antibodies
Active Helicobacter pylori infection is associated with higher TPO antibody titers and with levothyroxine malabsorption. Italian researchers (Centanni and colleagues, 2006) studied 248 people taking thyroxine for multinodular goiter: those with H. pylori gastritis, atrophic gastritis or both needed 22–34% more thyroxine than those without stomach disease. In 11 patients followed over time, catching H. pylori raised thyroid-stimulating hormone, and clearing the infection nearly reversed the rise. In 10 patients with reflux, the acid-reducing drug omeprazole raised thyroid-stimulating hormone in all of them, and a 37% higher thyroxine dose reversed it. The mechanism is partly molecular mimicry (H. pylori antigens share sequence with thyroid proteins) and partly mechanical: chronic H. pylori causes atrophic gastritis, which flattens acid-producing parietal cells and raises gastric pH.
Levothyroxine needs an acidic stomach to dissolve. When pH rises — from H. pylori, atrophic gastritis, or proton pump inhibitors — a tablet can sit intact in the stomach long enough to leave via the small bowel without being absorbed. The liquid (oral solution) and soft-gel capsule forms of levothyroxine skip the dissolution step and are used for people in this situation.
Testing: the H. pylori stool antigen or the urea breath test detects active infection (blood antibody tests are cheaper but cannot distinguish past from active infection). Standard eradication is a 14-day quadruple therapy (proton pump inhibitor + bismuth + two antibiotics), with a re-test at least four weeks after finishing therapy.
The Yeast/Candida Debate
Gut Candida overgrowth is a genuine phenomenon in immunocompromised patients, after heavy antibiotic courses, or in uncontrolled diabetes. Whether it drives Hashimoto's in otherwise healthy adults is contested. The integrative-medicine community treats it aggressively; mainstream gastroenterology is skeptical because the diagnostic tests (stool culture, organic acid urine markers) have mediocre specificity.
A middle position some practitioners describe: for people with a plausible history (prolonged antibiotics, recurrent vaginal or oral thrush, visible white tongue coating, strong carbohydrate cravings), a 4-week trial of reduced added sugar, a rotating antifungal (caprylic acid, undecylenic acid, or prescription nystatin for gut-limited exposure), and a probiotic such as Saccharomyces boulardii is cheap and low-risk. If nothing changes in four weeks, the trial is dropped; a year-long "candida protocol" is kept for cases where a stool test or biopsy actually confirms overgrowth.
The Integrative Gut-Healing Protocol: Remove, Repair, Repopulate
Integrative gastroenterology collapses gut work into three phases. They overlap in practice, but the scaffold is useful. The amounts and doses below are the ones integrative practitioners describe.
1. Remove
- Gluten — a 60–90 day strict trial at minimum; with confirmed celiac disease, gluten-free is lifelong.
- Dairy — especially conventional A1 casein; practitioners report that many Hashimoto's patients tolerate goat, sheep, or A2 cow dairy.
- Added sugar and refined seed oils — both feed dysbiosis and drive Th17 inflammation.
- Alcohol — opens tight junctions directly.
- Unnecessary nonsteroidal anti-inflammatory drugs and proton pump inhibitors — both damage barrier integrity.
- Treating identified pathogens — H. pylori, small intestinal bacterial overgrowth, parasites if found.
2. Repair
- L-glutamine: 5 g powder in water, 1–2 times daily between meals, 8–12 weeks. Glutamine is the preferred fuel of enterocytes and supports tight-junction protein synthesis.
- Zinc carnosine: 75 mg twice daily with food. Studied specifically for gastric and small-bowel mucosal repair; also supports thyroid enzyme function.
- Butyrate: either as a capsule (tributyrin or sodium butyrate, 300–600 mg twice daily) or, preferably, earned from eating 30+ g of fiber daily. Butyrate fuels colonocytes, tightens barrier, and induces Tregs.
- Collagen peptides / bone broth: 10–20 g daily. Glycine and proline are building blocks for mucosal repair.
- Vitamin D: practitioners target a serum 25(OH)D of 50–70 ng/mL. Vitamin D directly regulates tight-junction gene expression and Treg development.
- Deglycyrrhizinated licorice (DGL) or mastic gum for gastritis-type symptoms.
3. Repopulate
- Fermented foods daily: real sauerkraut, kimchi, kefir (if dairy tolerated), yogurt, and the traditional fermented soy foods miso, natto and tempeh. A 2021 Stanford randomized trial (17 weeks, 18 healthy adults per group) found that a high-fermented-food diet steadily increased gut microbiome diversity and decreased inflammatory markers, while microbial diversity stayed stable on the high-fiber diet of the same study.
- Fiber diversity > fiber quantity: a target of 30+ plant species per week, popularized by a microbiome-nutrition company. Different fibers feed different bacteria.
- Targeted probiotics: Lactobacillus rhamnosus GG, Bifidobacterium longum, and Saccharomyces boulardii have the most data. Practitioners favor rotating probiotics over the same strain indefinitely.
- Resistant starch: cooled potatoes, green-tip bananas, cooked-and-cooled rice. Feeds butyrate producers.
Levothyroxine Timing, Proton Pump Inhibitors, and What Actually Blocks Absorption
How much levothyroxine reaches the bloodstream depends heavily on what it is taken with. The usual rules:
- On an empty stomach, 60 minutes before food or coffee. In a 2008 study, swallowing levothyroxine with coffee lowered the average rise in blood T4 by 36% in patients and 29% in volunteers. Water only in that window.
- 4 hours apart from calcium, iron, magnesium, and multivitamins. These minerals bind levothyroxine into an unabsorbable complex.
- Apart from proton pump inhibitors and H2 blockers. These raise stomach pH and reduce dissolution. For people who stay on one, the soft-gel capsule and liquid (oral solution) forms of levothyroxine do not require acid to dissolve.
- At least 4 hours apart from soy, high-fiber meals, and fortified coffee creamers.
- Bedtime dosing is an acceptable alternative. It is taken at least 3–4 hours after the last meal, at least 1 hour after calcium or magnesium supplements. Some patients get more consistent thyroid-stimulating hormone this way because their morning routine is variable.
- Biotin warning. Biotin supplements (>5 mg) distort thyroid-stimulating hormone/T4/T3 assays on most immunoassay platforms and can make your labs look falsely off. A 72-hour break from biotin before a thyroid blood draw avoids this interference.
If your thyroid-stimulating hormone is unstable despite perfect timing, the likeliest culprits in order are: H. pylori, small intestinal bacterial overgrowth, celiac, a new proton pump inhibitor, a new calcium supplement, or a switch between generic manufacturers (bioequivalence is ±12.5%, which matters at narrow therapeutic windows). See the levothyroxine article for formulation differences.
Stool Testing — What Is Worth Paying For
Stool testing ranges from medically essential to expensive theater. A patient-facing breakdown:
- Worth it, covered by insurance: H. pylori stool antigen, fecal calprotectin (screens for inflammatory bowel disease, IBD), giardia/cryptosporidium antigen if recent travel, C. difficile toxin if recent antibiotics, standard O&P if symptomatic.
- Sometimes worth it, often out of pocket: A comprehensive stool test with 16S/shotgun sequencing (sold by several commercial laboratories) — useful if you have been symptomatic for years, have tried basic interventions, and want to target dysbiosis more specifically. Expect $300–$600.
- Mostly theater: Generic microbiome "wellness" reports that give you percentages of bacteria without clinical decision rules. Interesting, not actionable.
- Breath tests (lactulose or glucose for small intestinal bacterial overgrowth, urea for H. pylori) are cheaper, more targeted, and usually a better first step than a full stool panel.
Integrative practitioners describe a cheaper first sequence for most Hashimoto's patients than a $500 stool test: a 90-day gluten-free trial, correct levothyroxine timing, screening for H. pylori and celiac disease, and more fermented foods and fiber, with deep testing kept for after those basics.
Key Research Papers
- Fasano A. Zonulin, regulation of tight junctions, and autoimmune diseases. Ann N Y Acad Sci. 2012. — doi:10.1111/j.1749-6632.2012.06538.x
- Knéžević J, Starchl C, Tmava Berisha A, Amrein K. Thyroid-gut-axis: how does the microbiota influence thyroid function? Nutrients. 2020;12(6):1769. — PubMed PMID: 32545596
- Centanni M, Gargano L, Canettieri G, et al. Thyroxine in goiter, Helicobacter pylori infection, and chronic gastritis. N Engl J Med. 2006;354(17):1787–1795. — doi:10.1056/nejmoa043903
- Lauritano EC, et al. Association between hypothyroidism and small intestinal bacterial overgrowth. J Clin Endocrinol Metab. 2007. — doi:10.1210/jc.2007-0606
- Wastyk HC, et al. Gut-microbiota-targeted diets modulate human immune status. Cell. 2021. — doi:10.1016/j.cell.2021.06.019 (Stanford fermented-foods trial)
- Fasano A. Zonulin and its regulation of intestinal barrier function: the biological door to inflammation, autoimmunity, and cancer. Physiol Rev. 2011;91(1):151–175. — doi:10.1152/physrev.00003.2008
- Wang W, Uzzau S, Goldblum SE, Fasano A. Human zonulin, a potential modulator of intestinal tight junctions. J Cell Sci. 2000;113(Pt 24):4435–4440. — PubMed PMID: 11082037
- Roy A, Laszkowska M, Sundström J, Lebwohl B, Green PH, Kämpe O, Ludvigsson JF. Prevalence of celiac disease in patients with autoimmune thyroid disease: a meta-analysis. Thyroid. 2016;26(7):880–890. — PubMed PMID: 27256300
- Benvenga S, Bartolone L, Pappalardo MA, Russo A, Lapa D, Giorgianni G, Saraceno G, Trimarchi F. Altered intestinal absorption of L-thyroxine caused by coffee. Thyroid. 2008;18(3):293–301. — PubMed PMID: 18341376
PubMed Topic Searches
For readers who want to go deeper, these PubMed queries return current peer-reviewed work on the gut-thyroid axis:
- Gut microbiome and thyroid hormone metabolism
- Intestinal permeability and Hashimoto's thyroiditis
- Zonulin and autoimmune thyroid disease
- SIBO, hypothyroidism, and levothyroxine absorption
- Helicobacter pylori and thyroid autoantibodies
- Celiac disease and Hashimoto's co-occurrence
- Th17, Tregs, and microbiota in autoimmunity
- Butyrate, intestinal barrier, and autoimmune regulation
- Proton pump inhibitors and levothyroxine absorption
- L-glutamine and intestinal barrier repair
Connections
- Endocrinology
- How Your Thyroid Is Controlled — interactive animation
- Hashimoto's Thyroiditis Overview
- AIP and Gluten Elimination
- Levothyroxine vs NDT vs T3
- Selenium, Zinc, Iron, and Iodine
- Thyroid-Stimulating Hormone, T4, and T3 Optimal Ranges
- TPO and TgAb Antibodies
- Reverse T3 and Low T3 Syndrome
- Pregnancy and Hashimoto's
- Hashimoto, Postural Orthostatic Tachycardia Syndrome, and Mast Cell Activation Syndrome Overlap
- Small Intestinal Bacterial Overgrowth
- Celiac Disease
- Gut Healing
- Elimination Diet
- Glutamine
- Bloating
- Fermented Foods
- Thyroid Disorders