⚠ Evidence warning: Clinical trials or other evidence do not support the claims that desiccated thyroid, compounded slow-release T3 and combination T4+T3 make patients feel better than levothyroxine. This page keeps it as a report of what people, websites or other media say.
Levothyroxine vs NDT vs Combination T4+T3 for Hashimoto's
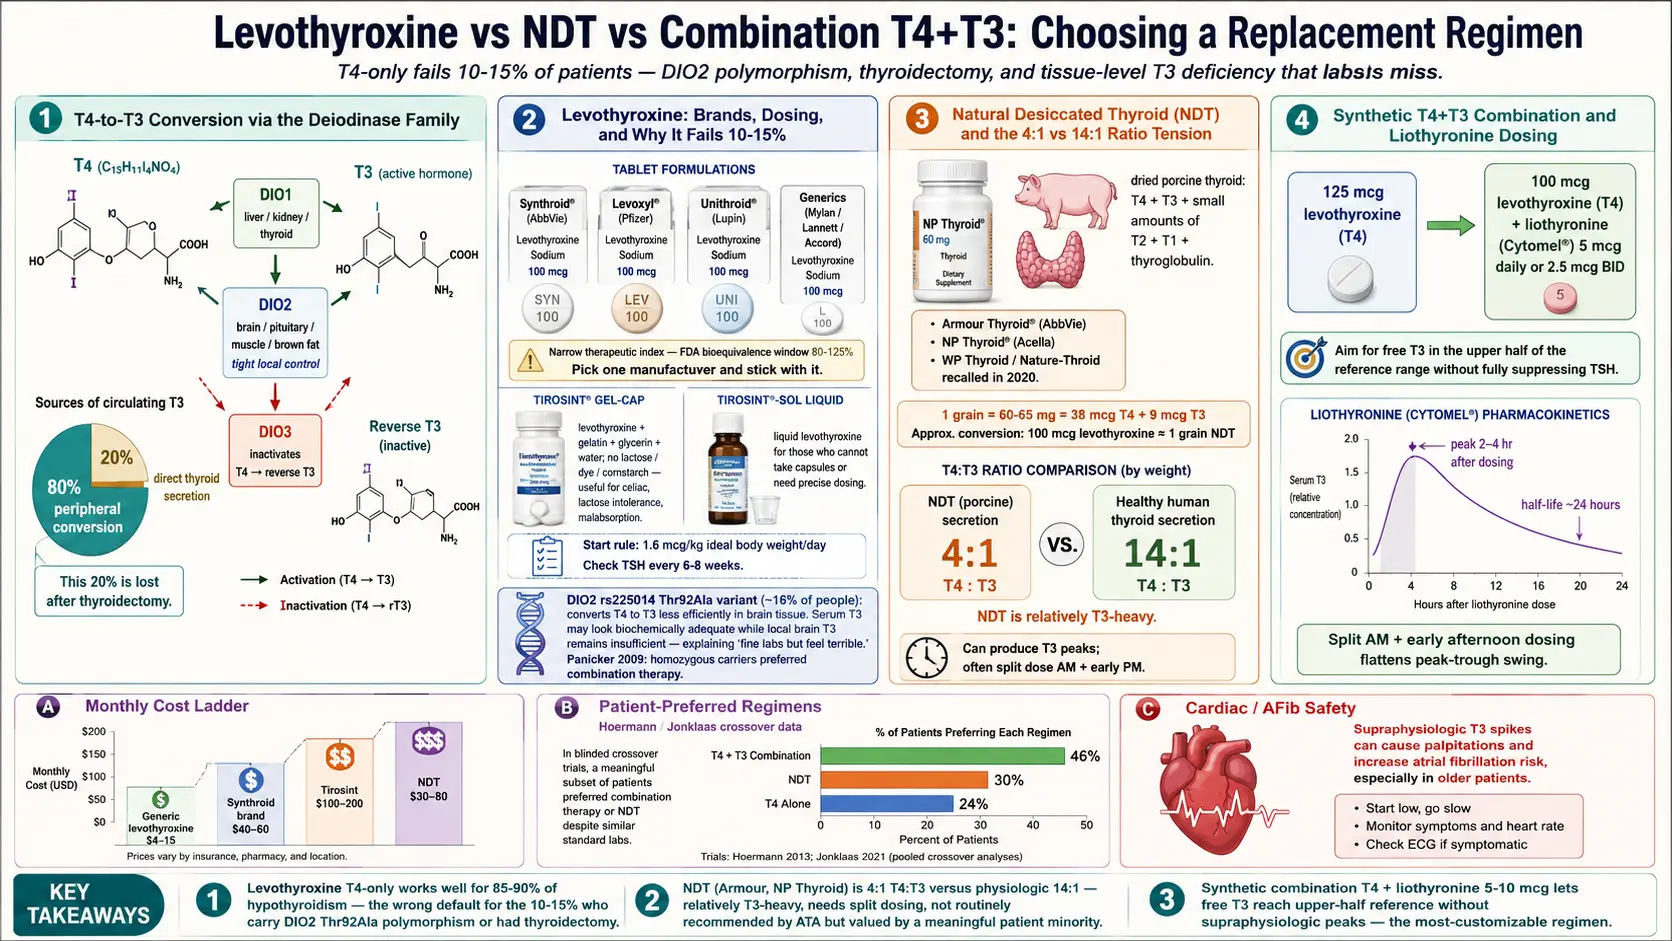
Table of Contents
- Levothyroxine — the T4-Only Standard
- Brand vs. Generic
- A Soft-Gel or Liquid Levothyroxine
- Dosing and How to Take Levothyroxine
- Why T4-Only Fails Some Patients
- Natural Desiccated Thyroid (NDT)
- Converting From Levo to NDT
- The NDT Controversy
- Combination T4 + T3 (Synthetic)
- Liothyronine Dosing
- Slow-Release Compounded T3
- Evidence Review — What the Trials Show
- DIO2 Polymorphism Testing
- How to Advocate for a Trial
- Compounded T4+T3 Slow-Release
- Side Effects and Cardiac Safety
- Practical Tips for Any Regimen
- When to Reconsider Thyroid as the Problem
- Key Research Papers
- Connections
- Featured Videos
Levothyroxine — the T4-Only Standard
Levothyroxine is synthetic thyroxine (T4), identical in molecular structure to the T4 your thyroid gland would have produced on its own. It is sold in the United States as brand-name tablets, a soft-gel capsule and an oral solution, plus multiple generic versions from several manufacturers. Worldwide, it is one of the most commonly prescribed drugs on the planet — in the top five by U.S. prescription volume for more than a decade.
T4 itself is mostly a prohormone. The biologically active thyroid hormone is T3 (triiodothyronine), which binds thyroid receptors inside cells and drives metabolic gene expression. Your body is expected to take the T4 you swallow, circulate it, and convert it to T3 as needed, tissue by tissue. The enzymes that perform that conversion are the deiodinases: DIO1 (mostly liver, kidney, thyroid), DIO2 (brain, pituitary, muscle, brown fat — the tissues that want tight local control), and DIO3, which inactivates thyroid hormone by converting T4 to reverse T3.
For roughly 85–90% of people with hypothyroidism, this T4-to-T3 conversion system works well. They take one tablet a day, their thyroid-stimulating hormone normalizes, their symptoms resolve, and they never think about thyroid hormone metabolism again. Levothyroxine is cheap (generic costs $4–$10 per month with insurance, often under $15 cash at warehouse pharmacies), stable, and extensively studied. The American Thyroid Association's 2014 guideline names levothyroxine as the standard treatment for hypothyroidism, including Hashimoto's. A 2021 consensus document of the American, British and European thyroid associations reported that fourteen clinical trials had not shown a consistent benefit of combination therapy and set out how new trials should be designed; it did not issue a new treatment guideline.
A 2025 European Thyroid Association guideline on levothyroxine taken on its own discusses the food, drug and disease factors that can raise the dose a person needs, with a specific focus on the liquid and soft-gel forms of the hormone.
Brand vs. Generic
Levothyroxine has a narrow therapeutic index — the dose that works and the dose that causes symptoms are close together. Patients sometimes report that switching between a brand-name tablet, a generic, and a different generic leaves them feeling off even when their thyroid-stimulating hormone looks similar on paper.
The U.S. Food and Drug Administration (FDA) allows generic levothyroxine to be between 80% and 125% of the labeled dose (the bioequivalence window for most drugs). For a narrow-therapeutic-index hormone, that range is wide enough to matter. A 100 mcg tablet from manufacturer A containing 95 mcg of actual drug, followed by a 100 mcg tablet from manufacturer B containing 112 mcg, is technically legal but biologically a 17% dose change.
The practical approach patients and clinicians describe is staying with one manufacturer, and re-testing thyroid-stimulating hormone about six weeks after a pharmacy switches generics because of supply. The manufacturer name is printed on the bottle label, so it can be compared with the last refill when symptoms appear after a refill. Some endocrinologists write "dispense as written" or "brand necessary" on brand-name prescriptions specifically to prevent substitution. Insurance may or may not honor this — brand-name tablets cost about $40–$60 per month out of pocket when a plan refuses them.
A Soft-Gel or Liquid Levothyroxine
A soft-gel levothyroxine capsule contains just four ingredients: levothyroxine, gelatin, glycerin, and water. No lactose, no dyes, no cornstarch, no talc, no acacia. For patients with celiac disease, lactose intolerance, dye allergies, or significant malabsorption (post-bariatric surgery, atrophic gastritis, long-term proton pump inhibitor (PPI) use), a soft-gel or liquid levothyroxine often works when tablets do not.
Levothyroxine is also available as a liquid solution in single-dose ampoules, useful for patients who cannot swallow pills or need doses between standard tablet strengths. The downside is cost: the soft-gel form typically runs $100–$200 per month with insurance and significantly more cash. Manufacturer copay cards sometimes reduce the price to $25–$50. For most patients a standard tablet works; the soft-gel and liquid forms serve a specific subset.
Dosing and How to Take Levothyroxine
The rough starting dose for full replacement (e.g., after thyroidectomy or in long-standing Hashimoto's with near-zero gland function) is 1.6 mcg per kilogram of ideal body weight per day. A 70 kg adult with ideal body weight close to that number starts around 112 mcg. In older adults, patients with cardiac disease, or anyone with subclinical hypothyroidism, a lower starting dose of 25–50 mcg is safer, titrated upward.
Thyroid-stimulating hormone (and ideally free T4 and free T3) is usually re-checked every 6 to 8 weeks after a dose change. Earlier testing catches only transient shifts; the steady-state thyroid-stimulating hormone lags the dose change by about six weeks.
Timing matters more than people realize. Levothyroxine is best absorbed on an empty stomach. The standard instructions given with it:
- Taken 30 to 60 minutes before food or coffee in the morning, with plain water.
- Or taken at bedtime, at least three hours after the last meal. Bedtime dosing produces slightly higher and steadier T4 levels for some patients, and it is an option if morning fasting is impractical.
- Spaced at least four hours from calcium, iron, magnesium, multivitamins, antacids, sucralfate, cholestyramine, soy protein, high-fiber foods, and espresso.
- Proton-pump inhibitors (omeprazole, pantoprazole) reduce absorption by about 10–15% by raising gastric pH. People who take a proton pump inhibitor often need a slightly higher levothyroxine dose.
Why T4-Only Fails Some Patients
Large patient surveys consistently find that 10–15% of levothyroxine-treated patients report ongoing symptoms — fatigue, weight gain they cannot shift, cognitive fog, mood changes, cold intolerance — despite a thyroid-stimulating hormone that the lab calls normal. This is not trivial. Ten percent of millions of prescriptions is a very large group of people who have been told "your labs are fine" while still feeling ill.
Two mechanisms are plausible and partially documented:
DIO2 polymorphism (rs225014, also called Thr92Ala). A common variant in the DIO2 gene produces a deiodinase enzyme that converts T4 to T3 less efficiently, especially in tissues like the brain. In a 2009 study of 552 people taking T4, about 16% carried two copies of the variant (the CC genotype). Carriers on T4-only therapy may have biochemically adequate serum T3 but locally insufficient brain T3, which would explain the subjective fog and low mood that lab numbers do not capture. Panicker and colleagues reported in 2009 that homozygous carriers showed significantly better psychological well-being on combination T4+T3 than on T4 alone.
Thyroidectomy effect. A healthy thyroid secretes both T4 and a small amount of T3 directly. When the gland is surgically removed (for cancer, nodules, or Graves), the direct-T3 source is gone, and the patient must make all their T3 from peripheral conversion. Thyroidectomized patients are disproportionately represented in the "still symptomatic on levo" group, and serum T3 tends to run in the low-normal range on T4-only therapy even when thyroid-stimulating hormone is suppressed.
A 2024 double-blind trial (the LEVOLIO study) tested combination therapy in 141 people with no thyroid after total thyroidectomy. For six months, 70 took levothyroxine plus liothyronine twice a day (an average of 5 mcg of liothyronine a day) and 71 took levothyroxine plus a placebo. Tissue markers of thyroid hormone action (sex hormone binding globulin, blood fats and bone markers) and quality of life did not differ between the groups, even though the free T3 to free T4 ratio rose on the combination, and no preference for combination therapy was found.
There are other hypotheses — chronic inflammation and elevated reverse T3, low ferritin, cortisol dysregulation, undiagnosed sleep apnea — and they matter too. But DIO2 variation and thyroidectomy are the two biologically cleanest reasons why T4-only does not work for everyone.
Natural Desiccated Thyroid (NDT)
NDT is dried, powdered pig thyroid gland compressed into tablets. It contains both T4 and T3, plus small amounts of T2, T1, and thyroglobulin. It predates synthetic levothyroxine by about 80 years — it was the standard hypothyroid treatment from the 1890s until the 1960s, when levothyroxine displaced it.
Current U.S. products are porcine (pig) desiccated thyroid tablets sold under a few product names. In 2020 two porcine thyroid products were recalled for sub-potency. A similar product is available in Canada and by limited import. Dosing is measured in grains: 1 grain = 60 or 65 mg depending on the product, delivering about 38 mcg T4 and 9 mcg T3 per grain.
The ratio is the key feature. NDT is roughly 4:1 T4 to T3 by weight, whereas a healthy human thyroid secretes closer to 14:1. In other words, NDT is relatively T3-heavy. This is a double-edged feature: patients who feel better on NDT usually credit the extra T3, but the same T3 load can produce transient peaks that cause palpitations or anxiety, particularly if a full daily dose is taken at once.
Converting From Levo to NDT
A standard equivalence used clinically: 100 mcg levothyroxine is approximately equal to 1 grain (60–65 mg) of NDT. This is only approximate; the T3 component in NDT is biologically more potent than its weight suggests, so many patients end up on a slightly lower "equivalent" NDT dose than the math predicts.
A conversion approach prescribers describe:
- Starting with the approximate equivalence (e.g., 125 mcg levo → about 1.25 grains NDT).
- Splitting the dose — half in the morning, half early afternoon — to blunt the T3 peak.
- Re-testing thyroid-stimulating hormone, free T4, and free T3 at 4–6 weeks. Thyroid-stimulating hormone typically runs lower on NDT than on levo at equivalent symptomatic doses because circulating T3 suppresses thyroid-stimulating hormone more strongly.
- Titrating by quarter-grain (about 15 mg) increments every 4–6 weeks based on symptoms and labs.
The NDT Controversy
Mainstream endocrinology is skeptical of NDT for reasonable reasons: the T4:T3 ratio is not physiologic, batch-to-batch potency has historically varied, and head-to-head randomized controlled trials have been mixed. The American Thyroid Association's 2014 guideline states that NDT is not routinely recommended.
Patient-preference data add another side. In a 2013 double-blind crossover trial, 70 people with hypothyroidism who had been on a stable levothyroxine dose took desiccated thyroid extract for 16 weeks and levothyroxine for 16 weeks without knowing which was which. There were no differences in symptoms or in memory and thinking tests between the two, and desiccated thyroid did not significantly improve quality of life, but people lost about 3 lb on it (172.9 vs 175.7 lb). At the end, 34 of the 70 (48.6%) preferred desiccated thyroid, 13 (18.6%) preferred levothyroxine and 23 (32.9%) had no preference. A larger 2021 three-arm trial by researchers from the same group is described in the evidence review below.
Patients who switch to desiccated thyroid often report feeling better, and practitioners who prescribe it describe it as safe in properly titrated doses, usually after a fair trial of T4 alone. In the blinded trials, the group averages did not differ from levothyroxine; the difference showed up as patient preference (nearly half in the 2013 trial) and in the most symptomatic third of patients in the 2021 trial.
Combination T4 + T3 (Synthetic)
An alternative to NDT is to combine standard levothyroxine with synthetic T3 (liothyronine, sold as brand-name and generic tablets). This lets the clinician pick any T4:T3 ratio rather than being locked into NDT's 4:1.
A common starting approach for a patient on, say, 125 mcg levothyroxine who still has symptoms:
- Levothyroxine reduced by about 12.5–25 mcg.
- Liothyronine 5 mcg added once daily (or 2.5 mcg twice daily).
- A re-test at 6 weeks, with free T3 aimed at the upper half of the reference range without thyroid-stimulating hormone fully suppressed.
Some endocrinologists target a T4:T3 ratio closer to physiologic (around 13:1 to 16:1), which is more conservative than NDT's 4:1. Others aim higher T3 based on symptoms.
Liothyronine Dosing
Synthetic T3 (liothyronine) has a short half-life of roughly 24 hours, with peak levels about 2–4 hours after dosing. This produces a daily peak-and-trough pattern that some patients tolerate fine and others find destabilizing.
Points prescribers describe:
- A low start: 5 mcg once daily in the morning.
- Slow titration: increases of 2.5–5 mcg every 2–4 weeks as tolerated.
- Many patients do better on split dosing — morning and early afternoon — to flatten the peak-trough swing.
- Evening T3 doses can fragment sleep in some people.
- Free T3 can be measured both in the morning (pre-dose trough) and 2–4 hours after the morning dose (peak) if symptoms of overdose appear.
Slow-Release Compounded T3
Compounding pharmacies can prepare sustained-release liothyronine capsules, designed to deliver T3 gradually over 8–12 hours and permit once-daily dosing without the sharp peak. This is popular with integrative and functional-medicine prescribers.
Limitations to know about:
- Compounded preparations are not U.S. Food and Drug Administration-approved; potency depends entirely on the pharmacy's quality control.
- The "slow release" effect is real but variable — some preparations release faster than labeled.
- Cost runs $30–$80 per month; rarely covered by insurance.
- Accreditation by the Pharmacy Compounding Accreditation Board (PCAB) and third-party potency testing of the finished product are the quality signals patients and prescribers look for.
Evidence Review — What the Trials Show
After about 14 to 18 trials over three decades (fourteen counted by the 2021 consensus document of the American, British and European thyroid associations, eighteen studies in a 2021 meta-analysis), the summary:
- Standard biochemical outcomes (thyroid-stimulating hormone, free T4, free T3) are achievable on T4 alone for most patients.
- When trials use only serum markers as the endpoint, combination therapy rarely beats T4 alone.
- When trials measure patient-reported outcomes on questionnaires, a 2021 meta-analysis of 18 studies found no difference between combination therapy and levothyroxine alone in clinical status, quality of life, psychological distress, depressive symptoms or fatigue.
- When patients are asked which treatment they prefer, many choose combination therapy. A 2019 meta-analysis of 7 blinded trials (348 people) found 46.2% preferred combination therapy, a figure not distinguishable from chance, and preference rose with the daily liothyronine dose. The 2021 meta-analysis found 43% preferred combination therapy, 23% levothyroxine alone and 30% had no preference. A 2025 network meta-analysis of 11 randomized trials (1,135 patients) found 52% preferred levothyroxine plus liothyronine or desiccated thyroid, 24% levothyroxine alone and 24% had no preference (relative risk 2.20, 95% confidence interval 1.38–3.52).
- A 2021 three-arm blinded trial in 75 people compared levothyroxine, levothyroxine plus liothyronine, and desiccated thyroid for 22 weeks each. On average there was no difference in symptoms, quality of life, memory or mood, and treatment preference did not differ; desiccated thyroid raised heart rate slightly. The third of patients who felt worst on levothyroxine preferred, and scored better on, the T3-containing treatments.
- The 2021 consensus document of the American, British and European thyroid associations found that fourteen trials had not shown a consistent benefit of combination therapy, judged that a new trial was justified, and agreed unanimously that future trials need to be large enough to study deiodinase and thyroid hormone transporter gene variants.
- No trial to date has demonstrated harm from properly titrated combination therapy in non-elderly, non-cardiac patients.
The mismatch between biochemistry and lived experience is the entire story. If you measure only blood, combination therapy looks unnecessary. If you measure how people feel, a meaningful minority benefit.
DIO2 Polymorphism Testing
The DIO2 rs225014 variant (Thr92Ala) is not part of any standard clinical lab panel, but it sits in the raw data of every consumer genetic test. People who have results from a consumer DNA test can:
- Download the raw data from the testing company's website (account settings → download raw data).
- Upload it to a raw-data interpretation tool, or search the raw-data file directly for "rs225014."
- Read the genotype: T/T (reference, efficient conversion), T/C (heterozygous carrier), C/C (homozygous, slower conversion — the clinically interesting group).
In the 2009 study of 552 people taking T4 (the Weston Area T4 T3 Study), 16% had the C/C genotype. While on T4 they scored worse on a 12-item well-being questionnaire (the General Health Questionnaire, GHQ-12, where a higher score is worse) than people with T/T (14.1 vs 12.8). On combination T4/T3 their scores improved by 2.3 points more than on T4 alone at 3 months and by 1.4 points more at 12 months, and the variant had no effect on blood thyroid hormone levels. The authors wrote that their results "require replication". Later trials did not confirm it: the 2021 three-arm trial of 75 patients found no influence of this DIO2 variant (Thr92Ala) on outcomes, and in the 2024 LEVOLIO trial the gene variants studied, including this one, did not influence any outcome.
Patients and practitioners who use the test describe it as most relevant for people still symptomatic on T4-only therapy. A C/C result does not predict that a person will feel better on combination therapy — at most it shifts the odds — and some patients bring it to an endocrinologist when asking about a combination trial.
How to Advocate for a Trial
Most U.S. endocrinologists will prescribe T4 monotherapy readily and become visibly reluctant when asked about T3 or NDT. Getting a fair trial requires preparation.
Documenting persistent symptoms. Patients describe keeping a written log for 4–8 weeks (daily energy, cognitive function, mood, weight, body temperature on waking, sleep quality) and bringing it to the appointment. Subjective complaints dismissed verbally carry more weight when you hand over a dated record.
Knowing the numbers. Patients bring recent thyroid-stimulating hormone, free T4, free T3, and reverse T3 values. If free T3 sits in the bottom quartile of the reference range on T4-only therapy, that is a legitimate pharmacologic reason to consider adding T3.
A specific request. Patients and patient advocates describe a concrete, time-limited request, for example: "I'd like a 12-week trial of combination T4+T3 therapy. I've read the published trials on combination therapy and I understand it may not help, but given my persistent symptoms and free T3 in the low-normal range, I think it's worth testing. Can we reduce my levothyroxine by 25 mcg and add liothyronine 5 mcg daily?" A concrete, time-limited request is harder to refuse than an open-ended complaint.
Other clinicians. When one clinician declines, patients describe turning to functional or integrative medicine MDs, osteopathic physicians (DOs) with endocrine interest, and some naturopathic doctors (licensed in many but not all states). A direct-primary-care clinician often has more flexibility than an insurance-contracted endocrinologist. Out-of-pocket costs run about $150–$400 for an initial consult and $75–$200 for follow-ups. The liothyronine or NDT prescription itself is usually covered by insurance even if the visit is not.
Compounded T4+T3 Slow-Release
Compounding pharmacies can also make combined T4+T3 capsules at any ratio, with T3 formulated for sustained release. This eliminates the two-pill regimen and flattens the T3 peak in one step. A typical compounded capsule might contain 100 mcg T4 plus 7.5 mcg sustained-release T3, taken once in the morning.
Cost is similar to compounded T3 alone ($40–$90 per month). The same caveats apply: PCAB accreditation, potency testing, and a consistent formulation once one works are what patients look for. Switching compounding pharmacies mid-therapy resets the clock.
Side Effects and Cardiac Safety
Any T3-containing regimen can push a person into mild hyperthyroidism faster than pure T4 therapy. The signs include:
- Resting heart rate rising more than 10 beats per minute above baseline.
- Palpitations, especially in the afternoon 3–4 hours after a T3 dose.
- Fine tremor in the outstretched hands.
- New or worsened anxiety, jitteriness, insomnia.
- Unintended weight loss.
- Heat intolerance and excess sweating.
In patients over 60 and anyone with coronary artery disease, atrial fibrillation history, or significant osteoporosis risk, T3 adds real cardiovascular and skeletal risk. Some prescribers take a baseline electrocardiogram (ECG) before starting, and some monitor bone density every two years on long-term T3.
A 2025 review of 21 randomized trials (2,128 people) found a similar risk of side effects with combination therapy and with levothyroxine alone (relative risk 1.22, 95% confidence interval 0.66–2.25). Combined cohort data on 630,254 people showed no increased risk of atrial fibrillation, heart failure or stroke in liothyronine users compared with levothyroxine-only users, and a lower death rate among liothyronine users (relative risk 0.70) in these observational data. Side effects blamed on liothyronine were reported only with unregulated liothyronine use or pharmacy compounding errors.
Pregnancy. The placenta actively metabolizes T3 and preferentially delivers T4 to the fetus, whose own thyroid produces T4 in the second and third trimesters. The 2017 American Thyroid Association pregnancy guideline names levothyroxine alone as the treatment in pregnancy, so T3 is usually tapered off and replaced with pure T4 before conception or at the first positive pregnancy test. Dose requirements rise by roughly 25–30% during pregnancy; the guideline describes raising the levothyroxine dose as soon as pregnancy is confirmed and re-testing thyroid-stimulating hormone about every 4 weeks. See the pregnancy and Hashimoto's article for the full protocol.
Practical Tips for Any Regimen
- Consistent timing. One fixed time (morning fasting, or bedtime three hours post-meal) keeps absorption steady. Day-to-day variation in timing creates day-to-day variation in absorption.
- Empty stomach. Coffee, milk, calcium, iron, and fiber all reduce absorption; the usual spacing is at least four hours.
- One manufacturer. Patients on levo, NDT, or combination therapy describe steadier results when the manufacturer stays the same across refills.
- Storage. Thyroid medication keeps best in its original container, away from heat, humidity, and direct light; a bathroom medicine cabinet is humid, a bedroom drawer is not.
- Tracking results. A simple spreadsheet of date, dose, thyroid-stimulating hormone, free T4 and free T3 at every blood draw reveals trends that a single abnormal value does not.
- Re-testing at 6–8 weeks after any change — new dose, new manufacturer, new product, added or removed T3 — is the usual practice.
When to Reconsider Thyroid as the Problem
If you have optimized thyroid-stimulating hormone to 1–2, pushed free T4 into the upper half of the range, raised free T3 into the upper half as well — and still feel unwell — the thyroid regimen is probably not the limiting factor. Other causes worth investigating:
- Iron deficiency. Serum ferritin under 70 ng/mL is a common and underdiagnosed driver of fatigue even when hemoglobin is normal. See the selenium, zinc, iron, iodine article.
- Vitamin B12. Levels under 400 pg/mL can cause fatigue and cognitive symptoms that mimic hypothyroidism.
- Adrenal dysregulation and chronic stress. Cortisol-driven fatigue is not fixed by thyroid hormone.
- Sleep apnea. Surprisingly common in Hashimoto's patients, particularly those who have gained weight; a home sleep study is low-friction and often diagnostic.
- Perimenopause. Overlapping fatigue, brain fog, and weight changes. Hormone assessment is worthwhile in women 40 and up.
- Postural orthostatic tachycardia syndrome (POTS), mast cell activation syndrome (MCAS), dysautonomia. Overlap with Hashimoto's is well documented. See the postural orthostatic tachycardia syndrome/mast cell activation syndrome overlap article.
- Depression. A separate condition with real overlap, worth assessing and treating in its own right.
Thyroid hormone is powerful but not a panacea. When the numbers are right and the symptoms remain, the cause often lies outside the thyroid, and more thyroid medication does not address it.
Key Research Papers
Foundational and recent peer-reviewed publications on monotherapy levothyroxine, T4+T3 combination therapy, desiccated thyroid extract, the DIO2 polymorphism, and the patient-reported quality-of-life literature. Each citation links to the full text via DOI.
- Jonklaas J, Bianco AC, Bauer AJ, et al. Guidelines for the Treatment of Hypothyroidism (American Thyroid Association). Thyroid. 2014;24(12):1670–1751. — doi:10.1089/thy.2014.0028
- Bunevicius R, Kazanavicius G, Zalinkevicius R, Prange AJ Jr. Effects of Thyroxine as Compared with Thyroxine plus Triiodothyronine in Patients with Hypothyroidism. New England Journal of Medicine. 1999;340(6):424–429. — doi:10.1056/NEJM199902113400603
- Hoang TD, Olsen CH, Mai VQ, Clyde PW, Shakir MK. Desiccated Thyroid Extract Compared with Levothyroxine in the Treatment of Hypothyroidism: A Randomized, Double-Blind, Crossover Study. Journal of Clinical Endocrinology & Metabolism. 2013;98(5):1982–1990. — doi:10.1210/jc.2012-4107
- Wiersinga WM, Duntas L, Fadeyev V, Nygaard B, Vanderpump MPJ. 2012 ETA Guidelines: The Use of L-T4 + L-T3 in the Treatment of Hypothyroidism. European Thyroid Journal. 2012;1(2):55–71. — doi:10.1159/000339444
- Panicker V, Saravanan P, Vaidya B, et al. Common Variation in the DIO2 Gene Predicts Baseline Psychological Well-Being and Response to Combination Thyroxine plus Triiodothyronine Therapy in Hypothyroid Patients. Journal of Clinical Endocrinology & Metabolism. 2009;94(5):1623–1629. — doi:10.1210/jc.2008-1301
- Saravanan P, Chau WF, Roberts N, Vedhara K, Greenwood R, Dayan CM. Psychological Well-Being in Patients on "Adequate" Doses of L-Thyroxine: Results of a Large, Controlled Community-Based Questionnaire Study. Clinical Endocrinology. 2002;57(5):577–585. — doi:10.1046/j.1365-2265.2002.01654.x
- Hoermann R, Midgley JEM, Larisch R, Dietrich JW. Recent Advances in Thyroid Hormone Regulation: Toward a New Paradigm for Optimal Diagnosis and Treatment. Frontiers in Endocrinology. 2017;8:364. — doi:10.3389/fendo.2017.00364
- Peterson SJ, Cappola AR, Castro MR, et al. An Online Survey of Hypothyroid Patients Demonstrates Prominent Dissatisfaction. Thyroid. 2018;28(6):707–721. — doi:10.1089/thy.2017.0681
- Wartofsky L, Dickey RA. The Evidence for a Narrower Thyrotropin Reference Range Is Compelling. Journal of Clinical Endocrinology & Metabolism. 2005;90(9):5483–5488. — doi:10.1210/jc.2005-0455
- Surks MI, Goswami G, Daniels GH. The Thyrotropin Reference Range Should Remain Unchanged. Journal of Clinical Endocrinology & Metabolism. 2005;90(9):5489–5496. — doi:10.1210/jc.2005-0170
- Centanni M, Gargano L, Canettieri G, et al. Thyroxine in Goiter, Helicobacter pylori Infection, and Chronic Gastritis. New England Journal of Medicine. 2006;354(17):1787–1795. — doi:10.1056/NEJMoa043903
- Caturegli P, De Remigis A, Rose NR. Hashimoto Thyroiditis: Clinical and Diagnostic Criteria. Autoimmunity Reviews. 2014;13(4-5):391–397. — doi:10.1016/j.autrev.2014.01.007
- Akirov A, Fazelzad R, Ezzat S, et al. A Systematic Review and Meta-Analysis of Patient Preferences for Combination Thyroid Hormone Treatment for Hypothyroidism. Frontiers in Endocrinology. 2019;10:477. — doi:10.3389/fendo.2019.00477
- Jonklaas J, Bianco AC, Cappola AR, et al. Evidence-Based Use of Levothyroxine/Liothyronine Combinations in Treating Hypothyroidism: A Consensus Document. Thyroid. 2021;31(2):156–182. — doi:10.1089/thy.2020.0720
- Shakir MKM, Brooks DI, McAninch EA, et al. Comparative Effectiveness of Levothyroxine, Desiccated Thyroid Extract, and Levothyroxine+Liothyronine in Hypothyroidism. Journal of Clinical Endocrinology & Metabolism. 2021;106(11):e4400–e4413. — doi:10.1210/clinem/dgab478
- Millan-Alanis JM, González-González JG, Flores-Rodríguez A, et al. Benefits and Harms of Levothyroxine/L-Triiodothyronine Versus Levothyroxine Monotherapy for Adult Patients with Hypothyroidism: Systematic Review and Meta-Analysis. Thyroid. 2021;31(11):1613–1625. — doi:10.1089/thy.2021.0270
- de Lima Beltrão FE, Carvalhal G, de Almeida Beltrão DC, et al. Treatment Preferences in Patients With Hypothyroidism. Journal of Clinical Endocrinology & Metabolism. 2025;110(3):887–900. — doi:10.1210/clinem/dgae651
- Bahl S, Taylor PN, Premawardhana LD, et al. Risk of Death and Adverse Effects in Patients on Liothyronine: A Multisource Systematic Review and Meta-analysis. Journal of Clinical Endocrinology & Metabolism. 2025;110(11):3278–3288. — doi:10.1210/clinem/dgaf449
- Brigante G, Santi D, Boselli G, et al. Randomized Double-Blind Placebo-Controlled Trial on Levothyroxine and Liothyronine Combination Therapy in Totally Thyroidectomized Subjects: The LEVOLIO Study. European Journal of Endocrinology. 2024;190(1):12–22. — doi:10.1093/ejendo/lvad172
- Centanni M, Duntas L, Feldt-Rasmussen U, et al. ETA Guidelines for the Use of Levothyroxine Sodium Preparations in Monotherapy to Optimize the Treatment of Hypothyroidism. European Thyroid Journal. 2025;14(4):e250123. — doi:10.1530/ETJ-25-0123
- Alexander EK, Pearce EN, Brent GA, et al. 2017 Guidelines of the American Thyroid Association for the Diagnosis and Management of Thyroid Disease During Pregnancy and the Postpartum. Thyroid. 2017;27(3):315–389. — doi:10.1089/thy.2016.0457
PubMed Topic Searches
Live PubMed queries that update as new papers are indexed.
Connections
- Endocrinology
- How Your Thyroid Is Controlled — interactive animation
- Hashimoto's Thyroiditis Overview
- Pregnancy and Hashimoto's
- Selenium, Zinc, Iron, and Iodine
- Thyroid-Stimulating Hormone, T4, and T3 Optimal Ranges
- AIP and Gluten Elimination
- TPO and TgAb Antibodies
- Reverse T3 and Low T3 Syndrome
- Hashimoto, Postural Orthostatic Tachycardia Syndrome, and Mast Cell Activation Syndrome Overlap
- Gut-Thyroid Axis and Intestinal Permeability
- Thyroid Disorders
- Selenium
- Iron
- Zinc
- Iodine
- Magnesium
- Celiac Disease
- Fatigue
- Thyroid Panel