⚠ Evidence warning: Clinical trials or other evidence do not support the claims that Hashimoto's patients feel best with a thyroid-stimulating hormone of 0.5 to 2.5 and free T4 and free T3 in the upper third of the range, and the free T3 to reverse T3 ratio target above 20. This page keeps it as a report of what people, websites or other media say.
Thyroid-Stimulating Hormone (TSH), Free T4, Free T3 Optimal Ranges
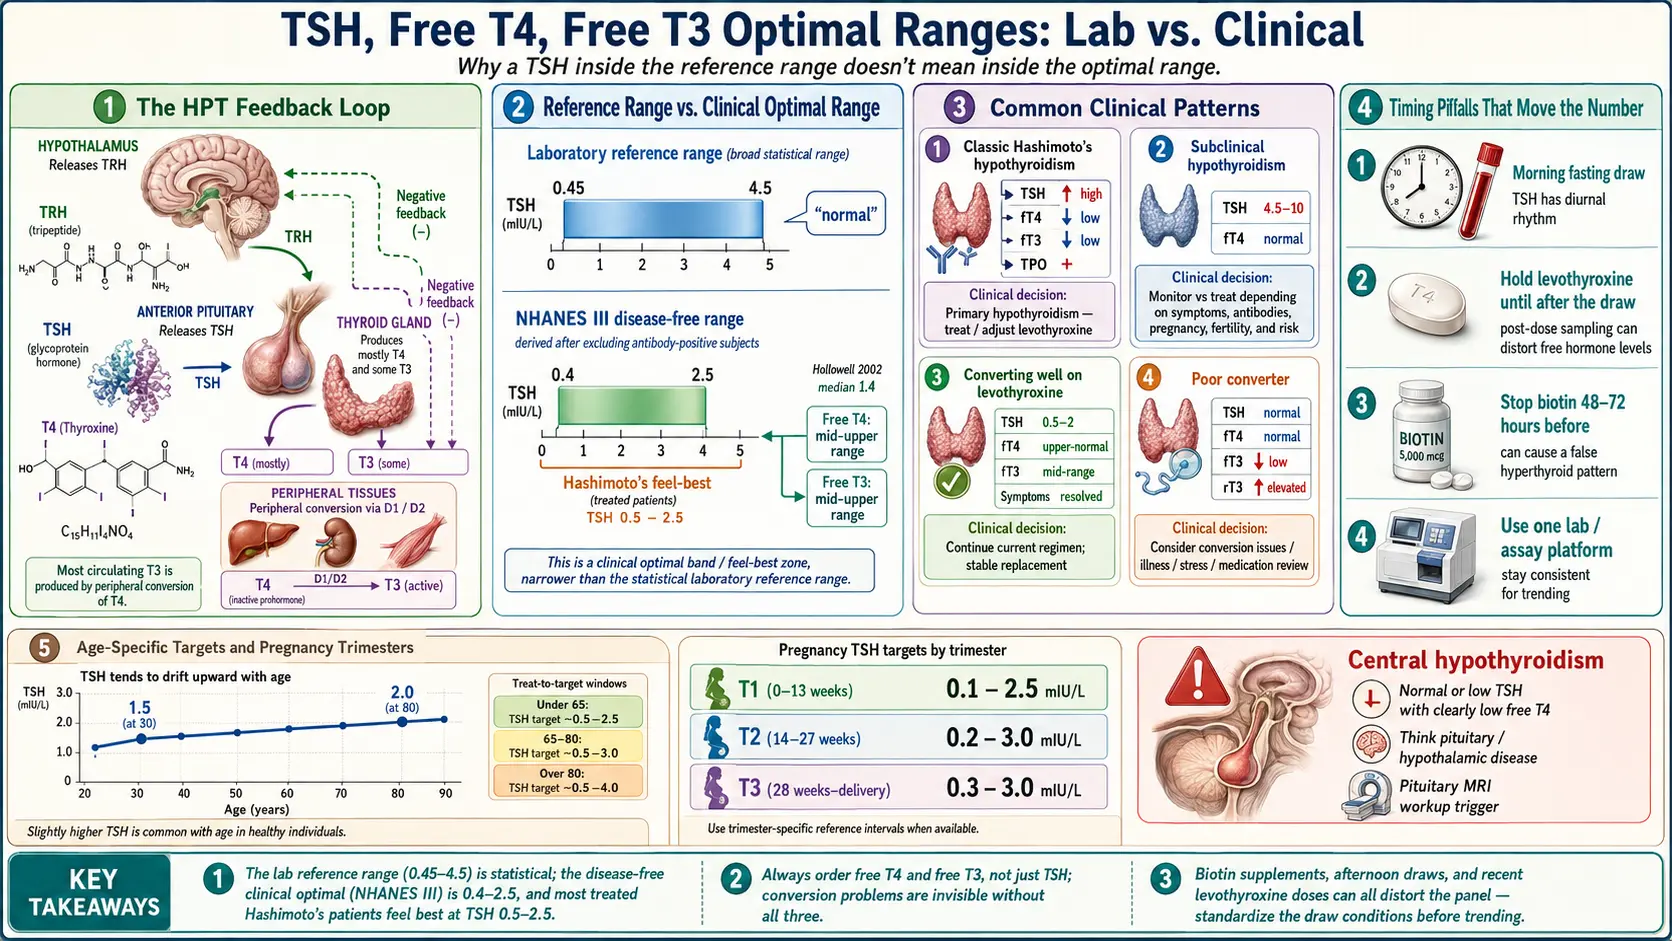
Table of Contents
- How Thyroid-Stimulating Hormone Works — The Pituitary Feedback Loop
- The Lab Reference Range vs. the Clinical "Optimal" Range
- Where Hashimoto's Patients Tend to Feel Best
- Free T4 — The Storage Hormone
- Free T3 — The Active Hormone at the Cell
- Reverse T3 and the fT3:rT3 Ratio
- TPO and TgAb — Always at Baseline
- The Full Thyroid Panel
- Common Clinical Patterns
- Timing of Blood Draws — Details That Move the Number
- Pharmacy and Lab Differences
- Age-Specific Ranges
- Gender and Lifecycle
- When to Suspect Central Hypothyroidism
- How to Advocate for the Full Panel
- Home Testing Options
- Key Research Papers
- Connections
- Featured Videos
How Thyroid-Stimulating Hormone Works — The Pituitary Feedback Loop
Thyroid-stimulating hormone (TSH) is not made by your thyroid. It is made by your pituitary gland, a pea-sized organ tucked at the base of your brain. The pituitary acts as a thermostat. It constantly samples the level of thyroid hormone floating in your blood, compares it to a set point, and dials its output of thyroid-stimulating hormone up or down to keep the level steady.
The loop runs like this. Your hypothalamus releases TRH (thyrotropin-releasing hormone), which tells the pituitary to release thyroid-stimulating hormone. Thyroid-stimulating hormone then travels to the thyroid and stimulates it to produce T4 (mostly) and T3 (a little). When T4 and T3 levels rise, they loop back and suppress TRH and thyroid-stimulating hormone release. When thyroid hormone drops, TRH and thyroid-stimulating hormone rise. A falling thyroid pushes thyroid-stimulating hormone up; a rising thyroid pulls thyroid-stimulating hormone down.
That is why thyroid-stimulating hormone is the first test doctors order. It is a proxy for how your pituitary perceives your thyroid status. A high thyroid-stimulating hormone means the pituitary is shouting at a slow thyroid. A low thyroid-stimulating hormone means the pituitary is telling a hot thyroid to quiet down. But proxies can mislead. Thyroid-stimulating hormone reflects what the pituitary sees, not necessarily what every cell in your body feels.
The Lab Reference Range vs. the Clinical "Optimal" Range
Open any lab report and thyroid-stimulating hormone will usually have a reference range of roughly 0.45 to 4.5 mIU/L. Anything inside is flagged as "normal." Anything outside is flagged as abnormal. This simple binary is the source of more frustrated Hashimoto's patients than almost any other single fact in medicine.
Reference ranges are statistical, not biological. A lab takes a sample of "apparently healthy" people, measures their thyroid-stimulating hormone, and reports the middle 95%. That is it. The problem: the reference population is usually not screened for thyroid autoimmunity. Undiagnosed Hashimoto's patients end up inside the reference cohort, widening the "normal" range upward.
In 2002, the landmark analysis of the third National Health and Nutrition Examination Survey (NHANES III) by Hollowell and colleagues measured thyroid-stimulating hormone in 17,353 Americans. Among the 16,533 who did not report thyroid disease, goiter or thyroid medication (the "disease-free" population), the mean was 1.50 mIU/L. The researchers then selected a reference population of 13,344 people by also excluding those who were pregnant, taking androgens or estrogens, had thyroid antibodies, or had biochemical hypothyroidism or hyperthyroidism. In that group the geometric mean thyroid-stimulating hormone was 1.40 mIU/L, rising with age, and it was lower in Black Americans (1.18) than in white Americans (1.45).
The 2.5 cut-off comes from a different source. Laboratory guidelines from the National Academy of Clinical Biochemistry state that more than 95% of normal individuals have a thyroid-stimulating hormone below 2.5 mIU/L. In a 2005 review, Wartofsky and Dickey argued that most people above that value are likely to have underlying Hashimoto's thyroiditis or another cause of raised thyroid-stimulating hormone, and that the 1.18 mean in Black Americans, who rarely have Hashimoto's, is the true normal mean. In the same journal issue, Surks and colleagues argued the opposite: that the thyrotropin (thyroid-stimulating hormone) reference range should remain unchanged.
This is why many endocrinologists and functional-medicine practitioners distinguish between the laboratory reference range (statistical, 0.45–4.5) and the clinical optimal range (what healthy people without autoimmunity actually show, roughly 0.4–2.5). When your thyroid-stimulating hormone is 3.8 and your doctor says "normal," both of you can be right and wrong at the same time.
Where Hashimoto's Patients Tend to Feel Best
Symptom studies and clinical observation converge on a narrower window for treated Hashimoto's patients:
- Thyroid-stimulating hormone: 0.5–2.5 mIU/L — most patients on levothyroxine report best energy, mood, cognition, and menstrual regularity in this band.
- Free T4: mid-to-upper third of the reference range.
- Free T3: mid-to-upper third of the reference range.
These are not regulatory targets. The American Thyroid Association's 2014 guideline for adult hypothyroidism accepts a thyroid-stimulating hormone anywhere inside the laboratory reference range as adequate. The narrower "feel best" band is an observation from people who live in their own bodies and report how those bodies function at different numbers. Patients and clinicians who use it treat it as a hypothesis to test together, not as grounds to demand medication changes.
Free T4 — The Storage Hormone
Total T4 in your blood is mostly bound to carrier proteins (thyroxine-binding globulin, transthyretin, albumin). Bound hormone is biologically inert. Only the small unbound fraction — free T4 — can enter cells, be converted to T3, and do work. Free T4 is the measurement that matters.
Typical reference ranges are 0.8 to 1.8 ng/dL (sometimes reported as 10–23 pmol/L), though labs vary. Many clinicians treating Hashimoto's aim for a free T4 in the 1.2 to 1.6 ng/dL zone — comfortably mid-to-upper range, not suppressed.
Free T4 is the steadier of the active hormones. It has a long half-life (about a week), so day-to-day fluctuation is small. It is your storage pool. Conversion enzymes in the liver, kidney, muscle, and brain take T4 and remove one iodine atom to make T3, the active form. A low free T4 means the storage tank is low; a mid-to-upper free T4 means your cells have something to work with.
Free T3 — The Active Hormone at the Cell
T3 is the hormone that actually binds the thyroid hormone receptor inside your cells and switches on the genes that govern metabolism. It is three to four times more potent than T4. Of the T3 in your bloodstream, roughly 80% is made outside the thyroid by enzymatic conversion of T4; the thyroid itself produces only a fraction directly.
Typical reference ranges are 2.3 to 4.2 pg/mL (3.5–6.5 pmol/L). A clinical target often cited for symptomatic patients is 3.2 to 3.8 pg/mL — upper-middle of the range.
Free T3 has a short half-life (roughly a day) and fluctuates more than free T4. It is also the most likely test to reveal a conversion problem: a patient on enough levothyroxine to produce a pretty free T4 but whose deiodinase enzymes are not efficiently turning T4 into T3. The thyroid-stimulating hormone and free T4 look textbook, the patient still feels cold, tired, foggy, and constipated — and free T3 is sitting near the bottom of its range. Without that third number, the conversion problem is invisible.
Reverse T3 and the fT3:rT3 Ratio
T4 can be deiodinated in two ways. Removing one iodine from the outer ring yields active T3. Removing one from the inner ring yields reverse T3 (rT3), a structural mirror image that binds the receptor without activating it. Reverse T3 is a natural brake — a way for the body to throttle metabolism during stress, starvation, severe illness, trauma, and intense caloric restriction.
A high rT3 is generally not a thyroid problem; it is a signal of systemic stress. Common drivers include chronic infection, prolonged caloric deficit, over-training, sleep deprivation, cortisol excess, liver disease, and critical illness. Many practitioners use the free T3 to reverse T3 ratio as a rough indicator of conversion health, targeting a ratio above 20 (when free T3 is in pg/mL and reverse T3 in ng/dL). Mainstream endocrinology considers this ratio controversial — assay standardization is poor and prospective outcome data are thin — but the test is cheap, so many patients order it once to rule out a gross problem.
For a deeper treatment of rT3 biology, low-T3 syndrome, and non-thyroidal illness, see the Reverse T3 article.
TPO and TgAb — Always at Baseline
Anti-thyroid peroxidase (TPO) and anti-thyroglobulin (TgAb) antibodies are the immunologic fingerprint of Hashimoto's disease. TPO is positive in about 90% of Hashimoto's cases; TgAb is positive in about 60–80%. Together they catch almost everyone. These belong on every initial thyroid workup, because a "normal thyroid-stimulating hormone" in an antibody-positive person carries very different implications from a normal thyroid-stimulating hormone in an antibody-negative person.
For how to interpret antibody titers, trend them over time, and use them to track disease activity, see the sibling article on TPO and TgAb antibodies.
The Full Thyroid Panel
The full panel at baseline, ideally drawn before any thyroid medication is started:
- Thyroid-stimulating hormone — pituitary signal.
- Free T4 — active, unbound storage hormone.
- Free T3 — active hormone at the cell.
- Reverse T3 — conversion brake; useful once to rule out a gross problem.
- TPO antibodies — autoimmune fingerprint.
- Thyroglobulin antibodies (TgAb) — the other autoimmune fingerprint.
Once a person is on therapy and stable, the typical follow-up set is thyroid-stimulating hormone, free T4, and free T3, drawn every 6–8 weeks after a dose change and every 6–12 months once stable. Antibodies and reverse T3 are usually not repeated at every visit; once or twice a year is typical unless something changes clinically.
Common Clinical Patterns
The same set of numbers tells different stories depending on how they move together. A few recurring patterns:
Classic Hashimoto's hypothyroidism. Thyroid-stimulating hormone elevated (often >4.5), free T4 low or low-normal, free T3 low or low-normal, TPO strongly positive. Clear diagnosis; levothyroxine is the first-line response.
Subclinical hypothyroidism. Thyroid-stimulating hormone 4.5–10, free T4 still inside the reference range, symptoms variable. Treatment is debated. Most guidelines recommend treating if thyroid-stimulating hormone is above 10, if the patient is pregnant or trying to conceive, if symptoms are disabling, or if antibodies are positive and thyroid-stimulating hormone is trending upward. Otherwise, watchful monitoring every 6–12 months is acceptable.
Converting well on levothyroxine. Thyroid-stimulating hormone 0.5–2, free T4 upper-normal, free T3 mid-range, symptoms resolved. This is the outcome most patients and clinicians are aiming for.
Poor converter. Thyroid-stimulating hormone normal, free T4 normal or high-normal, free T3 low, sometimes rT3 elevated. The patient still has cold hands, stubborn weight, fatigue, and brain fog. This is the pattern that drives the clinical conversation about adding T3 (liothyronine) or switching to natural desiccated thyroid — see the levothyroxine vs NDT vs T3 article.
Thyroid hormone resistance or treatment failure. Numbers look optimal by every yardstick and the patient still feels unwell. Before resistance is concluded, the usual causes to rule out are iron deficiency, ferritin below 50, low vitamin D, B12 deficiency, sleep apnea, depression, perimenopause, adrenal insufficiency, and the postural orthostatic tachycardia syndrome (POTS)/mast cell activation syndrome (MCAS) overlap syndromes. "Optimal thyroid" is not always the full story.
Timing of Blood Draws — Details That Move the Number
Small procedural details meaningfully shift thyroid numbers. Keeping them the same means a trend reflects real physiology, not noise:
- Morning, fasting draws. Thyroid-stimulating hormone follows a daily rhythm, peaking overnight and hitting its lowest point in the afternoon. An afternoon draw can read a full point lower than a morning one in the same person.
- Levothyroxine taken after the draw. Levothyroxine absorbed hours before a test can transiently spike the free T4 reading and misstate the true baseline, so the usual practice is to take the pill right after blood is drawn.
- Biotin stopped 48–72 hours beforehand. High-dose biotin (commonly 5,000–10,000 mcg in hair/skin/nail supplements) interferes with many immunoassay platforms and can artifactually lower thyroid-stimulating hormone and raise free T4 and free T3 — mimicking hyperthyroidism on paper. This is a famous real-world source of misdiagnosis.
- Consistency. Draws at about the same time of day, under the same fasting conditions, relative to the same medication timing. Trending requires reproducibility.
Pharmacy and Lab Differences
Not all labs run the same assay. Free T3, free T4, and especially reverse T3 are measured on different analyzer platforms (from several analyzer makers, plus liquid chromatography-tandem mass spectrometry (LC-MS/MS) reference methods) with subtly different reference ranges and calibrations. A free T3 of 3.2 pg/mL at one national lab chain is not numerically identical to a 3.2 at another.
The practical rule patients and clinicians use: the same lab for every draw that will be trended. Switching labs midstream introduces noise that can look like disease activity when nothing has changed.
Pharmacy also matters. Levothyroxine products (brand-name tablets, a soft-gel capsule, and generics) are not truly bioequivalent for everyone, despite U.S. Food and Drug Administration (FDA) labeling. When a person is stabilized on one product and the pharmacy silently substitutes another, the numbers can drift. A prescription marked "dispense as written" keeps the pharmacy on one manufacturer.
Age-Specific Ranges
The thyroid-stimulating hormone upper limit drifts upward with age. In the U.S. national survey, among people without thyroid disease, 10.6% of 20- to 29-year-olds had a thyroid-stimulating hormone above 2.5 mIU/L, rising to 40% of people aged 80 and over, 14.5% of whom were above 4.5. The 97.5th percentile (the cut-off for the top 2.5%) rose from 3.56 mIU/L at ages 20–29 to 7.49 mIU/L at 80 and over. Seventy percent of older people with a thyroid-stimulating hormone above 4.5 were within the normal range for their age, so the authors concluded that "subclinical hypothyroidism" may be significantly overcounted unless an age-specific range is used. Treating an 80-year-old to a thyroid-stimulating hormone of 1 may cause more harm (atrial fibrillation, bone loss) than benefit.
Rough age targets many geriatricians describe:
- Adults under 65: a thyroid-stimulating hormone of 0.5–2.5.
- Ages 65–80: a thyroid-stimulating hormone of roughly 1–4.
- Over 80: a thyroid-stimulating hormone of 4–7 may be physiologic and well-tolerated.
At the other end, infants and children have higher thyroid-stimulating hormone set points than adults and are measured against pediatric-specific ranges.
Gender and Lifecycle
Sex per se does not shift reference ranges much, but lifecycle events do. Estrogen raises thyroxine-binding globulin, which increases total T4 without changing free T4 — one of several reasons total T4 is not a useful test anymore.
Pregnancy imposes much tighter targets because fetal brain development depends on maternal thyroid hormone, especially in the first trimester before the fetal thyroid is active. The 2011 American Thyroid Association and 2012 Endocrine Society guidelines set thyroid-stimulating hormone limits of 0.1–2.5 in the first trimester, 0.2–3.0 in the second and 0.3–3.0 in the third. The 2017 American Thyroid Association pregnancy guideline replaced these fixed limits with a pregnancy-specific range from the local population; when no such range is available, the revised upper limit is about 0.5 mIU/L below the non-pregnant value, or 4.0 mIU/L. Free T4 is often kept in the upper half of a trimester-specific range. Pre-conception counseling and medication adjustment at the positive pregnancy test are standard. See Pregnancy and Hashimoto's for the full protocol.
Menopause can unmask or aggravate Hashimoto's. Many women first receive a diagnosis in the perimenopausal window because symptom overlap (fatigue, weight gain, brain fog, hair thinning, mood shifts) triggers the lab workup that finally catches the antibodies.
When to Suspect Central Hypothyroidism
Primary hypothyroidism is thyroid failure: the thyroid is dying, so thyroid hormones fall and thyroid-stimulating hormone climbs. Central hypothyroidism is pituitary failure: the pituitary cannot produce thyroid-stimulating hormone, so despite a starving thyroid, thyroid-stimulating hormone stays normal or even low. Free T4 and free T3 fall anyway, because the signal to the thyroid is missing.
It is rare but regularly missed, because the reflex "thyroid-stimulating hormone is normal, you are fine" habit blinds clinicians to a low free T4. Clues that point to central hypothyroidism:
- Thyroid-stimulating hormone is normal or low but free T4 is clearly below range.
- A history of pituitary surgery, radiation, head trauma, or postpartum hemorrhage with severe blood loss (Sheehan syndrome).
- Other pituitary hormone deficiencies are present — low cortisol, low sex hormones, diabetes insipidus.
- Mass-effect symptoms: new headaches, visual field changes.
Workup includes pituitary magnetic resonance imaging (MRI) and a full anterior-pituitary hormone screen. This is one of the strongest reasons to always look at free T4 alongside thyroid-stimulating hormone, rather than stopping at thyroid-stimulating hormone alone.
How to Advocate for the Full Panel
Many primary care offices run only thyroid-stimulating hormone, sometimes with reflex free T4. Getting free T3, reverse T3, and antibodies often requires specifically asking. Requests patients describe using:
- "Would you order a full thyroid panel including free T3 and reverse T3? I want to see conversion, not just thyroid-stimulating hormone."
- "I have Hashimoto's disease, so my antibodies confirm I have an autoimmune thyroid condition. I would like my thyroid-stimulating hormone, free T4, and free T3 checked together so we can see the whole picture."
- "I understand thyroid-stimulating hormone is usually sufficient for screening. I am asking for the full panel because I am still symptomatic and want to rule out a conversion issue before I assume nothing is wrong."
When insurance pushes back on reverse T3, the cash price is usually low ($30–60 at most labs). Antibody testing is almost always covered once at baseline.
When a clinician declines, patients describe three options: asking again at the next visit with more specifics about symptoms, a second opinion from an endocrinologist or functional-medicine physician, or direct-to-consumer testing with the results brought to the next appointment.
Home Testing Options
Direct-to-consumer thyroid testing has become reliable and affordable in the last decade. Two kinds of service exist in the United States:
- Mail-in finger-stick kits — at-home finger-stick thyroid panels (thyroid-stimulating hormone, free T4, free T3, TPO), some with optional physician consultation, processed in laboratories certified under the Clinical Laboratory Improvement Amendments (CLIA).
- Direct-to-consumer laboratory ordering services — standard venous draws ordered online and drawn at a local commercial draw station without a physician's order, in most U.S. states. Typically the cheapest way to get a full panel including reverse T3.
Two caveats. First, finger-stick capillary assays are accurate but can differ slightly from venous assays — trends are cleanest when one method is used throughout. Second, home testing gives data, not treatment. A full panel with abnormal numbers is a starting point for a conversation with a licensed prescriber, not a do-it-yourself prescription.
Becoming lab-literate is a form of self-advocacy. You are not trying to replace your doctor; you are trying to arrive at the appointment with enough understanding to ask the right questions, interpret the answers, and recognize when "your numbers are normal" is the end of the story or the beginning of it.
Key Research Papers
Foundational and recent peer-reviewed publications on the thyroid-stimulating hormone reference range debate, the clinical utility of free T3, the subclinical-hypothyroidism treatment literature, and the assay-interference issues that complicate panel interpretation. Each citation links to the full text via DOI.
- Hollowell JG, Staehling NW, Flanders WD, et al. Serum TSH, T4, and Thyroid Antibodies in the United States Population (NHANES III). Journal of Clinical Endocrinology & Metabolism. 2002;87(2):489–499. — doi:10.1210/jcem.87.2.8182
- Jonklaas J, Bianco AC, Bauer AJ, et al. Guidelines for the Treatment of Hypothyroidism (American Thyroid Association). Thyroid. 2014;24(12):1670–1751. — doi:10.1089/thy.2014.0028
- Wartofsky L, Dickey RA. The Evidence for a Narrower Thyrotropin Reference Range Is Compelling. Journal of Clinical Endocrinology & Metabolism. 2005;90(9):5483–5488. — doi:10.1210/jc.2005-0455
- Surks MI, Goswami G, Daniels GH. The Thyrotropin Reference Range Should Remain Unchanged. Journal of Clinical Endocrinology & Metabolism. 2005;90(9):5489–5496. — doi:10.1210/jc.2005-0170
- Rodondi N, den Elzen WPJ, Bauer DC, et al. Subclinical Hypothyroidism and the Risk of Coronary Heart Disease and Mortality. JAMA. 2010;304(12):1365–1374. — doi:10.1001/jama.2010.1361
- Razvi S, Shakoor A, Vanderpump M, Weaver JU, Pearce SHS. The Influence of Age on the Relationship Between Subclinical Hypothyroidism and Ischemic Heart Disease: A Metaanalysis. Journal of Clinical Endocrinology & Metabolism. 2008;93(8):2998–3007. — doi:10.1210/jc.2008-0167
- Bunevicius R, Kazanavicius G, Zalinkevicius R, Prange AJ Jr. Effects of Thyroxine as Compared with Thyroxine plus Triiodothyronine in Patients with Hypothyroidism. New England Journal of Medicine. 1999;340(6):424–429. — doi:10.1056/NEJM199902113400603
- Surks MI, Hollowell JG. Age-Specific Distribution of Serum Thyrotropin and Antithyroid Antibodies in the U.S. Population: Implications for the Prevalence of Subclinical Hypothyroidism. Journal of Clinical Endocrinology & Metabolism. 2007;92(12):4575–4582. — doi:10.1210/jc.2007-1499
- Hoermann R, Midgley JEM, Larisch R, Dietrich JW. Recent Advances in Thyroid Hormone Regulation: Toward a New Paradigm for Optimal Diagnosis and Treatment. Frontiers in Endocrinology. 2017;8:364. — doi:10.3389/fendo.2017.00364
- Barbesino G. Misdiagnosis of Graves' Disease with Apparent Severe Hyperthyroidism in a Patient Taking Biotin Megadoses. Thyroid. 2016;26(6):860–863. — doi:10.1089/thy.2015.0664
- Caturegli P, De Remigis A, Rose NR. Hashimoto Thyroiditis: Clinical and Diagnostic Criteria. Autoimmunity Reviews. 2014;13(4-5):391–397. — doi:10.1016/j.autrev.2014.01.007
- Alexander EK, Pearce EN, Brent GA, et al. 2017 Guidelines of the American Thyroid Association for the Diagnosis and Management of Thyroid Disease During Pregnancy and the Postpartum. Thyroid. 2017;27(3):315–389. — doi:10.1089/thy.2016.0457
- Khadilkar S. Thyroid-Stimulating Hormone Values in Pregnancy: Cutoff Controversy Continues? Journal of Obstetrics and Gynaecology of India. 2019;69(5):389–394. — doi:10.1007/s13224-019-01272-w
PubMed Topic Searches
Live PubMed queries that update as new papers are indexed.
Connections
- Endocrinology
- How Your Thyroid Is Controlled — interactive animation
- Levothyroxine vs NDT vs T3
- TPO and TgAb Antibodies
- Reverse T3 and Low T3 Syndrome
- Pregnancy and Hashimoto's
- Hashimoto, Postural Orthostatic Tachycardia Syndrome & Mast Cell Activation Syndrome Overlap
- Thyroid Panel
- AIP and Gluten Elimination
- Selenium, Zinc, Iron & Iodine
- Hashimoto's Thyroiditis
- Thyroid Disorders
- Iodine
- Fatigue
- Brain Fog
- Graves' Disease
- Selenium
- Postural Orthostatic Tachycardia Syndrome
- Mast Cell Activation Syndrome
- Gut-Thyroid Axis and Intestinal Permeability