Hashimoto's, Postural Orthostatic Tachycardia Syndrome (POTS) & Mast Cell Activation Syndrome (MCAS) Overlap
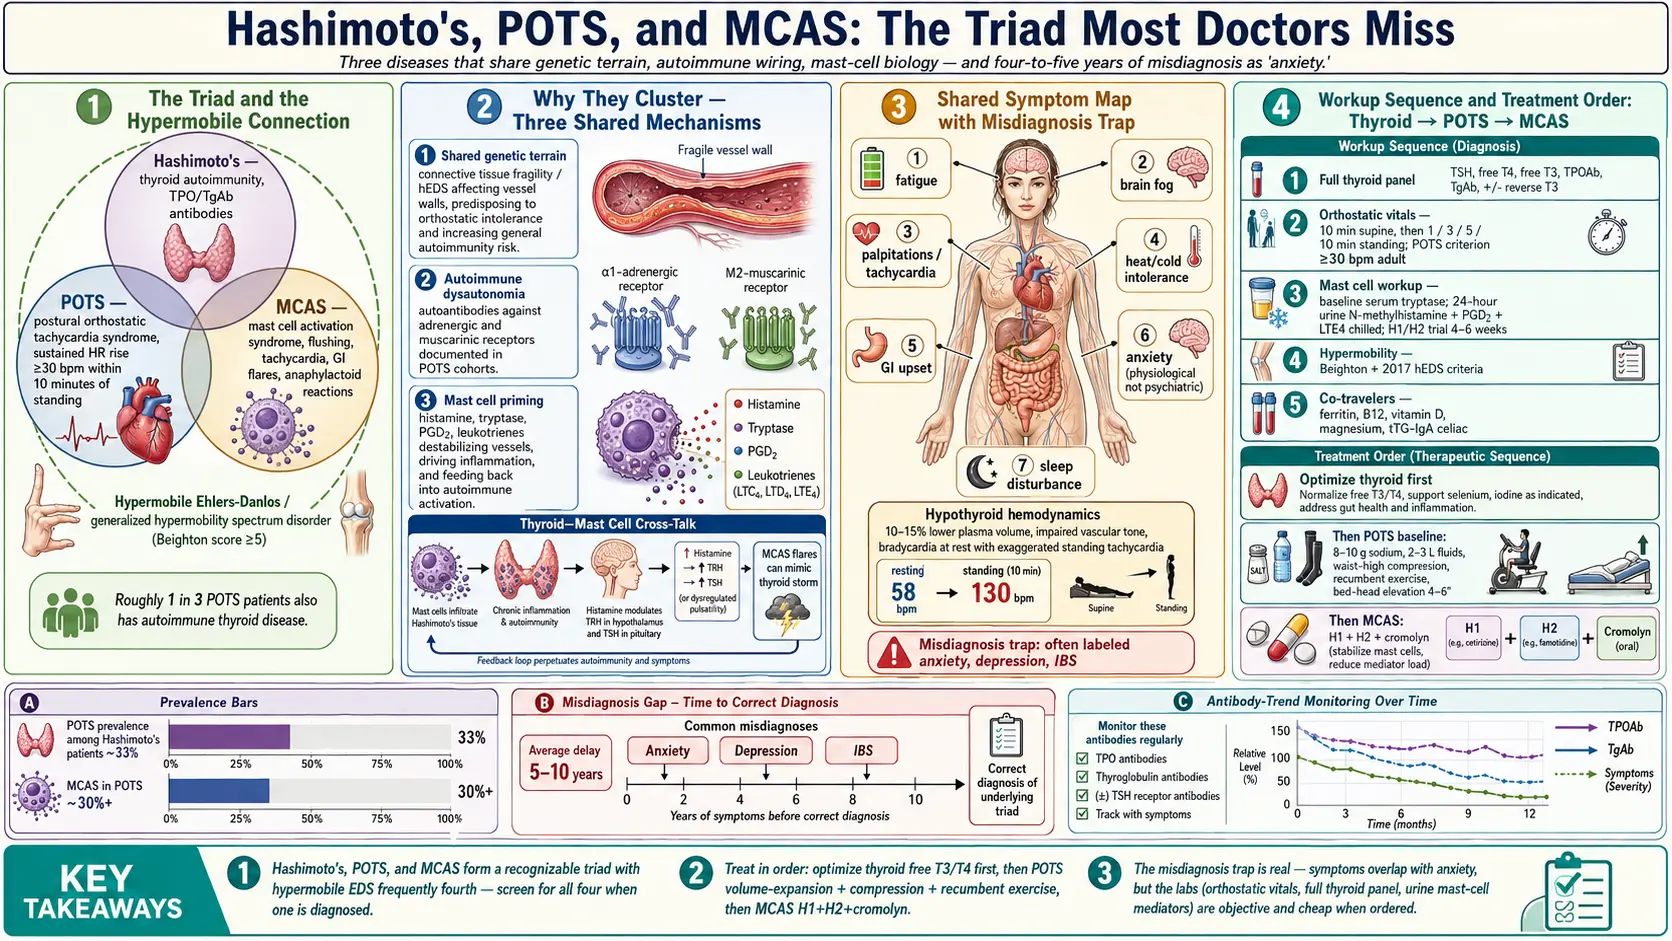
Table of Contents
- Why These Three Cluster Together
- Shared Symptoms That Cause Misdiagnosis
- How Hypothyroidism Mimics and Worsens Postural Orthostatic Tachycardia Syndrome
- Mast Cells, Histamine, and Thyroid Autoimmunity
- Workup Sequence — What to Ask For and In What Order
- Treatment Ordering — Thyroid First, Then Postural Orthostatic Tachycardia Syndrome, Then Mast Cell Activation Syndrome
- Gluten, Histamine, and Iodine — Dietary Landmines
- Practical Self-Monitoring
- When to Push Back on Your Doctor
- Key Research Papers
- Connections
- Featured Videos
Why These Three Cluster Together
If you are a woman in your twenties or thirties, you have been told your labs are "basically normal," and you still feel like your body is falling apart — exhausted, dizzy when you stand up, flushing at random, brain fog you cannot think through — there is a good chance you are not dealing with one disease. You are dealing with three.
Hashimoto's thyroiditis, postural orthostatic tachycardia syndrome (POTS), and mast cell activation syndrome (MCAS) form a recognizable triad. The fourth member that often travels with them is hypermobile Ehlers-Danlos syndrome (hEDS) or generalized hypermobility spectrum disorder. Clinicians who see this overlap regularly — Afrin, Blitshteyn, Shaw, Seneviratne — describe it often. In Blitshteyn's 2015 study of 100 postural orthostatic tachycardia syndrome patients, about one in nine had Hashimoto's thyroiditis and almost one in three had some marker of autoimmunity; these clinicians also report that a majority of hEDS patients will eventually meet criteria for at least two of the four.
Why do they travel together? Three mechanisms tie them:
- Shared genetic terrain. Connective tissue fragility (hEDS) affects blood vessel walls, which predisposes to orthostatic intolerance. The same patients show higher rates of autoimmunity in general, and thyroid autoimmunity in particular.
- Autoimmune dysautonomia. Autoantibodies against adrenergic and muscarinic receptors have been documented in postural orthostatic tachycardia syndrome cohorts. The immune system that attacks thyroid peroxidase is the same immune system that can produce these receptor antibodies.
- Mast cell priming. Mast cells release histamine, tryptase, prostaglandins, and dozens of other mediators that destabilize blood vessels, drive inflammation, and feed back into autoimmune activation. A chronically primed mast cell compartment makes every other system noisier.
The practical takeaway clinicians in this field draw: a diagnosis of one of these three is a reason to look for the other two. Treating Hashimoto's alone will not fix the dizziness. Treating postural orthostatic tachycardia syndrome alone will not fix the flushing. You need the full picture before you can rank the fires.
Shared Symptoms That Cause Misdiagnosis
The reason this triad gets missed for years is that the symptoms overlap almost completely. A patient walks into a primary care office and says: "I'm tired, my heart races, I can't think, I get hot and cold for no reason, and I feel like I'm allergic to everything." The doctor orders a thyroid-stimulating hormone, sees it sitting at 3.8, says "your thyroid is fine," and sends you home with a referral to a therapist.
Here is the overlap map — the symptoms shared by at least two of the three conditions:
- Fatigue — core feature of all three. Hypothyroid fatigue is heavy and cold. Postural orthostatic tachycardia syndrome fatigue is a post-exertional crash after standing or doing chores. Mast cell activation syndrome fatigue often follows a flare, meals, or exposures.
- Brain fog. Hashimoto's slows cognition globally. Postural orthostatic tachycardia syndrome brain fog spikes when upright (cerebral hypoperfusion). Mast cell activation syndrome brain fog tracks with histamine release.
- Palpitations and tachycardia. Thyroid autoimmunity can produce a transient thyrotoxic phase (Hashitoxicosis). Postural orthostatic tachycardia syndrome is defined by a sustained heart-rate rise of 30+ bpm on standing. Mast cell activation syndrome flares release adrenaline-like mediators that speed the heart.
- Heat and cold intolerance. Hypothyroid patients are cold; thyrotoxic ones are hot. Postural orthostatic tachycardia syndrome blunts the autonomic response to temperature. Mast cell activation syndrome flushes and sweats unpredictably.
- Gastrointestinal (GI) upset. Constipation (hypothyroid), gastroparesis (postural orthostatic tachycardia syndrome), diarrhea and cramping (mast cell activation syndrome).
- Anxiety. All three produce genuine physiological anxiety that is indistinguishable from psychiatric anxiety without a workup.
- Sleep disturbance. Night sweats, middle-of-the-night adrenaline surges, non-restorative sleep.
The emotional cost of this overlap is its own problem. Many patients describe years of being told they have anxiety, depression, or "it's stress." In a 2019 survey of 4,835 people with postural orthostatic tachycardia syndrome, the middle (median) wait for a diagnosis was 24 months, and misdiagnosis along the way was common. The symptoms are real. The labs just have not been ordered yet.
How Hypothyroidism Mimics and Worsens Postural Orthostatic Tachycardia Syndrome
Thyroid hormone regulates blood volume, vascular tone, and the sensitivity of your heart to adrenaline. When thyroid hormone is low — or when your labs look normal but the tissue level is actually low — every one of these systems becomes unstable.
The mechanisms:
- Reduced blood volume. Hypothyroid patients run 10–15% lower plasma volume than euthyroid controls. Postural orthostatic tachycardia syndrome is, at its core, a low-blood-volume illness made worse by pooling. Adding hypothyroidism takes an already under-filled circulation and drains it further.
- Impaired vascular tone. Thyroid hormone supports endothelial function and vasoconstriction in the legs. When it drops, blood pools harder when you stand.
- Bradycardia at rest, exaggerated tachycardia on standing. A hypothyroid heart beats slowly when you are horizontal but overshoots when adrenaline takes over in the upright position. This is why patients with untreated Hashimoto's often have a resting pulse of 58 and a standing pulse of 130.
- Cold extremities and Raynaud-like symptoms. Peripheral vasoconstriction conserves heat in hypothyroidism, but it also worsens the hands-and-feet-freezing complaint typical of postural orthostatic tachycardia syndrome.
This is why the first move in any suspected postural orthostatic tachycardia syndrome patient is to nail down the thyroid. Not with a single thyroid-stimulating hormone — which can be in range while free T3 is in the basement — but with a full panel (thyroid-stimulating hormone, free T4, free T3, TPO antibodies, thyroglobulin antibodies, and often reverse T3). See thyroid-stimulating hormone/T4/T3 optimal ranges and Reverse T3 and low-T3 syndrome for the interpretation details.
Mast Cells, Histamine, and Thyroid Autoimmunity
Mast cells are tissue-resident immune cells stationed in skin, gut, airways, and — importantly — the thyroid gland. When they degranulate, they release histamine, tryptase, prostaglandin D2, leukotrienes, heparin, and dozens of cytokines.
Why this matters for Hashimoto's:
- Mast cells infiltrate autoimmune thyroid tissue. Histological studies of Hashimoto's glands consistently show increased mast cell density around the lymphocytic infiltrate.
- Histamine and thyroid function. Histamine affects TRH and thyroid-stimulating hormone release at the hypothalamic-pituitary level. A chronically activated mast cell system feeds into the loop that controls thyroid output.
- Mast cell activation syndrome flares mimic thyroid storm. A severe mast cell flare can produce tachycardia, flushing, hypertension, anxiety, tremor, diarrhea, and a sense of impending doom — the same symptoms as a thyrotoxic crisis. ER workups often find normal thyroid labs and send the patient home with no explanation.
- Patients report that mast cell treatment lowers autoimmune noise. Patients on H1/H2 blockers and cromolyn frequently report their Hashimoto's antibodies trend down over six to twelve months. This is anecdotal — it comes from what patients report.
The reverse is also true. Poorly controlled Hashimoto's — particularly during a Hashitoxic flare — can destabilize mast cells. The thyroid and the mast cell compartment talk to each other constantly. Treating only one of them leaves the other to stir the pot.
Workup Sequence — What to Ask For and In What Order
If you suspect this triad, here is the order of operations. You can often get most of it through a supportive primary care doctor; the harder pieces may need a rheumatologist, cardiologist, or allergist.
Step 1. Thyroid panel (done first)
- Thyroid-stimulating hormone, free T4, free T3
- TPO antibodies and thyroglobulin antibodies — see TPO and TgAb explained
- Reverse T3 if fatigue dominates and free T3 looks borderline
- Thyroid ultrasound if antibodies are positive — confirms the characteristic heterogeneous, hypoechoic pattern
Step 2. Orthostatic vitals (in-office, ten minutes)
- Lie flat for 10 minutes. Measure HR and blood pressure (BP).
- Stand up. Measure HR and blood pressure at 1, 3, 5, and 10 minutes.
- Postural orthostatic tachycardia syndrome criterion: sustained HR rise of ≥30 bpm (≥40 bpm in teens) within 10 minutes of standing, without a drop in blood pressure >20/10.
- If the in-office test is negative but symptoms persist, the next test is a tilt-table test with autonomic reflex screen.
Step 3. Mast cell workup
- Serum tryptase (baseline, when not flaring). Normal does not rule out mast cell activation syndrome; elevated points strongly toward it.
- 24-hour urine N-methylhistamine, prostaglandin D2 (or 11-beta-PGF2-alpha), and leukotriene E4. Collect chilled.
- Chromogranin A (off proton pump inhibitors (PPIs) for 5 days before the test, which falsely elevates it).
- A clinical trial of H1 + H2 antihistamines for 4–6 weeks can be diagnostic if symptoms respond.
Step 4. Hypermobility screen
- Beighton score (0–9). Score ≥5 in adults suggests hypermobility.
- Family history of "double-jointedness," easy bruising, stretchy skin, or early joint problems.
- Full hEDS criteria (2017 international) require more than just Beighton — skin findings and musculoskeletal complications count.
Step 5. Co-travelers worth checking
- Ferritin (practitioners in this field look for >50 ng/mL, ideally 70–100, in postural orthostatic tachycardia syndrome)
- Vitamin B12, vitamin D, magnesium
- Celiac panel (tTG-IgA + total immunoglobulin A, IgA) — a 2016 pooled analysis of 6,024 people with autoimmune thyroid disease found biopsy-confirmed celiac disease in 1.6% (about 1 in 62): 2.7% of adults and 6.2% of children
- Cortisol (AM serum, or 4-point salivary) — hypothalamic-pituitary-adrenal-axis dysregulation is common in the triad
Treatment Ordering — Thyroid First, Then Postural Orthostatic Tachycardia Syndrome, Then Mast Cell Activation Syndrome
Clinicians who treat this triad describe treating all three at once as going in circles. The order they describe is thyroid → postural orthostatic tachycardia syndrome → mast cell activation syndrome.
1. The thyroid first
The targets these clinicians describe are free T3 in the upper third of the reference range and free T4 in the mid-to-upper third; they report that thyroid-stimulating hormone in this population often needs to be below 2.0 for patients to feel well, though individual response varies. Some patients do fine on levothyroxine alone; others need a T4/T3 combination or natural desiccated thyroid (see levothyroxine vs NDT vs T3). A dose is usually judged after at least 8–12 weeks at a stable dose.
Why first? Practitioners report that a significant fraction of postural orthostatic tachycardia syndrome-like symptoms resolve on their own once tissue thyroid levels come up — otherwise three more drugs get stacked on a patient whose core problem is actually undertreated hypothyroidism.
2. Then Postural Orthostatic Tachycardia Syndrome, starting without drugs
- Salt. The 2015 Heart Rhythm Society expert statement gives about 10–12 grams of salt (sodium chloride) a day, “if tolerated,” for people with postural orthostatic tachycardia syndrome. The U.S. Department of Agriculture (USDA) lists a teaspoon of table salt as 6 grams, so that is roughly 1⅔ to 2 teaspoons.
- Fluids. The same statement gives 2–3 liters of water a day. People with the condition describe commercial electrolyte mixes or homemade salt-and-sugar drinks as helping.
- Compression. Waist-high 20–30 mmHg stockings or an abdominal binder. Knee-highs are mostly cosmetic.
- Recumbent exercise (Levine or CHOP protocol). Rowing, recumbent bike, swimming — these programs start horizontal and move to upright exercise over months.
- Sleeping with the head of the bed elevated 4–6 inches, which practitioners describe as training renin-angiotensin regulation.
If the baseline is not enough, medications come next: beta-blockers (propranolol, metoprolol) for hyperadrenergic postural orthostatic tachycardia syndrome, midodrine for vasoconstriction, fludrocortisone for volume, ivabradine if beta-blockade is not tolerated, pyridostigmine for some autoimmune phenotypes.
3. Then Mast Cell Activation Syndrome therapy
The sequence practitioners describe starts with the cheap, safe pieces and escalates:
- H1 antihistamines (daytime: cetirizine, fexofenadine, loratadine; night: hydroxyzine or diphenhydramine)
- H2 antihistamines (famotidine 20–40 mg twice daily)
- Mast cell stabilizers: cromolyn sodium 200 mg four times daily before meals, ketotifen 1–2 mg twice daily
- Quercetin 500–1000 mg twice daily, often paired with bromelain or luteolin
- Leukotriene blockers (montelukast) for respiratory-predominant flares
- Low-dose naltrexone 1.5–4.5 mg at night — modulates both mast cells and autoimmune activity; increasingly used across the triad
Known mast cell triggers among drugs and other exposures include opioids (morphine, codeine), vancomycin, radiocontrast given without premedication, nonsteroidal anti-inflammatory drugs (NSAIDs) in some patients, and alcohol.
Gluten, Histamine, and Iodine — Dietary Landmines
Diet is not a cure for any of these three conditions, but it is a lever, and the triad makes the lever tricky because the rules for one disease sometimes clash with the rules for another.
Gluten
Hashimoto's and celiac share genetic background (HLA-DQ2/DQ8). Even in non-celiac patients, a strict gluten-free trial of 3–6 months lowers TPO antibodies in a sizable minority. The autoimmune protocol (AIP) is a more aggressive version. See AIP and gluten elimination. Gluten is not known to directly trigger mast cells or postural orthostatic tachycardia syndrome, but the inflammation it drives in susceptible people makes both worse.
Histamine
This is the real landmine for mast cell activation syndrome patients. High-histamine foods: aged cheeses, cured meats, fermented foods (sauerkraut, kimchi, kombucha), wine and beer, leftovers stored more than 24 hours, tomatoes, spinach, eggplant, avocado, banana, strawberries, chocolate, vinegar. The problem is that several of these — fermented foods especially — are darlings of the "gut health for Hashimoto's" crowd. For people with both conditions, practitioners describe a low-histamine diet for 4–8 weeks, followed by reintroducing foods one at a time. See the dedicated low-histamine diet guide.
Iodine
This is where well-meaning advice goes wrong most often. High-dose iodine (kelp tablets, Lugol's solution, 12.5 mg daily protocols) can accelerate Hashimoto's autoimmune activity. Studies from iodine-replete populations show that excess iodine increases TPO antibodies and hastens the transition to overt hypothyroidism. The Recommended Dietary Allowance (RDA) for adults is 150 mcg a day — the scale of food plus a standard multivitamin, far below megadose supplements. See selenium, zinc, iron, and iodine for the full nuance.
Salt
For postural orthostatic tachycardia syndrome, the 2015 Heart Rhythm Society statement gives about 10–12 grams of salt (sodium chloride) a day, if tolerated. Mast cell activation syndrome usually tolerates this fine. Hashimoto's does not care. This is one of the easier wins.
Practical Self-Monitoring
You will be your own most reliable data source between appointments. A cheap wrist blood pressure cuff and a smartphone are enough.
- Daily orthostatic vitals (first 4–6 weeks, then weekly). Supine HR/blood pressure after 5 minutes flat in the morning, then readings at 1, 3, 5, and 10 minutes after standing. People log it in a spreadsheet or a heart-rate app.
- Resting heart rate trend. A smartwatch that logs overnight HR shows the thyroid and autonomic picture more reliably than a single clinic reading. A trend from 75 down to 58 often means thyroid is undertreated. A trend up from 65 to 88 often means you are flaring or thyroid is swinging.
- Symptom-and-trigger diary. Date, food, environment, menstrual cycle day, symptoms, severity 1–10. Three weeks of this usually reveals a pattern no doctor can extract in a 15-minute visit.
- Basal body temperature first thing in the morning. Chronically below 97.4°F (36.3°C) suggests under-treated hypothyroidism.
- Flare journal. A record, after a bad day, of what was eaten, done, worn, and taken in the preceding 24 hours. Patterns emerge: a specific detergent, a skipped dose, a high-histamine dinner, a hot shower, a missed salt load.
When to Push Back on Your Doctor
Diagnosis is slow. In the 2019 survey of 4,835 people with postural orthostatic tachycardia syndrome, the median delay was 24 months, with the middle half of patients waiting between 6 and 72 months — though the survey also found the delay is improving. Patients and clinicians describe the reason as almost always that individual specialists look only at their own organ. You may need to advocate hard. Red flags for a workup that is not thorough enough:
- Thyroid-stimulating hormone alone ordered with no antibodies or free T3/T4.
- "Your labs are normal, it's just anxiety" without orthostatic vitals ever being measured.
- Being told mast cell activation syndrome is not real. It is real; it is in the ICD-10 as D89.42.
- A refusal to trial H1/H2 antihistamines for 4 weeks. These are cheap, over-the-counter, and virtually risk-free.
- No recognition that hypermobility is clinically significant.
When a current provider is not engaged, the clinicians who see this triad are dysautonomia specialists, allergists/immunologists who see mast cell activation syndrome, and integrative/functional medicine physicians who understand the triad. Dysautonomia International maintains a physician directory. You are not a difficult patient — you have a complex illness, and it takes the right team.
Key Research Papers
Foundational and recent peer-reviewed publications on the Hashimoto's / postural orthostatic tachycardia syndrome / mast cell activation syndrome triad — autoimmune thyroid disease, postural tachycardia, mast-cell activation, and the connective-tissue overlap. Each citation links to the full text via DOI.
- Caturegli P, De Remigis A, Rose NR. Hashimoto Thyroiditis: Clinical and Diagnostic Criteria. Autoimmunity Reviews. 2014;13(4-5):391–397. — doi:10.1016/j.autrev.2014.01.007
- Blitshteyn S. Autoimmune Markers and Autoimmune Disorders in Patients with Postural Tachycardia Syndrome (POTS). Lupus. 2015;24(13):1364–1369. — doi:10.1177/0961203315587566
- Shaw BH, Stiles LE, Bourne K, et al. The Face of Postural Tachycardia Syndrome — Insights from a Large Cross-Sectional Online Community-Based Survey. Journal of Internal Medicine. 2019;286(4):438–448. — doi:10.1111/joim.12895
- Kohno R, Cannom DS, Olshansky B, et al. Mast Cell Activation Disorder and Postural Orthostatic Tachycardia Syndrome: A Clinical Association. Journal of the American Heart Association. 2021;10(17):e021002. — doi:10.1161/JAHA.121.021002
- Seneviratne SL, Maitland A, Afrin L. Mast Cell Disorders in Ehlers-Danlos Syndrome. American Journal of Medical Genetics Part C: Seminars in Medical Genetics. 2017;175(1):226–236. — doi:10.1002/ajmg.c.31555
- Afrin LB, Self S, Menk J, Lazarchick J. Characterization of Mast Cell Activation Syndrome. American Journal of the Medical Sciences. 2017;353(3):207–215. — doi:10.1016/j.amjms.2016.12.013
- Theoharides TC, Tsilioni I, Ren H. Recent Advances in Our Understanding of Mast Cell Activation — or Should It Be Mast Cell Mediator Disorders? Expert Review of Clinical Immunology. 2019;15(6):639–656. — doi:10.1080/1744666X.2019.1596800
- Vernino S, Stiles LE. Autoimmunity in Postural Orthostatic Tachycardia Syndrome: Current Understanding. Autonomic Neuroscience. 2018;215:78–82. — doi:10.1016/j.autneu.2018.04.005
- Watari M, Nakane S, Mukaino A, et al. Autoimmune Postural Orthostatic Tachycardia Syndrome. Annals of Clinical and Translational Neurology. 2018;5(4):486–492. — doi:10.1002/acn3.524
- Hollowell JG, Staehling NW, Flanders WD, et al. Serum TSH, T4, and Thyroid Antibodies in the United States Population (NHANES III). Journal of Clinical Endocrinology & Metabolism. 2002;87(2):489–499. — doi:10.1210/jcem.87.2.8182
- Jonklaas J, Bianco AC, Bauer AJ, et al. Guidelines for the Treatment of Hypothyroidism (American Thyroid Association). Thyroid. 2014;24(12):1670–1751. — doi:10.1089/thy.2014.0028
- Knezevic J, Starchl C, Tmava Berisha A, Amrein K. Thyroid–Gut-Axis: How Does the Microbiota Influence Thyroid Function? Nutrients. 2020;12(6):1769. — doi:10.3390/nu12061769
- Sheldon RS, Grubb BP 2nd, Olshansky B, et al. 2015 Heart Rhythm Society Expert Consensus Statement on the Diagnosis and Treatment of Postural Tachycardia Syndrome, Inappropriate Sinus Tachycardia, and Vasovagal Syncope. Heart Rhythm. 2015;12(6):e41–e63. — PubMed PMID: 25980576
- Roy A, Laszkowska M, Sundström J, et al. Prevalence of Celiac Disease in Patients with Autoimmune Thyroid Disease: A Meta-Analysis. Thyroid. 2016;26(7):880–890. — PubMed PMID: 27256300
PubMed Topic Searches
Live PubMed queries that update as new papers are indexed.
- PubMed: Hashimoto's + POTS
- PubMed: POTS + mast cell activation
- PubMed: EDS + POTS + MCAS triad
- PubMed: autoimmune thyroid + dysautonomia
- PubMed: mast cells + thyroid autoimmunity
- PubMed: hypothyroidism + orthostatic intolerance
- PubMed: histamine intolerance + autoimmune
- PubMed: iodine + Hashimoto's antibody
Connections
- Endocrinology
- How Your Thyroid Is Controlled — interactive animation
- Hashimoto's Thyroiditis Overview
- AIP and Gluten Elimination
- Levothyroxine vs NDT vs T3
- Thyroid-Stimulating Hormone, T4, and T3 Optimal Ranges
- Selenium, Zinc, Iron, and Iodine
- TPO and TgAb Antibodies
- Reverse T3 and Low T3 Syndrome
- Pregnancy and Hashimoto's
- Gut-Thyroid Axis and Intestinal Permeability
- Postural Orthostatic Tachycardia Syndrome
- Mast Cell Activation Syndrome
- Thyroid Disorders
- Low-Histamine Diet
- Brain Fog
- Iodine
- Neurology