Uveitis & Eye Involvement in Ankylosing Spondylitis (AS)
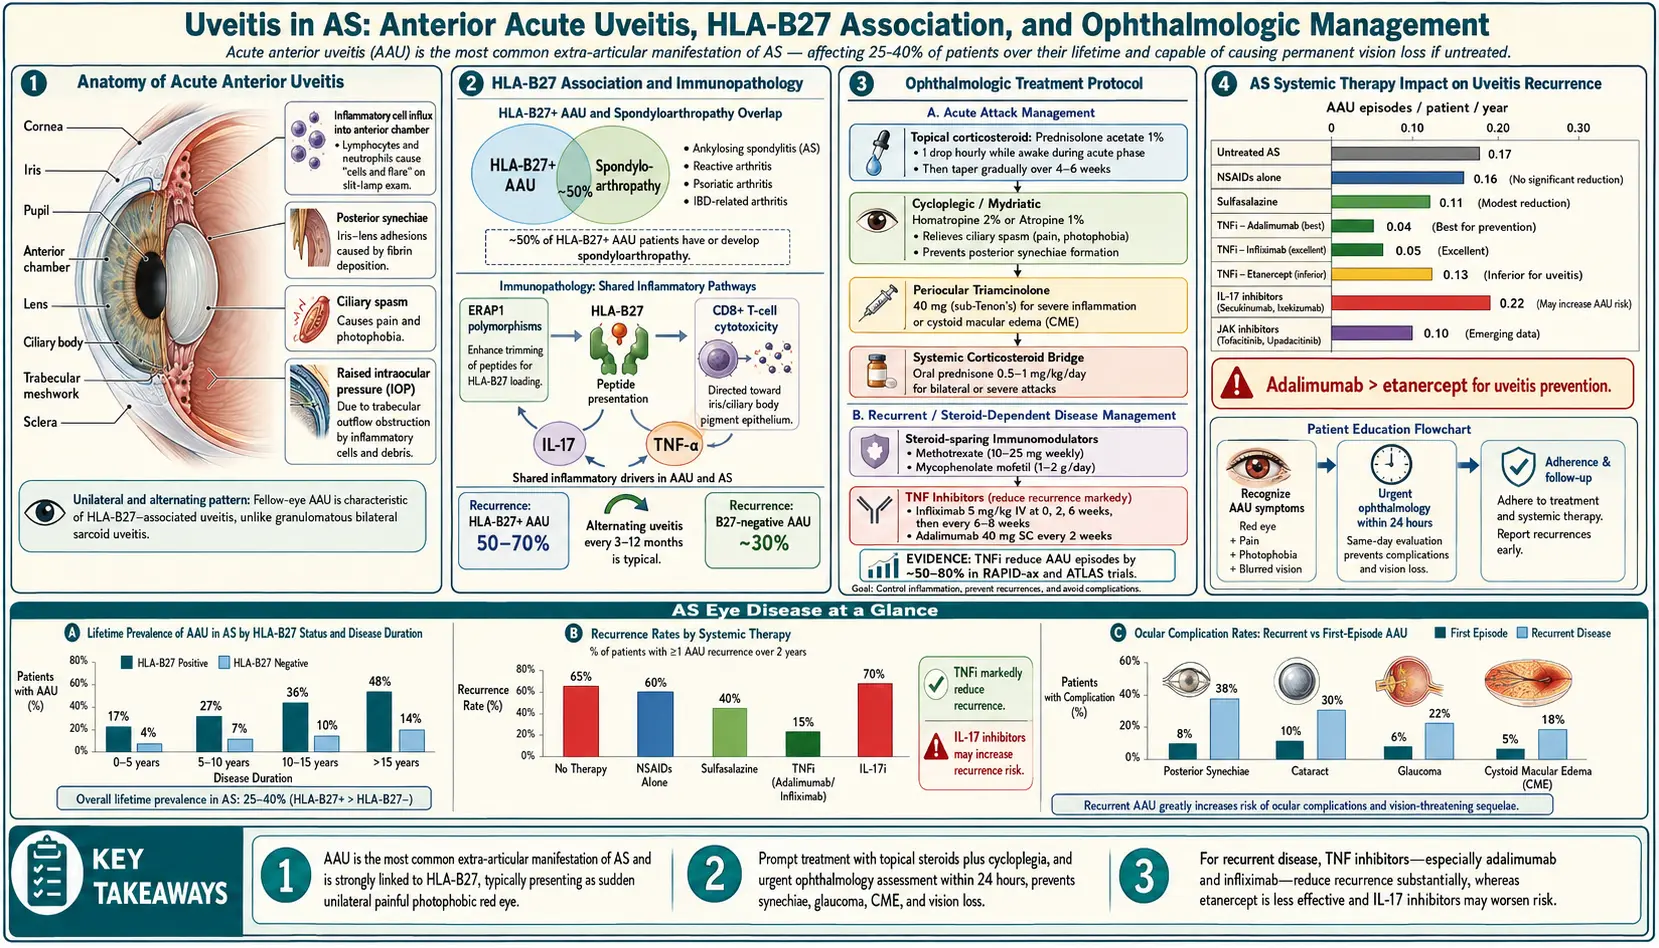
Read this first if your eye is red and painful right now: a sudden, painful, red, light-sensitive eye in someone with ankylosing spondylitis (AS) (or human leukocyte antigen-B27) is treated as acute anterior uveitis until proven otherwise — and it is a true eye emergency. The standard of care is a slit-lamp exam by an ophthalmologist within 24 hours — an exam that a primary care office or an urgent care clinic usually cannot do. When the regular eye clinic cannot see the patient the same day, an emergency department with an on-call ophthalmologist can. Every hour of delay increases the risk of permanent scarring, glaucoma, or vision loss.
Now the background. Uveitis is the single most common non-spinal complication of ankylosing spondylitis. Roughly 25–40% of ankylosing spondylitis patients will have at least one episode in their lifetime, and for many, a uveitis flare is the first symptom — showing up years before the back pain that eventually gets the ankylosing spondylitis diagnosis. If you have a strong family history of ankylosing spondylitis or you have already tested human leukocyte antigen-B27 positive, understanding what uveitis looks like and what to do about it can literally save your sight.
Table of Contents
- What Uveitis Is and Which Kind Ankylosing Spondylitis Patients Get
- Symptoms — How to Recognize an Attack
- Why Human Leukocyte Antigen-B27 Drives It
- Uveitis vs Conjunctivitis vs "Pink Eye"
- Diagnosis — The Slit-Lamp Exam
- Treatment — Drops, Dilators, and Systemic Therapy
- How Ankylosing Spondylitis Biologics Change Your Uveitis Risk
- Complications if Treatment Is Delayed
- Emergency Action Plan for an Ankylosing Spondylitis Eye Flare
- Key Research Papers
- PubMed Topic Searches
- Connections
- Featured Videos
What Uveitis Is and Which Kind Ankylosing Spondylitis Patients Get
The uvea is the middle, pigmented layer of the eye. It has three parts: the iris (the colored ring you can see), the ciliary body (which makes the fluid inside the eye and controls the lens focusing muscle), and the choroid (a vascular layer behind the retina). "Uveitis" means inflammation of any portion of the uvea.
The type almost every ankylosing spondylitis patient gets is acute anterior uveitis (AAU) — also called iritis because the iris and the front of the ciliary body are where the inflammation concentrates. Key features:
- Acute: comes on over hours to a day or two, not weeks.
- Anterior: confined to the front chamber of the eye. The retina is usually spared, which is why prompt treatment almost always preserves vision.
- Unilateral: one eye at a time, though it often alternates between eyes across episodes. Simultaneous bilateral AAU is unusual in human leukocyte antigen-B27 disease and prompts a look for other causes (sarcoidosis, Behçet, infection).
- Recurrent: once you have had one, the lifetime odds of another are high — most patients average roughly one flare every one to two years if untreated.
The numbers from the research. A 2008 systematic review pooled 126 studies (29,877 patients) on how often uveitis occurs in the spondyloarthritis family of diseases. Uveitis affected 33.2% of people with ankylosing spondylitis (against 25.1% in psoriatic arthritis), and it was more common the longer the disease had lasted and in people who carry human leukocyte antigen-B27 (odds ratio 4.2). In the 36 studies (1,989 patients) that described the eye attacks themselves, uveitis was sudden (acute) in 88.7%, at the front of the eye (anterior) in 90.5% and in one eye (unilateral) in 87.3%; it came back in 50.6%, and 8.3% had reduced sharpness of vision.
Posterior uveitis (inflammation of the choroid/retina) and panuveitis (whole-eye inflammation) are not typical of ankylosing spondylitis. When an ophthalmologist finds posterior or panuveitis, the workup widens to sarcoid, tuberculosis, syphilis, Behçet's, and other causes.
Symptoms — How to Recognize an Attack
These are the signs to know. They come in any combination, and the first one often appears while you are still doing something ordinary — reading, driving into sunlight, sitting at a computer.
- Eye pain — a deep ache, not a surface scratchy feeling. Often worse when you look at something bright or when the eye tries to focus up close.
- Redness concentrated around the iris — called a ciliary flush. The redness forms a pink-to-purple ring hugging the colored part of the eye, as opposed to diffuse redness across the whole white of the eye.
- Photophobia — even normal room lighting feels painfully bright. Sunlight is unbearable. Many patients instinctively pull sunglasses on indoors.
- Blurred vision — from inflammatory cells floating in the fluid of the front chamber and from a constricted, spasming pupil.
- Floaters — specks or wisps drifting across your field of view, because white blood cells are literally suspended in the aqueous humor.
- A small, sluggish, or irregularly shaped pupil — the iris muscle is inflamed and may stick to the lens, pulling the pupil out of round.
- Tearing (without much discharge) — reflex tears from pain, not the thick goop of conjunctivitis.
Three or more of these in one eye point strongly to uveitis, which eye specialists examine the same day.
Why Human Leukocyte Antigen-B27 Drives It
The link between human leukocyte antigen-B27 and acute anterior uveitis is as tight as the link to ankylosing spondylitis itself. Across multiple international cohorts, roughly 50–60% of people presenting with a first episode of acute anterior uveitis carry human leukocyte antigen-B27 — vastly higher than the 6–8% B27 prevalence in the general Caucasian population. Conversely, of people who are human leukocyte antigen-B27 positive, about 1% per year will have a uveitis flare, cumulative over a lifetime.
Clinically this matters because human leukocyte antigen-B27-associated uveitis has a signature that an experienced ophthalmologist can recognize: acute onset, unilateral, anterior only, alternating sides over years, strongly responsive to topical steroids, and often clustered in people who also have back stiffness, psoriasis, reactive arthritis, or inflammatory bowel disease. In most centers, an adult who shows up with a first episode of AAU is asked about chronic back pain and offered human leukocyte antigen-B27 testing — because a positive result often uncovers undiagnosed spondyloarthritis. For the full genetics and mechanism, see the human leukocyte antigen-B27 article.
Uveitis is also more common in ankylosing spondylitis patients with concurrent inflammatory bowel disease (see ankylosing spondylitis & inflammatory bowel disease (IBD) overlap) and in those with longer disease duration.
Uveitis vs Conjunctivitis vs "Pink Eye"
Most red eyes are not uveitis. Knowing the differences lets you self-triage and lets you push back if a clinician waves you off with "looks like pink eye, use some drops."
- Viral or bacterial conjunctivitis ("pink eye") — usually bilateral (both eyes, or the second within a day or two), diffuse redness across the whole sclera, thick discharge that crusts lashes shut overnight, mild gritty irritation rather than deep pain, normal vision, normal pupil, no photophobia.
- Dry eye / corneal abrasion — scratchy surface feeling, watery, sometimes a foreign-body sensation. Pain improves dramatically with an anesthetic drop in the emergency room (a diagnostic clue). Pupil normal.
- Acute angle-closure glaucoma — severe pain, nausea, vomiting, hazy cornea, fixed mid-dilated pupil. Also an emergency. Distinguished by tonometry (very high eye pressure).
- Acute anterior uveitis — usually unilateral, deep aching pain, ciliary flush around the iris, photophobia, blurred vision, small or irregular pupil, minimal discharge (watery, not purulent).
The shortcut: bilateral, gooey, no real pain is almost always conjunctivitis. Unilateral, truly painful, light-sensitive, with vision changes is uveitis (or angle-closure) until an ophthalmologist says otherwise.
Diagnosis — The Slit-Lamp Exam
Uveitis is diagnosed in the clinic with a slit lamp — a microscope with a narrow beam of light that the ophthalmologist shines into the front chamber of your eye. You will be asked to rest your chin on a cushion and stare at a tiny target. The whole exam takes five to ten minutes. What they look for:
- Cells and flare. Individual inflammatory cells floating in the aqueous humor look like dust motes in a sunbeam. A hazy background ("flare") is protein leaking from inflamed blood vessels. Both are graded 0 to 4+.
- Keratic precipitates (KPs). Clumps of inflammatory cells that stick to the inner surface of the cornea. In human leukocyte antigen-B27 uveitis they are usually fine and scattered.
- Posterior synechiae. Adhesions where the iris has glued itself to the front of the lens. If present, the pupil will not dilate cleanly when drops are instilled — it will snag at the adhesion points and look scalloped or pulled-in.
- Hypopyon. In severe flares, a layer of white cells settles at the bottom of the front chamber, visible as a small white crescent. Uncommon but classic for human leukocyte antigen-B27 uveitis.
- Intraocular pressure. Measured with a tonometer. Can be low (inflamed ciliary body making less fluid) or elevated (cells clogging outflow, or steroid response later on).
- Dilated fundus exam. To confirm the back of the eye is not involved — an important step, because posterior involvement would change the diagnosis and workup.
Bloodwork and imaging are usually not needed for a first episode of classic unilateral acute anterior uveitis in someone already known to have ankylosing spondylitis. Recurrent, bilateral, posterior, or atypical uveitis gets a broader workup: human leukocyte antigen-B27 if not done, chest X-ray (sarcoid, tuberculosis), syphilis blood tests (rapid plasma reagin (RPR) and fluorescent treponemal antibody (FTA) tests), angiotensin-converting enzyme (ACE) level (for sarcoid), a QuantiFERON-TB blood test, and occasionally brain imaging for Behçet's or multiple sclerosis.
Treatment — Drops, Dilators, and Systemic Therapy
The goals are three: stop the inflammation fast, keep the iris from sticking to the lens, and control pain. Most uncomplicated flares are handled topically.
Topical corticosteroid drops
The workhorse is prednisolone acetate 1% eye drops. A typical starting regimen for a moderate flare is one drop in the affected eye every 1 to 2 hours while awake for the first 2–3 days, then a slow taper over four to six weeks guided by repeat slit-lamp exams. Stopping the drops early because the eye feels better is a common cause of rebound inflammation — it is frequent when the taper is rushed. Alternatives include difluprednate 0.05% (stronger, dosed two to four times a day) and dexamethasone 0.1%.
Warning: topical steroids can raise eye pressure and, over months, accelerate cataract. Both are manageable when the ophthalmologist is monitoring. Self-treating a later flare from a leftover bottle of steroid drops, without an exam, carries a real hazard: steroid drops on top of a herpes simplex keratitis or a bacterial ulcer that looks like uveitis can blind the eye.
Cycloplegic / mydriatic drops
Drops that paralyze the iris muscle and dilate the pupil. They do three things: relieve the painful spasm of the ciliary body, pull the iris away from the lens so adhesions cannot form, and break any adhesions that have already started. Options:
- Cyclopentolate 1%, one drop 2–3 times daily — most common choice for moderate flares.
- Homatropine 5%, twice daily — longer-acting middle-ground.
- Atropine 1%, once daily — the strongest dilator, reserved for severe inflammation or when posterior synechiae are already forming.
Near vision is usually blurry and the pupil enlarged for several days to a week after these drops. Bright light is uncomfortable, and many people wear sunglasses during this time.
Stepping up — oral steroids and injections
If topical therapy is not controlling the flare after 48–72 hours, or if the inflammation is severe from the start (dense cells, hypopyon, macular involvement), the next steps are:
- Oral prednisone — typically 40–60 mg daily with a taper over weeks.
- Periocular steroid injection — triamcinolone delivered into the sub-Tenon's space or transseptally; gives weeks of high local drug levels without as much systemic exposure.
- Intravitreal steroid implants (dexamethasone, fluocinolone) — used mostly for chronic or posterior disease, rarely needed in classic human leukocyte antigen-B27 AAU.
Systemic immunomodulation
For patients with frequent, sight-threatening, or steroid-dependent uveitis, systemic therapy enters the picture. In ankylosing spondylitis patients this usually overlaps with the drugs already being considered for the spine — see the next section and the biologics guide.
How Ankylosing Spondylitis Biologics Change Your Uveitis Risk
This is one of the most important — and underappreciated — decisions in ankylosing spondylitis care: different biologics have different effects on uveitis. Some protect the eyes, some do little for them, and in rare cases some are linked to new flares — which is why the 2022 ASAS-EULAR recommendations name a preferred drug class for people with recurrent uveitis (below).
Monoclonal anti-TNF antibodies — reduce flares
The monoclonal tumor necrosis factor (TNF) inhibitors — infliximab, adalimumab, certolizumab pegol, golimumab — consistently reduce the rate of uveitis flares in spondyloarthritis, in some cohorts by more than half. Adalimumab is also U.S. Food and Drug Administration-approved for uveitis, on the strength of the VISUAL-1, VISUAL-2, and VISUAL-3 trials — but its label covers non-infectious intermediate, posterior, and panuveitis in adults and children 2 years of age and older, not the anterior uveitis (iritis) typical of ankylosing spondylitis; VISUAL-1 enrolled adults with active intermediate, posterior or panuveitis. For people with active ankylosing spondylitis and recurrent uveitis, the 2022 ASAS-EULAR recommendations state that TNF monoclonal antibodies are preferred.
Etanercept — the notable exception
Etanercept, a soluble tumor necrosis factor receptor rather than a monoclonal antibody, protects the eye less than the monoclonal antibodies and is linked to more uveitis than they are. A 2005 pooled analysis of anti-TNF trials in ankylosing spondylitis counted anterior uveitis flares: 15.6 per 100 patient-years on placebo, against 6.8 on anti-TNF drugs overall — 7.9 on etanercept and 3.4 on infliximab (the difference between those two drugs was not statistically significant). A 2025 network meta-analysis found that etanercept raised the risk of new-onset uveitis compared with golimumab and infliximab (relative risk 2.03 and 2.47), and that adalimumab cut it compared with etanercept (relative risk 0.30). Etanercept is still effective for peripheral arthritis and for the spine itself. The 2022 ASAS-EULAR recommendations state that TNF monoclonal antibodies are preferred for recurrent uveitis.
Interleukin-17 (IL-17) inhibitors — mixed data
Secukinumab and ixekizumab are highly effective for the spine and for psoriasis. Their effect on uveitis is less clear. Some post-marketing reports describe paradoxical uveitis in patients starting secukinumab, though registry data suggest the overall rate is low. The 2022 ASAS-EULAR recommendations prefer IL-17 inhibitors when significant psoriasis is present, and TNF monoclonal antibodies when recurrent uveitis is the dominant problem.
The 2025 network meta-analysis. A 2025 analysis combined 18 studies with 11,529 people with ankylosing spondylitis to compare biologics head to head on uveitis. It concluded that blocking IL-17A alone (secukinumab, ixekizumab) “might increase the risk of uveitis”, with both drugs ranking below placebo, while bimekizumab — which blocks IL-17A and IL-17F together — ranked best for lowering recurrent uveitis and was the most effective overall at reducing uveitis. Among all the drugs, the Janus kinase (JAK) inhibitor upadacitinib ranked best for preventing new-onset uveitis.
Janus kinase (JAK) inhibitors — emerging
Tofacitinib and upadacitinib are approved for ankylosing spondylitis and show promising signals for non-infectious uveitis, with trials ongoing. They are generally a later-line option after tumor necrosis factor failure, but the eye data are still emerging.
Traditional disease-modifying antirheumatic drugs (DMARDs)
Methotrexate, azathioprine, and mycophenolate are used for chronic or recurrent non-infectious uveitis, particularly as steroid-sparing agents. They do not help the ankylosing spondylitis spine much but may be combined with a biologic specifically to control the eye.
Complications if Treatment Is Delayed
Most acute anterior uveitis episodes, treated promptly, resolve without lasting damage. Delay — or repeated untreated flares — invites a predictable list of complications:
- Posterior synechiae. The iris scars to the lens. Visible as a pupil that is pulled out of round or that will not dilate evenly. Small synechiae are tolerable; extensive ones can block fluid flow and precipitate secondary glaucoma.
- Cataract. Both chronic inflammation and chronic steroid exposure accelerate cataract formation, often years or decades earlier than normal age-related cataract. Modern cataract surgery is effective but more complex in an eye with a scarred iris.
- Secondary glaucoma. From inflammatory debris clogging the drainage angle, from steroid response, or from synechiae physically blocking outflow. Can cause permanent optic-nerve damage if uncontrolled.
- Cystoid macular edema. Fluid accumulating in the central retina, blurring the sharpest part of your vision. More common when inflammation is prolonged.
- Band keratopathy. A chalky calcium band across the cornea from long-standing chronic inflammation.
- Permanent vision loss. Rare with modern treatment, but real when episodes are missed, under-treated, or repeated over decades.
Emergency Action Plan for an Ankylosing Spondylitis Eye Flare
Uveitis care teams describe a plan like this one, written down, saved in a phone and shared with anyone who might drive the patient to care.
- The trigger symptoms. One-sided eye pain + redness + light sensitivity + blurred vision = uveitis until proven otherwise.
- An ophthalmologist on file before one is needed. For people with ankylosing spondylitis or a positive human leukocyte antigen-B27 test, the plan includes a uveitis-experienced ophthalmologist chosen while the eyes feel fine, with that office's after-hours number and its policy for same-day add-on appointments.
- Calling at once. When symptoms start, the plan is an immediate call to the ophthalmology office, saying: "I have ankylosing spondylitis / I am human leukocyte antigen-B27 positive and I have a painful red light-sensitive eye. I need to be seen for possible uveitis today." Most offices fit such patients in.
- No visit possible within 24 hours: an emergency department (ED) with on-call ophthalmology. A call ahead confirms ophthalmology coverage. Community ERs without eye coverage are of limited help; academic centers and larger hospitals usually have a resident available.
- The medication list and the rheumatologist's contact. The ophthalmologist will want to know the current ankylosing spondylitis regimen and may want to discuss escalating systemic therapy.
- No self-treatment with old steroid drops. Steroids on an undiagnosed herpes or bacterial cause can blind the eye, which is why the diagnosis is confirmed with a slit-lamp exam first.
- The full taper. Once prednisolone drops are started, the plan follows the taper schedule exactly, with the follow-up appointments. Most rebound flares happen because drops were stopped early.
- A flare log. A simple log records date, which eye, severity, treatment and recovery time. After two or three episodes, it is the single best argument a rheumatologist sees for escalating to (or switching to) a monoclonal anti-TNF.
A note on contact lenses
During an active flare, eye specialists have contact lenses left out of both eyes. The affected eye is too inflamed to tolerate a lens, and any surface trauma from a lens can confuse the diagnosis (uveitis versus contact-lens-related keratitis). Lenses go back in only after the ophthalmologist confirms the inflammation is fully resolved and the drops are tapered off. Standard contact lens hygiene year-round — daily disposables where possible, no sleeping in lenses, no rinsing or storing lenses in tap water — matters because a corneal infection on top of ankylosing spondylitis uveitis is a dangerous combination.
Key Research Papers
- Rosenbaum JT. Characterization of uveitis associated with spondyloarthritis. J Rheumatol. 1989;16(6):792-796. — PubMed PMID: 2778762
- Rudwaleit M, et al. Adalimumab effectively reduces the rate of anterior uveitis flares in patients with active ankylosing spondylitis. Ann Rheum Dis. 2009. — doi:10.1136/ard.2008.092585
- Braun J, Baraliakos X, Listing J, Sieper J. Decreased incidence of anterior uveitis in patients with ankylosing spondylitis treated with the anti-tumor necrosis factor agents infliximab and etanercept. Arthritis Rheum. 2005;52(8):2447-2451. — PubMed PMID: 16052578
- Zeboulon N, Dougados M, Gossec L. Prevalence and characteristics of uveitis in the spondyloarthropathies: a systematic literature review. Ann Rheum Dis. 2008;67(7):955-959. — PubMed PMID: 17962239
- Zhao X, Xie Q, He X, Lu Y, Li M, Shuai S. Risk of new-onset and recurrent uveitis with different biologics for ankylosing spondylitis: a network meta-analysis. Front Immunol. 2025;16:1556313. — PubMed PMID: 40621455
- Jaffe GJ, et al. (VISUAL-1) Adalimumab in patients with active noninfectious uveitis. N Engl J Med. 2016. — doi:10.1056/NEJMoa1509852
- Ramiro S, et al. ASAS-EULAR recommendations for the management of axial spondyloarthritis: 2022 update. Ann Rheum Dis. 2023. PubMed PMID: 36270658
- Dick AD, Rosenbaum JT, Al-Dhibi HA, et al. Guidance on noncorticosteroid systemic immunomodulatory therapy in noninfectious uveitis: Fundamentals Of Care for UveitiS (FOCUS) initiative. Ophthalmology. 2018;125(5):757–773. — doi:10.1016/j.ophtha.2017.11.017
PubMed Topic Searches
For further reading, the following PubMed topic searches return current peer-reviewed work on ankylosing spondylitis-associated uveitis biology, diagnosis, and treatment:
- HLA-B27 and acute anterior uveitis
- Ankylosing spondylitis and uveitis prevalence
- Adalimumab and uveitis in spondyloarthritis
- Etanercept and uveitis flares
- Infliximab for anterior uveitis
- Secukinumab and paradoxical uveitis
- JAK inhibitors and uveitis
- Posterior synechiae and iritis treatment
- Prednisolone acetate taper for uveitis
- Cystoid macular edema in uveitis
Connections
- Rheumatology
- Ankylosing Spondylitis
- Human Leukocyte Antigen-B27 Explained
- Biologics Guide
- Ankylosing Spondylitis and Inflammatory Bowel Disease Overlap
- Exercise and PT Protocol
- Nonsteroidal Anti-Inflammatory Drug Strategy
- Morning Stiffness Management
- Starch-Free Diet and Ebringer
- Pregnancy and Ankylosing Spondylitis
- Arthritis
- Lupus
- Inflammatory Bowel Disease
- Psoriasis
- Glaucoma
- Tuberculosis
- Inflammatory Markers
- Uveitis — the general overview of uveitis in all its forms, beyond the ankylosing spondylitis-associated anterior type.