Biologics Guide for Ankylosing Spondylitis
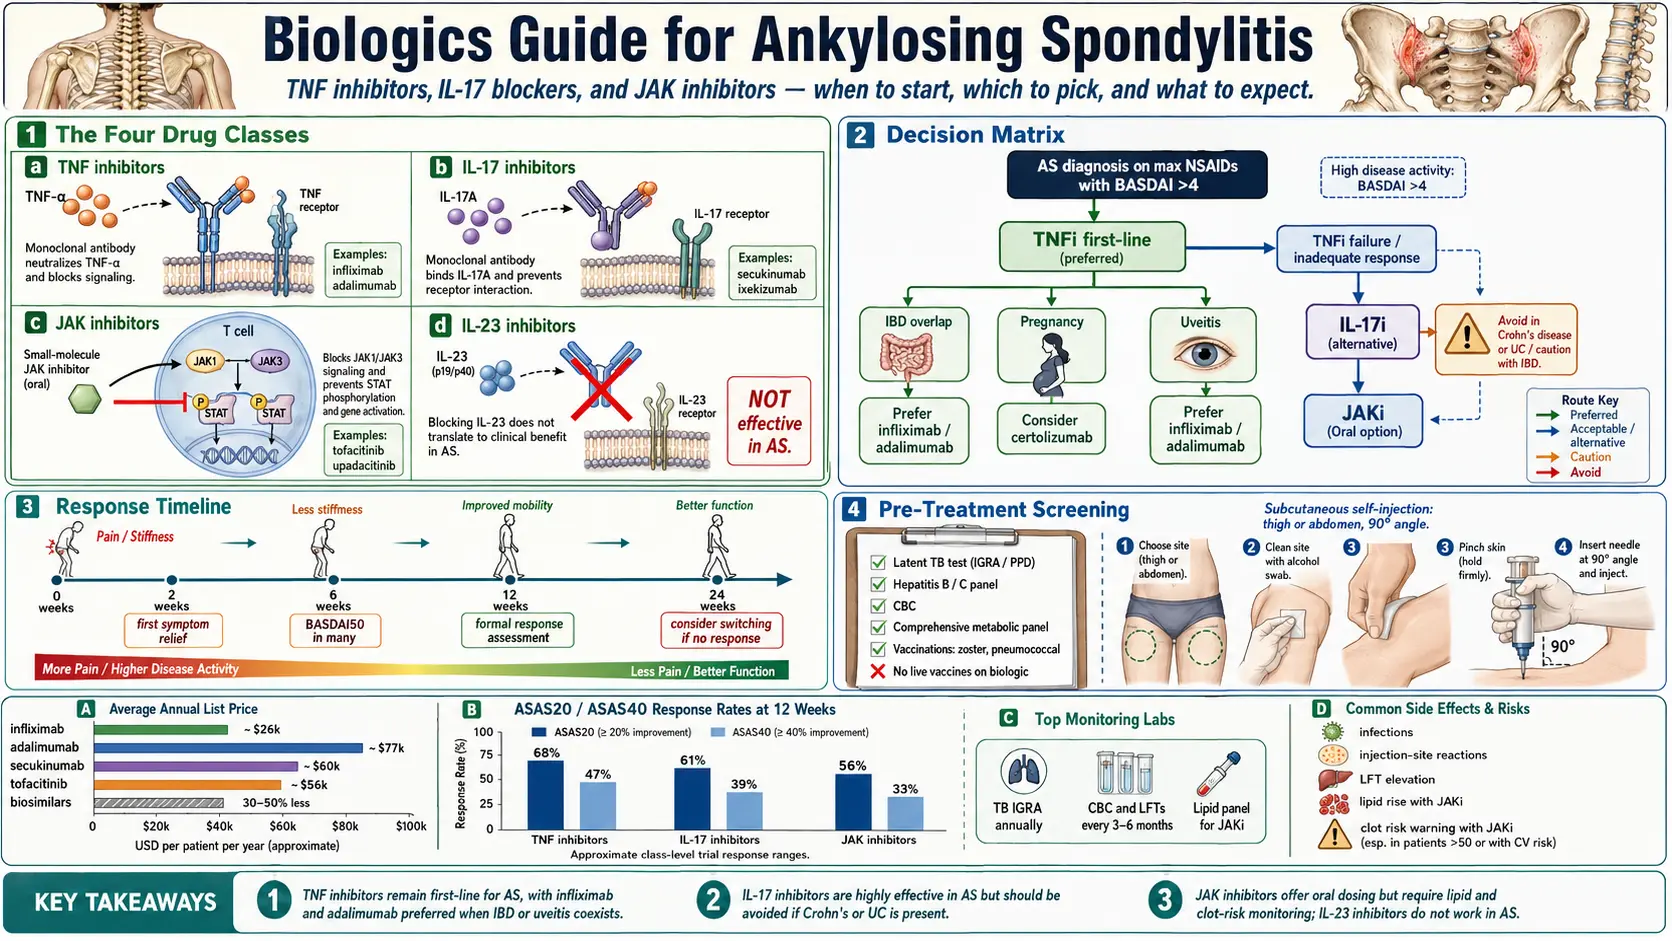
Table of Contents
- Why Biologics Are Different from Nonsteroidal Anti-Inflammatory Drugs
- When to Start Biologics
- The Four Drug Classes in Ankylosing Spondylitis
- Tumor Necrosis Factor Inhibitors — First-Line Biologics
- IL-17 Inhibitors
- JAK Inhibitors — Oral Option
- IL-23 Inhibitors — Not Effective for Ankylosing Spondylitis
- Picking Your Biologic — Decision Matrix
- Cost and Insurance Reality
- How to Give Yourself an Injection
- What to Expect — Timeline of Response
- Side Effects — What to Watch
- Pre-Treatment Screening Checklist
- Monitoring During Treatment
- Stopping or Switching
- Combining Biologics with Other Drugs
- Key Research Papers
- Connections
- Featured Videos
1. Why Biologics Are Different from Nonsteroidal Anti-Inflammatory Drugs
When your rheumatologist says “we’re going to start a biologic,” they are talking about a fundamentally different class of drug than the nonsteroidal anti-inflammatory drugs (NSAIDs) you have probably been taking. Nonsteroidal anti-inflammatory drugs (ibuprofen, naproxen, celecoxib, indomethacin) manage pain and inflammation by blocking cyclooxygenase enzymes. They help you function. They do not, in any meaningful way, change the long-term course of ankylosing spondylitis.
Biologics block specific cytokines — the molecular messengers driving the disease. In ankylosing spondylitis (AS) these are primarily tumor necrosis factor-alpha, IL-17, and, in the case of JAK inhibitors, the intracellular signaling pathway (JAK-STAT) that many cytokines use to deliver their messages. Turning off these pathways can slow or halt spinal fusion when started early, before syndesmophytes (bony bridges between vertebrae) form.
The trade-off is real. Biologics mean injections or infusions instead of pills. They suppress parts of the immune system. They cost thousands of dollars a month. They involve insurance battles, prior authorizations, specialty pharmacies, and baseline infectious-disease screening. For the right patient — especially a young person with active inflammation — the trade-off is worth it. For someone with mild disease well-controlled on nonsteroidal anti-inflammatory drugs, it usually is not.
2. When to Start Biologics
The 2019 ACR/SAA/SPARTAN guidelines (American College of Rheumatology / Spondylitis Association of America) recommend moving to a biologic after failing 2 or more nonsteroidal anti-inflammatory drugs at adequate doses for 2–4 weeks each. “Failure” means active disease despite full anti-inflammatory dosing. For the details of what counts as an adequate nonsteroidal anti-inflammatory drug (NSAID) trial, see nonsteroidal anti-inflammatory drug Strategy.
But there are several situations where rheumatologists push to start a biologic earlier:
- Peripheral arthritis or enthesitis (joint swelling outside the spine, inflammation where tendons attach to bone) — nonsteroidal anti-inflammatory drugs often don’t touch these.
- Uveitis flares — recurrent eye inflammation strongly predicts structural progression and responds well to tumor necrosis factor (TNF) inhibitors.
- Inflammatory bowel disease (IBD) overlap (Crohn’s or ulcerative colitis) — nonsteroidal anti-inflammatory drugs can actively worsen inflammatory bowel disease; a single drug can treat both diseases. See ankylosing spondylitis and inflammatory bowel disease Overlap.
- BASDAI score above 4 (the Bath Ankylosing Spondylitis Disease Activity Index, a validated questionnaire).
- Elevated C-reactive protein (CRP) or erythrocyte sedimentation rate (ESR) despite nonsteroidal anti-inflammatory drugs — systemic inflammation that nonsteroidal anti-inflammatory drugs are failing to suppress.
- Structural damage visible on imaging — magnetic resonance imaging (MRI) showing active sacroiliitis, or plain films showing early syndesmophyte formation.
The reason rheumatologists give for not waiting months on nonsteroidal anti-inflammatory drugs in these situations: time with inflamed vertebrae is time in which fusion that does not reverse can build.
3. The Four Drug Classes in Ankylosing Spondylitis
Four cytokine/pathway-targeted drug classes are relevant to ankylosing spondylitis, and only three of them actually work for the axial (spine) disease:
- Tumor necrosis factor inhibitors (TNFi) — first-line biologic. Block tumor necrosis factor-alpha.
- IL-17 inhibitors (IL-17i) — second-line or first-line with specific comorbidities.
- JAK inhibitors (JAKi) — oral pills; block intracellular signaling. Approved (drug labels) for people who had too little response to, or could not tolerate, one or more TNF inhibitors.
- IL-23 inhibitors — effective in psoriatic arthritis and psoriasis, but not in axial ankylosing spondylitis. Not used for ankylosing spondylitis (see section 7).
4. Tumor Necrosis Factor Inhibitors (TNFi) — First-Line Biologics
Tumor necrosis factor inhibitors are the oldest, best-studied, and usually the first biologic class offered for ankylosing spondylitis. They work in about two-thirds of patients.
Adalimumab
40 mg subcutaneous every 2 weeks. The most prescribed biologic in the world. Self-injected at home as either a pre-filled pen or syringe. Refrigerated shipping, shelf-stable at room temperature for up to 14 days.
Etanercept
50 mg subcutaneous weekly. Self-injected. Etanercept is a soluble tumor necrosis factor receptor fusion protein (slightly different mechanism from the monoclonal antibodies). Important caveat: etanercept is not effective for inflammatory bowel disease, and the 2019 American College of Rheumatology guideline favors TNF-inhibitor monoclonal antibodies over other biologics for people with ankylosing spondylitis plus Crohn’s or UC.
Infliximab
5 mg/kg intravenous (IV) infusion at weeks 0, 2, and 6, then every 6 weeks (the label’s ankylosing spondylitis schedule). Requires an infusion center — roughly a 2-hour appointment each time. No self-injection. The label’s wording on raising the dose (up to 10 mg/kg every 8 weeks, or as often as every 4 weeks) is in its rheumatoid arthritis section, not its ankylosing spondylitis section. Excellent evidence in ankylosing spondylitis + inflammatory bowel disease and ankylosing spondylitis + uveitis.
Certolizumab pegol
400 mg subcutaneous at weeks 0, 2, and 4, then 200 mg every 2 weeks or 400 mg every 4 weeks. Certolizumab is pegylated and lacks the Fc portion of a normal antibody — which means it does not actively cross the placenta. This makes it the safest TNFi in pregnancy. See Pregnancy and ankylosing spondylitis.
Golimumab
50 mg subcutaneous monthly (the injected form), or intravenous 2 mg/kg at weeks 0 and 4, then every 8 weeks (the infusion form). Monthly dosing is a selling point for patients who hate weekly or bi-weekly injections.
Biosimilars for TNFi
Biosimilars are U.S. Food and Drug Administration-approved, near-identical copies of the originator biologic — comparable to generic drugs for small molecules, although the regulatory pathway is different.
- Adalimumab biosimilars: several biosimilars are approved.
- Infliximab biosimilars: several biosimilars are approved.
- Etanercept biosimilars: biosimilars are approved as well.
Biosimilars are often cheaper and have equivalent efficacy in head-to-head studies. Insurance companies may force a switch to whichever biosimilar they contract with this year — this is annoying but usually clinically fine.
TNFi Response and Structural Effects
In the main adalimumab trial (ATLAS, 2006), 45.2% of patients on adalimumab reached a BASDAI 50 response (at least 50% improvement in the disease activity score) at week 12, against 15.9% on placebo. Long-term studies show slower spinal fusion with sustained TNFi use, especially when started before significant syndesmophyte formation.
5. IL-17 Inhibitors (IL-17i) — When TNFi Fails or for Specific Comorbidities
IL-17 is a cytokine central to the spondyloarthritis disease process. Blocking it works well in ankylosing spondylitis and psoriasis, and somewhat less well in inflammatory bowel disease (where it can actually cause trouble).
Secukinumab
150 mg subcutaneous at weeks 0, 1, 2, 3, and 4, then every 4 weeks (or 150 mg every 4 weeks without the loading doses). The label lists 300 mg every 4 weeks for people whose ankylosing spondylitis is still active.
Ixekizumab
160 mg subcutaneous (two 80 mg injections) at week 0, then 80 mg every 4 weeks (the label’s ankylosing spondylitis schedule; the 80 mg doses at weeks 2, 4, 6, 8, 10, and 12 belong to the plaque-psoriasis schedule).
Bimekizumab
Newer. Targets both IL-17A and IL-17F (where secukinumab and ixekizumab only target IL-17A). 160 mg subcutaneous every 4 weeks, with no loading dose, in the label’s ankylosing spondylitis schedule. Early data suggest higher response rates than single-target IL-17i.
When to Prefer IL-17i Over TNFi
- Concurrent plaque psoriasis — IL-17i is more effective for skin clearance than TNFi.
- Prior TNFi failure (primary non-response or secondary loss of response).
- Specific TNFi contraindications — demyelinating disease history, advanced heart failure.
IL-17i CAUTION in Inflammatory Bowel Disease
This is crucial. Secukinumab and ixekizumab can trigger or worsen Crohn’s disease and ulcerative colitis flares. The secukinumab label reports inflammatory bowel disease flares, in some cases serious, in its clinical trials, and the 2019 American College of Rheumatology guideline favors TNF-inhibitor monoclonal antibodies (such as adalimumab or infliximab) over other biologics for people with ankylosing spondylitis plus inflammatory bowel disease. See ankylosing spondylitis and inflammatory bowel disease Overlap.
IL-17i Side Effects
Most characteristic: increased rate of candidiasis (oral thrush, vaginal yeast infections). Also injection site reactions and upper respiratory infections. Typically manageable; in the secukinumab label’s psoriasis trials, candida infections of the skin and mouth occurred in 1.2% of treated people against 0.3% on placebo.
6. JAK Inhibitors (JAKi) — Oral Option
JAK inhibitors are small molecules, not biologics in the strict sense, but they occupy the same therapeutic niche and are often grouped with biologics in clinical conversation.
Tofacitinib
5 mg twice daily. U.S. Food and Drug Administration (FDA) approved for ankylosing spondylitis in 2021.
Upadacitinib
15 mg once daily. U.S. Food and Drug Administration approved for ankylosing spondylitis. Many rheumatologists prefer upadacitinib for its once-daily dosing and slightly more selective JAK1 inhibition.
Advantages of JAKi
- Oral — no injections, no infusion center.
- Faster onset — some patients feel improvement within 1–2 weeks.
- No need for refrigeration or sharps disposal.
Disadvantages of JAKi
The U.S. Food and Drug Administration has placed a boxed warning on all oral JAKi for serious infections (including tuberculosis), mortality (death), malignancy, MACE (major adverse cardiovascular events), and thrombosis. The warning is based on the ORAL-SURVEILLANCE trial, which was conducted in rheumatoid arthritis patients over age 50 with at least one cardiovascular risk factor. Whether the same risk applies to younger ankylosing spondylitis patients is debated, but the warning stands.
A baseline cardiovascular risk assessment is done before starting a JAKi. Both labels approve them for adults with ankylosing spondylitis who had too little response to, or could not tolerate, one or more TNF inhibitors; the labels set no IL-17-inhibitor step. They are also an option for people who cannot do injections.
Cost and Monitoring
JAKi require quarterly lab monitoring: complete blood count (CBC), LFTs, and lipid panel. JAK inhibitors reliably raise low-density lipoprotein (LDL) cholesterol and occasionally suppress neutrophil or lymphocyte counts.
7. IL-23 Inhibitors — Currently NOT Effective for Ankylosing Spondylitis
Ustekinumab blocks IL-12 and IL-23, and risankizumab blocks IL-23, a cytokine upstream of IL-17 in the inflammatory cascade. They work beautifully in psoriasis and, to a lesser degree, peripheral psoriatic arthritis. Randomized trials in ankylosing spondylitis showed no efficacy for axial disease. This was a genuine surprise to the field given the mechanistic logic.
The 2019 American College of Rheumatology guideline states that treatment with ustekinumab (like rituximab, abatacept, or interleukin-6 inhibitors) is not recommended in ankylosing spondylitis, even when TNF inhibitors cannot be used, due to lack of effectiveness. These drugs are used for psoriatic arthritis with peripheral joint disease, not axial spondyloarthritis.
8. Picking Your Biologic — Decision Matrix
How other conditions (comorbidities) shape the choice of drug:
- Ankylosing spondylitis + inflammatory bowel disease (Crohn’s or UC): Adalimumab or infliximab — both treat both diseases. The 2019 American College of Rheumatology guideline does not recommend secukinumab or ixekizumab here, and etanercept does not treat inflammatory bowel disease.
- Ankylosing spondylitis + severe psoriasis: IL-17i (secukinumab, ixekizumab, bimekizumab) — superior skin clearance.
- Ankylosing spondylitis + recurrent uveitis: Adalimumab or infliximab have the best evidence; certolizumab is also effective. The 2019 American College of Rheumatology guideline prefers adalimumab or infliximab over etanercept (less effective for uveitis).
- Ankylosing spondylitis + pregnancy planning: Certolizumab — doesn’t cross the placenta.
- Ankylosing spondylitis + reluctance to inject: JAK inhibitor (tofacitinib or upadacitinib) — oral.
- Ankylosing spondylitis + prior TNFi failure: IL-17i or JAKi.
- First-line, no comorbidities: Any TNFi — the choice usually comes down to dosing frequency, patient preference, and insurance formulary.
9. Cost and Insurance Reality
These drugs are expensive.
- TNFi retail list prices: $4,000–$7,000 per month.
- IL-17i: $5,000–$10,000 per month.
- JAKi: $4,000–$6,000 per month.
- Biosimilars: 20–50% cheaper than the originator.
Insurance coverage is usually available with prior authorization. The PA packet typically requires: documented nonsteroidal anti-inflammatory drug failure (2+ nonsteroidal anti-inflammatory drugs for 2–4 weeks each), a BASDAI score, C-reactive protein or erythrocyte sedimentation rate results, and in some cases imaging. Many rheumatology offices have a PA coordinator who prepares this packet.
Manufacturer copay assistance programs dramatically reduce out-of-pocket costs for commercially-insured patients:
- The makers of most of the drugs on this page run their own manufacturer co-pay and support programs.
- Most bring the copay down to $5–$10 per month for eligible patients.
- Medicare and Medicaid patients are usually not eligible (federal anti-kickback rules).
Patient assistance programs provide free drug to uninsured patients meeting income criteria — typically up to 400–500% of the federal poverty level. Applications go directly through the manufacturer.
Specialty pharmacy is required for most biologics — a few large national specialty pharmacies fill most of them. Retail pharmacies generally cannot fill these drugs. Expect monthly phone calls to confirm each shipment.
Switching biologics: insurance often enforces step therapy — a cheaper TNFi has to fail first before the plan will pay for an IL-17i or JAKi. Carefully documented failures make appeals go more smoothly.
10. How to Give Yourself an Injection
If you have never given yourself a shot, the first one is nerve-wracking. After three or four, it’s boring. Points that injection nurses commonly teach:
- Warming the pen to room temperature before injecting (the adalimumab label: 15 to 30 minutes out of the refrigerator). Cold drug stings badly; room-temperature drug is nearly painless.
- Rotating sites — front of thigh, abdomen (staying 2 inches away from the navel), or upper outer arm. Rotating prevents lipohypertrophy (fatty lumps under the skin) and bruising.
- Pinching up a fold of skin, inserting at 90 degrees, and holding the pen or syringe for the full 10 seconds (or whatever the device manual specifies) to deliver the complete dose.
- Icing the site afterward for 1–2 minutes to reduce bruising.
- Doing the first injection in clinic, with a nurse walking through it. Drug makers run free nurse-educator programs.
- Disposal in a sharps container, which the pharmacy provides free; used pens are not put in the regular trash.
11. What to Expect — Timeline of Response
- Weeks 1–4: Many patients notice morning stiffness improving first. Fatigue may lift.
- Weeks 4–12: BASDAI score drops, C-reactive protein normalizes, functional capacity improves.
- Full response: 12–16 weeks is the standard window to judge response; week 6 is too early to judge.
- Non-responders at 16 weeks: the usual next step is a switch of drug class (or to a different drug within the class, if there are logistical or side-effect reasons).
- Secondary loss of response: occurs in 20–30% of TNFi users over 2–3 years, often due to anti-drug antibody formation. Switching within the class (e.g., adalimumab to certolizumab) or to a different class (TNFi to IL-17i) typically recaptures response.
12. Side Effects — What to Watch
Common and usually manageable:
- Injection site reactions (redness, itching, bruising).
- Upper respiratory tract infections.
- Mild fatigue the day of injection.
Boxed warning: every TNF-inhibitor label (adalimumab, etanercept, infliximab, certolizumab, golimumab) carries a boxed warning for serious infections that can lead to hospitalization or death, including tuberculosis (TB), bacterial sepsis and invasive fungal infections, and for malignancy — lymphoma and other cancers, some fatal, have been reported in children and teenagers treated with TNF blockers.
Serious but rare:
- Reactivation of latent tuberculosis — screening before starting uses an interferon-gamma release assay blood test for TB, with a chest X-ray added if it is positive or risk factors are present.
- Hepatitis B reactivation — screening checks HBsAg, anti-HBc, anti-HBs.
- Drug-induced lupus — rare, seen with TNFi; typically resolves on stopping the drug.
- Heart failure worsening — the labels report worsening and new-onset congestive heart failure with TNF blockers, and the 2019 American College of Rheumatology guideline treats heart failure as a contraindication to TNFi (secukinumab or ixekizumab is preferred then).
- Demyelinating disease — the labels report rare new or worsened demyelinating disease, including multiple sclerosis and optic neuritis, with TNF blockers, and the 2019 American College of Rheumatology guideline treats demyelinating disease as a contraindication to TNFi.
Cancer risk: TNFi use is associated with a slightly increased risk of lymphoma — roughly a doubling of baseline risk, but because baseline risk is very low the absolute numbers remain small. Non-melanoma skin cancers are more common; annual skin checks are the usual practice.
Vaccines:
- Live vaccines are contraindicated during biologic therapy (the adalimumab label allows other vaccinations “except for live vaccines”) — these include MMR, varicella (chickenpox), yellow fever, and the nasal-spray live flu vaccine.
- Killed and inactivated vaccines can be given — annual injected flu shot, pneumococcal (PCV20 or PCV15 + PPSV23), the recombinant shingles vaccine, Tdap, and any of the non-live respiratory vaccines.
13. Pre-Treatment Screening Checklist
Screening usually done before the first dose:
- Tuberculosis (TB) screening — an interferon-gamma release assay blood test; chest X-ray if the test is positive or risk factors suggest it.
- Hepatitis B serology (HBsAg, anti-HBc, anti-HBs) and hepatitis C antibody.
- Human immunodeficiency virus (HIV) screening if any risk factors.
- Baseline labs — CBC, CMP, ESR, C-reactive protein.
- Pregnancy test for women of childbearing age.
- Vaccines brought up to date before starting — pneumococcal, the recombinant shingles vaccine, annual flu, Tdap if due. Live vaccines are given at least 4 weeks before the first biologic dose.
- Dental exam — active infections treated first. Dental abscesses during biologic therapy are dangerous.
- Malignancy screen appropriate for age (mammogram, colonoscopy, skin exam, Pap smear) — particularly if over 50 or with family history.
14. Monitoring During Treatment
- Labs: CBC, CMP, ESR/C-reactive protein every 3–6 months. LFTs and lipid panel quarterly on JAKi.
- BASDAI scoring every rheumatology visit to track response trend.
- Magnetic resonance imaging of SI joints or spine: not routinely repeated, but useful if response is in question or to document structural stability over years.
- Annual skin check for non-melanoma skin cancer.
- Annual flu shot (injected, not the nasal-spray live vaccine); updated COVID-19 vaccines per current U.S. Centers for Disease Control and Prevention (CDC) guidance.
15. Stopping or Switching
The 2019 American College of Rheumatology guideline recommends against stopping a biologic in people whose disease is stable; the observational studies it cites found relapses in 60–74% of patients after a TNF inhibitor was stopped, sometimes within a few weeks to months. Biologics can be paused for surgery — typically one dosing interval before and held until wounds are healed, often 1–2 weeks post-op — with low risk of losing response. Longer pauses (months) can cause loss of response that may require re-titration or a switch.
Switching within a class is common and often works: adalimumab to certolizumab, secukinumab to ixekizumab. Switching across classes (TNFi to IL-17i, IL-17i to JAKi) is the standard move after primary or secondary failure.
16. Combining Biologics with Other Drugs
- Nonsteroidal anti-inflammatory drugs — compatible with biologics and frequently continued. They handle breakthrough stiffness the biologic hasn’t fully quelled.
- DMARDs — methotrexate is rarely added to ankylosing spondylitis biologic therapy because it does not help axial disease, although it can be useful for concurrent peripheral arthritis. Sulfasalazine can help peripheral arthritis and in some cases inflammatory bowel disease overlap. Neither does much for the spine.
- Corticosteroids — short courses (oral prednisone 10–20 mg tapers, or intra-articular injections) are used for acute flares. The 2019 American College of Rheumatology guideline strongly recommends against treatment with systemic glucocorticoids (steroids taken by mouth or injected to act on the whole body) in active ankylosing spondylitis; long-term systemic steroids don’t meaningfully help axial disease and they accelerate osteoporosis, a major concern in this population.
For non-pharmacologic adjuncts, see Exercise and PT Protocol — exercise remains foundational no matter which biologic you’re on.
Key Research Papers
- van der Heijde D, et al. 2016 update of the ASAS-EULAR management recommendations for axial spondyloarthritis. Annals of the Rheumatic Diseases. 2017. — doi:10.1136/annrheumdis-2016-210770
- Ward MM, et al. 2019 Update of the ACR/SAA/SPARTAN recommendations for the treatment of axial spondyloarthritis. Arthritis & Rheumatology. 2019. — doi:10.1002/art.41042
- Baeten D, et al. Secukinumab, an interleukin-17A inhibitor, in ankylosing spondylitis (MEASURE 1 and MEASURE 2). New England Journal of Medicine. 2015. — doi:10.1056/NEJMoa1505066
- van der Heijde D, et al. Ixekizumab, an interleukin-17A antagonist in radiographic axial spondyloarthritis (COAST-V). Lancet. 2018. — doi:10.1016/S0140-6736(18)31946-9
- van der Heijde D, Kivitz A, Schiff MH, et al. (2006). Efficacy and safety of adalimumab in patients with ankylosing spondylitis: results of a multicenter, randomized, double-blind, placebo-controlled trial. Arthritis and Rheumatism — PubMed PMID: 16802350
PubMed Topic Searches
Curated PubMed topic searches — each link opens a live query so you always see the most recent literature.
- PubMed: Ankylosing spondylitis biologic therapy
- PubMed: TNF inhibitor ankylosing spondylitis
- PubMed: Secukinumab ankylosing spondylitis
- PubMed: Ixekizumab axial spondyloarthritis
- PubMed: Tofacitinib ankylosing spondylitis
- PubMed: Upadacitinib ankylosing spondylitis
- PubMed: Biosimilar spondyloarthritis
Connections
- Rheumatology
- Ankylosing Spondylitis
- Human Leukocyte Antigen-B27 Explained
- Ankylosing Spondylitis and Inflammatory Bowel Disease Overlap
- Exercise and PT Protocol
- Nonsteroidal Anti-Inflammatory Drug Strategy
- Morning Stiffness Management
- Starch-Free Diet and Ebringer
- Pregnancy and Ankylosing Spondylitis
- Uveitis and Eye Involvement
- Arthritis
- Psoriasis
- Crohn's Disease
- Ulcerative Colitis
- Inflammatory Markers