Ankylosing Spondylitis (AS) and Inflammatory Bowel Disease (IBD) Overlap: Crohn's, UC, and the Shared Biology
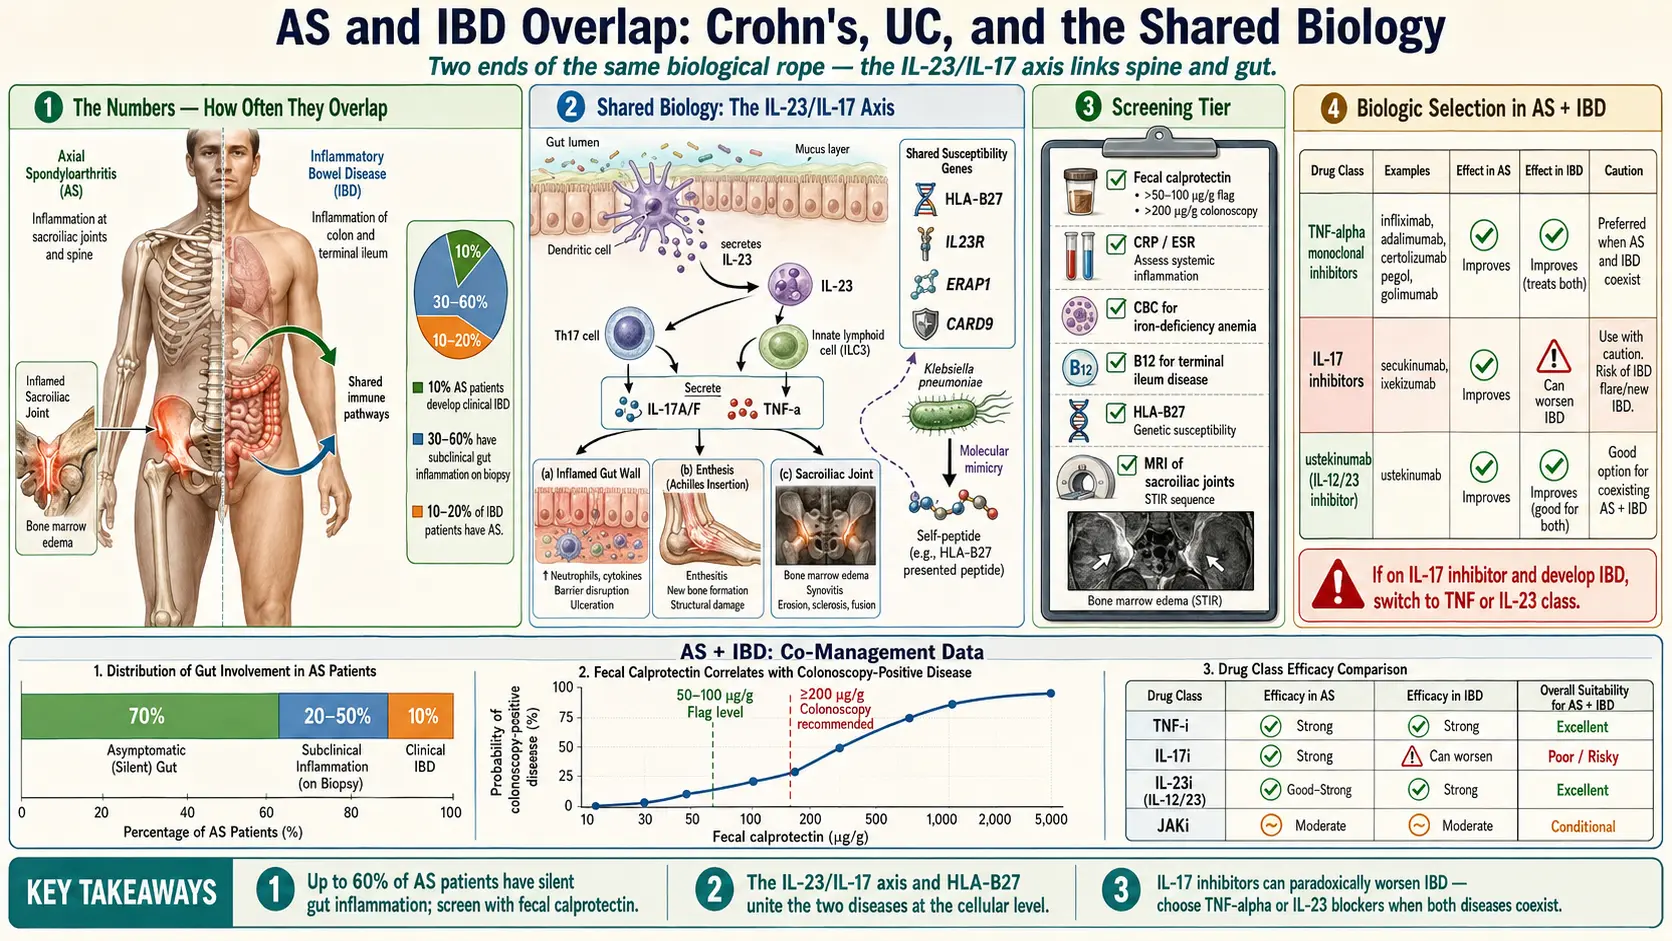
Table of Contents
- The Numbers — How Often They Overlap
- Why They Cluster — The Shared Biology
- Symptoms of Inflammatory Bowel Disease to Watch For if You Have Ankylosing Spondylitis
- Screening Ankylosing Spondylitis Patients for Occult Inflammatory Bowel Disease
- Symptoms of Ankylosing Spondylitis to Watch For if You Have Inflammatory Bowel Disease
- Screening Inflammatory Bowel Disease Patients for Ankylosing Spondylitis
- How Inflammatory Bowel Disease Overlap Changes Biologic Selection
- The “Best Single Drug” Question for Ankylosing Spondylitis + Inflammatory Bowel Disease
- When Inflammatory Bowel Disease Develops on an IL-17 Inhibitor
- Gut-Directed Approaches That Help Both
- Nonsteroidal Anti-Inflammatory Drugs in Ankylosing Spondylitis + Inflammatory Bowel Disease — The Conflict
- Monitoring Co-Managed Disease
- Other Extraintestinal Manifestations Connecting Ankylosing Spondylitis and Inflammatory Bowel Disease
- Pregnancy and Ankylosing Spondylitis+Inflammatory Bowel Disease Overlap
- Key Research Papers
- Connections
- Featured Videos
1. The Numbers — How Often They Overlap
If you have ankylosing spondylitis (AS) and you’ve noticed you also run to the bathroom more than your friends, you’re not imagining it. Ankylosing spondylitis and inflammatory bowel disease (IBD) — Crohn’s disease and ulcerative colitis — are two ends of the same biological rope.
Roughly 10% of ankylosing spondylitis patients develop clinical inflammatory bowel disease over their lifetime, with Crohn’s being more common than ulcerative colitis. A UK study of 4,101 people with ankylosing spondylitis found that 3.7% already had inflammatory bowel disease when ankylosing spondylitis was diagnosed and that the 20-year cumulative incidence was 7.5% for inflammatory bowel disease (24.5% for acute anterior uveitis); the risk of inflammatory bowel disease was 3.3 times that of matched controls and highest in the first years after diagnosis. That number climbs dramatically when you look under the microscope: 30–60% of ankylosing spondylitis patients have subclinical gut inflammation visible on colonoscopy with biopsy, even when they have no gastrointestinal (GI) symptoms at all. In a Belgian cohort of 65 people with spondyloarthritis who had ileocolonoscopy, 46.2% had microscopic gut inflammation; in axial disease it was linked to male sex, high disease activity, restricted spinal mobility and younger age. The bowel is inflamed; the patient just doesn’t feel it yet.
The traffic runs both ways. 10–20% of inflammatory bowel disease patients have ankylosing spondylitis or another form of spondyloarthritis, and inflammatory back pain is the single most common extraintestinal manifestation of inflammatory bowel disease. Both conditions cluster in families that carry human leukocyte antigen-B27, and both live inside the same IL-23/IL-17 cytokine pathway. When you treat one, you are often — whether you know it or not — treating the other.
2. Why They Cluster — The Shared Biology
The IL-23/IL-17 Axis
The dominant unifying theme is the IL-23/IL-17 axis. IL-23 is produced by dendritic cells and macrophages at mucosal surfaces — the gut especially — and it drives a population of T cells and innate lymphoid cells to release IL-17 and tumor necrosis factor-α. Those cytokines inflame the gut wall, the entheses (where tendon meets bone), and the sacroiliac joints. The same inflammatory cocktail, in different tissues.
Gut Dysbiosis
The intestinal microbiome of ankylosing spondylitis patients looks abnormal in the same way inflammatory bowel disease microbiomes look abnormal: reduced diversity, expansion of pro-inflammatory species, loss of butyrate-producing commensals. Whether dysbiosis causes the disease or is caused by it is still argued, but the overlap in microbial signatures is striking.
Intestinal Permeability
Both ankylosing spondylitis and inflammatory bowel disease patients show increased intestinal permeability — the so-called “leaky gut.” Bacterial lipopolysaccharide and peptidoglycan fragments cross the gut wall and enter systemic circulation, where they can trigger inflammation at distant sites, including the spine.
Shared Genetics
Several susceptibility genes are shared: human leukocyte antigen-B27, IL23R, ERAP1, CARD9, STAT3, and others. These genes sit inside the innate immune response and antigen processing pipeline — the exact machinery that decides when to treat a gut bacterium as a threat.
Molecular Mimicry
Some of the most durable hypotheses invoke molecular mimicry. Peptides from gut bacteria — notably Klebsiella pneumoniae and certain E. coli strains — bear structural similarity to self-peptides that human leukocyte antigen-B27 presents, creating a crossfire where an anti-bacterial immune response ends up attacking joint and gut tissue. See Starch-Free Diet and the Ebringer Hypothesis and human leukocyte antigen-B27 Explained for the mechanistic detail.
3. Symptoms of Inflammatory Bowel Disease to Watch For if You Have Ankylosing Spondylitis
If you have ankylosing spondylitis, your inflammation doesn’t only live in your spine. These signs point to possible inflammatory bowel disease and are common reasons for a gastrointestinal referral:
- Chronic diarrhea lasting more than four weeks, especially if accompanied by blood or mucus.
- Abdominal cramping, particularly if it worsens after meals.
- Unintentional weight loss — not a crash diet, just pounds drifting off.
- Night sweats, fatigue, and low-grade fever, which point to systemic inflammation.
- Perianal disease — fissures, fistulas, or abscesses. These strongly suggest Crohn’s disease, and clinicians treat them as reasons for same-week gastrointestinal evaluation.
- Iron-deficiency anemia or persistently low ferritin on your ankylosing spondylitis blood panels.
- Elevated fecal calprotectin above 50–100 μg/g, a direct marker of bowel inflammation.
4. Screening Ankylosing Spondylitis Patients for Occult Inflammatory Bowel Disease
Because subclinical gut inflammation is so common, a reasonable screening tier looks like this:
- Fecal calprotectin — the single most useful stool test. Inexpensive, non-invasive, and correlates tightly with colonic inflammation.
- Complete blood count (CBC) — low iron, low ferritin, and elevated platelets form a classic inflammation fingerprint.
- C-reactive protein (CRP) and erythrocyte sedimentation rate (ESR) — if these run persistently higher than your ankylosing spondylitis activity would predict, occult gut inflammation is a leading suspect.
- B12 deficiency — points to terminal ileum disease, a Crohn’s hallmark.
- Colonoscopy with ileoscopy — definitive, indicated if you have gastrointestinal symptoms or a fecal calprotectin above roughly 200 μg/g. Ileal intubation and random biopsies matter, since microscopic disease may be invisible to the naked eye.
Abnormal results are the usual point at which a gastroenterologist becomes involved. The Crohn’s Disease page covers the full workup pathway.
5. Symptoms of Ankylosing Spondylitis to Watch For if You Have Inflammatory Bowel Disease
If you already carry an inflammatory bowel disease diagnosis and you start noticing back pain, it is not necessarily a desk-chair problem. Inflammatory back pain has a fingerprint:
- Chronic inflammatory back pain — insidious onset, lasting more than three months, typically starting before age 40.
- Morning stiffness lasting more than 30 minutes, and often two hours or more.
- Pain that improves with exercise and NOT with rest — the opposite of a mechanical back problem.
- Night pain waking you in the second half of the night, relieved only by getting up and moving.
- Alternating buttock pain — a classic signature of sacroiliac joint involvement.
- Enthesitis — heel pain (Achilles), plantar fascia pain, chest wall tenderness.
- Dactylitis — “sausage digit” swelling of a whole finger or toe (more characteristic of psoriatic spondyloarthritis).
- Peripheral arthritis, usually in larger joints and asymmetric.
6. Screening Inflammatory Bowel Disease Patients for Ankylosing Spondylitis
The screening workup for ankylosing spondylitis in inflammatory bowel disease patients is relatively simple and high-yield:
- Clinical exam for spinal range of motion, Schober’s test, SI joint tenderness, and enthesitis at the Achilles, plantar fascia, and costochondral junctions.
- Human leukocyte antigen-B27 testing if inflammatory back pain is present or there’s a family history of spondyloarthritis, psoriasis, or uveitis.
- Magnetic resonance imaging (MRI) of the SI joints if inflammatory back pain is present. Magnetic resonance imaging is far more sensitive than plain X-ray for early disease and can show bone marrow edema before structural damage appears.
- Pelvis X-ray for established sacroiliitis if disease has been present for years.
- Referral to rheumatology with any positive finding. Early biologic therapy can halt structural progression.
7. How Inflammatory Bowel Disease Overlap Changes Biologic Selection
This is where the overlap matters most practically. A biologic that is a home run for axial ankylosing spondylitis can be a disaster for inflammatory bowel disease — and vice versa. Get this decision wrong and you can trigger a flare in the organ you weren’t even targeting.
Drugs That Treat BOTH Axial Ankylosing Spondylitis and Inflammatory Bowel Disease
- Adalimumab — U.S. Food and Drug Administration-approved for both ankylosing spondylitis and inflammatory bowel disease; monoclonal anti-TNF.
- Infliximab — U.S. Food and Drug Administration-approved for both; monoclonal anti-TNF given by infusion.
- Certolizumab pegol — approved for Crohn’s disease and ankylosing spondylitis; pegylated anti-TNF with no Fc region (relevant in pregnancy).
- Golimumab — approved for ulcerative colitis and ankylosing spondylitis.
- Upadacitinib — a Janus kinase (JAK) inhibitor taken as a pill rather than a biologic. Its U.S. Food and Drug Administration label lists active ankylosing spondylitis, non-radiographic axial spondyloarthritis with objective signs of inflammation, ulcerative colitis and Crohn’s disease, each in adults who had an inadequate response or intolerance to one or more TNF blockers. The label carries a boxed warning for serious infections, mortality, malignancy, major adverse cardiovascular events and thrombosis.
Drugs That Treat Ankylosing Spondylitis but Do NOT Treat (and May Worsen) Inflammatory Bowel Disease
- Etanercept — a soluble tumor necrosis factor (TNF) receptor fusion protein. Works for ankylosing spondylitis but does NOT treat inflammatory bowel disease because of its different tumor necrosis factor-binding mechanism. It usually doesn’t worsen inflammatory bowel disease, but it offers no protection either, so it leaves the gut side untreated when overlap exists.
- Secukinumab — IL-17A inhibitor. Can trigger or worsen inflammatory bowel disease flares; in its one placebo-controlled trial in Crohn’s disease it was ineffective and caused more adverse events (see Emerging Options below).
- Ixekizumab — same IL-17A class; same caution.
- Bimekizumab — IL-17A/F dual inhibitor; similar caution.
Drugs That Treat Inflammatory Bowel Disease but Not Axial Ankylosing Spondylitis
- Vedolizumab — gut-selective integrin blocker. Highly effective for inflammatory bowel disease but offers no axial ankylosing spondylitis benefit. Sometimes used for peripheral joint disease.
- Ustekinumab — IL-12/23 inhibitor. Effective for Crohn’s and ulcerative colitis, with modest benefit for peripheral joint disease but little to no axial ankylosing spondylitis benefit.
Emerging Options
Risankizumab and guselkumab are IL-23 selective inhibitors, effective for inflammatory bowel disease and psoriatic arthritis. In the spine they have not shown benefit: a 2018 placebo-controlled phase 2 trial of risankizumab in 159 people with active ankylosing spondylitis failed its main goal — at week 12, 15.0% on the 180 mg dose reached the ASAS40 response vs 17.5% on placebo — and showed no evidence of clinically meaningful improvement; the authors suggested IL-23 may not be a relevant driver of ankylosing spondylitis.
The gut side shows the mirror image. In a 2012 trial in 59 people with moderate-to-severe Crohn’s disease, the IL-17A blocker secukinumab was ineffective (the authors called the results “unexpected”): Crohn’s activity scores favoured placebo, and 20 infections occurred on secukinumab vs none on placebo. Together these trials explain why IL-23 drugs help the gut but not the spine, while IL-17 drugs help the spine but not the gut, and why the TNF-blocking antibodies above remain the drugs that cover both.
See the Biologics Guide for dosing, safety monitoring, and how to sequence agents.
8. The “Best Single Drug” Question for Ankylosing Spondylitis + Inflammatory Bowel Disease
For most patients with overlapping ankylosing spondylitis and inflammatory bowel disease, the answer is simple: adalimumab or infliximab. Both have decades of prospective trial and registry data in both conditions, and both are genuinely effective at controlling axial, peripheral, and intestinal disease.
Choosing between them is mostly a lifestyle call. Infliximab is loaded and maintained by infusion every 6–8 weeks in an infusion center, which suits severe or difficult-to-control inflammatory bowel disease (the dose can be escalated and the interval shortened quickly). Adalimumab is a self-administered subcutaneous injection every 2 weeks, more convenient for stable disease and for patients who dislike infusion chairs.
Biosimilars are now available for both drugs and are often the insurance-preferred option, typically at a fraction of the branded price with equivalent efficacy.
9. When Inflammatory Bowel Disease Develops on an IL-17 Inhibitor
This is a scenario rheumatologists see more often as IL-17 agents become popular. A patient on secukinumab or ixekizumab for ankylosing spondylitis starts passing bloody stools and is diagnosed with new-onset inflammatory bowel disease. What now?
Rheumatologists typically stop the IL-17 inhibitor and switch to a tumor necrosis factor-α inhibitor (most commonly adalimumab or infliximab). IL-17 inhibition-triggered inflammatory bowel disease often reverses once the drug is stopped, especially if caught early. A gastroenterologist usually manages induction therapy — sometimes a short course of steroids is used to quiet the flare while the new biologic takes effect.
10. Gut-Directed Approaches That Help Both
Non-pharmacologic interventions that target the gut have plausible dual benefit:
- Low-FODMAP diet — well-established for irritable bowel syndrome-overlap symptoms and sometimes helpful with post-IBD functional pain. See Low-FODMAP Diet for the structured elimination and reintroduction phases.
- Starch-free / low-starch diet (Ebringer protocol) — theoretical benefit for both conditions by starving Klebsiella pneumoniae in the bowel. See Starch-Free Diet and Ebringer.
- Exclusive enteral nutrition (EEN) — strong evidence in pediatric Crohn’s induction. Theoretical ankylosing spondylitis benefit is unproven but plausible given the gut-joint axis.
- Fecal microbiota transplant (FMT) — experimental for both diseases, with some encouraging small-trial data in UC.
- Probiotics — a multi-strain probiotic has modest evidence in ulcerative colitis and pouchitis; evidence in ankylosing spondylitis is mixed but the side-effect profile is benign.
11. Nonsteroidal Anti-Inflammatory Drugs in Ankylosing Spondylitis + Inflammatory Bowel Disease — The Conflict
Nonsteroidal anti-inflammatory drugs (NSAIDs) are first-line pain control in ankylosing spondylitis, and for good reason — they work, and they may even slow radiographic progression when taken continuously. But they can worsen inflammatory bowel disease flares and cause mucosal ulceration, creating a direct conflict in overlap patients.
How clinicians commonly handle the conflict:
- Celecoxib (cyclooxygenase-2 (COX-2) selective) is the least gut-toxic option and is the one clinicians generally prefer when nonsteroidal anti-inflammatory drugs are unavoidable.
- If inflammatory bowel disease is active, nonsteroidal anti-inflammatory drugs are commonly minimized or stopped entirely, with the biologic carrying the joint inflammation and acetaminophen used for pain bridging.
- When inflammatory bowel disease is in deep remission, low-dose intermittent celecoxib with gastrointestinal-protective co-therapy (e.g., a proton pump inhibitor (PPI) if indicated for other reasons) is often tolerated.
See nonsteroidal anti-inflammatory drug (NSAID) Strategy for the full risk-benefit framework.
12. Monitoring Co-Managed Disease
If you have both conditions, the ideal setup is a rheumatologist and a gastroenterologist who share notes. Typically a single biologic is prescribed and monitored by the rheumatologist while the gastroenterologist tracks disease activity from the inflammatory bowel disease side.
- Quarterly visits alternating between specialists for the first year, then annually once stable.
- Labs every 3–6 months: complete blood count, C-reactive protein, fecal calprotectin, LFTs, and a biologic-specific safety panel (e.g., TB screen annually on anti-TNF).
- Imaging: magnetic resonance imaging of SI joints or spine as clinically indicated (often annually early, then less frequent once stable); colonoscopy per inflammatory bowel disease surveillance guidelines, usually every 1–3 years depending on disease extent and dysplasia history.
- Extraintestinal flares tracked: iritis / anterior uveitis, pyoderma gangrenosum, erythema nodosum, and primary sclerosing cholangitis (PSC).
13. Other Extraintestinal Manifestations Connecting Ankylosing Spondylitis and Inflammatory Bowel Disease
Both diseases share a portfolio of extraintestinal manifestations that can precede, accompany, or follow the index diagnosis:
- Anterior uveitis (eye inflammation) — affects 30–40% of ankylosing spondylitis patients over their lifetime and is even more common when inflammatory bowel disease overlap is present. Red, painful, photophobic eye — a sign eye clinics treat as a same-day emergency.
- Psoriasis — a subset of overlap patients develop plaque or inverse psoriasis, reflecting the common IL-23/IL-17 axis.
- Primary sclerosing cholangitis (PSC) — more tightly associated with ulcerative colitis; can present with elevated alkaline phosphatase and pruritus.
- Osteoporosis — both diseases reduce bone density, and any history of systemic steroid use compounds the risk. DXA scanning is appropriate for most overlap patients.
14. Pregnancy and Ankylosing Spondylitis+Inflammatory Bowel Disease Overlap
Biologic choice becomes even more critical in pregnancy. Certolizumab pegol is the preferred agent for patients trying to conceive or already pregnant because its lack of an Fc region means minimal placental transfer to the fetus. Adalimumab and infliximab are also considered compatible through much of pregnancy but are typically timed carefully in the third trimester.
Disease activity tends to improve during the first trimester (pregnancy’s natural immunomodulation) but flares are common postpartum, so close follow-up and early re-dosing of the biologic after delivery are usual. See Pregnancy and ankylosing spondylitis for the full roadmap.
Key Research Papers
- Van Praet L, Van den Bosch FE, Jacques P, et al. Microscopic gut inflammation in axial spondyloarthritis: a multiparametric predictive model. Ann Rheum Dis. 2013;72(3):414–417. — PubMed PMID: 23139267
- Ward MM, et al. 2019 Update of the ACR/SAA/SPARTAN Recommendations for the Treatment of Axial Spondyloarthritis. Arthritis & Rheumatology. 2019. — doi:10.1002/art.41042
- Harbord M, Annese V, Vavricka SR, et al. The First European Evidence-based Consensus on Extra-intestinal Manifestations in Inflammatory Bowel Disease. Journal of Crohn’s and Colitis. 2016;10(3):239–254. — doi:10.1093/ecco-jcc/jjv213
- Hueber W, et al. Secukinumab, a human anti-IL-17A monoclonal antibody, for moderate to severe Crohn’s disease: unexpected results of a randomised, double-blind placebo-controlled trial. Gut. 2012;61(12):1693–1700. — doi:10.1136/gutjnl-2011-301668 (demonstrates IL-17 inhibitor harm in IBD)
- Baeten D, Østergaard M, Wei JC, et al. Risankizumab, an IL-23 inhibitor, for ankylosing spondylitis: results of a randomised, double-blind, placebo-controlled, proof-of-concept, dose-finding phase 2 study. Ann Rheum Dis. 2018;77(9):1295–1302. — PubMed PMID: 29945918
- Stolwijk C, Essers I, van Tubergen A, et al. The epidemiology of extra-articular manifestations in ankylosing spondylitis: a population-based matched cohort study. Ann Rheum Dis. 2015;74(7):1373–1378. — PubMed PMID: 24658834
PubMed Topic Searches
Curated PubMed topic searches for ankylosing spondylitis and inflammatory bowel disease overlap. Each link opens a live PubMed query so you always see the most current studies.
- PubMed: Ankylosing spondylitis and inflammatory bowel disease
- PubMed: Spondyloarthritis and subclinical gut inflammation
- PubMed: IL-17 inhibitors and Crohn’s disease
- PubMed: Anti-TNF in AS and Crohn’s
- PubMed: Fecal calprotectin in spondyloarthritis
- PubMed: HLA-B27 and inflammatory bowel disease
- PubMed: Gut-joint axis in spondyloarthritis
- PubMed: Vedolizumab and spondyloarthritis
Connections
- Rheumatology
- Ankylosing Spondylitis
- Human Leukocyte Antigen-B27 Explained
- Biologics Guide
- Exercise and PT Protocol
- Nonsteroidal Anti-Inflammatory Drug Strategy
- Morning Stiffness Management
- Starch-Free Diet and Ebringer
- Pregnancy and Ankylosing Spondylitis
- Uveitis and Eye Involvement
- Crohn's Disease
- Ulcerative Colitis
- Inflammatory Bowel Disease
- Inflammatory Bowel Disease Extraintestinal Manifestations
- Inflammatory Bowel Disease Biologics Guide
- JAK Inhibitors and S1P Modulators
- Small Intestinal Bacterial Overgrowth
- Inflammatory Markers
- Crohn's Disease vs Ulcerative Colitis